
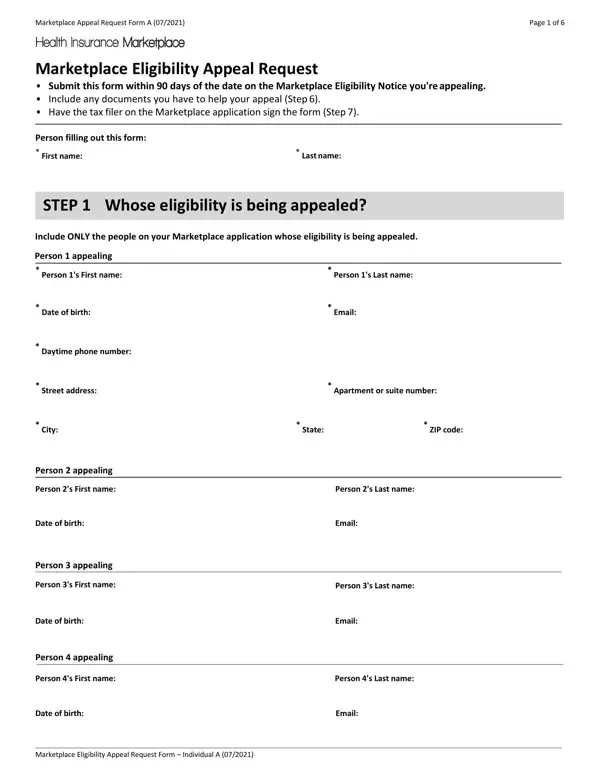
Marketplace Appeal Request Form A (CMS-12153) at a glance
What it is: Marketplace Appeal Request Form A is the Marketplace Eligibility Appeal Request.
Who signs: Signature of the tax filer listed on your Marketplace application (even if they're not appealing).
A filled-in Marketplace Appeal Request Form A (CMS-12153) example: an appeal of the amount of financial help

How to fill out Marketplace Appeal Request Form A (CMS-12153), box by box
Person filling out this form

Under Person filling out this form, enter First name and Last name.
Whose eligibility is being appealed?
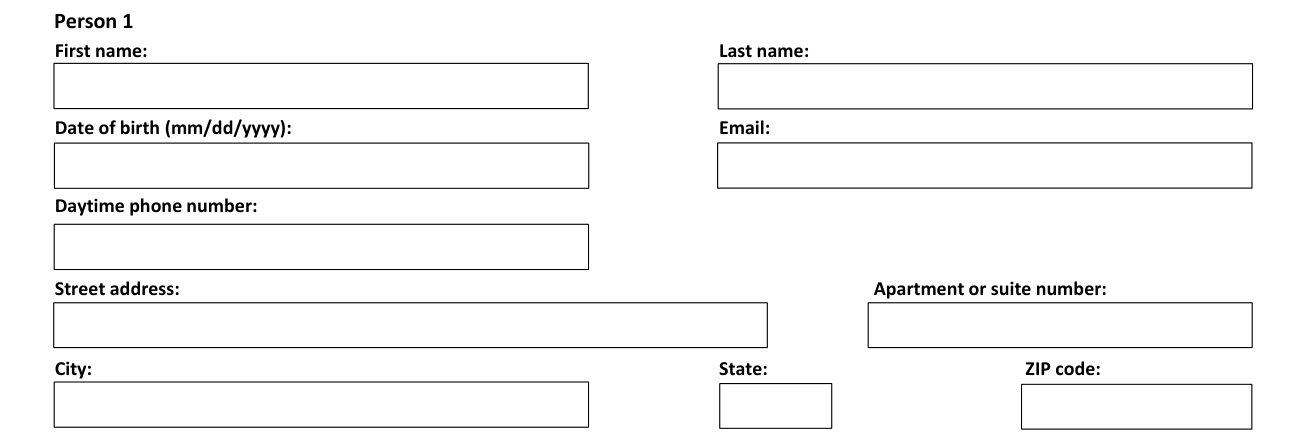
Only include the people on your Health Insurance Marketplace application whose eligibility is being appealed.
For Person 1, enter First name, Last name, Date of birth (mm/dd/yyyy), Email and Daytime phone number.
For Person 1, enter Street address, Apartment or suite number, City, State and ZIP code.
Reason for the appeal

Enter the Application ID # found on the first page of the Marketplace Eligibility Notice, and the Notice Date (mm/dd/yyyy).
What Marketplace decision(s) are you appealing? Select all that apply.
The Marketplace said I'm not eligible to buy a Marketplace plan, for financial help with Marketplace costs (including premium tax credits or cost-sharing reductions), for a Special Enrollment Period to enroll in or change my Marketplace plan, for a Catastrophic plan, or for an exemption from the requirement to have health insurance. I disagree with the amount of financial help the Marketplace said I qualify for.
Explain why you think the Marketplace decision is wrong.
If you're filing this appeal more than 90 days after the date on the Marketplace Eligibility Notice you're appealing, please also explain the delay in filing your appeal.
Do you need to expedite your appeal?

If you think waiting for a standard decision may seriously jeopardize your life, health, or ability to attain, maintain, or regain maximum function, you can ask for a fast (expedited) appeal. (For example, you might qualify for an expedited appeal if you're currently in the hospital or urgently need medication).
Do you need to expedite your appeal? No. Yes. Please explain the reason you need an expedited appeal.
Get electronic updates

Step 4 Get electronic updates (optional): get updates about your appeal from the Marketplace Appeals Center.
Do you want to appoint a representative?

Do you want to appoint a representative? If No, go to Step 6. If Yes, fill out the section.
You can choose to have someone you trust (like a family member, friend, advocate, or attorney) act on your behalf for your appeal by giving them permission to be your authorized representative.
If you appoint an authorized representative, they'll be the main contact during your appeal.
All communications about your appeal (including email and text reminders) will go to your authorized representative, not you.
If you change your mind, you must call or write the Marketplace Appeals Center to remove your authorized representative.
Sign to give the person listed in this section permission to sign your appeal request, get official information about your appeal and act for you during your appeal.
Signature of the tax filer

Under Step 7 Signature, sign to let the Marketplace share federal tax information and Social Security Administration information for use during an appeal.
Each adult member of the household must consent to the disclosure of his or her own federal tax information and also consent to the release of monthly and annual Social Security Benefit information under Title II of the Social Security Act by signing.
Signature of the tax filer listed on your Marketplace application (even if they're not appealing).
The authorization is valid until the earlier of the resolution of the appeal; or my written notification that I want any or all of my authorized representatives removed from this appeal.
More rules for Marketplace Appeal Request Form A (CMS-12153)
Submit this form within 90 days of the date on the Marketplace Eligibility Notice you're appealing. Include any documents you have to help your appeal (Step 6). Have the tax filer on the Marketplace application sign the form (Step 7).
You may want to submit documents with your request to help show why you think the Marketplace decision was incorrect. Submit any documents you think will help your case.
This could be things like tax returns, pay stubs, W2 forms, passports, or other documents that show your income or prove other information.
Submit copies, not originals, since your documents won't be returned.
Appealing a Marketplace decision because of missing information about your taxes? Submit a Record of Account Transcript and a copy of IRS Form 8962, if you filed it.
If you have questions about your appeal call the Marketplace Appeals Center at 1-855-231-1751. Hours of operation are Monday through Friday, 7:00 a.m. to 8:30 p.m. Eastern Time (ET).
Common questions about Marketplace Appeal Request Form A (CMS-12153)
Where do I file it?
Sign the completed form and send your documents either By Mail: Health Insurance Marketplace Attn: Appeals 465 Industrial Blvd. London KY 40750-0061, or By Secure Fax: 1-877-369-0130. The Marketplace will send you a notice letting you know the Marketplace got your appeal request and giving more information about the appeal process within 7-10 days.
Is there a penalty?
I know that I may be subject to penalties under federal law if I provide false information.
What am I certifying when I sign?
I'm signing this form under penalty of perjury, which means I've provided true answers to all the questions, and I've answered to the best of my knowledge.
Sources
[1] Marketplace Appeal Request Form A (02/2025), CMS-12153, HealthCare.gov (the Official source link on this page).