


Caring Hearts Financial Assistance Application at a glance
What it is: Caring Hearts Application, with Account Number, Name of responsible party, Birth Date, Marital Status and a list of all dependents in your household.
Who signs: Date of Request and Applicant's Signature, then proceed to the appropriate section on pages 3 and 4 based on your tax filing status.
What to bring and attach to Caring Hearts Financial Assistance Application
Section A is for you if you are required to file taxes and your financial situation has not changed since filing. Section B is for you if you are not required to file taxes. Section C is for you if you are self-employed. Section D is for you if you are required to file taxes and your financial situation has changed since filing. In Sections A, C and D, submit a copy of your most recent Federal Tax Return. To request a copy of your taxes if needed, call 1-800-829-1040. In Sections B and D, include 2 most recent payroll statements or proof of income received. In all sections, include the full, detailed statement for the most recent month for all bank accounts listed, and the Completed and signed Caring Hearts Application. Statements need to include financial institute name, account holder name, account number(s) and need to include all pages. In Sections A, B and D, include a Written approval/denial response from Medical Assistance if any of the following apply: if you have children under the age of 18; if you are currently pregnant; if you have been determined disabled; if you are over the age of 65; if you are a Wisconsin immigrant with a medical emergency; if you are childless adult within Federal Poverty Guidelines. In Section C, include a Written approval/denial response from Medical Assistance. Contact the Department of Health and Human Services in the county that you reside in or access their website at (https://access.wisconsin.gov/access/) for assistance.
A filled-in Caring Hearts Financial Assistance Application example: a single parent applies for help with a hospital bill

How to fill out Caring Hearts Financial Assistance Application, box by box
Caring Hearts Application Date and Name of responsible party
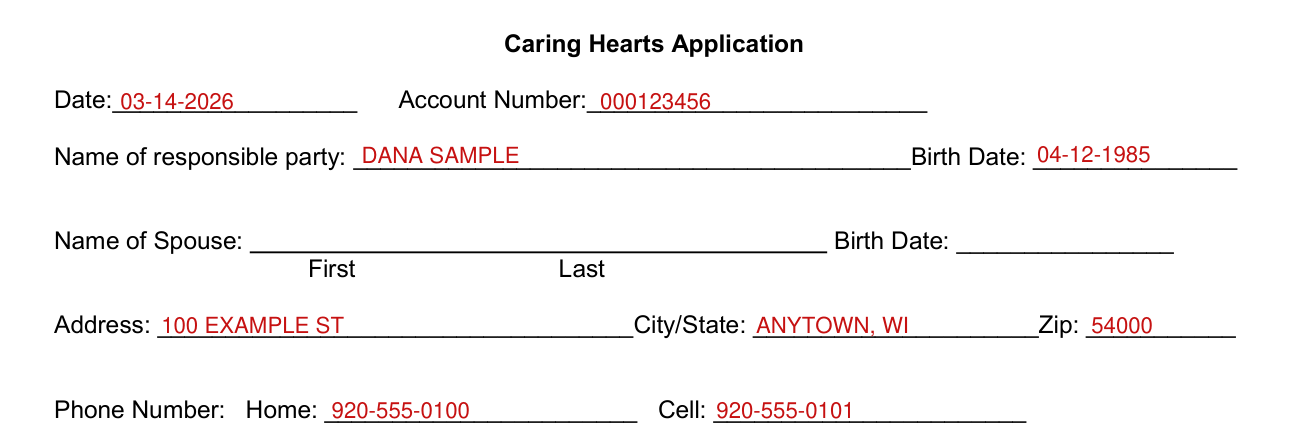
Enter the Caring Hearts Application Date, the Account Number, the Name of responsible party and the Birth Date.
Enter the Address, City/State, Zip, and the Phone Number: Home and Cell.
Under Marital Status (Please Circle), circle Married, Single, Widowed, Separated, Divorced or Life Partner.
Name of Spouse

If you have a spouse, enter the Name of Spouse (First, Last) and the Birth Date.
Dependents in your household
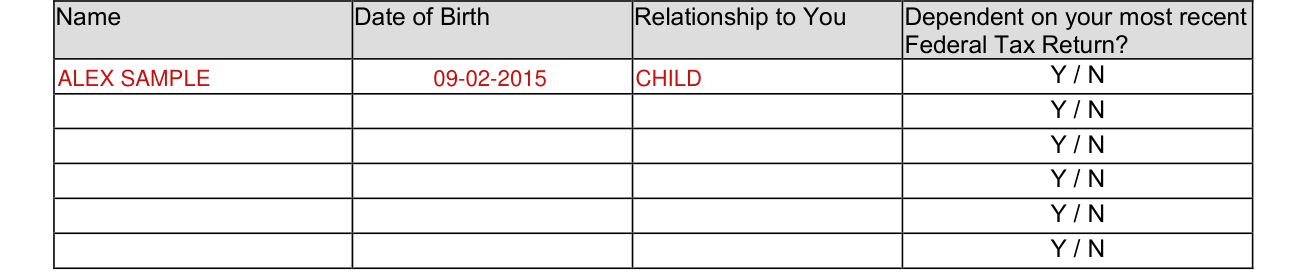
Under List all dependents in your household, enter the Name, the Date of Birth, the Relationship to You, and Y / N for Dependent on your most recent Federal Tax Return?
Income
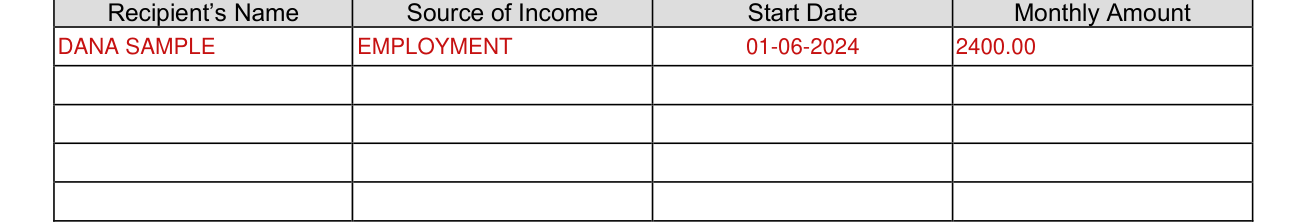
Income includes: employment, self-employment, unemployment, social security, disability, VA benefits, pension, retirement, monthly annuity payments, etc. Enter the Recipient's Name, the Source of Income, the Start Date and the Monthly Amount.
More rules for Caring Hearts Financial Assistance Application
Are there any open claims for workman's compensation, motor vehicle accidents, or third party liability that may pay on dates of service related to this request for financial assistance? Yes or No. If yes, date of Incident. Are you participating in a cost share program? Yes or No. Is there anyone in the household currently without health insurance? Yes or No. If yes, please list who. Income: Please list all income received monthly by all members of the household.
If you have no source of income, write how you have been supporting yourself.
The person supporting you signs the Signature of person supporting you line; enter the Print Name and the Relationship, and mark Y or N for discussing this application with that person.
List all open checking and savings account(s) for all household members, with the Account Owner, the Type of Account, the Bank Name and the Estimated Balance.
Under Are you required to file taxes by the Federal Government? check one: If Yes and your financial situation has not changed since filing, proceed to Section A. If No, proceed to Section B. If Yes and self-employed, proceed to Section C. If Yes and your financial situation has changed since filing, proceed to Section D.
You only need to complete the one section that best fits your situation, and the financial documentation must be submitted with your application.
Any false or misleading information will void this application and exclude you from financial assistance.
By signing, you authorize ThedaCare to verify any and all information presented in this application including but not limited to: employment verification and bank verification.
By signing you will take action to apply for any assistance (Medicaid, Medicare, insurance, etc.), which may be applicable for payment of your hospital/physician charges, and you will take any action reasonably necessary to obtain such assistance.
If your situation is different
Returning the application within 30 days
Caring Hearts is a financial assistance program designed for patients who are unable to pay for medically necessary services provided by all divisions within ThedaCare. Complete the entire application and submit all requested supporting documentation to avoid denial of your application. Eligibility guidelines for the Caring Hearts Program are based on financial need, and the program is considered to be the last resort after all other payment sources have paid. The Caring Hearts Program covers services which are deemed to be medically necessary as determined by your physician. The Caring Hearts Program does not cover: Elective Services - cosmetic, bariatric, as well as other non-medically necessary services. Non program providers - examples include radiologists, pathologists, anesthesiologists, independent surgeons, and independent physicians. A complete list of covered and non-covered providers can be found in the document titled "List of Providers that are covered/not covered by Caring Hearts". Dates of Service that were paid directly to you by the insurance company. Dates of Service pending third party liability payment. You may obtain a copy of the Caring Hearts Financial Assistance Policy or the list of covered and non-covered providers by: 1. Visiting the web site at www.thedacare.org/paymentoptions. 2. Contacting the Customer Support Department at 1-800-236-4102. 3. Mailing a request in writing to: Billing PO Box 8003 Appleton, WI 54912. 4. Visit a Patient Billing Services Office at one of the following locations; for the privacy of all patients, present to registration during the hours of 8:30 - 4:30, and they will connect you with a customer support team member: Regional Medical Center - Appleton - 1818 N. Meade St., Appleton, WI; Medical Center - Berlin - 225 N. Memorial St, Berlin, WI; Medical Center - Shawano - 100 County Road B, Shawano, WI. Collection efforts of unpaid balances may continue if a complete application along with all requested supporting documentation is not returned within 30 days. A letter stating your acceptance or exclusion from the Caring Hearts Program will be sent after your completed application has been processed. If you have any questions or need assistance in completing the application, call the customer support department at 920-830-5900, or toll free at 800-236-4102.
Financial Changes
In Section D, under Financial Changes, describe any financial changes that have occurred since the completion of most recent Federal Tax Return, with the Previous and Current, and attach any additional documentation or verification of the financial changes noted.
Common questions about Caring Hearts Financial Assistance Application
Who signs it?
The applicant enters the Date of Request and signs the Applicant's Signature line. Read the scenarios under Required Financial Documentation and proceed to the appropriate section on pages 3 and 4 based on your tax filing status.
What am I certifying when I sign?
You certify that the information is true and accurate to the best of your knowledge.
Sources
[1] Caring Hearts Financial Assistance Application, ThedaCare (served file) (the Official source link on this page).