


EAP Statement of Services Rendered Form at a glance
What it is: EAP Statement of Services Rendered Form: Sessions Provided.
Who signs: Sign on the Provider Signature line and enter the Date.
A filled-in EAP Statement of Services Rendered Form example: a counselor reports twelve sessions

How to fill out EAP Statement of Services Rendered Form, box by box
Provider, Billing Address, Reference Number, Start Date, End Date, Company and EAP Model

Enter the Rendering Provider National Provider Identifier (NPI), the Fax Number, the Billing Address, Make Check Payable to, the Tax ID, the Billing Provider National Provider Identifier (NPI), the Reference Number (Required), the Start Date, the End Date, the Company and the EAP Model. Due to HIPAA privacy regulations Anthem EAP can no longer include any EAP member's name on these confirmation forms and will only release the member name telephonically. For the member name that corresponds to the reference number, please feel free to contact Anthem EAP at the toll free number located in the "From:" box on the fax cover sheet. For the Scheduled Appt Date (Date Reported by Client), (Reminder: please call (800) 728-9492, Option 1# and report first session date).
Sessions Provided
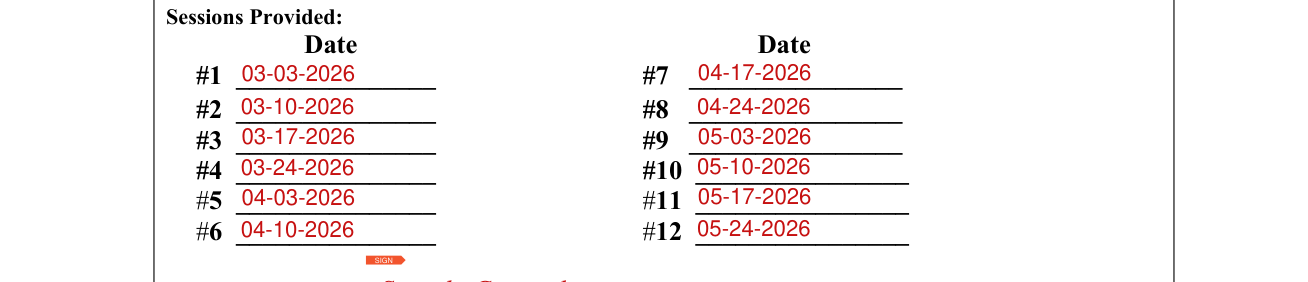
Under Sessions Provided, enter a Date for each of the sessions #1 to #12.
Mail Claims to, Or Fax to and For Claim Status

Mail Claims to: EAP Claims, 9655 Granite Ridge Drive, 6th Floor, San Diego, CA 92123.
Or Fax to: (858) 571-8102.
For Claim Status: (800) 728-9492 Option 3#.
More rules for EAP Statement of Services Rendered Form
The EAP Case Form is Confidential Health Information. Phone (800) 728-9492, Option 2#. Fax (858) 571-8102.
Enter the Client Name, the Reference # (Required) and the Company. EAP Assessment: (Check 1 box only).
Alcohol, Marital/Couple Problem, Drug, Violence, Impacted By Alcohol Family/Significant Other, Medical Problem, Impacted by Drug Family/ Significant Other, Legal, Emotional/Psychological, Financial Problem, Impacted by Emotional/Psych of Family/ Significant Other, Work Related Concern, Eating Disorder, Dependent Care, Family Problems and Other Issues.
Recommendation: (Primary) (Check 1 box only).
EAP only, Partial hospital psychiatric, Medical doctor referral, Outpatient mental health (office), Psychiatric meds. Eval/tx, Psychological testing, Alcohol/drug detoxification, Social agency, public program/mental health, Inpatient alcohol/drug tx, Self-help/support group, Structured outpatient alcohol/drug tx, Employer, H.R., management, benefits, etc., Non Hospital Residential Facility, Childcare/eldercare resources, Inpatient psychiatric tx and Career / vocational counseling.
Enter the Closing Date.
Benefit Utilization: EAP Assistance Only, Referrals Not Utilizing Insurance Benefits (Community Resources) and Referrals Utilizing Insurance Benefits.
Referral Information: The Client Was Referred to Psychiatrist, Psychologist, MFT/LCSW, Community Resources (Referrals Not Utilizing Insurance Benefits), PCP/Medical Specialist, Other or Case Closed (EAP Assistance Only/No Additional Referral Needed). If care was transferred to another licensed professional or behavioral health facility, was the transfer of care coordinated with the new provider by Phone, Fax, Report/Letter, Other or Not Applicable?
Disposition of Case: Resolved, Improved, No Change, Deteriorated, Declined Recommendation and Unable to Contact.
Please read thoroughly before signing and direct any questions to your consultant.
The client enters the Client Name (Please Print), signs on the Client Signature line and enters the Date, the Social Security # and the Company Name.
Common questions about EAP Statement of Services Rendered Form
Are there fees?
There are no fees to employees or family members for any service received directly from BCC. When BCC refers to resources in the community for ongoing or specialized services, you are responsible for paying any applicable fees.
Is there a penalty?
Unauthorized re-disclosure or failure to maintain confidentiality could subject you to penalties described in Federal and State law.
Sources
[1] EAP Statement of Services Rendered Form, Anthem Blue Cross (Blue Cross of California) (the Official source link on this page).