

Form CMS-855A at a glance
What it is: Medicare enrollment application CMS-855A for institutional providers.
Who signs: Only an authorized official has the authority to sign (1) the initial enrollment application on behalf of the provider and (2) add or remove additional authorized officials and delegated officials.
What to bring and attach to Form CMS-855A
If you are enrolling for the first time, or reactivating or revalidating your enrollment, you must submit all applicable documents.
Licenses, certifications and registrations required by Medicare or State law.
Written confirmation from the IRS confirming your Tax Identification Number with the Legal Business Name (e.g., IRS CP 575) provided in section 2A.
Completed Form CMS-588, Authorization Agreement for Electronic Funds Transfer. Include a voided check or bank letter.
A filled-in Form CMS-855A example: a hospital enters its business information

How to fill out Form CMS-855A, box by box
Reason for submitting this application
Check one box and complete the required sections.
You are a new enrollee in Medicare Complete all applicable sections except 2G, 2H, and 2I
Skilled Nursing Facilities must complete Attachment 1
You are solely enrolling in Medicare to participate in Medicaid or another health care program and will not be billing Medicare Complete all applicable sections except 2G, 2H, and 2I
You are enrolling with another Medicare Administrative Contractor (MAC) Complete all applicable sections except 2G, 2H, and 2I
You are revalidating your Medicare enrollment Complete all applicable sections except 2G, 2H, and 2I
You are reactivating your Medicare enrollment Complete all applicable sections except 2G, 2H, and 2I
You are changing your Medicare information Go to Section 1B
There has been a Change of Ownership (CHOW) of the Medicare-enrolled provider You are the: Seller/Former owner: 1A, 2B1, 2G, 13, and either 15B (if you are the authorized official) or 15C (if you are the delegated official) Buyer/New owner: Complete all sections except 2H and 2I
Your organization has taken part in an acquisition or merger You are the: Seller/Former owner: 1A, 2B1, 2H, 13, either 15B or 15C, and 6 for the signer if that authorized or delegated official has not been established for this provider. Buyer/New Owner: 1A, 2H, 4, 13, either 15B (if you are the authorized official) or 15C (if you are the delegated official), and 6 for the signer if that authorized or delegated official has not been established for this provider.
Your organization has consolidated with another organization You are the: Former organizations: 1A, 2B1, 2I, 13, and either 15B (if you are the authorized official) or 15C (if you are the delegated official) New organization: Complete all sections except 2G and 2H
You are voluntarily terminating your Medicare enrollment Complete sections: 1, 2B1, 13, either 15B or 15C, and 6 for the signer if that authorized or delegated official has not been established for this provider.
Type of provider
Check only one provider type.
If the provider functions as two or more provider types, a separate enrollment application (CMS-855A) must be submitted for each type.
Business information
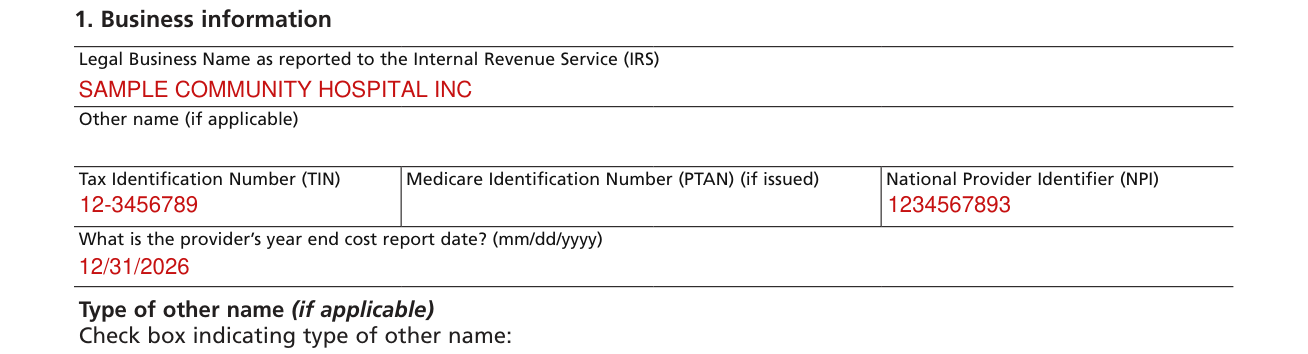
1. Business information Legal Business Name as reported to the Internal Revenue Service (IRS)
NOTE: The Legal Business Name (LBN) and Tax Identification Number (TIN) that you furnish in section 2B1 must be the same LBN and TIN you used to obtain your NPI.
Ensure that the Legal Business Name shown in Section 2B1 matches the name on the tax documents.
IRS business designation

IRS business designation Identify how your business is registered with the IRS.
NOTE: If a checkbox identifying how the business is registered with the IRS is not completed, the supplier will be defaulted to “proprietary.”
Identify the business structure

Identify the business structure: (Check one)
More rules for Form CMS-855A
Sign and date Section 15.
Keep a copy of your completed Medicare enrollment package for your records.
If your situation is different
You are an institutional provider
Complete and submit this application if you are a health care organization that plans to bill Medicare and you are: An institutional organization that will bill for Medicare Part A services (e.g., hospitals, community mental health centers, skilled nursing facilities).
Institutional providers can apply for enrollment in the Medicare program or make a change in their enrollment information using either: The internet-based Provider Enrollment, Chain and Ownership System (PECOS), or The paper CMS-855A enrollment application.
NOTE: Applicants using this application require a Type 2 NPI.
Medicare healthcare providers, except organ procurement organizations, must obtain an NPI prior to enrolling in Medicare or before submitting a change to your existing Medicare enrollment information.
This form must be typed. It may not be handwritten.
All information on this form is required with the exception of those fields specifically marked as “optional.” Any field marked as optional is not required to be completed nor does it need to be updated or reported as a “change of information” as required in 42 C.F.R. section 424.516.
You are enrolling for the first time
Enrolling in the Medicare program for the first time with this MAC under this tax identification number.
NOTE: Per Section 125 of the Consolidated Appropriations Act of 2021 (CAA) an action plan is required to be submitted with the enrollment application.
You are revalidating
Revalidating your Medicare enrollment. The MAC will notify you when it is time for you to revalidate your enrollment information. Do not submit a revalidation application until you have been contacted by the MAC.
Common questions about Form CMS-855A
Who signs it?
Once the delegation of authority has been established all other enrollment application submissions can be signed by either an authorized official or delegated official.
Is there a deadline?
If the MAC requests additional documentation to support or validate information reported on the application, you are responsible for providing it within 30 days of the request per 42 C.F.R. section 424.525(a)(1).
Where do I file it?
WHERE TO MAIL YOUR APPLICATION Send this completed application with original signatures and all required documentation to your designated MAC.
Are there fees?
Pay the required application fee (via PECOS.cms.hhs.gov/pecos/feePaymentWelcome.do) upon initial enrollment, the addition of a new practice location, and revalidation PRIOR to completing and submitting this application to your MAC.
Is there a penalty?
I understand that any omission, misrepresentation, or falsification of any information contained in this application or contained in any communication supplying information to Medicare, or any alteration of any text on this application form, may be punished by criminal, civil, or administrative penalties including, but not limited to, the denial or revocation of Medicare billing privileges, and/or the imposition of fines, civil damages, and/or imprisonment.
When is this form not the right one?
If your provider type is not listed, contact your designated Medicare Administrative Contractor (MAC) before you submit this application.
Sources
[1] Form CMS-855A (09/24), Centers for Medicare & Medicaid Services (the Official source link on this page).
