
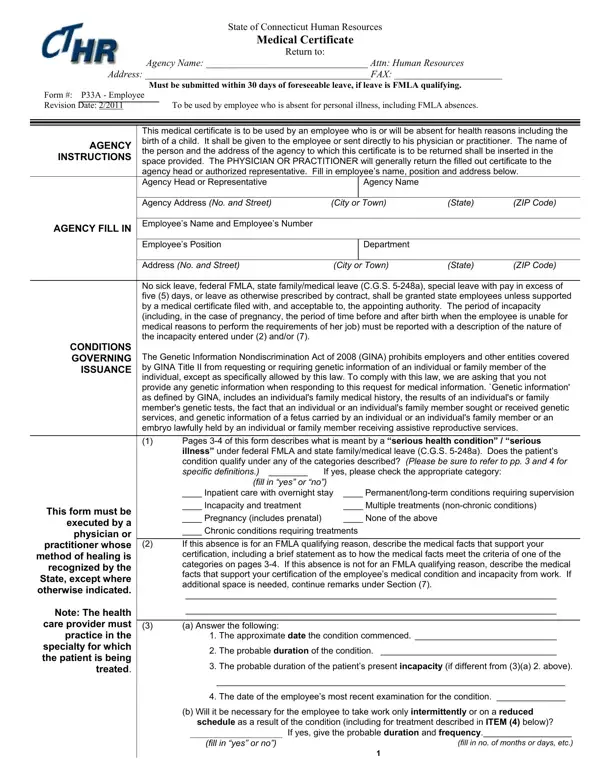
Form P33A at a glance
What it is: State of Connecticut Human Resources Medical Certificate, Form #: P33A - Employee Revision Effective Date: 1/1/2022, to be used by employee who is absent for personal illness, including FMLA absences.
Who signs: A physician or practitioner whose method of healing is recognized by the State must execute this form.
Where and when to file: Submit it within 30 days of foreseeable leave if leave is FMLA qualifying. Return to Human Resources at: Agency Name, Attn, E-mail Address and FAX.
A filled-in Form P33A example: an employee fills the employee information

How to fill out Form P33A, box by box
Employee information
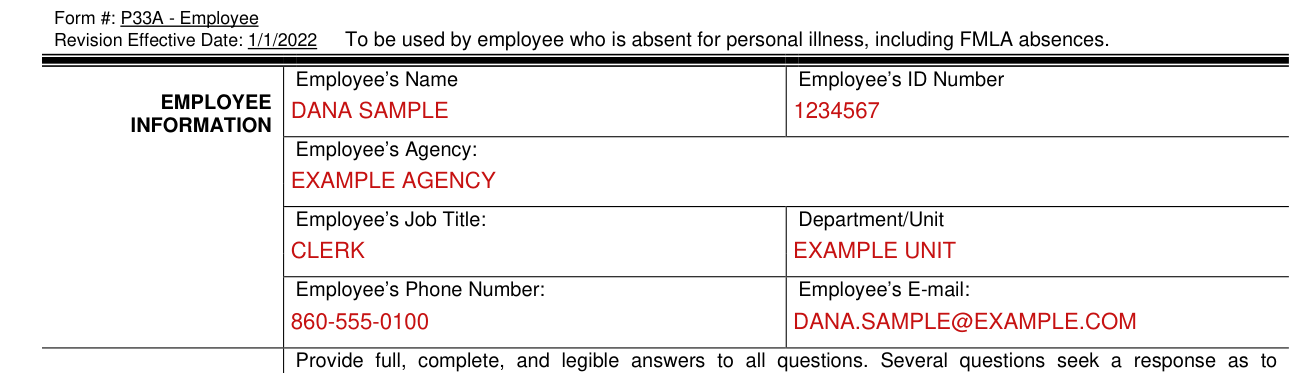
Under EMPLOYEE INFORMATION, enter the Employee's Name, Employee's ID Number, Employee's Agency, Employee's Job Title, Department/Unit, Employee's Phone Number and Employee's E-mail.
Medical facts
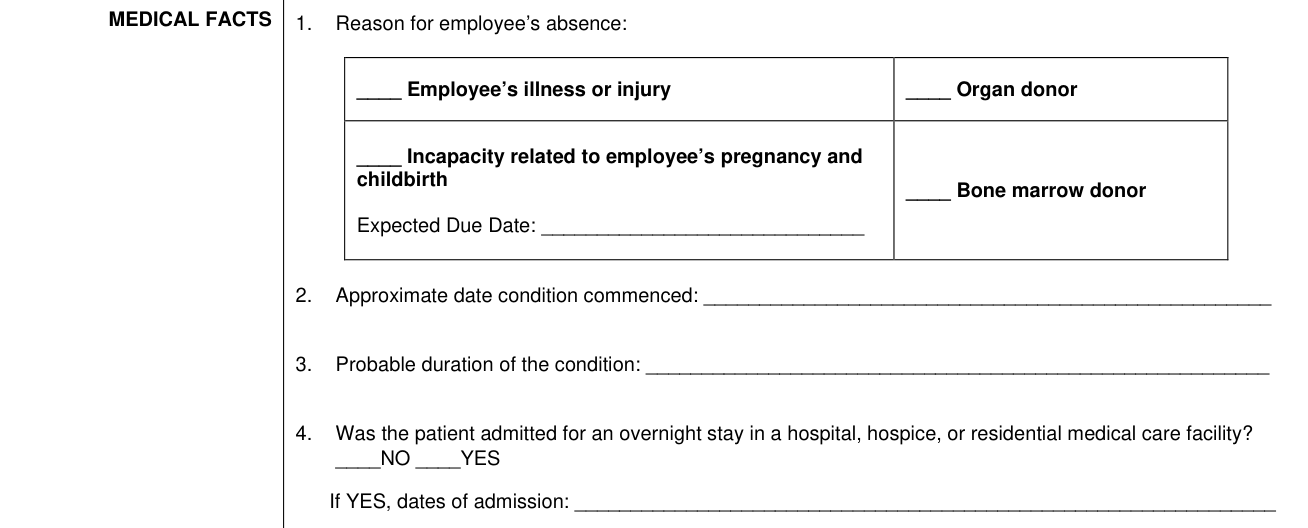
MEDICAL FACTS 1. Reason for employee's absence: Employee's illness or injury, Organ donor, Incapacity related to employee's pregnancy and childbirth, or Bone marrow donor. Expected Due Date.
2. Approximate date condition commenced. 3. Probable duration of the condition.
4. Was the patient admitted for an overnight stay in a hospital, hospice, or residential medical care facility? NO or YES. If YES, dates of admission.
More rules for Form P33A
INSTRUCTIONS TO THE HEALTH CARE PROVIDER: Provide full, complete, and legible answers to all questions. Several questions seek a response as to frequency and duration of a condition, treatment, etc. Your answer should be your best estimate based upon your medical knowledge, experience, and examination of the patient. Be as specific as you can; terms such as “lifetime,” “unknown,” or “indeterminate” may not be sufficient to determine coverage under the Family and Medical Leave Entitlements.
Limit your responses to the condition for which the employee is or will be absent from work. Do not provide information about the manifestation of disease or disorder in the employee's family members, 29 C.F.R. §1635.3(b), genetic services, as defined in 29 C.F.R. §1635.3(e), or genetic tests, as defined in 29 C.F.R. §1635.3(f).
If additional space is needed, please attach a separate sheet and identify the question number. Please be sure to sign the form on page 3.
5. Is it medically necessary for the patient to receive continuing treatment by a medical provider? NO or YES. If YES, provide the following information about the treatment:
Dates you treated the patient for the condition. Will the patient need to have treatment visits at least twice per year due to the condition? NO or YES. Was medication, other than over-the-counter medication, prescribed? NO or YES. Was the patient referred to other health care provider(s) for evaluation or treatment? NO or YES.
Describe other relevant medical facts, if any, related to the condition for which the employee seeks leave, including, as applicable, a description of relevant symptoms, the regimen of continuing treatment or the plan for continuing supervision provided by the health care provider for a condition for which treatment may not be effective.
6. Is the employee unable to perform any of their job functions due to the medical condition (including the need for treatment and recovery)? NO or YES. If YES, identify the job functions the employee is unable to perform (using the employee's job specification, if provided, as a reference).
LEAVE NEEDED 7. Is it medically necessary for the employee to be absent from work due to their medical condition, including the need for treatment and recovery? NO or YES.
8. Will the employee be incapacitated for a single continuous period due to their medical condition, including any time for treatment and recovery? NO or YES. If YES, estimate the beginning and ending dates for the period of incapacity: Beginning Date and Ending Date.
9. Is it medically necessary for the employee to attend follow-up treatment appointments because of the medical condition? NO or YES. If YES, provide the actual or estimated treatment schedule. Include the dates of any scheduled appointments, the time required for each appointment, and any recovery period:
10. Is it medically necessary for the employee to work on a reduced schedule due to the employee's condition? NO or YES. If YES, estimate the reduced work schedule needed by the employee: hour(s) per day, day(s) per week, From through.
11. Will the condition cause episodic flare-ups periodically preventing the employee from performing their job functions? NO or YES. If YES: Is it medically necessary for the employee to be absent from work during the flare-ups? NO or YES. If YES, explain.
12. Based upon the patient's medical history and your knowledge of the medical condition, estimate the frequency of flare-ups and the duration of related incapacity that the patient may have (e.g., 1 episode every 3 months lasting 1-2 days): Frequency: time(s) every week(s) OR time(s) every month(s). Duration: hour(s) per episode OR day(s) per episode.
On the EMPLOYEE FITNESS-FOR-DUTY CERTIFICATION, the employee's treating health care provider must complete this fitness-for-duty certification. The employee must provide the completed fitness-for-duty certification to Human Resources before reporting to their department or unit.
Will the employee have any restrictions when they return to work? NO or YES. If YES, describe the restrictions (If additional space is needed, please attach a separate sheet:
Common questions about Form P33A
Who signs it?
Name of Physician or Practitioner (please type or print), Physician or Practitioner License Number, Address, Phone Number, Fax Number, Signed (Physician or Practitioner) and Date: the EMPLOYEE FITNESS-FOR-DUTY CERTIFICATION has the same lines.
Is there a deadline?
Submit it within 30 days of foreseeable leave if leave is FMLA qualifying.
Where do I file it?
Return to Human Resources at: Agency Name, Attn, E-mail Address and FAX.
What am I certifying when I sign?
By signing the EMPLOYEE FITNESS-FOR-DUTY CERTIFICATION you certify that you have examined (employee's name) and that they are able to return to work. Enter the Employee's Name, Employee's ID Number, Employee's Job Title and Department/Unit, and the Date the employee will be able to return from leave.
Sources
[1] Form P33A (Employee Revision Effective Date 1/1/2022), State of Connecticut Human Resources Medical Certificate (the Official source link on this page).