


Desjardins 19132A at a glance
What it is: 19132A, Claim for Health Care Benefits: a Group Insurance - Health Claims form.
Who signs: Please sign section I.
A filled-in Desjardins 19132A example: a plan member fills out sections A and B

How to fill out Desjardins 19132A, box by box
Identification
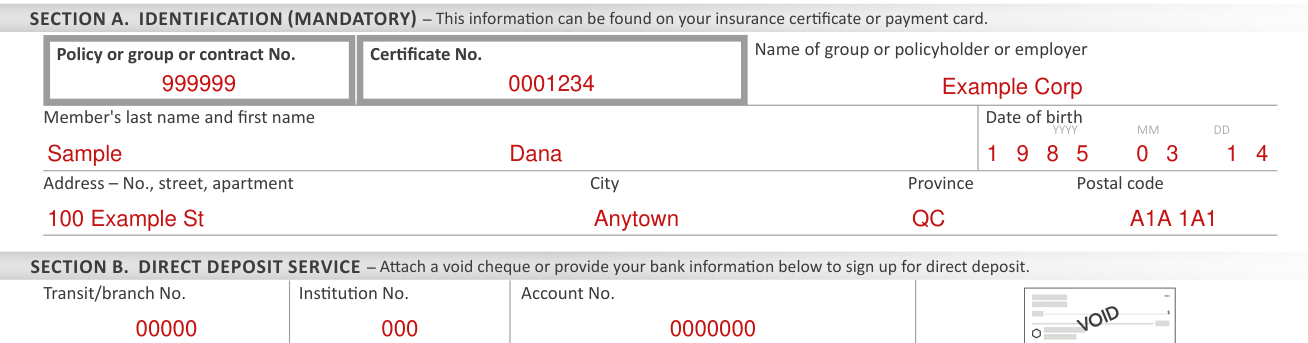
Section A, Identification, is mandatory: enter the policy or group or contract No., certificate No., name of group or policyholder or employer, member's last name and first name, and date of birth.
This information can be found on your insurance certificate or payment card.
Write the date of birth as YYYY MM DD.
Enter the address (No., street, apartment), city, province and postal code.
Direct deposit service
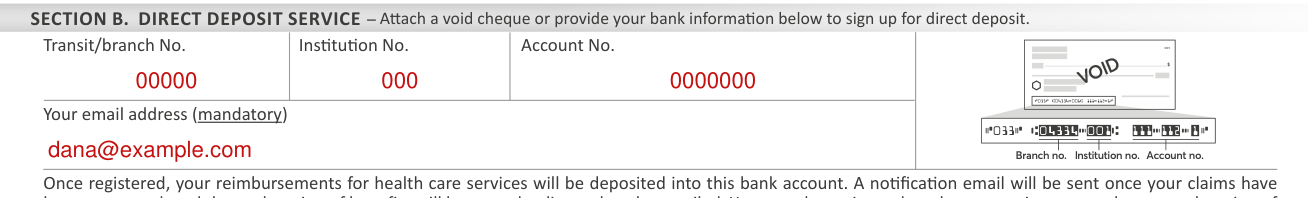
To sign up for direct deposit, attach a void cheque or provide your bank information: transit/branch No., institution No. and account No.
Your email address is mandatory.
Once registered, your reimbursements for health care services will be deposited into this bank account. A notification email will be sent once your claims have been processed, and the explanation of benefits will be posted online rather than mailed. You must be registered on the secure site to consult your explanation of benefits. Desjardins Insurance is not responsible for the accuracy of the banking information you enter and for verifying that the due amounts are deposited into your account.
Coordination of benefits
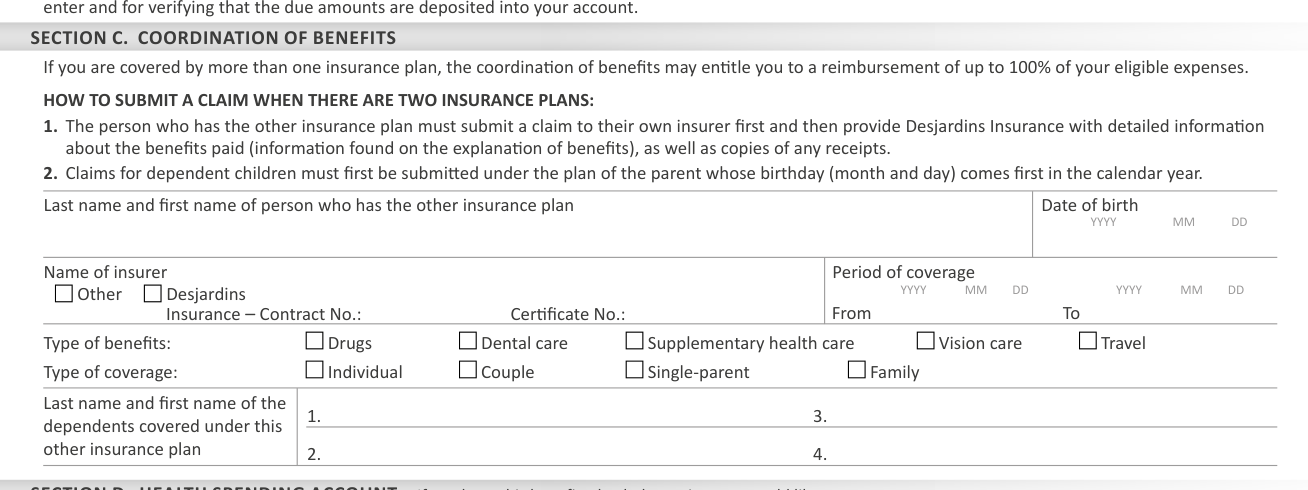
If you are covered by more than one insurance plan, the coordination of benefits may entitle you to a reimbursement of up to 100% of your eligible expenses.
When there are two insurance plans, the person who has the other insurance plan must submit a claim to their own insurer first and then provide Desjardins Insurance with detailed information about the benefits paid (information found on the explanation of benefits), as well as copies of any receipts.
When there are two insurance plans, claims for dependent children must first be submitted under the plan of the parent whose birthday (month and day) comes first in the calendar year.
Enter the last name and first name of the person who has the other insurance plan, the date of birth as YYYY MM DD, the name of insurer (Other, or Desjardins Insurance) and the Contract No. and Certificate No.
Enter the period of coverage From YYYY MM DD To YYYY MM DD.
Mark the type of benefits: Drugs, Dental care, Supplementary health care, Vision care or Travel. Mark the type of coverage: Individual, Couple, Single-parent or Family.
Enter the last name and first name of the dependents covered under this other insurance plan.
Health spending account

If you have this benefit, check the option you would like.
One of the three options is the box "I do not wish to use my Health Spending Account". If you don't choose an option, the portion of expenses that isn't covered by your plan will be automatically submitted to the Health Spending Account for reimbursement.
Ineligible expenses: I wish to use my Health Spending Account to cover the expenses that are not reimbursed under my group insurance plan. Spouse's family coverage: I wish to use my Health Spending Account for myself and my dependent children to cover the expenses that are not reimbursed under my group insurance plan, and I will not submit a claim to my spouse's insurer (coordination of benefits).
I confirm that I am eligible for a reimbursement of the indicated expenses under my Health Spending Account.
Information about dependents
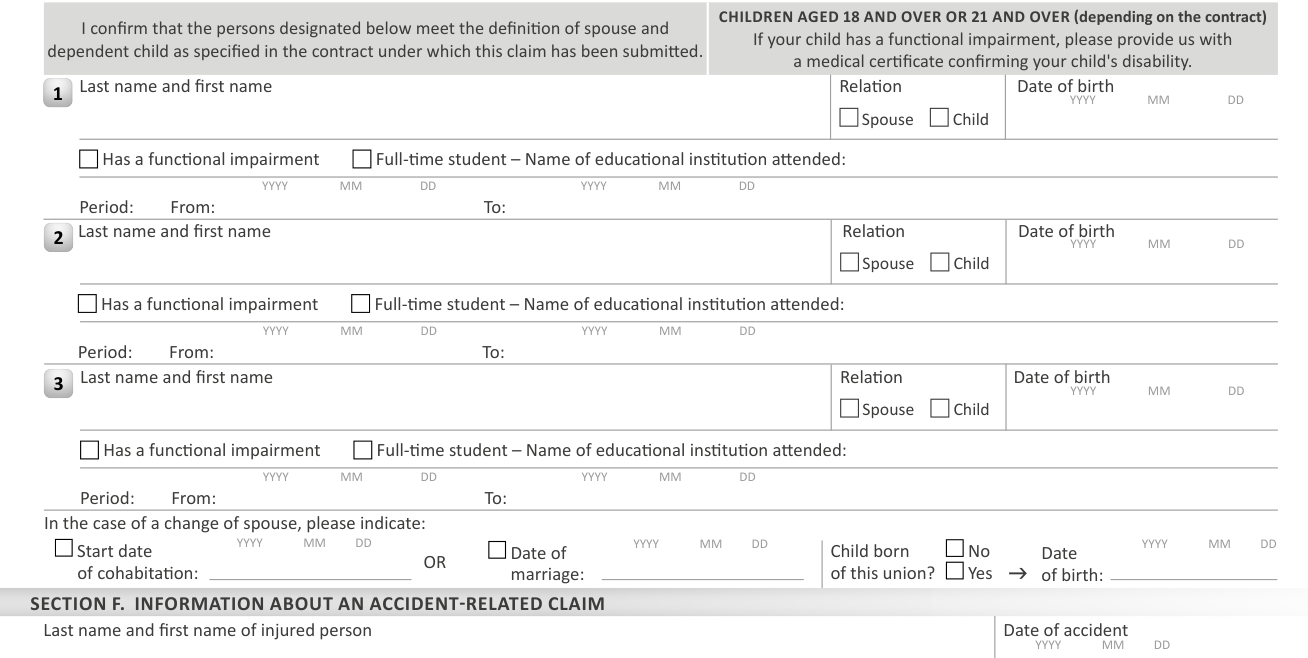
Section E, Information about dependents, is for the period in which expenses were incurred: the persons designated meet the definition of spouse and dependent child as specified in the contract under which this claim has been submitted.
Enter the last name and first name, the relation (Spouse or Child) and the date of birth as YYYY MM DD.
For children aged 18 and over or 21 and over (depending on the contract), mark Has a functional impairment, or Full-time student with the name of educational institution attended and the Period: From YYYY MM DD To YYYY MM DD.
If your child has a functional impairment, provide a medical certificate confirming your child's disability.
In the case of a change of spouse, please indicate: Start date of cohabitation: YYYY MM DD OR Date of marriage: YYYY MM DD. Child born of this union? No or Yes; if Yes, Date of birth: YYYY MM DD.
Information about an accident-related claim

Section F, Information about an accident-related claim: enter the last name and first name of injured person and the Date of accident as YYYY MM DD.
Is the claim the result of a work injury? a motor vehicle accident? Mark the one that applies.
Please note that the claim must first be submitted under your provincial workers' compensation plan or automobile insurance plan (if applicable in your province) before being submitted to your group insurance plan.
Out-of-province expenses
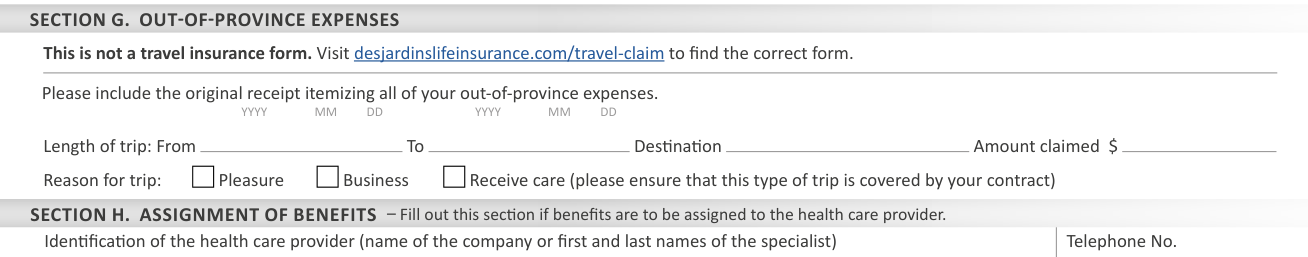
Please include the original receipt itemizing all of your out-of-province expenses.
Enter the Length of trip: From YYYY MM DD To YYYY MM DD, the Destination and the Amount claimed.
Reason for trip: mark Pleasure, Business or Receive care (please ensure that this type of trip is covered by your contract).
Assignment of benefits

Section H, Assignment of benefits: Fill out this section if benefits are to be assigned to the health care provider.
Enter the identification of the health care provider (name of the company or first and last names of the specialist), Telephone No., address (No., street, suite), city, province and postal code.
By signing, you understand that the expenses being claimed may not be covered by the insurer or may exceed the maximum benefit payable, and that you are responsible for paying these expenses; you assign benefits payable to the health care provider designated and authorize the insurer to pay this provider directly. Sign as the member and have the health care provider sign, each with the Date.
Declaration and authorization

Section I, Declaration and authorization for the collection, use and communication of personal information: All the information I have provided on the claim form is accurate and complete. I acknowledge having read the Personal Information Management section.
This authorization is also valid for the collection, use and communication of personal information concerning my dependents, insofar as applicable to the claim. A photocopy of this authorization is as valid as the original.
Sign as the member with the Date, and enter the Telephone Nos: Home, Office and Extension.
More rules for Desjardins 19132A
Would you like to submit your claim online? Go to desjardinslifeinsurance.com/planmember for online and mobile services and direct deposit.
If your claim is for a dependent, accident-related expenses, out-of-province expenses or an assignment of benefits, please complete the appropriate section on the back of the form.
Common questions about Desjardins 19132A
Where do I file it?
Send the form and original receipt to: Desjardins Insurance, C. P. 3950, Lévis (Québec) G6V 8C6.
When is this form not the right one?
Section G, Out-of-province expenses: This is not a travel insurance form. Visit desjardinslifeinsurance.com/travel-claim to find the correct form.
Sources
[1] Claim for Health Care Benefits, form 19132A (2024-07), Desjardins Insurance (the Official source link on this page).