
Form DHB-3051 at a glance
What it is: Form DHB-3051 is the Request for Independent Assessment for Personal Care Services and Attestation of Medical Need, to request a PCS Independent Assessment.
Who signs: Practitioner, sign and date once completed. Signature stamps are not allowed.
Where and when to file: Form Submission for PCS: Fax NCLIFTSS at 1-833-521-2626 (toll free). Form Submission for Expedited Assessment: Fax NCLIFTSS at 1-833-551-2602 (toll free).
Requested assessments will be one of the following: Disenrollment, New Request, Change of Status (Medical or Non-Medical), or Change of Provider.
Sections A - E: Change of Status: Medical, New Request, and Managed Care Disenrollment (located on pg. 1-2 of the form) shall be completed by a practitioner with Section E completed by the PCS Provider if for Managed Care Disenrollment.
It is required that the beneficiary's PCP or inpatient practitioner complete this form. If beneficiary does not have a PCP, the practitioner, currently providing care and treatment for the medical, physical or cognitive condition causing the functional limitation, may complete the form.
What to bring and attach to Form DHB-3051
If identified as legal guardian or Power of Attorney (POA), submit guardianship/POA documents to NC LIFTSS.
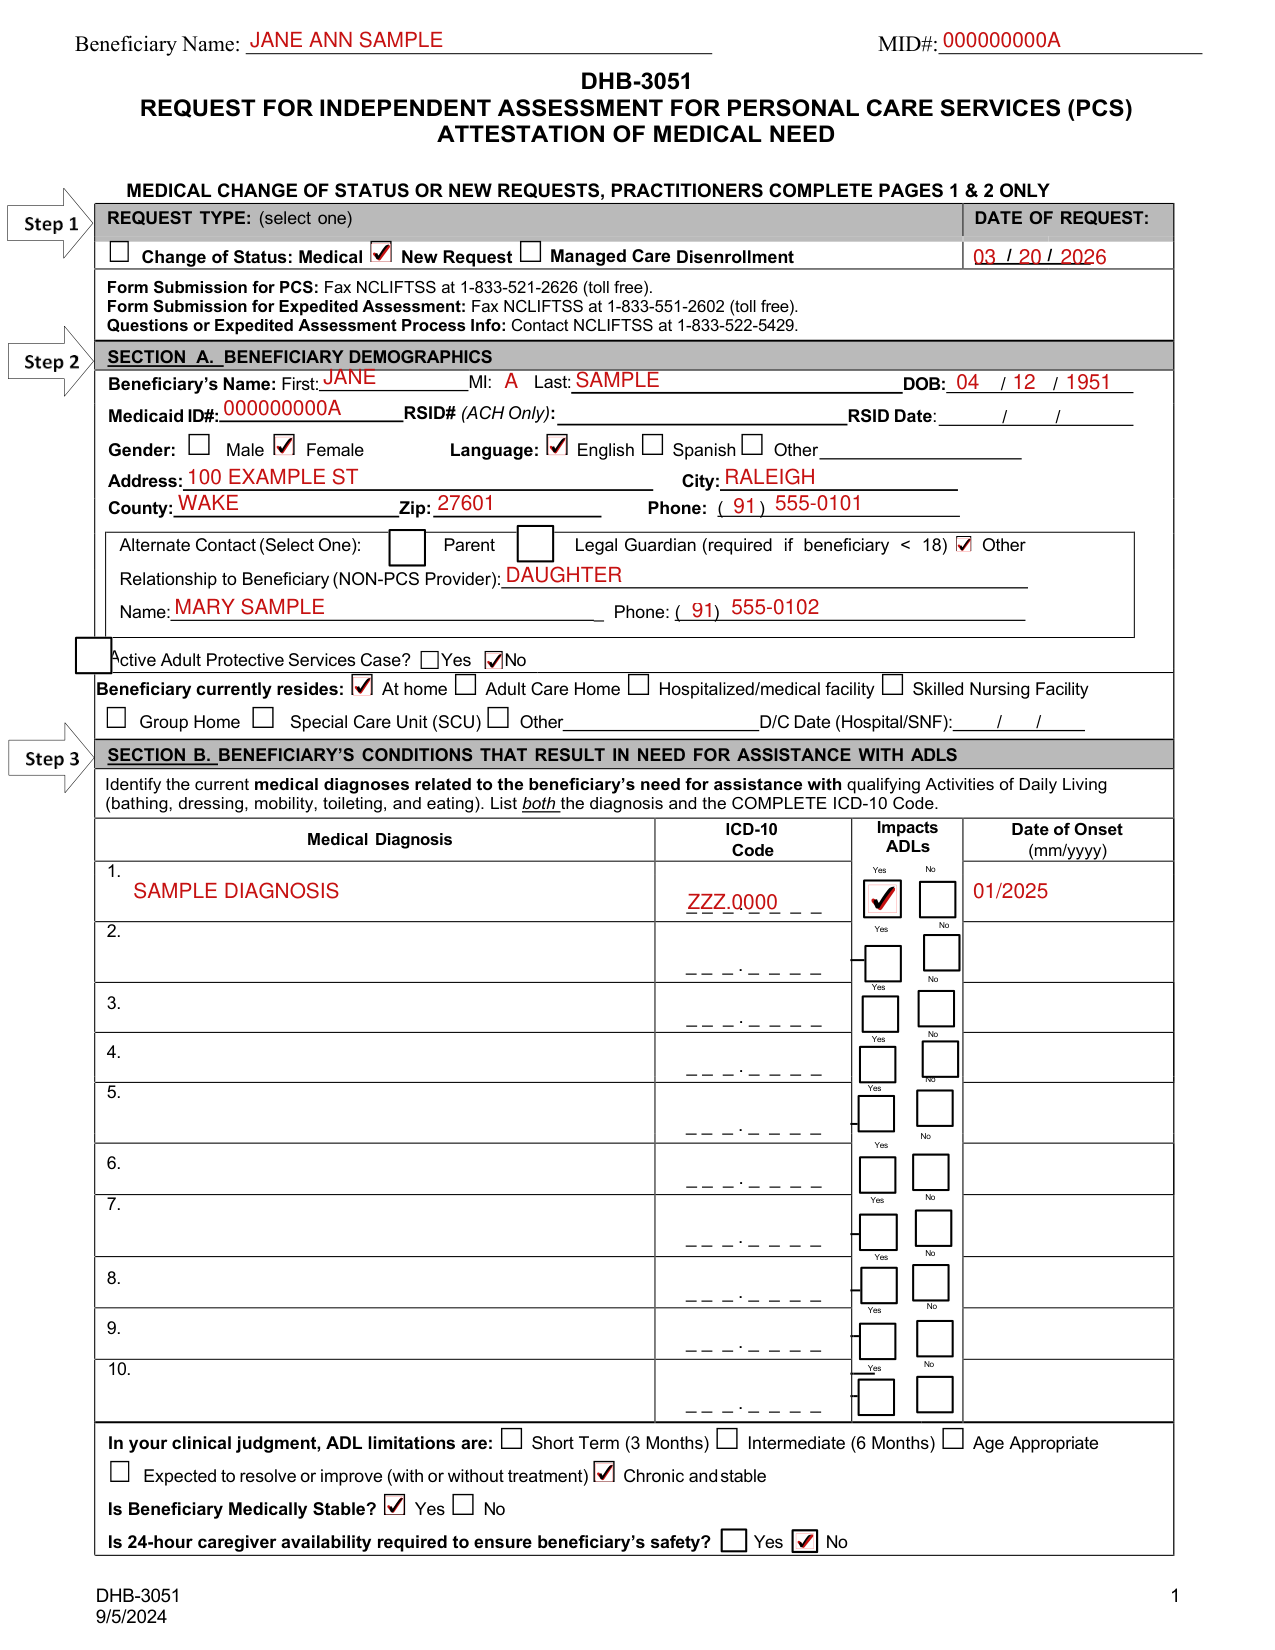
A filled-in Form DHB-3051 example: a practitioner submits a New Request
How to fill out Form DHB-3051, box by box
Request Type
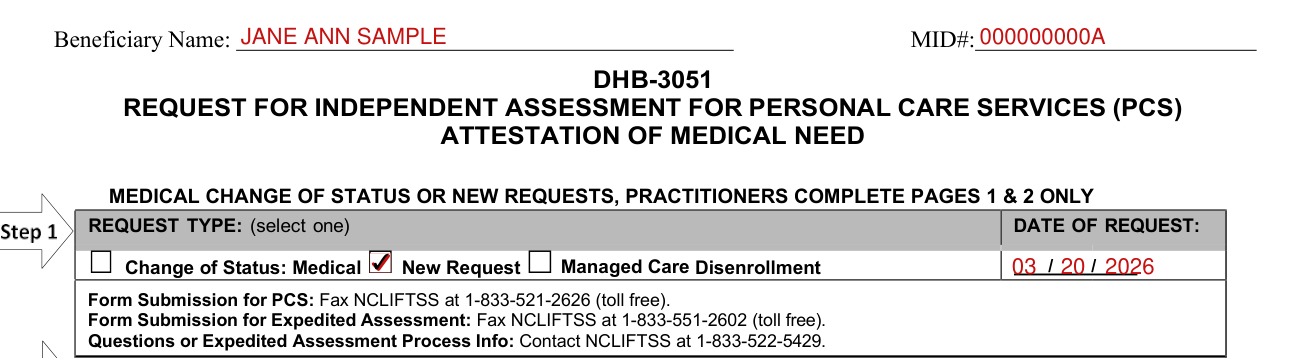
Request Type: Select the type that indicates the reason for the request. Enter the Date of Request in the appropriate field.
Medical Change of Status or New Requests, practitioners complete pages 1 & 2 only.
Section A. Beneficiary Demographics
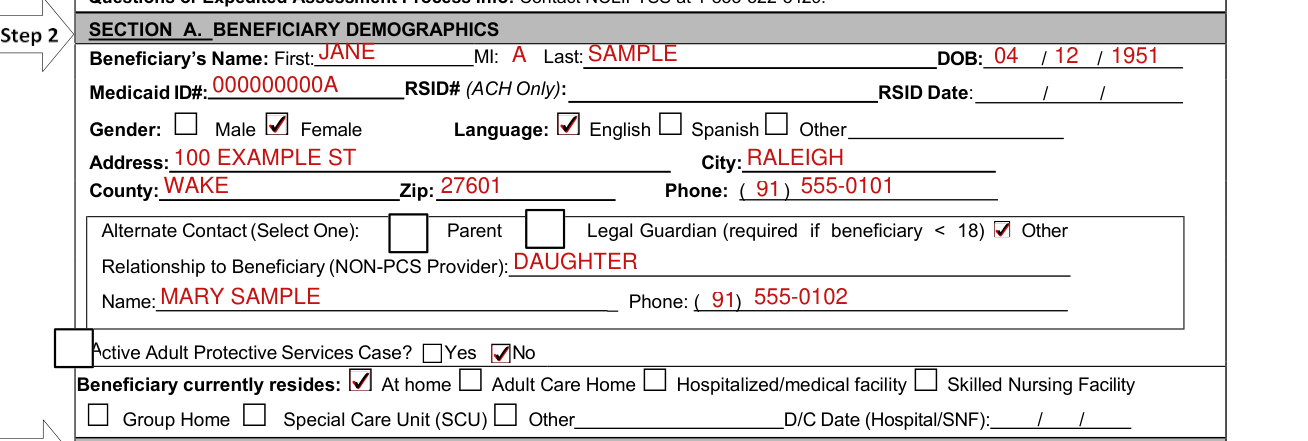
The beneficiary's name should be the same as it appears on their Medicaid card.
Beneficiaries living in, and those seeking admission to, an Adult Care Home (ACH) will have the facility's address and phone number.
The RSID # and RSID Date is generated when a beneficiary, being referred or seeking admission to an ACH, is referred to a LME-MCO for the RSVP.
The Alternate Contact should not be a PCS Provider.
Section B. Beneficiary's Conditions That Result in Need for Assistance with ADLs
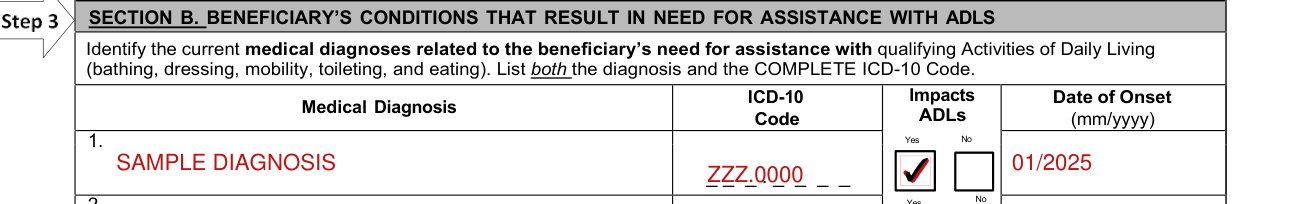
Identify the current medical diagnoses related to the beneficiary's need for assistance with qualifying Activities of Daily Living (bathing, dressing, mobility, toileting, and eating). List both the diagnosis and the COMPLETE ICD-10 Code.
Medical Diagnosis and ICD-10 Code are both required fields.
The Diagnosis and ICD-10 entered must relate to the ADL deficit for this request to be processed.
Date of Onset (mm/yyyy).
In your clinical judgment, ADL limitations are

In your clinical judgment, ADL limitations are: Short Term (3 Months), Intermediate (6 Months), Age Appropriate, Expected to resolve or improve (with or without treatment), or Chronic and stable.
Is Beneficiary Medically Stable? Yes or No.
Is 24-hour caregiver availability required to ensure beneficiary's safety? Yes or No.
More rules for Form DHB-3051
Questions or Expedited Assessment Process Info: Contact NCLIFTSS at 1-833-522-5429.
Other requests
You are the practitioner completing Section C
Practitioner, sign and date once completed. Signature stamps are not allowed.
Enter Practitioner and Practice information in the appropriate field. You may use the practice stamp if applicable.
Practitioner should review the following and initial only if applicable.
Select one: Beneficiary's Primary Care Practitioner, Outpatient Specialty Practitioner, or Inpatient Practitioner.
The date of the beneficiary's last PCP visit must be < 90 days from Received Date by the IAE.
Signature stamp not allowed. “I hereby attest that the information contained herein is current, complete, and accurate to the best of my knowledge and belief.”
“I understand that my attestation may result in the provision of services which are paid for by state and federal funds and I also understand that whoever knowingly and willfully makes or causes to be made a false statement or representation may be prosecuted under the applicable federal and state laws.”
You are requesting a Medical Change of Status
Change of Status: Medical: Complete for medical change of status request only.
Section D, located on page 2, is a required field for all Medical Change of Status Requests.
You are requesting Managed Care Disenrollment
Section E: Managed Care Disenrollment: Medical. Complete if requesting disenrollment from Managed Care. Enter the information regarding the beneficiary's current plan, date of enrollment, effective date of disenrollment, current approved PCS hours, and current PCS provider.
Completed form should be faxed to NC LIFTSS prior to disenrollment date.
You are requesting a Non-Medical Change of Status
Sections F - G: Non-Medical Change of Status and Change of Provider Requests, located on pg. 3 of the form, shall be completed by the beneficiary, family member, legal guardian, home care provider, or residential provider.
Complete if requesting a Non-Medical Change of Status.
Enter the Facility License # and Date, if applicable.
Describe the specific change in condition and its impact on the beneficiary's need for hands on assistance (Required).
Form Submission: Fax NC LIFTSS at 1-833-521-2626 (toll free). Questions: Call NC LIFTSS at 1-833-522-5429.
You are requesting a Change of Provider
Complete if requesting a Change of Provider. Effective 11/1/2018 any Medicaid beneficiary referred to or seeking admission to Adult Care Homes (ACH) licensed under G.S. 131D-2.4 must be referred to a LME-MCO for the Referral Screening Verification Process (RSVP).
Adult Care Home providers licensed under G.S. 131D-2.4 shall not receive a PCS assessment or prior approval without verification of a Referral Screening ID (RSID).
If you have questions about your status in this process, please contact the Division of Mental Health at 919-981-2580.
Common questions about Form DHB-3051
Where do I file it?
DHB-3051 9/5/2024: Completed Request Forms should be submitted to NC LIFTSS via fax at 1-833-521-2626 (toll free).
Sources
[1] DHB-3051 (9/5/2024), Request for Independent Assessment for Personal Care Services, Attestation of Medical Need, North Carolina Division of Health Benefits (the Official source link on this page).