


Form DS-6 at a glance
What it is: Physician's Reporting Form: for use by a physician, physician assistant, or nurse practitioner to report an individual whose driving ability may be affected due to some physical or mental impairment.
Who signs: This form must be completed and signed by a licensed physician, physician assistant or nurse practitioner.
A filled-in Form DS-6 example: a physician reports a driver

How to fill out Form DS-6, box by box
Part 1 - Driver identification

Under Part 1 - Driver identification (please print), fill in Driver License Number, Last Name*, First Name*, M.I., Date of Birth (if not known, give approximate age), Street Address, City* and State, and Zip Code. * Required information: Last Name, First Name and City.
Part 2 - The condition, the medication and the opinion
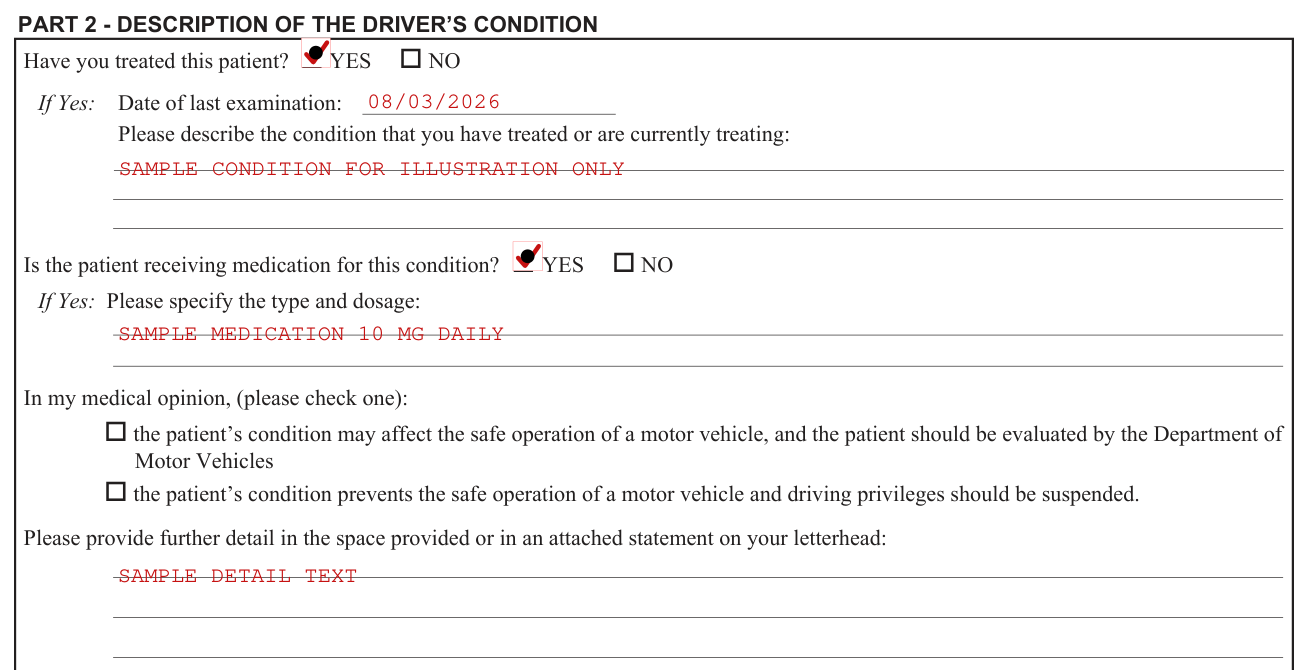
Have you treated this patient? YES or NO. If Yes: Date of last examination. Please describe the condition that you have treated or are currently treating.
Is the patient receiving medication for this condition? YES or NO. If Yes: Please specify the type and dosage.
In my medical opinion, (please check one): the patient's condition may affect the safe operation of a motor vehicle, and the patient should be evaluated by the Department of Motor Vehicles, or the patient's condition prevents the safe operation of a motor vehicle and driving privileges should be suspended.
Provide further detail in the space provided or in an attached statement on your letterhead.
Part 3 - Identification and certification of the practitioner
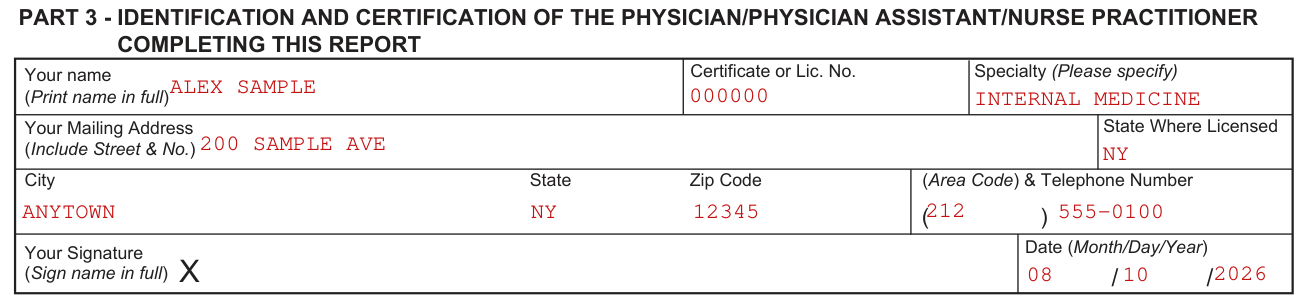
Under Part 3 - Identification and certification of the physician/physician assistant/nurse practitioner completing this report, print your name in full, then fill in Certificate or Lic. No., Specialty (Please specify), Your Mailing Address (Include Street & No.), State Where Licensed, City, State, Zip Code, (Area Code) & Telephone Number and Date (Month/Day/Year), and sign your name in full on Your Signature.
More rules for Form DS-6
Please provide all of the information requested in Parts 1 through 3, and sign and date the form.
If additional assistance is needed, contact the Medical Review Unit at (518) 474-0774, option #2 then option #3.
If your patient is an older driver, you may also visit the Resources for the Older Driver website at dmv.ny.gov/olderdriver.
Common questions about Form DS-6
Where do I file it?
Email the completed form to the Medical Review Unit at dmv.sm.MedicalReview@dmv.ny.gov OR mail the completed form to: Medical Review Unit, NYS Department of Motor Vehicles, 6 Empire State Plaza, Room 337, Albany, NY 12228
Sources
[1] Form DS-6 (7/26), Physician's Reporting Form, New York State Department of Motor Vehicles (the Official source link on this page).