


Form DHHS 116M at a glance
What it is: Form DHHS 116M, EMPLOYER'S HEALTH INSURANCE INFORMATION, State of Utah Department of Health and Human Services.
Where and when to file: Return Completed Form To: Department of Workforce Services, PO Box 143245, SLC, UT 84114-3245; Fax: 1-801-526-9500, Toll-Free Fax: 1-877-313-4717.
Have your employer's Human Resources representative or department who manages employee benefits complete this form for each employed household member.
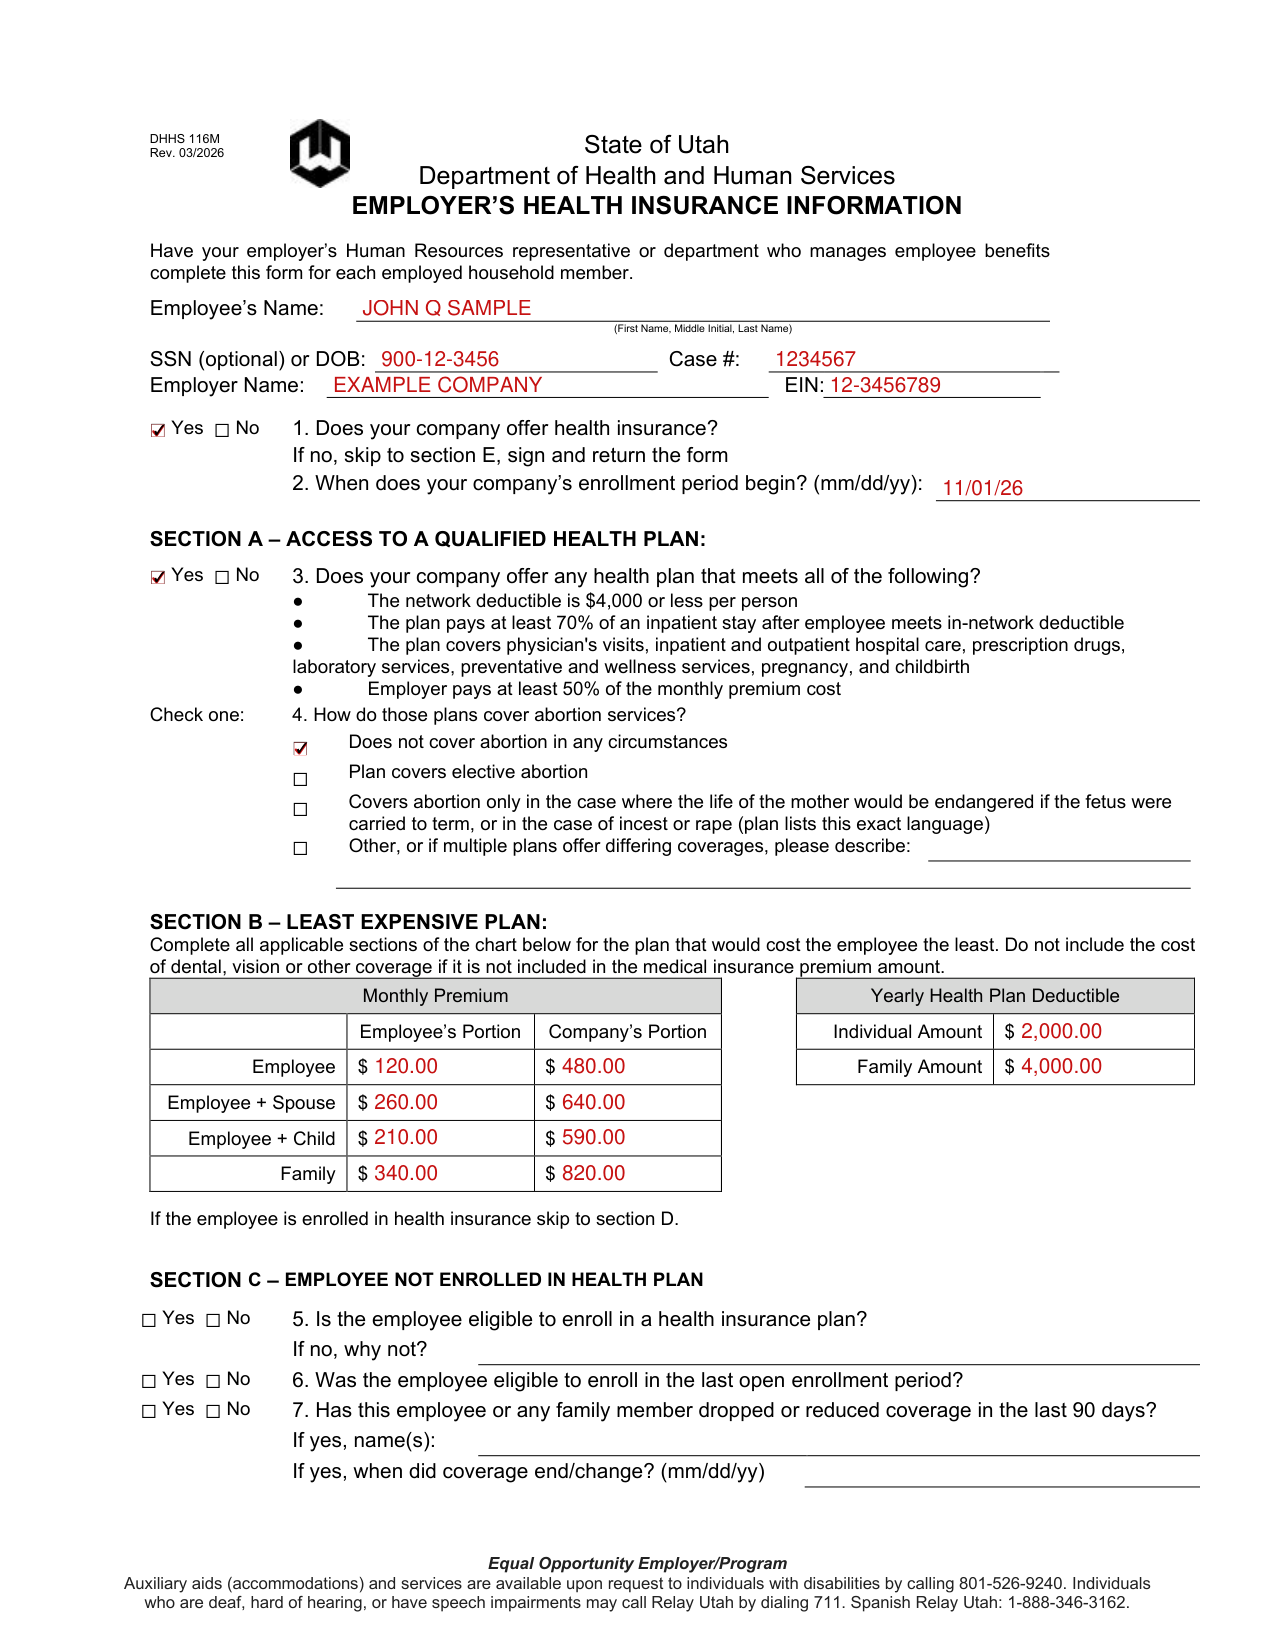
A filled-in Form DHHS 116M example: an employer lists an enrolled employee's plan
How to fill out Form DHHS 116M, box by box
Employee's Name, SSN (optional) or DOB, Case #, Employer Name and EIN

Enter the Employee's Name (First Name, Middle Initial, Last Name).
Enter the SSN (optional) or DOB, the Case #, the Employer Name and the EIN.
1 and 2: Does your company offer health insurance, and when does the enrollment period begin

Check Yes or No for 1. Does your company offer health insurance? If no, skip to section E, sign and return the form.
Enter the following in mm/dd/yy: 2. When does your company's enrollment period begin?
Section A - Access to a qualified health plan

Check Yes or No for 3. Does your company offer any health plan that meets all of the following? The network deductible is $4,000 or less per person; the plan pays at least 70% of an inpatient stay after employee meets in-network deductible; the plan covers physician's visits, inpatient and outpatient hospital care, prescription drugs, laboratory services, preventative and wellness services, pregnancy, and childbirth; employer pays at least 50% of the monthly premium cost (checked October 19, 2026).
Check one for 4. How do those plans cover abortion services? Does not cover abortion in any circumstances; Plan covers elective abortion; Covers abortion only in the case where the life of the mother would be endangered if the fetus were carried to term, or in the case of incest or rape (plan lists this exact language); Other, or if multiple plans offer differing coverages, please describe.
Section B - Least expensive plan
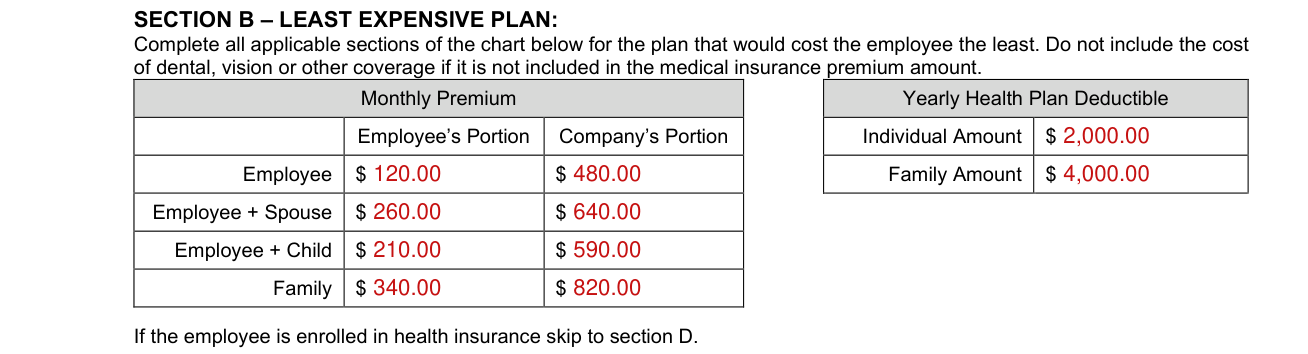
Complete all applicable sections of the chart for the plan that would cost the employee the least.
Do not include the cost of dental, vision or other coverage if it is not included in the medical insurance premium amount.
Enter the Monthly Premium, Employee's Portion and Company's Portion, for Employee, Employee + Spouse, Employee + Child and Family.
Enter the Yearly Health Plan Deductible, Individual Amount and Family Amount.
If the employee is enrolled in health insurance skip to section D.
Section C - Employee not enrolled in health plan
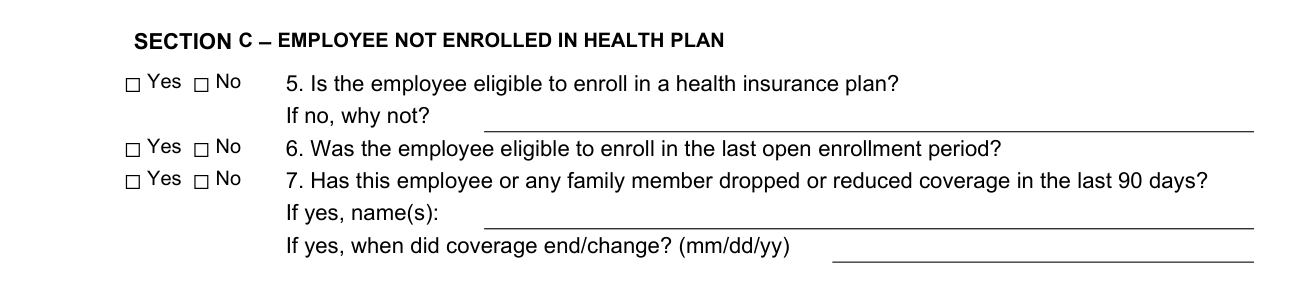
Check Yes or No for 5. Is the employee eligible to enroll in a health insurance plan? If no, enter why not.
Check Yes or No for 6. Was the employee eligible to enroll in the last open enrollment period?
Check Yes or No for 7. Has this employee or any family member dropped or reduced coverage in the last 90 days? If yes, enter the name(s) and, in mm/dd/yy, when did coverage end/change?
Section D - Employee's health plan information
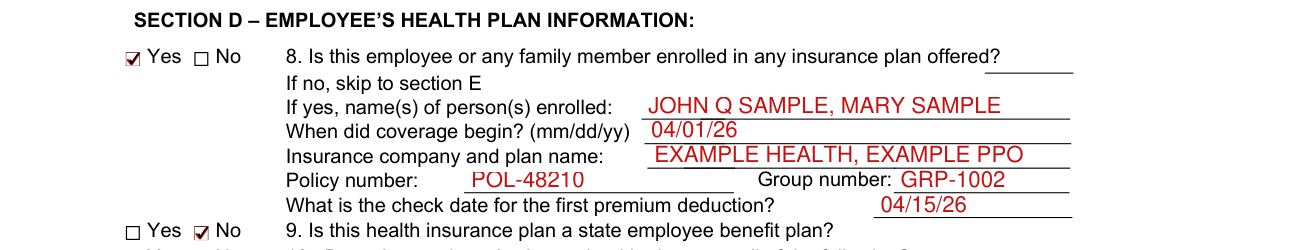
Check Yes or No for 8. Is this employee or any family member enrolled in any insurance plan offered? If no, skip to section E. If yes, enter name(s) of person(s) enrolled, when did coverage begin? (mm/dd/yy), insurance company and plan name, policy number, group number, and what is the check date for the first premium deduction?
Check Yes or No for 9. Is this health insurance plan a state employee benefit plan?
10 and 11: Does the employee's chosen health plan meet all of the following, and how does the plan cover abortion services

Check Yes or No for 10. Does the employee's chosen health plan meet all of the following? The network deductible is $4,000 or less per person; the plan pays at least 70% of an inpatient stay after employee meets in-network deductible; the plan covers physician's visits, inpatient and outpatient hospital care, prescription drugs, laboratory services, preventative and wellness services, pregnancy, and childbirth; employer pays at least 50% of the cost (checked October 19, 2026).
Check one for 11. How does the plan cover abortion services? This can typically be found in the paternity/pregnancy or exclusion sections of your policy. Does not cover abortion in any circumstances; Plan covers elective abortion; Covers abortion only in the case where the life of the mother would be endangered if the fetus were carried to term, or in the case of incest or rape (plan lists this exact language); Other, please describe.
12 and 13: What is the monthly premium cost of this plan, and how often is the premium deducted
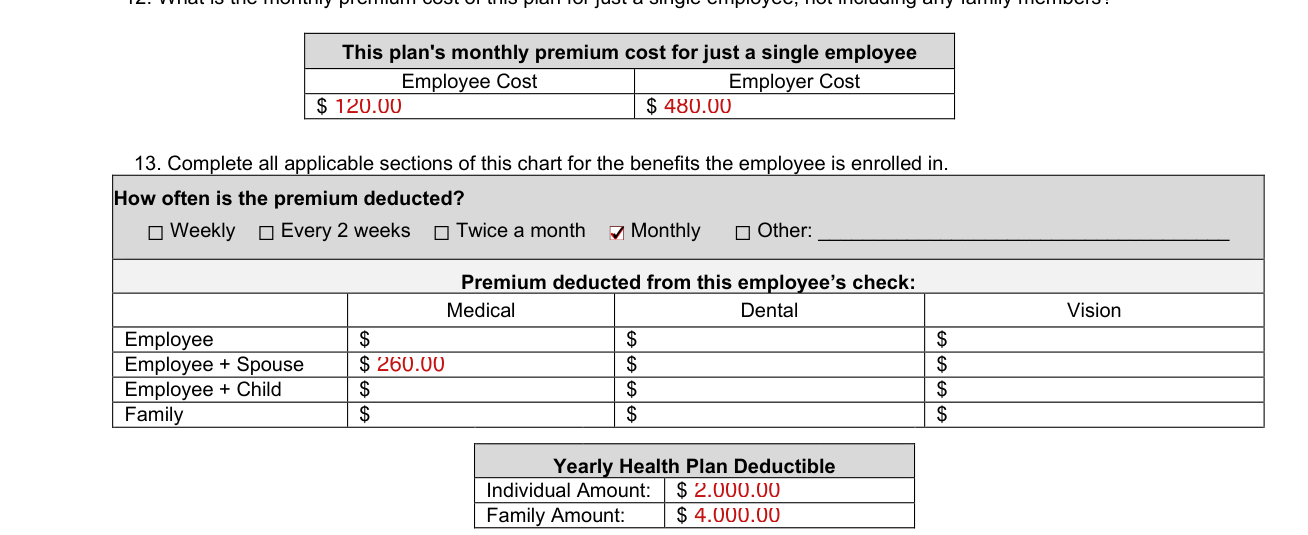
Enter the Employee Cost and the Employer Cost for 12. What is the monthly premium cost of this plan for just a single employee, not including any family members?
For 13., complete all applicable sections of this chart for the benefits the employee is enrolled in.
Check Weekly, Every 2 weeks, Twice a month, Monthly or Other: for How often is the premium deducted?
Enter the Premium deducted from this employee's check: Medical, Dental and Vision, for Employee, Employee + Spouse, Employee + Child and Family.
Enter the Individual Amount and the Family Amount of the Yearly Health Plan Deductible.
14. List any children who have dental coverage

List any children who have dental coverage.
Section E - Signature
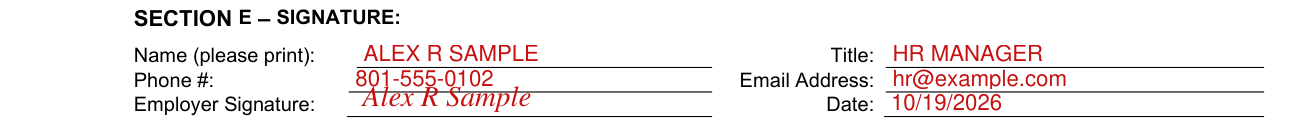
Enter Name (please print), Title, Phone #, Email Address, Employer Signature and Date.
Common questions about Form DHHS 116M
Where do I file it?
Return Completed Form To: Department of Workforce Services, PO Box 143245, SLC, UT 84114-3245; Fax: 1-801-526-9500, Toll-Free Fax: 1-877-313-4717.
Sources
[1] Form DHHS 116M (Rev. 03/2026), Employer's Health Insurance Information, State of Utah Department of Health and Human Services (the Official source link on this page).