

Form 8584 at a glance
What it is: Form 8584 December 2020-E, Comprehensive Nursing Assessment, is to be performed by a Registered Nurse.
Who signs: Participants in Comprehensive Assessment: Must complete section A, B orC; and RN section.
A filled-in Form 8584 example: a nurse fills out page 1
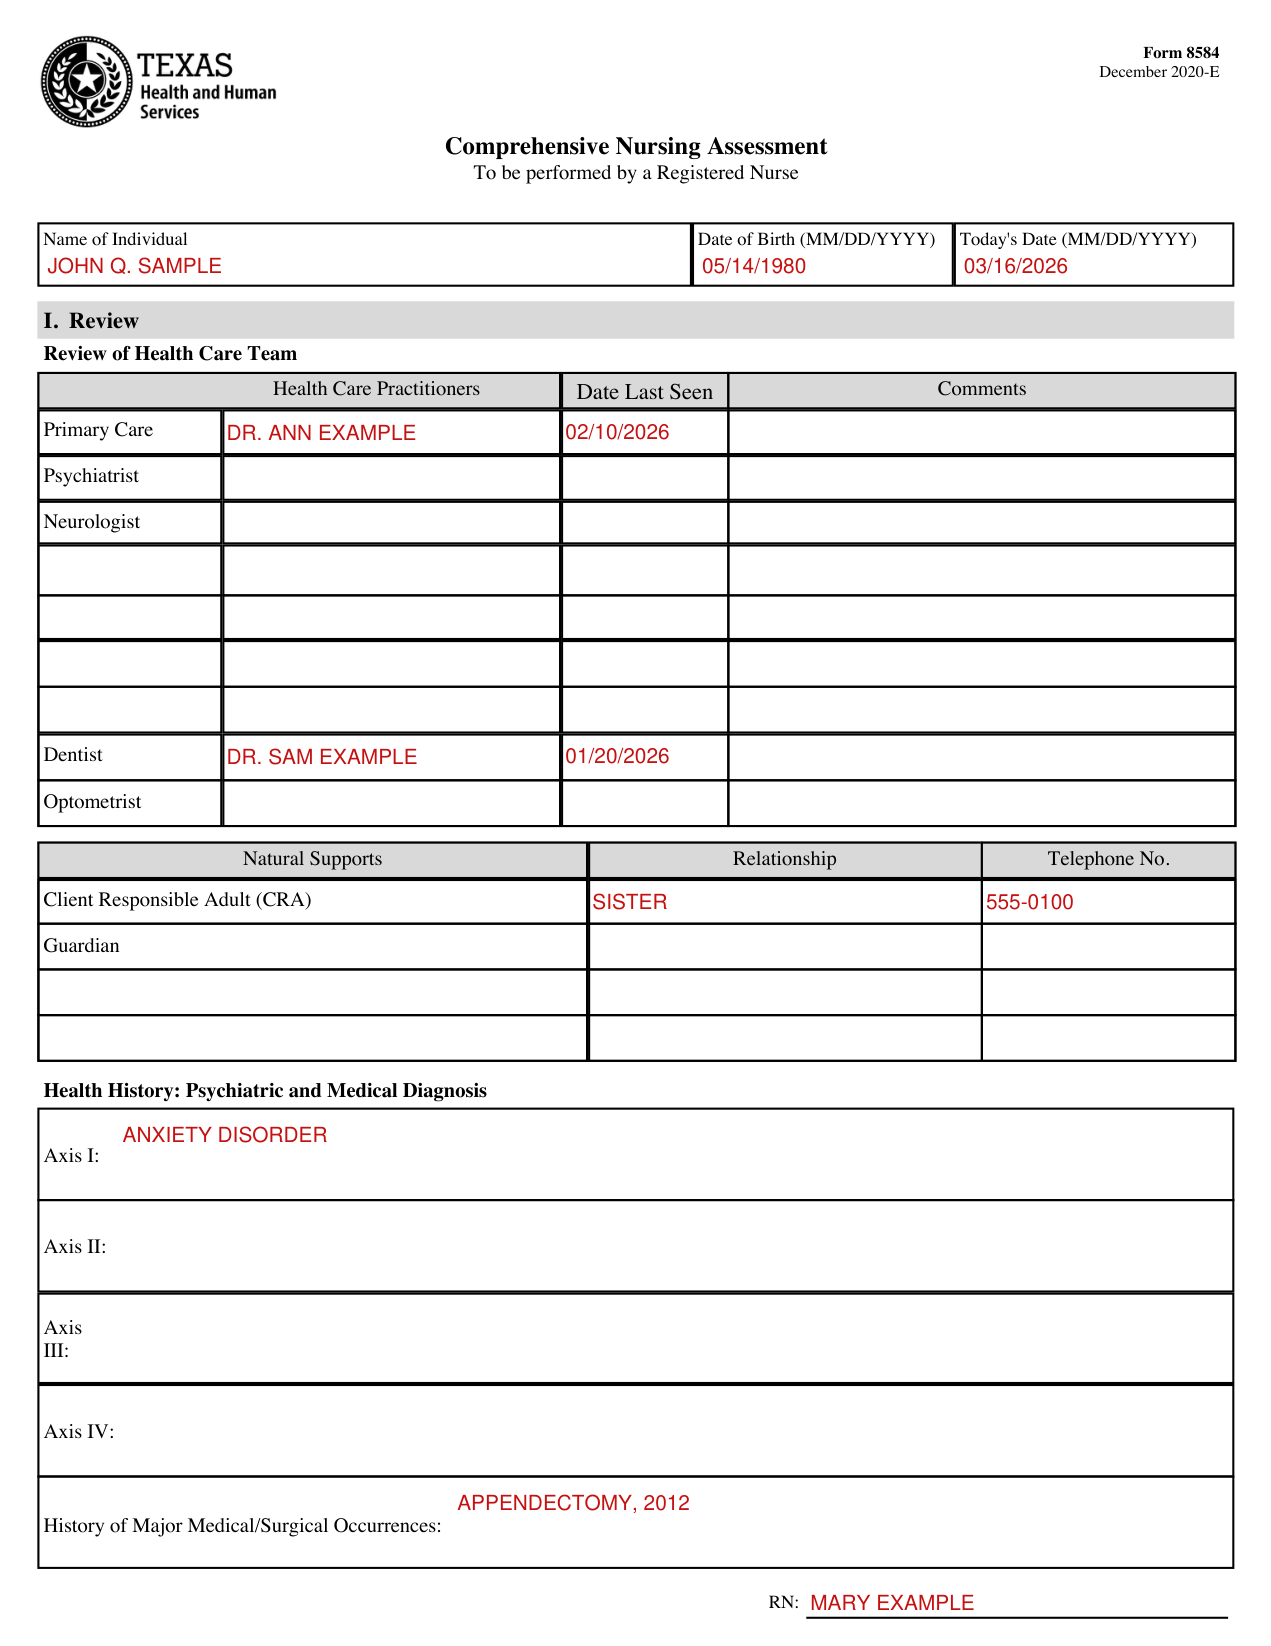
How to fill out Form 8584, box by box
Name of Individual, Date of Birth and Today's Date
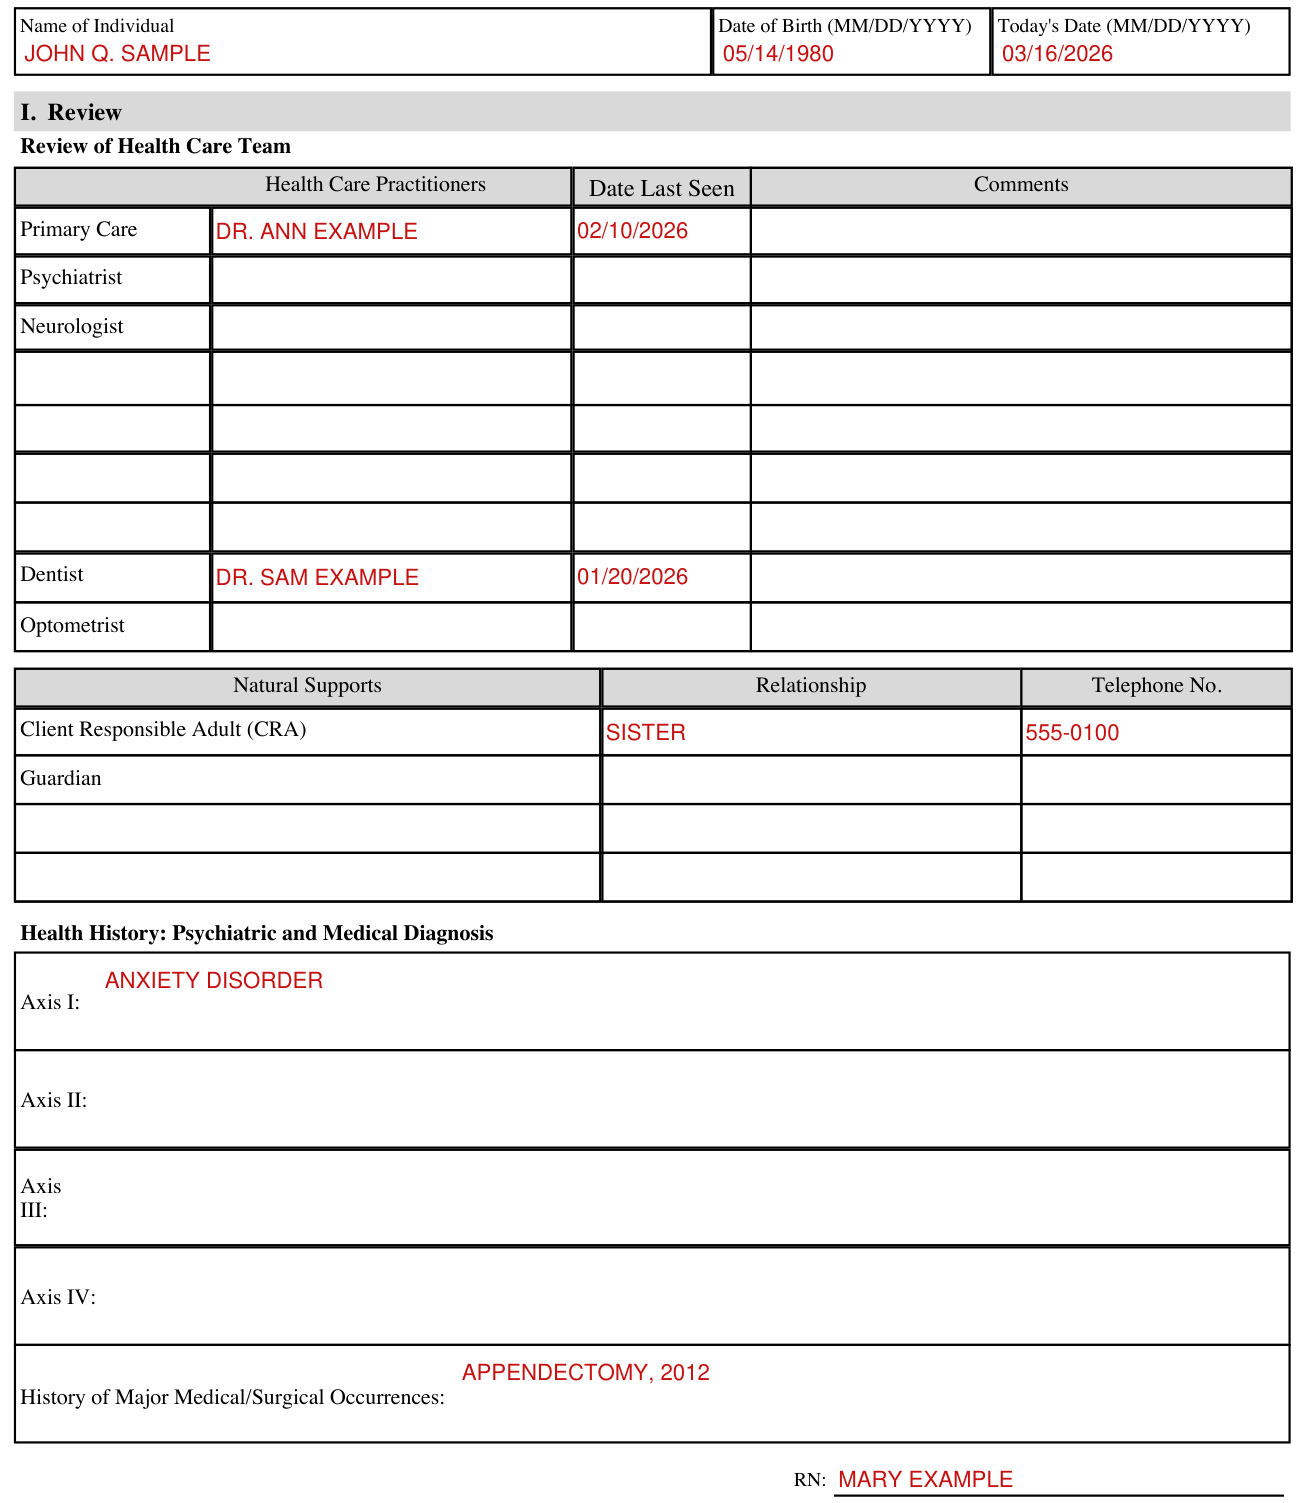
Fill in Name of Individual, Date of Birth (MM/DD/YYYY) and Today's Date (MM/DD/YYYY).
I. Review of Health Care Team
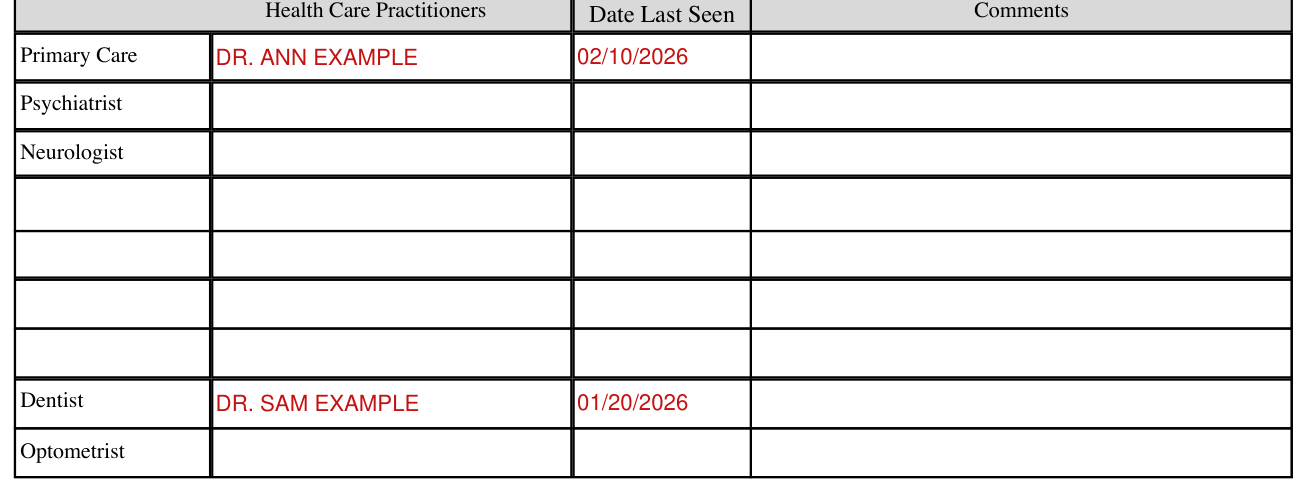
Under Review of Health Care Team, fill in Health Care Practitioners, Date Last Seen and Comments for Primary Care, Psychiatrist, Neurologist, Dentist and Optometrist.
Natural Supports
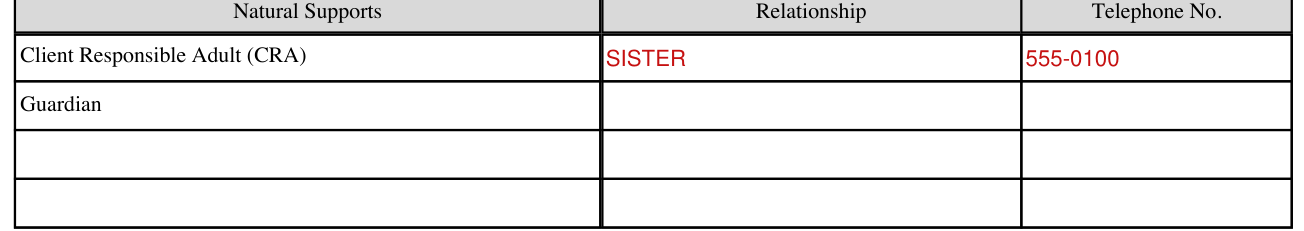
Under Natural Supports, fill in Relationship and Telephone No. for the Client Responsible Adult (CRA) and the Guardian.
Health History: Psychiatric and Medical Diagnosis
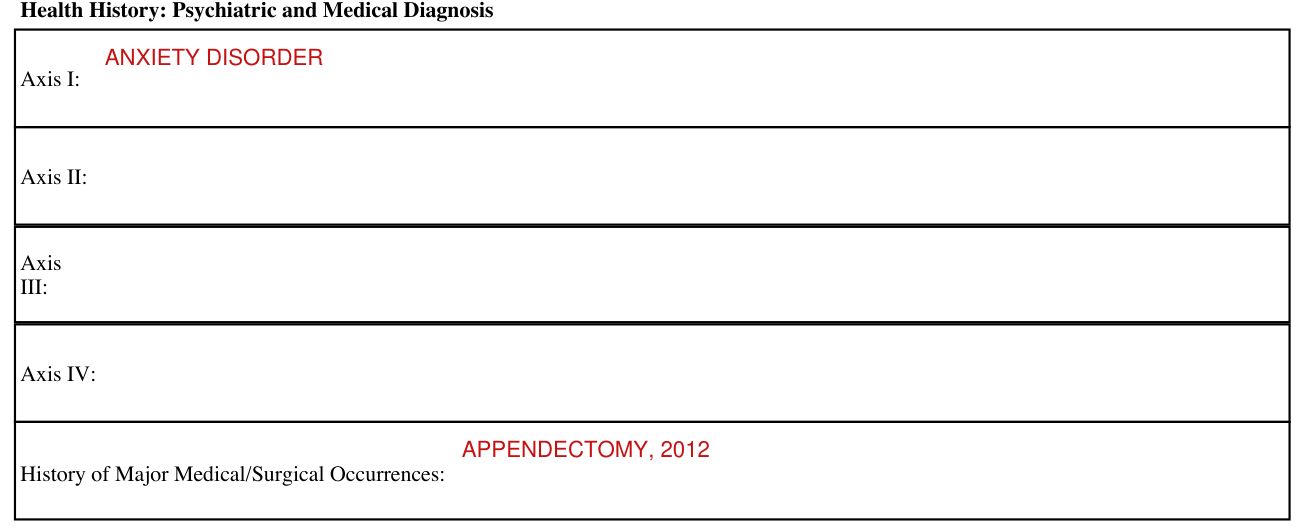
Under Health History: Psychiatric and Medical Diagnosis, fill in Axis I, Axis II, Axis III, Axis IV and History of Major Medical/Surgical Occurrences.
II. Current Status, III. Review of Systems, IV. Additional Health Status Information, V. Implementation Assessment, VI. Summary
II. Current Status
Review of Current Medications: Include OTCs, vitamins and herbs, with Medication, Dose, Freq., Route, Purpose/Rationale and Side Effects/Labs.
Fill in Allergies: Food, Environmental, etc.
Under Current medical and psychiatric history, briefly describe recent changes in health or behavioral status, hospitalizations, falls, seizure activity, restraints, etc., within the past year.
Write what is of primary concern/greatest expressed needs of the individual, legally authorized representative (LAR) or client's responsible adult (CRA) from their own perspective.
Under Vital Signs, fill in Blood Pressure, Pulse, Respirations, Temperature, Pain level, Blood Sugar, Weight and Height.
Under Labs, briefly review ordered labs, dates and abnormal values within the past year.
Under Fall Risk Assessment, mark: Has a fall risk assessment been completed?
If it applies, mark Yes (attached) and mark Fall risk due to: Neurological, Musculoskeletal or Unknown.
III. Review of Systems
III. Review of Systems: Neurological.
For the Abnormal Involuntary Movement Scale (AIMS) Assessment, mark Attached or Deferred.
Fill in Bowel sounds, Last bowel movement and Bowel habits (frequency and description).
List Medications influencing bowels (laxatives, anti-diarrheals, iron, calcium, anticholinergics, etc.)
For the Skin Assessment, mark Attached or Deferred.
Under Endocrine, mark Thyroid dysfunction and Diabetes if they apply; if yes, type.
IV. Additional Health Status Information
Under IV. Additional Health Status Information, Immunizations: fill in the Date last received for DPT, TOPV, HIB, MMR, TD, TDS and FLU SHOT.
Under Nutritional Assessment, mark how nutrition is received: Orally, Via jejunostomy tube, Via gastrotomy tube if residual, or Other.
Fill in average number of hours per night; difficulty falling asleep; number of times awake at night; number of naps during a day.
Under Substance Use/Abuse, fill in caffeine, tobacco, alcohol, recreational drugs, history of non-compliance with prescribed medications.
For Home Life, Work/School/Day Activity, Social Life and Spiritual Life, write Satisfaction/Desires.
Mental Status and Challenging Behaviors
Mental Status.
Under Challenging Behaviors, mark Are medications used to control any behaviors? Y N and Currently has a formal Behavior Plan? Y N.
For frequency: 1 = less than once per month; 2 = 1 to 3 x month; 3 = 1 to 6 x week; 4 = 1 to 10 x day; and 5 = 1 or more x hour.
For severity: 1 = mild; 2 = moderate; 3 = severe; and 4 = critical. Fill in Frequency, Severity and Last Exhibited.
Communication
Fill in Primary language. Mark ways the individual commonly communicates.
Mark ways that pain is communicated.
If able to use pain scale, mark Able to use pain scale and list type/name of pain scale.
V. Implementation Assessment
V. Implementation Assessment: under Health care and Decision Making Capacity, the preceding review of functional capabilities, physical and cognitive status, and limitations indicate this individual's highest level of ability to make health care decisions.
Probably can make higher level decisions (such as whether to undergo or withdraw life sustaining treatments that require understanding the nature, probable consequences, burdens and risks of proposed treatment).
Probably can make limited decisions that require simple understanding, able to direct own health care, including delegated tasks.
Probably can express agreement with decisions proposed by someone else.
Cannot effectively participate in any kind of health care decision making.
Support Systems: Discuss the adequacy, reliability, availability, ability to communicate effectively.
Under Safe Administration of Medications, mark RN Delegation Worksheet: Attached or N/A.
Check all that apply: CRA can safely direct as an HMA. No RN delegation is necessary.
RN delegation necessary to ensure safe medication administration. RN can safely authorize unlicensed personnel to administer medications for stable and predictable conditions as defined in §225.4(11) not requiring nursing judgment. Competency of each unlicensed personnel, including the ability to recognize and inform the RN of client changes related to the task must be verified by RN.
Individual (if competent), CRA (if one exists) or Provider Advocate Committee (PAC) must approve the decision of the RN to delegate tasks in writing.
Under Nurse Supervision, fill in the Name of Unlicensed Personnel and list all who were consulted in determining the level of nurse supervision for the named unlicensed personnel.
Fill in Frequency of required RN monitoring.
Participants in Comprehensive Assessment
Participants in Comprehensive Assessment: Must complete section A, B orC; and RN section.
Option A: In this situation, the individual does not have a guardian/LAR and is able to make decisions regarding health care. To be completed by the Individual.
SIGN, with Printed Name and Date.
Option B: In this situation, the individual cannot make decisions regarding health care or has asked for assistance. To be completed by the CRA.
If it applies, mark: I will be participating in decisions only, not directing care. No HMAs will be performed by unlicensed personnel.
SIGN, with Printed Name and Date.
Option C: In this situation, the individual cannot make decisions regarding health care and does not have a single identified adult who is willing and able to participate in decisions about the overall management of the individual's health care. [§225.1(a)(2)] Provider Advocate Committee (PAC) will act as CRA (form attached).
Registered Nurse (RN): I have developed this plan and retain accountability for delegated tasks. Each unlicensed personnel's competency will be verified before allowing delegated tasks to be performed without direct nursing supervision. An RN will be immediately accessible by phone to the unlicensed personnel when the task is performed.
SIGN, with Printed Name and Date.
VI. Summary
VI. Summary: under Summary/Clinical Impressions, fill in Strengths as related to health, Consultations recommended and Summary.
Under Nursing Service Plan, fill in Concerns/Nursing Diagnoses.
Fill in Intervention/Strategies with the Implementation Strategy, Objectives, Start Date and Target Completion.
SIGN, with Printed Name and Credentials and Date.
Review of Comprehensive Nursing Assessment by RN
Note: The nursing assessment must be reviewed at least annually to verify information remains current and decisions remain appropriate.
Review of Comprehensive Nursing Assessment by RN: fill in the Date of Review and Purpose (must check one): review of a temporary or permanent change in the individual's physical health, support system, mental status, social functioning, ability to perform activities of daily living or health maintenance activities, or medication or treatment regimen; review assessments, documentation and decisions made by a previous RN; or annual review of assessments, documentation and decisions to verify information remains current and decisions remain appropriate.
Fill in Description of Review, Action Taken by RN and Change(s) in Nursing Service Plan.
Mark No change required or fill in Nursing service plan revisions, then SIGN and Date.
Sources
[1] Form 8584 (December 2020-E), Comprehensive Nursing Assessment, Texas Health and Human Services (the Official source link on this page).
