


Form 3485-ENG-DPH at a glance
What it is: Form 3485-ENG-DPH, the Bureau of EMS and Trauma Interfacility Transport Form, records any drugs, devices and/or ventilator settings that may be required for patient care during an interfacility transport.
Who signs: Part A (Drug Report), Part B (Device Report) and Part C (Ventilator Settings) shall be completed as indicated, signed by the sending facility and attached to the EMS ePCR once transport is complete.
The form will be completed by the sending facilities medical provider that is in charge of patient care (RN / RT / PA / NP / MD / DO).
A filled-in Form 3485-ENG-DPH example: a nurse completes the drug report

How to fill out Form 3485-ENG-DPH, box by box
Patient Name, DOB, Physician and Facility
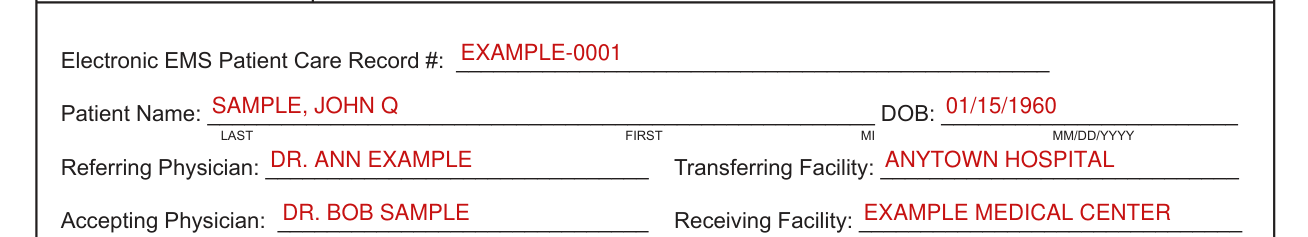
Enter the Electronic EMS Patient Care Record #.
Enter the Patient Name (LAST FIRST MI) and the DOB (MM/DD/YYYY).
Enter the Referring Physician, the Transferring Facility, the Accepting Physician and the Receiving Facility.
Diagnosis and last vital signs

Enter the DIAGNOSIS as (1), (2) and (3), and the LAST VITAL SIGNS: Time, Initials, HR, B/P, RR, SpO2, BGL and Other.
IV fluids and medications

Fill in IV Fluids, Rate, Medications, Dosage / Rate/Concentration and Comments/Additional Orders.
Signing Part A

This report was given by (Print name): RN / PA / NP / MD / DO, with Signature, Date and Time. None of the drugs being sent with this patient are part of an experimental program.
This report was accepted by (EMT-P signature), with the Date.
Part B devices

Enter the DOB (MM/DD/YYYY), the Referring Physician, the Transferring Facility, the Accepting Physician and the Receiving Facility.
Check all devices being used, or check Not Applicable.
Automatic Internal Cardiac Defibrillator (AICD); Arterial Lines, Arterial Sheathes; Tube Thoracostomy/Chest Tube; Percutaneously Placed Central Venous Catheters (does not include Swan-Ganz catheters); Peritoneal Dialysis Catheters; Epidural Catheters; Urethral/Suprapubic Catheter; Implantable Central Venous Catheters; Nasogastric/Orogastric Tubes; Surgically Placed Gastrointestinal Tubes; Percutaneous Drainage Tubes; Completely Implantable Venous Access Port; Surgical Drains.
Add any Comments/Additional Orders.
Signing Part B

Given by (print name): RN / PA / NP / MD / DO, Signature, Date, Time. This report was accepted by (EMT-Paramedic), with Signature, Date and Time.
Part C ventilator settings
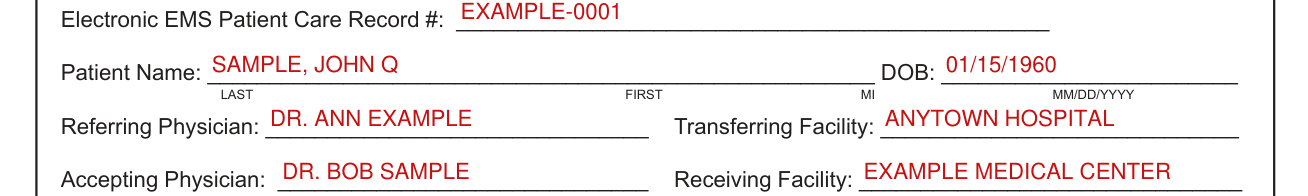
Enter the Electronic EMS Patient Care Record #, the Patient Name (LAST FIRST MI), the DOB (MM/DD/YYYY), the Referring Physician, the Transferring Facility, the Accepting Physician and the Receiving Facility.
If a ventilator is used during interfacility transport the following information MUST be reported to the receiving Paramedic and attested to by the RT / NP / PA / MD / DO turning over the patient.
Facility Settings: to be filled out by RT/NP/PA/MD/DO.
Initial Transport Settings: to be filled out by EMS Provider.
Mode (check one): AC, SIMV, PSV, PRVC, BiPAP or Other.
Patient Sedated: No, Induction or Maintenance. Patient Paralyzed: No, Induction or Maintenance.
Enter the ET Tube Size, the Depth @ Teeth/Lip, the Respiratory Set Rate, the Actual Rate, the Tidal Volume (VT), the Fraction of Inspired Oxygen (FiO2), Insp. Press/PS, PEEP, I:E ratio, PIP, SpO2 and ETCO2.
Add any Additional Orders/ Comments.
Signing Part C

The equipment is able to meet the settings and the Paramedic attests to competency to operate this equipment during transport: Paramedic Signature, Date and Time.
Given by (print name): RT / PA / NP / MD / DO, Signature, Date, Time.
Accepted by (EMT-Paramedic): Signature, Date, Time.
More rules for Form 3485-ENG-DPH
The form is filed with the agencies ePCR (electronic patient care report) and uploaded into the state database.
It is maintained by retention schedule 10010 - Licensed Provider Files.
EMS Service must retain a copy of this form for their records. If any problems are experienced en route, the EMT-P must contact on-line medical control.
Original Copy: Sending Facility. Copy 2: Accepting Facility. Copy 3: Transport agency.
Before you go
Check the interfacility devices being used in this transport on Device Report, Part B, and Ventilator Settings, Part C.
Sources
[1] Form 3485-ENG-DPH (05/2025), Interfacility Transport Form, South Carolina Department of Public Health (the Official source link on this page).