Form Doh 5059 PDF Details

Understanding the specifics of the DOH 5059 form is crucial for Medicaid clients in New York State who are considering their options regarding Health Home care management and services. This form serves as an official opt-out document for those eligible for but not interested in enrolling in Health Home programs at the current time. It provides a structured way for clients to assert their decision after having a detailed discussion with either a Health Home care manager or a representative from their Medicaid Managed Care Plan about the benefits and offerings of Health Home services. In addition to acknowledging a client's refusal to participate, the form also outlines the necessity for those eligible for Office for People With Developmental Disabilities’ (OPWDD) Home and Community Based Services (HCBS) to enroll in an alternative form of care management should they opt-out of Health Home services. This attestation includes areas for the signature of the client, and if applicable, their parent, guardian, or legally authorized representative, as well as the names and signatures of the care manager or Medicaid Managed Care Plan representative who provided the program information. Moreover, the document ensures clients are aware they can opt into Health Home services in the future if they change their mind, detailing contact information for easy access to enrollment. The DOH 5059 form stands as a critical tool for aligning a client's healthcare services with their personal choices and needs.

QuestionAnswer
Form NameForm Doh 5059
Form Length1 pages
Fillable?No
Fillable fields0
Avg. time to fill out15 sec
Other namesnys opt out letter 2021, nys opt out letter 2020, doh opt out form, nys assessment opt out letter

How to Fill Out Form DOH-5059

Form DOH-5059 at a glance

What it is: The New York State Department of Health Medicaid Health Home Opt-out Form is for use by Health Home eligible Medicaid client.

Who signs: Write the Name of Medicaid Client (print), the Original Signature of Medicaid Client and the Date. Write the Name of Health Home Care Manager (print), the Original Signature of Health Home Care Manager and the Date. Write the Name of Medicaid Managed Care Plan Representative (print), the Original Signature of Medicaid Managed Care Plan Representative and the Date.

A filled-in Form DOH-5059 example: a client opts out after meeting the care manager

Form DOH-5059 example filled out, example: a client opts out after meeting the care manager
A New York Medicaid client fills out the Health Home Opt-out Form. The client met a Health Home care manager and decided not to join the program at this time. The picture shows the client's copy, and its names and figures are sample values. The client names the Health Home, so Name of Medicaid Managed Care Plan stays empty. The care manager did not call the client, so the box and Reason for Opting Out in the part for use by Health Home Care Manager or Medicaid Managed Care Plan Representative stay empty. The client signs without a parent, guardian or legally authorized representative, so the lines for the parent, guardian or legally authorized representative stay empty. The care manager signs, so the lines for the Medicaid Managed Care Plan Representative stay empty.

How to fill out Form DOH-5059, box by box

Attestation Statement

Form DOH-5059 example filled out, attestation Statement

Mark the box for I have met with the Health Home care manager for, and write the Name of Health Home, or the Name of Medicaid Managed Care Plan for the representative from my Medicaid Managed Care Plan, who has explained the Health Home program to me and the Health Home care management services I can get. I have decided not to join the Health Home program at this time.

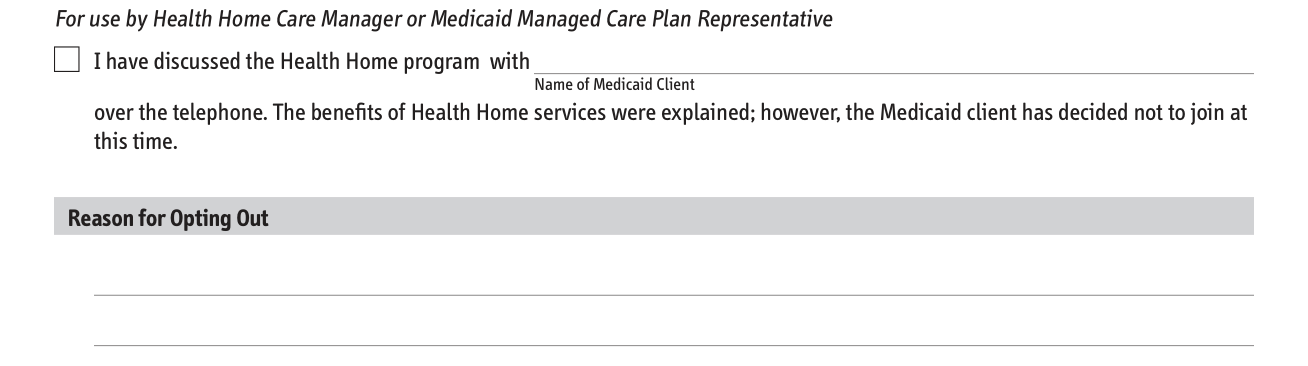
For use by Health Home Care Manager or Medicaid Managed Care Plan Representative
Form DOH-5059 example filled out, for use by Health Home Care Manager or Medicaid Managed Care Plan Representative

For use by Health Home Care Manager or Medicaid Managed Care Plan Representative: I have discussed the Health Home program with Name of Medicaid Client over the telephone. The benefits of Health Home services were explained; however, the Medicaid client has decided not to join at this time. Write the Reason for Opting Out.

Signatures
Form DOH-5059 example filled out, signatures

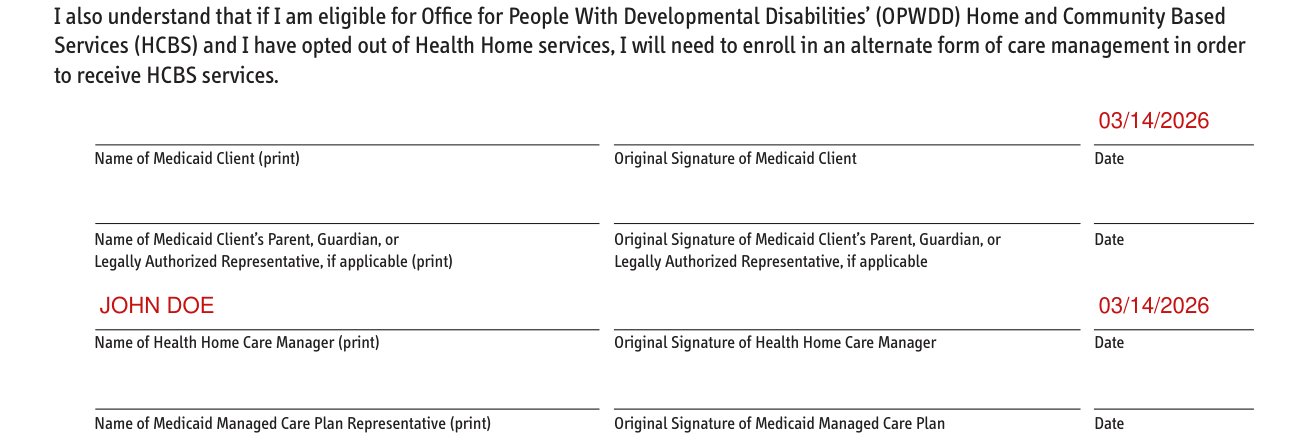
Under Signatures: I understand that I will not get a Health Home care manager or Health Home services.

I also understand that if I am eligible for Office for People With Developmental Disabilities' (OPWDD) Home and Community Based Services (HCBS) and I have opted out of Health Home services, I will need to enroll in an alternate form of care management in order to receive HCBS services.

Write the Name of Medicaid Client's Parent, Guardian, or Legally Authorized Representative, if applicable (print), the Original Signature of Medicaid Client's Parent, Guardian, or Legally Authorized Representative, if applicable and the Date.

If your situation is different

You would ever like to get Health Home services

NOTE: If you would ever like to get Health Home services, contact the New York State Medicaid Program by calling the Medicaid Call Center at 1-800-541-2831, or your Medicaid Managed Care Plan.

Sources

[1] Form DOH-5059 (4/19), Health Home Opt-out Form, New York State Department of Health (the Official source link on this page).

Please rate Form Doh 5059

1 Votes
If you believe this page is infringing on your copyright, please familiarize yourself with and follow our DMCA notice and takedown process - click here to proceed .