


Form FOH-6 at a glance
What it is: Form FOH-6, Authorization for Disclosure of Information, is used by FOH to obtain medical certification related to your Family Medical Leave Act (FMLA) and Reasonable Accommodation request from your health care provider.
Who signs: In Section 5 Employee Signature, enter the Name of patient, Patient signature and Date signed.
A filled-in Form FOH-6 example: an IRS employee requests FMLA leave

How to fill out Form FOH-6, box by box
Section 1 Employee Information
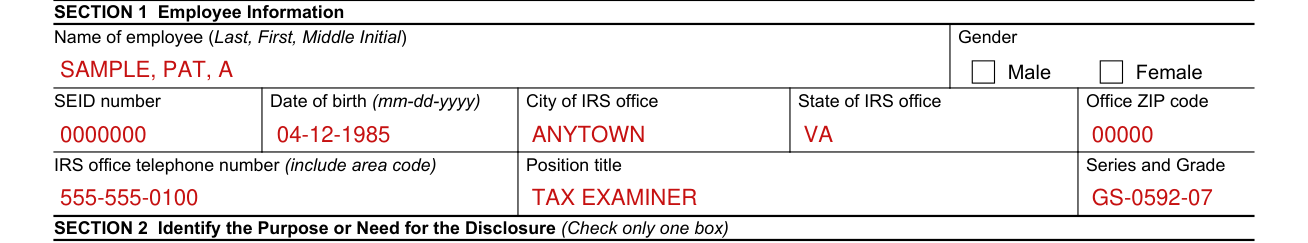
In Section 1 Employee Information, enter the Name of employee (Last, First, Middle Initial), Gender, SEID number, Date of birth (mm-dd-yyyy), City of IRS office, State of IRS office, Office ZIP code, IRS office telephone number (include area code), Position title, and Series and Grade.
Section 2 Identify the Purpose or Need for the Disclosure

In Section 2 Identify the Purpose or Need for the Disclosure, check only one box: ERGO - Ergonomic Assessment, RA - Reasonable Accommodation, FMLA - Family Medical Leave Act, or Other.
Section 3 Employee's Treating Health Care Provider Contact Information
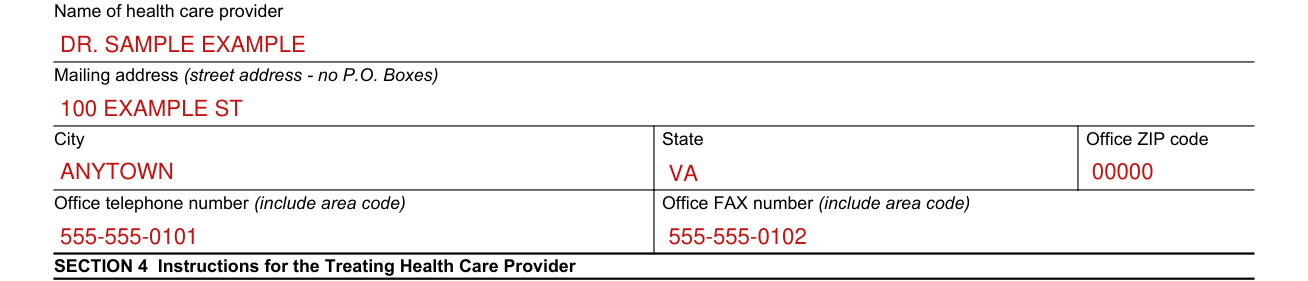
In Section 3 Employee's Treating Health Care Provider Contact Information, enter the Name of health care provider and the Mailing address (street address - no P.O. Boxes), then City, State, Office ZIP code, Office telephone number (include area code) and Office FAX number (include area code).
Section 4 Instructions for the Treating Health Care Provider

Your response should be your best estimate based upon your medical knowledge, experience, and examination of the patient. Be as specific as you can; terms such as “lifetime,” “unknown,” or “indeterminate” may not be sufficient to determine FMLA or RA coverage. Limit your responses to the condition for which the employee is seeking leave.
Enter the Name of patient. You are hereby authorized to furnish information from the record of the patient named, which is in the record system of your facility, and release it to: Federal Occupational Health (FOH) Services, Bethesda, MD FAX number 301-594-3321.
Section 5 Signature
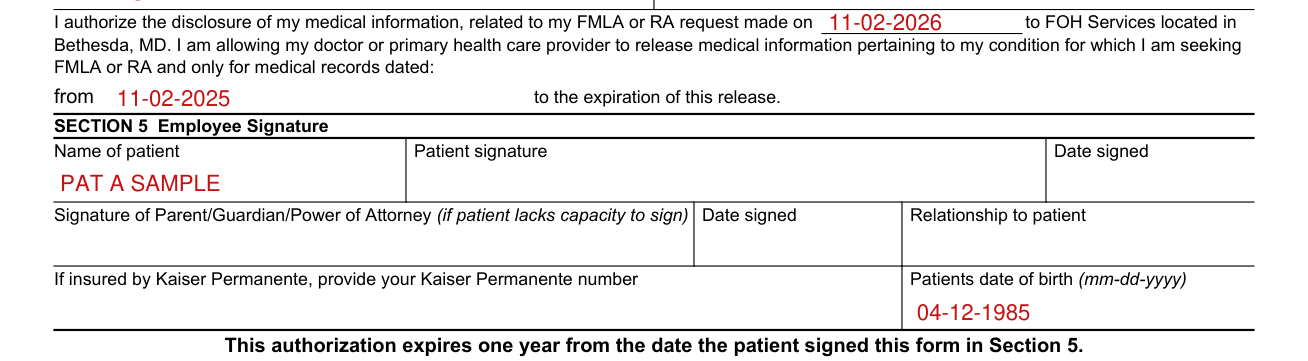
Enter the date of your FMLA or RA request. Release medical information only for medical records dated: from the first date to the expiration of this release.
Enter the Signature of Parent/Guardian/Power of Attorney (if patient lacks capacity to sign), Date signed and Relationship to patient.
Enter the Patients date of birth (mm-dd-yyyy). If insured by Kaiser Permanente, provide your Kaiser Permanente number.
More rules for Form FOH-6
The use of this form is voluntary.
This authorization expires one year from the date the patient signed this form in Section 5.
This authorization is subject to revocation by the employee at any time except to the extent that FOH has already taken action in reliance on it.
Common questions about Form FOH-6
Is there a penalty?
Any person who knowingly and willfully requests or obtains any record concerning an individual from a Federal agency under false pretenses shall be guilty of a misdemeanor.
Sources
[1] Form FOH-6 (1-2013) (Form 14258 (1-2013)), Authorization for Disclosure of Information, Department of Health and Human Services, Federal Occupational Health (FOH) Services (the Official source link on this page).