
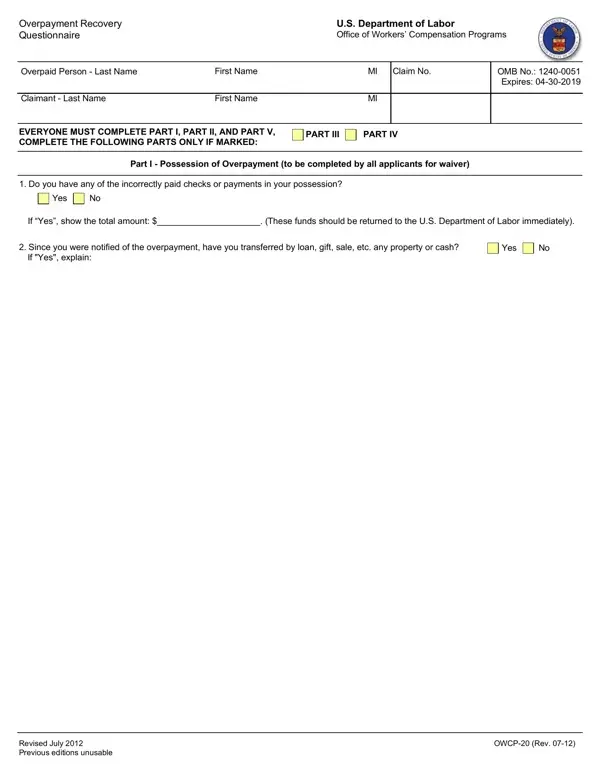
Form OWCP-20 at a glance
What it is: The Overpayment Recovery Questionnaire is from the U.S. Department of Labor Office of Workers' Compensation Programs.
Who signs: The signature line is for the Signature of Overpaid Person or Representative Payee, with the Date - Month, day, year.
Part I, Possession of Overpayment, is to be completed by all applicants for waiver.
Everyone must complete Part I, Part II, and Part V; complete the following parts only if marked:
Part III, Part IV.
A filled-in Form OWCP-20 example: a representative payee fills out the questionnaire
How to fill out Form OWCP-20, box by box
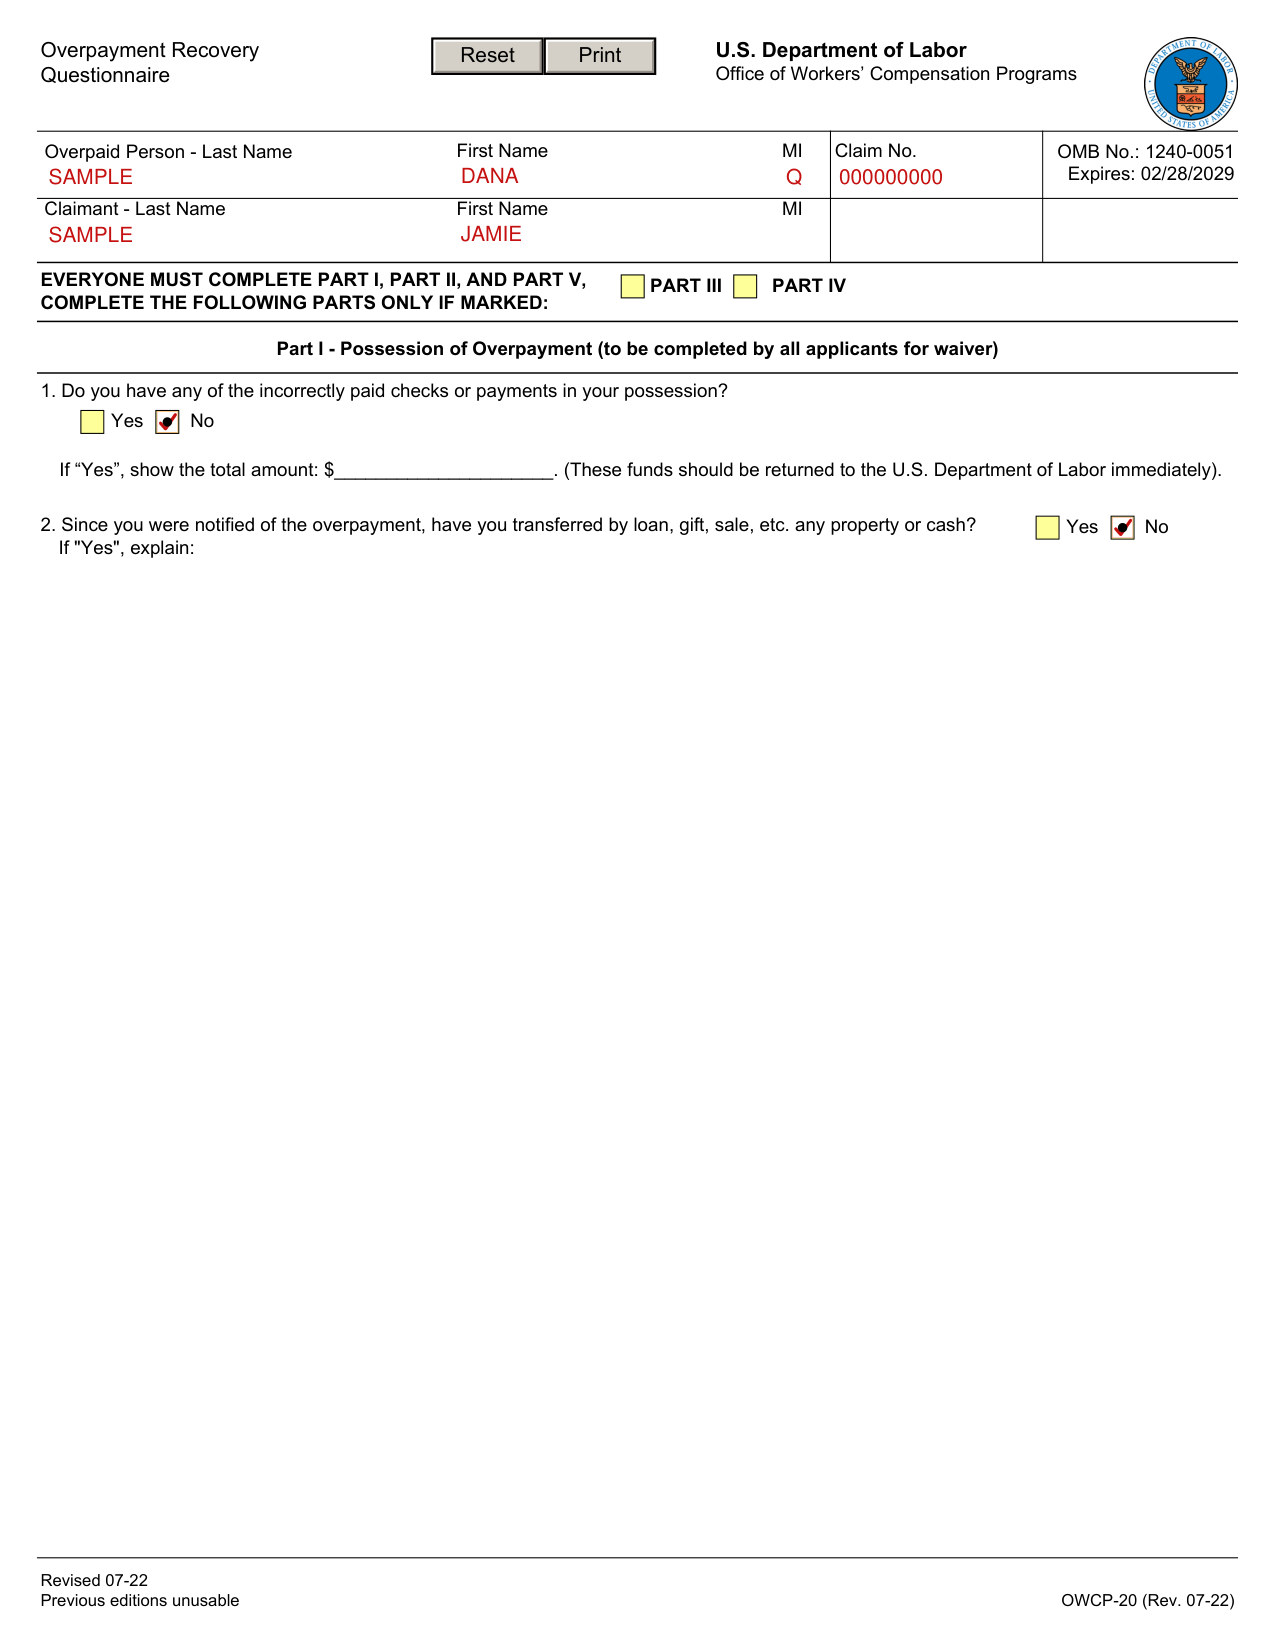
Name, claim number and claimant

Write the Overpaid Person's Last Name, First Name and MI, the Claim No., and the Claimant's First Name, Last Name and MI.
Part I - Possession of Overpayment
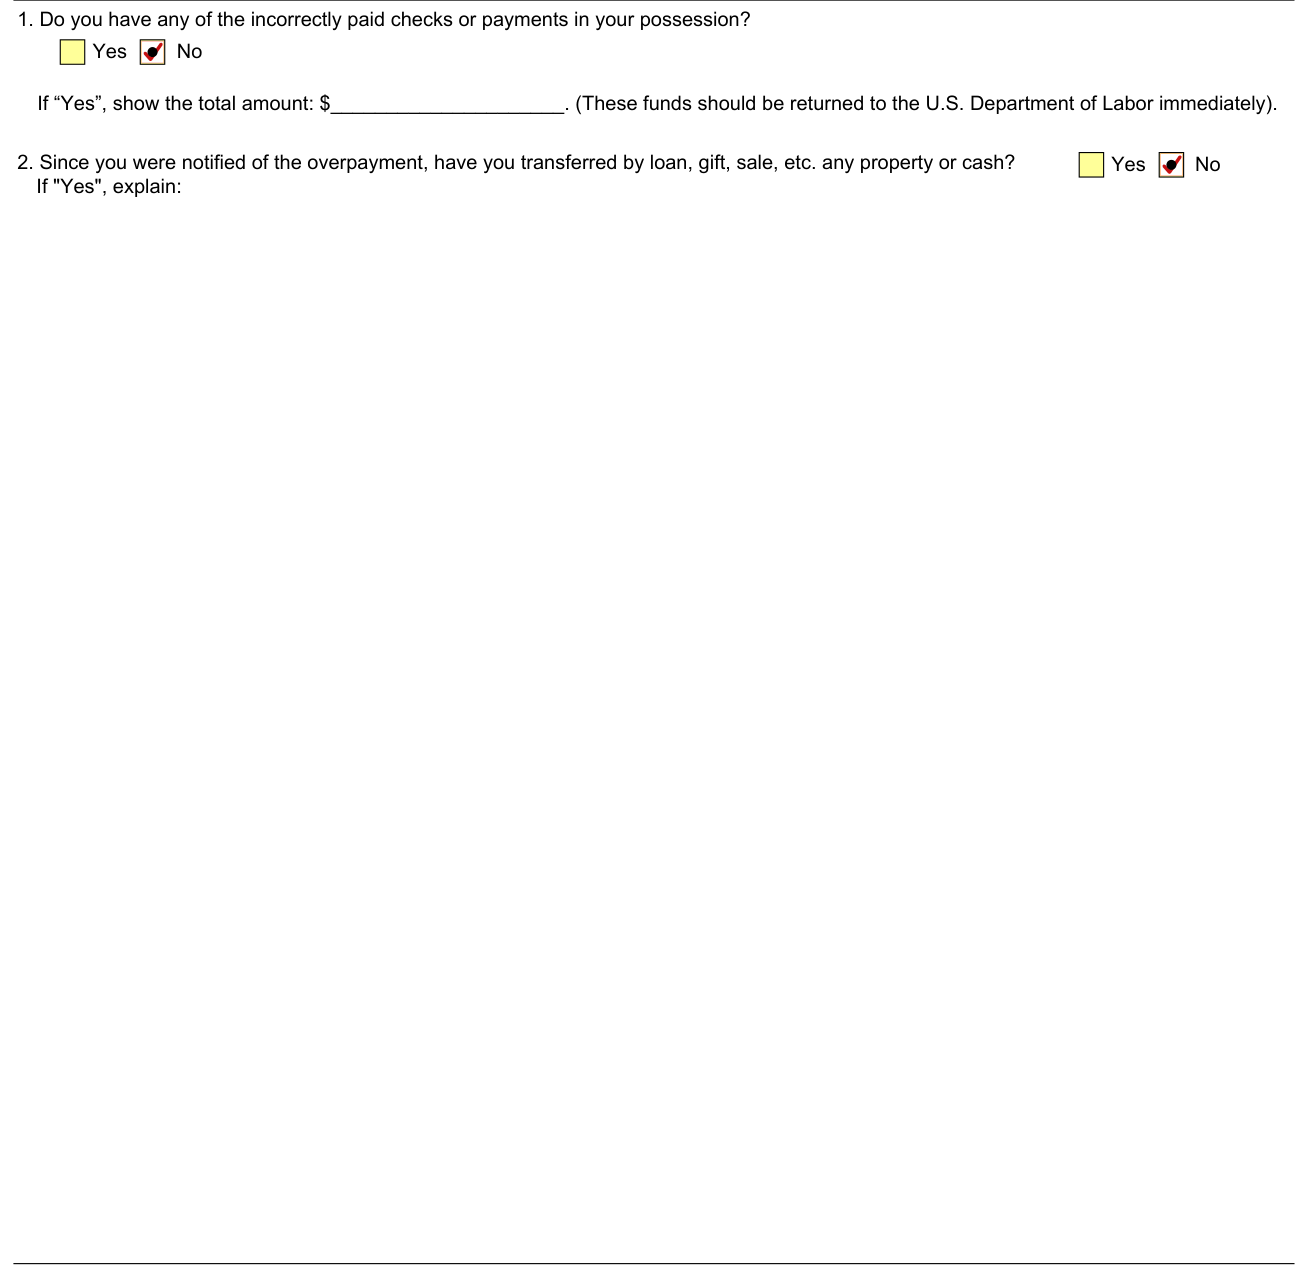
Do you have any of the incorrectly paid checks or payments in your possession? If “Yes”, show the total amount. These funds should be returned to the U.S. Department of Labor immediately.
Since you were notified of the overpayment, have you transferred by loan, gift, sale, etc. any property or cash? If "Yes", explain.
Part II - Refund Questionnaire: monthly income
Part II, the Refund Questionnaire, is to be completed by the person for whom repayment of the overpayment would cause undue hardship.
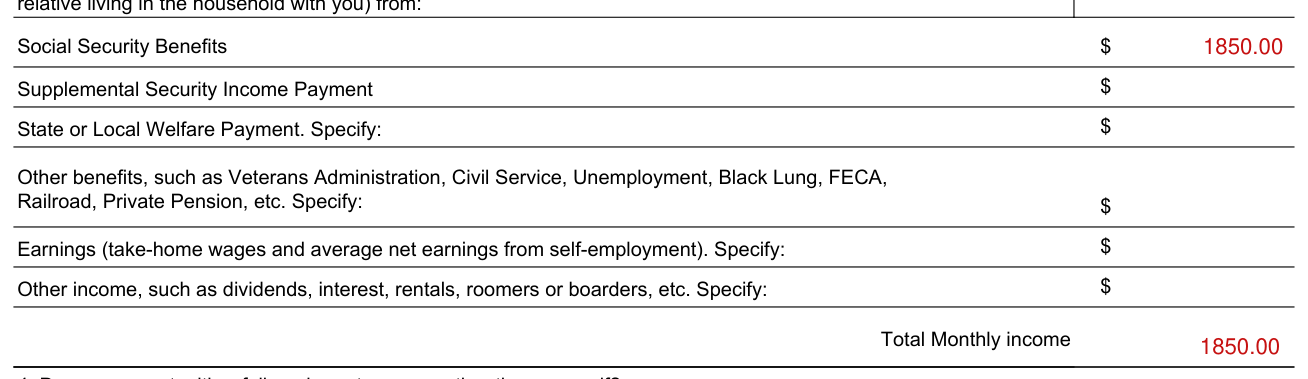
List your monthly income, including any income of your spouse or any dependent relative living in the household with you.
Social Security Benefits. Supplemental Security Income Payment. State or Local Welfare Payment. Specify. Other benefits, such as Veterans Administration, Civil Service, Unemployment, Black Lung, FECA, Railroad, Private Pension, etc. Specify. Earnings (take-home wages and average net earnings from self-employment). Specify. Other income, such as dividends, interest, rentals, roomers or boarders, etc. Specify.
Enter the Total Monthly income.
Do you support anyone other than yourself

Do you support, either fully or in part, anyone other than yourself? Yes No. If "Yes", give the following information about each person you support:
Name, Address, Age, Relationship To You (If None, Enter "None").
Monthly expenses
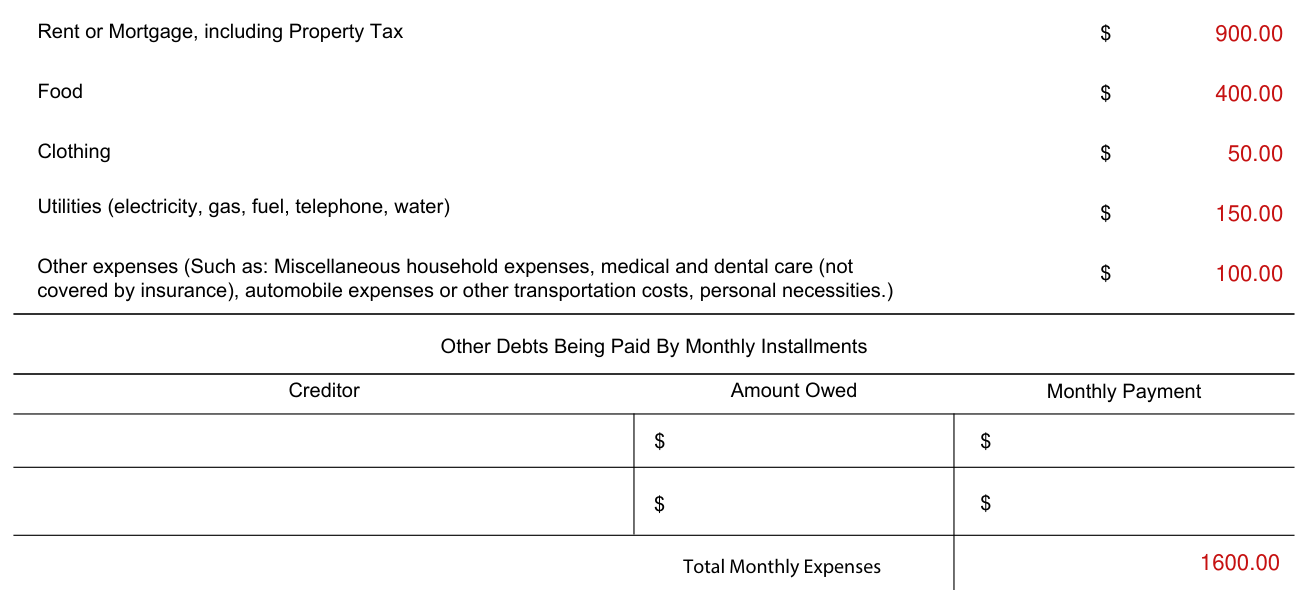
List the usual expenses of your household on a monthly basis: Rent or Mortgage, including Property Tax, Food, Clothing, and Utilities (electricity, gas, fuel, telephone, water).
Under Other expenses, list miscellaneous household expenses, medical and dental care (not covered by insurance), automobile expenses or other transportation costs, and personal necessities.
Other Debts Being Paid By Monthly Installments: Creditor, Amount Owed and Monthly Payment.
Enter the Total Monthly Expenses.
Valuable property and funds
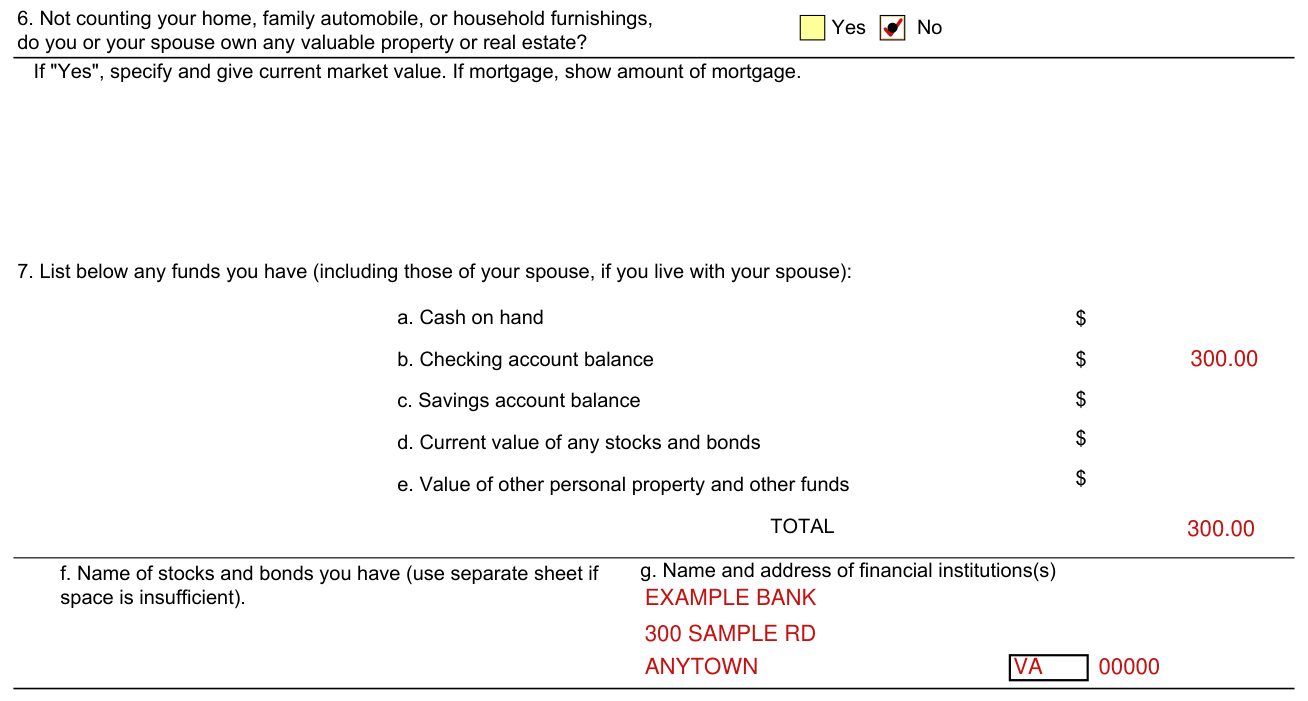
Not counting your home, family automobile, or household furnishings, do you or your spouse own any valuable property or real estate?
If "Yes", specify and give current market value. If mortgage, show amount of mortgage.
List any funds you have, including those of your spouse, if you live with your spouse: Cash on hand, Checking account balance, Savings account balance, Current value of any stocks and bonds, and Value of other personal property and other funds.
Enter the TOTAL.
Name of stocks and bonds you have (use separate sheet if space is insufficient). Name and address of financial institutions(s).
Part III - Without Fault Statement
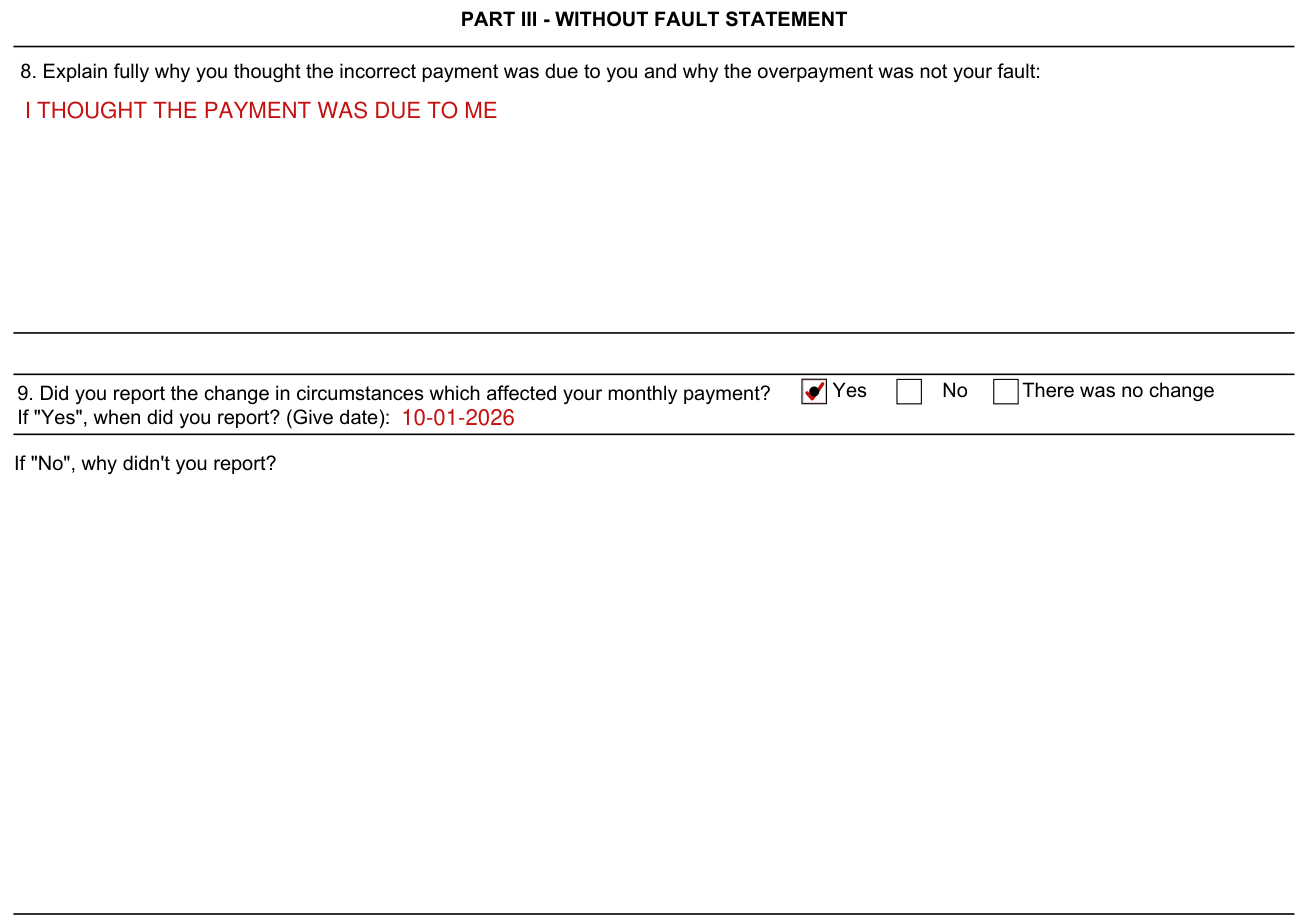
Part III, the Without Fault Statement, is completed only if marked. Explain fully why you thought the incorrect payment was due to you and why the overpayment was not your fault.
Did you report the change in circumstances which affected your monthly payment? Yes, No, or There was no change. If "Yes", when did you report? (Give date). If "No", why didn't you report?
Reporting responsibilities

In Part III, which is completed only if marked: when were the conditions under which you could receive payments first explained to you?
Do you NOW fully understand reporting responsibilities? If "No", explain.
Part IV - Representative Payment Made
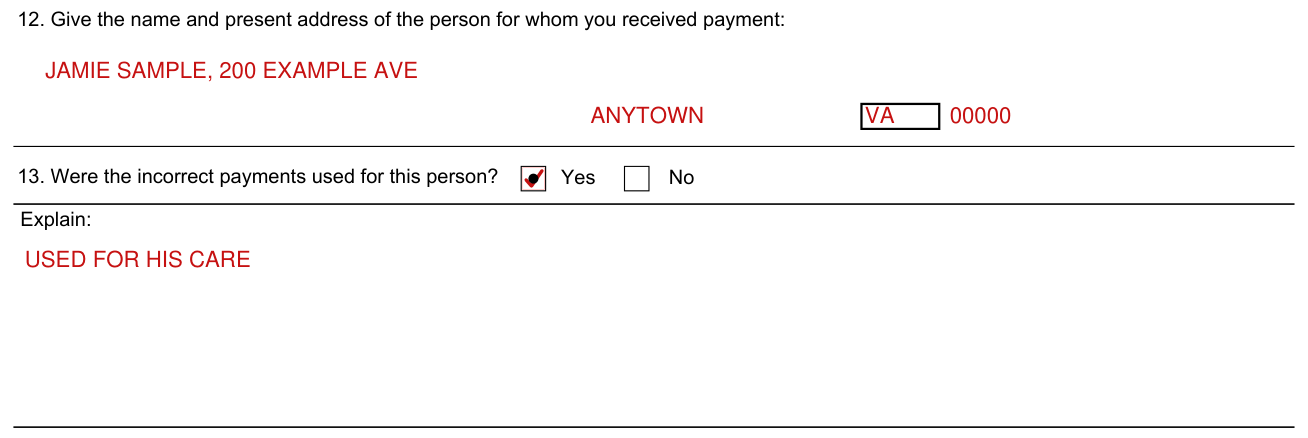
Part IV, Representative Payment Made, is to be completed ONLY by a representative payee. Give the name and present address of the person for whom you received payment.
Were the incorrect payments used for this person? Yes No. Explain.
Part V - Signature, date and address
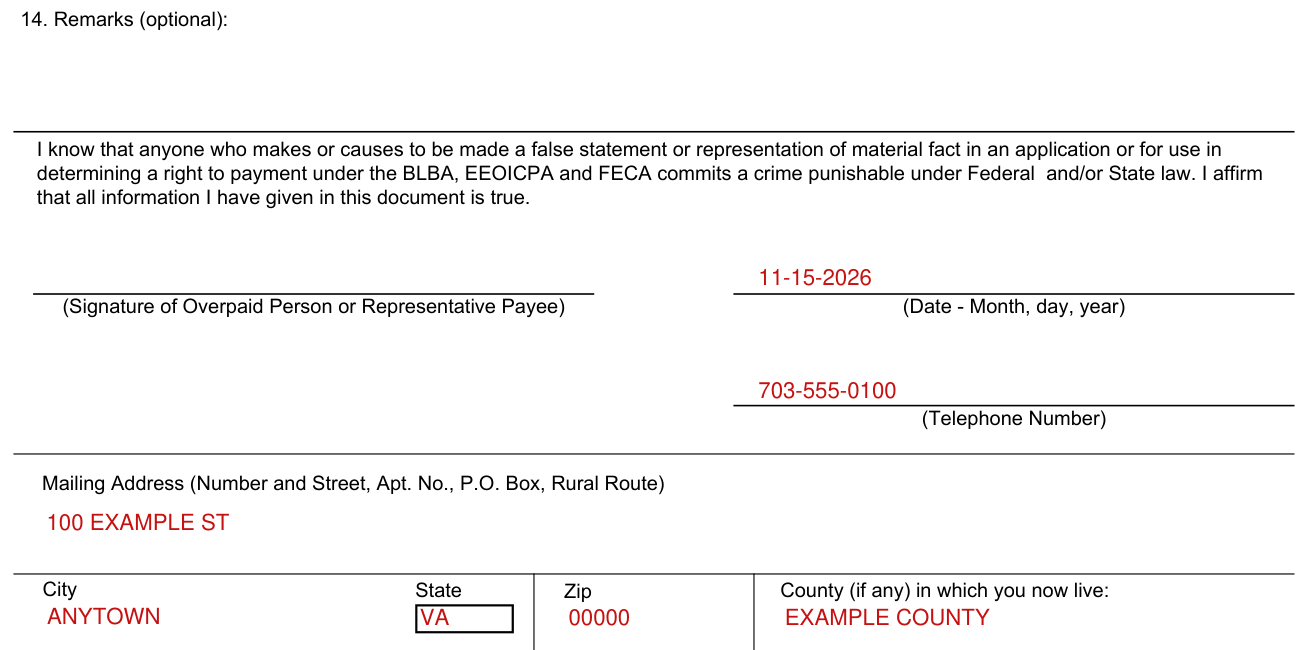
Remarks are optional.
The signature line is for the Signature of Overpaid Person or Representative Payee, with the Date - Month, day, year.
Telephone Number. Mailing Address (Number and Street, Apt. No., P.O. Box, Rural Route). State, City, Zip. County (if any) in which you now live.
More rules for Form OWCP-20
Completion and submission of this form is voluntary; however, failure to provide the information may result in the denial of a request to waive recovery of the overpayment.
Common questions about Form OWCP-20
Is there a penalty?
Anyone who makes or causes to be made a false statement or representation of material fact in an application or for use in determining a right to payment under the BLBA, EEOICPA and FECA commits a crime punishable under Federal and/or State law.
What am I certifying when I sign?
Affirm that all information you have given in this document is true.
Sources
[1] Form OWCP-20 (Rev. 07-22), Overpayment Recovery Questionnaire, U.S. Department of Labor Office of Workers' Compensation Programs (the Official source link on this page).