Invisalign Patient Transfer Form PDF Details

The journey of orthodontic treatment often involves multiple professionals and, at times, necessitates the transfer of a patient from one caregiver to another for continued care. This process is articulated through the completion of the Invisalign Patient Transfer Authorization Form, a critical document designed to facilitate the smooth transition of a patient's treatment from one doctor to another within the network of Invisalign® Trained Doctors. This document outlines essential information including the patient's personal data, the release of the patient by the current treating doctor, and the acceptance of the patient by the new doctor. The form serves multiple purposes, including the transfer of ClinCheck® files and the acknowledgment by both parties of their respective responsibilities concerning treatment costs and obligations. Moreover, it contains a section authorizing the release of medical records, ensuring the new treating doctor has access to necessary treatment records for continuing care. The form also highlights conditions related to the transfer’s legal and financial implications for both the releasing and receiving doctors, alongside the necessary contact details for Align Technology, Inc., the company behind Invisalign, thereby ensuring a comprehensive framework for the transfer process. Such detailed attention to the transition process underscores the importance of maintaining the integrity and continuity of patient care, while also protecting the legal and financial interests of all parties involved.

QuestionAnswer
Form NameInvisalign Patient Transfer Form
Form Length2 pages
Fillable?No
Fillable fields0
Avg. time to fill out30 sec
Other namesinvisalign doctor site patient transfer, release invisalign, patient transfer authorization form, invisalign transfer form 2020

How to Fill Out Invisalign Patient Transfer Authorization Form

Invisalign Patient Transfer Authorization Form at a glance

What it is: Invisalign Patient Transfer, Authorization Form 1 of 2: read the form and sign in corresponding area to authorize Align Technology, Inc. to transfer patient.

Where and when to file: This form must be faxed to 408-790-0670.

A filled-in Invisalign Patient Transfer Authorization Form example: a doctor transfers a patient

Invisalign Patient Transfer Authorization Form example filled out, example: a doctor transfers a patient
Dr. Ana Sample fills out the Invisalign transfer form for a patient. Jamie Example, born 04/17/1991, moves away, so Dr. Ben Test accepts. The picture shows page 1 only; all its values are invented.

How to fill out Invisalign Patient Transfer Authorization Form, box by box

Patient information

Invisalign Patient Transfer Authorization Form example filled out, patient information

Under PATIENT INFORMATION, enter the Name (Last, First, Middle).

Enter the Patient Number under PATIENT #.

Enter the Date of Birth as mm/dd/yyyy and mark Female or Male under Gender.

Release of patient (current doctor)

Invisalign Patient Transfer Authorization Form example filled out, release of patient (current doctor)

Under RELEASE OF PATIENT (CURRENT DOCTOR): Transfer this patient out of my Invisalign® Doctor Site including the patient's ClinCheck® files. I understand that by doing so, I relinquish all control of this patient to the new treating doctor. Align Technology, Inc. shall not be responsible for any cost, liability or obligation resulting from my decision to transfer the patient to another doctor for treatment. I acknowledge that I am still responsible for any open balance incurred in this patient's treatment prior to the transfer.

Enter the Reason for Transfer.

Enter the Doctor's Name (Please print), sign as Current Treating Doctor, and enter the Practice Name and Practice Address.

Acceptance of patient (new doctor)
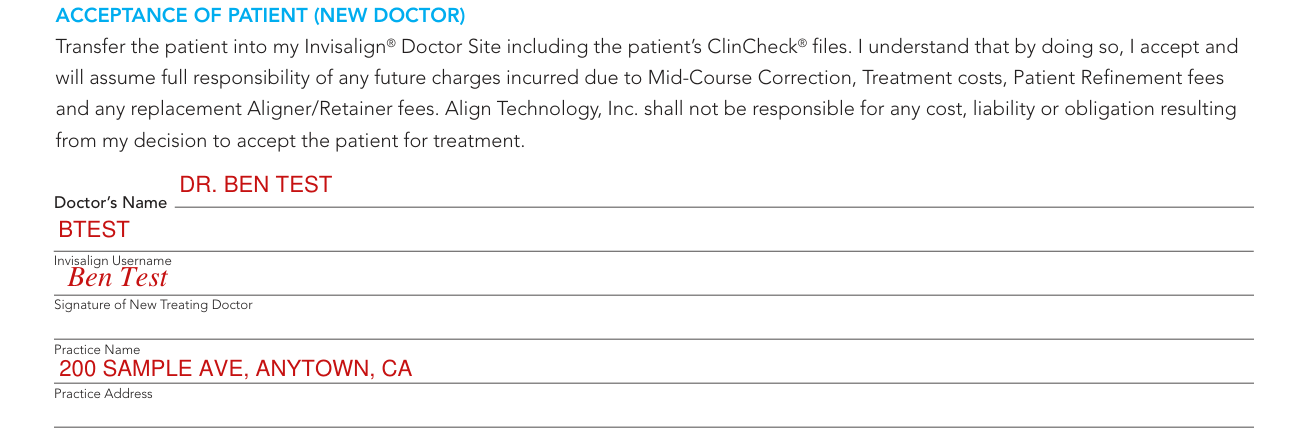
Invisalign Patient Transfer Authorization Form example filled out, acceptance of patient (new doctor)

Under ACCEPTANCE OF PATIENT (NEW DOCTOR): Transfer the patient into my Invisalign® Doctor Site including the patient's ClinCheck® files.

I understand that by doing so, I accept and will assume full responsibility of any future charges incurred due to Mid-Course Correction, Treatment costs, Patient Refinement fees and any replacement Aligner/Retainer fees. Align Technology, Inc. shall not be responsible for any cost, liability or obligation resulting from my decision to accept the patient for treatment.

Enter the Doctor's Name and the Invisalign Username, and sign as New Treating Doctor.

Enter the Practice Name and Practice Address.

If your situation is different

Authorization to release medical records

Under AUTHORIZATION TO RELEASE MEDICAL RECORDS, enter the Name (Last, First, Middle), PATIENT # and Date of Birth under PATIENT INFORMATION, then enter the from doctor and the to doctor, an Invisalign® Trained doctor (hereinafter “New Doctor”), for the release of the individual's personal medical records for use by New Doctor in treatment with products from Align Technology, Inc.

This Release also notifies and authorizes Align Technology, Inc., its representatives, successors, assigns and agents (collectively “Align”) to transfer all Medical Records for the individual in its possession to New Doctor, wherein New Doctor will have electronic access to such records.

This authorization shall be valid three years from its date.

A photocopy of this Release shall be considered as effective and valid as the original.

Sign on the Signature line and enter the Print Name, Address, City, State, Zip and Date; the Witness signs on the Witness line and enters the Print Name.

Signature of Parent/Guardian if signatory is under 21

If signatory is under 21, the parent or Legal Guardian must also sign to signify agreement, on the Signature of Parent/Guardian line.

Common questions about Invisalign Patient Transfer Authorization Form

Who signs it?

In order to complete a Patient Transfer, it is desired that both the Invisalign® Trained Doctor that is transferring the patient, and the Invisalign® Trained Doctor that is accepting the patient, sign the transfer. However in some instances patients desire to transfer without authorization from their current doctor due to something that occurred during treatment, inability to locate the doctor or other similar reasons. As a result Align will accept a case transfer request if signed by patient and new doctor only. Each doctor agrees to indemnify, defend and hold harmless Align Technology, Inc. and its affiliates from and against any and all damages, losses, settlement payments, obligations, liabilities, penalties, claims, actions or causes of action, encumbrances and reasonable costs and expenses (including, without limitation, attorneys' fees and costs of investigation) suffered, sustained, incurred or paid by Align Technology, Inc. arising from this transfer.

Where do I file it?

Fax the completed form to 408-790-0670.

What am I certifying when I sign?

I have read and understand the contents of this Release.

Sources

[1] Invisalign Patient Transfer, Authorization Form 1 of 2 and 2 of 2 (the served file; no issuer file found) (the Official source link on this page).

Please rate Invisalign Patient Transfer Form

1 Votes
If you believe this page is infringing on your copyright, please familiarize yourself with and follow our DMCA notice and takedown process - click here to proceed .