
Form 470-4299 at a glance
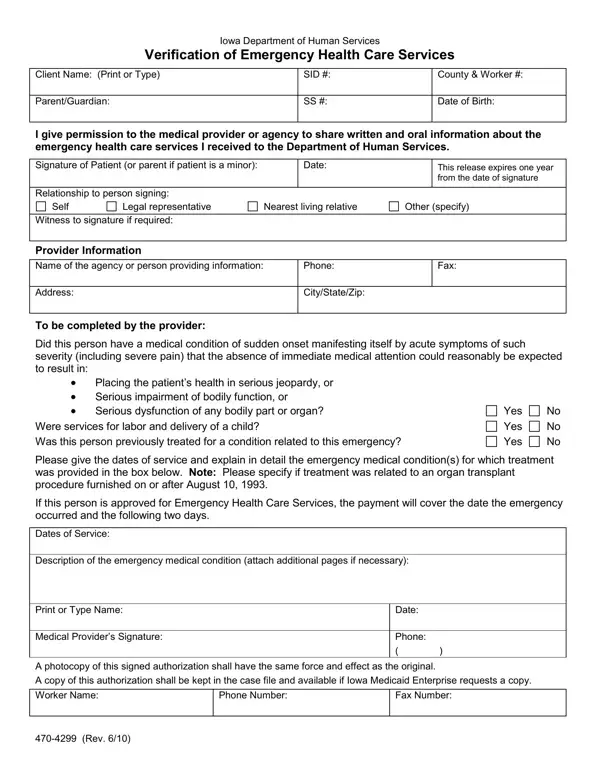
What it is: Form 470-4299 is the Iowa Department of Human Services Verification of Emergency Health Care Services, with a section to be completed by the provider.
Who signs: The Patient (or parent if patient is a minor) signs the release, and the medical provider signs on the Medical Provider's Signature line.
You give permission to the medical provider or agency to share written and oral information about the emergency health care services received to the Department of Human Services.
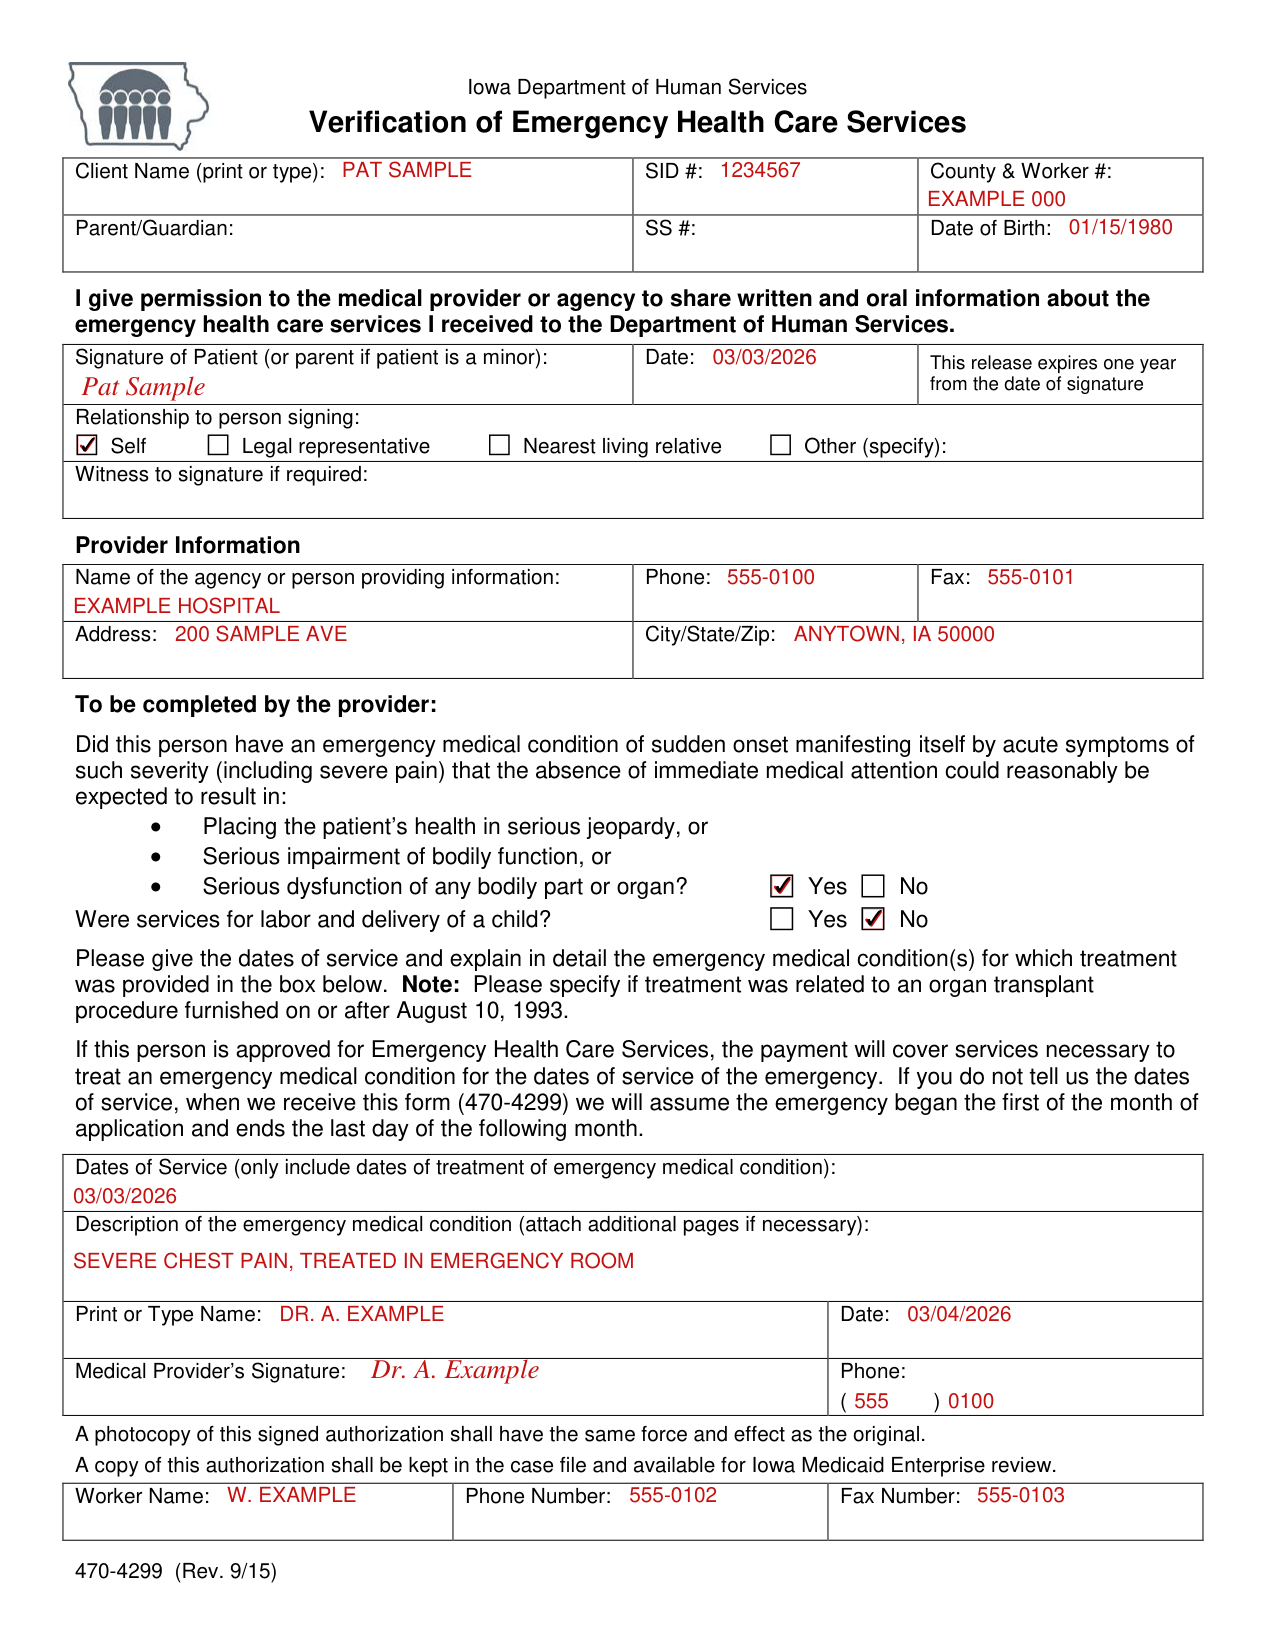
A filled-in Form 470-4299 example: a verification of emergency care
How to fill out Form 470-4299, box by box
Client Name, County & Worker #, Parent/Guardian, SID # and Date of Birth

Enter the Client Name (print or type), the County & Worker #, the Parent/Guardian, the SID # and the Date of Birth.
Signature of Patient and Date
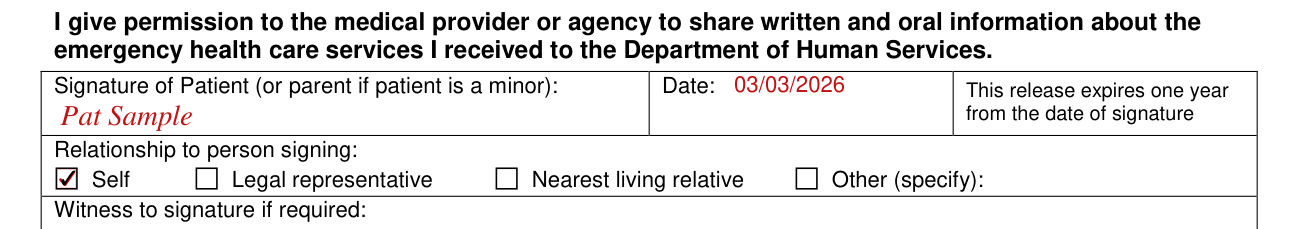
Sign on the Signature of Patient (or parent if patient is a minor) line and enter the Date; this release expires one year from the date of signature.
Relationship to person signing

Under Relationship to person signing, mark Self, Legal representative, Nearest living relative or Other (specify), and fill in Witness to signature if required.
Provider Information
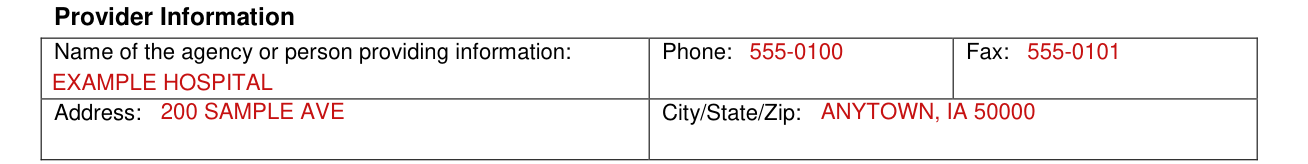
Under Provider Information, enter the Name of the agency or person providing information, the Address, the City/State/Zip, the Phone and the Fax.
Did this person have an emergency medical condition

To be completed by the provider: mark Yes or No: Did this person have an emergency medical condition of sudden onset manifesting itself by acute symptoms of such severity (including severe pain) that the absence of immediate medical attention could reasonably be expected to result in placing the patient's health in serious jeopardy, serious impairment of bodily function, or serious dysfunction of any bodily part or organ?
Were services for labor and delivery of a child

The provider marks Yes or No: Were services for labor and delivery of a child?
Dates of Service

The provider gives the dates of service and explains in detail the emergency medical condition(s) for which treatment was provided in the box; only include dates of treatment of emergency medical condition. If the provider does not tell the Iowa Department of Human Services the dates of service, when it receives this form (470-4299) it will assume the emergency began the first of the month of application and ends the last day of the following month.
The provider specifies if treatment was related to an organ transplant procedure furnished on or after August 10, 1993.
Description of the emergency medical condition

The provider describes the emergency medical condition in the Description of the emergency medical condition box; attach additional pages if necessary.
Medical Provider's Signature

The medical provider enters the Print or Type Name, the Date, the Medical Provider's Signature and the Phone.
Worker Name, Phone Number and Fax Number

Enter the Worker Name, the Phone Number and the Fax Number.
More rules for Form 470-4299
A photocopy of this signed authorization shall have the same force and effect as the original, and a copy shall be kept in the case file and available for Iowa Medicaid Enterprise review.
Sources
[1] Form 470-4299 (Rev. 9/15), Verification of Emergency Health Care Services, Iowa Department of Human Services (the Official source link on this page).