

Form MSA-115 at a glance
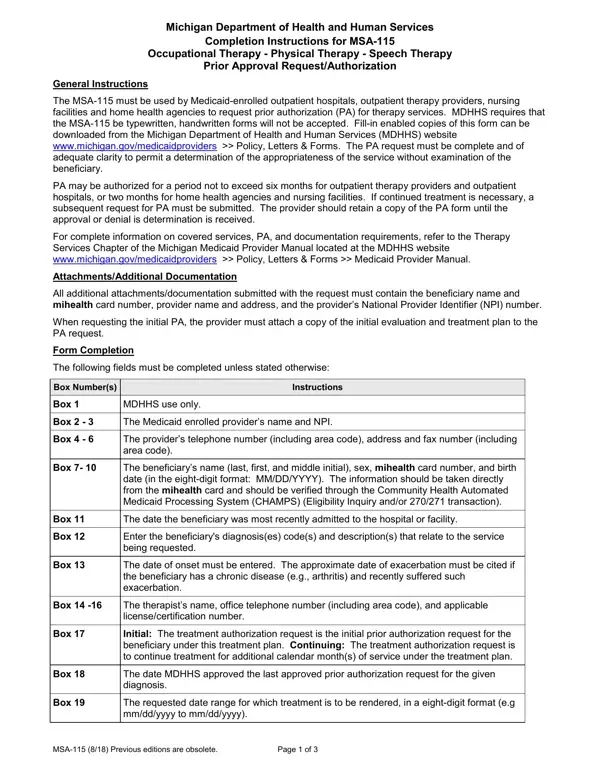
What it is: Michigan Department of Health and Human Services MSA-115 Occupational Therapy, Physical Therapy, Speech Therapy Prior Authorization Request.
Where and when to file: Alternatively, providers may submit PA requests via fax to FAX (517) 335-0075.
For therapy services requiring prior authorization (PA) for individuals enrolled in Fee-for-Service Medicaid and/or Children's Special Health Care Services (CSHCS), providers must request prior authorization (PA) through the Program Review Division.
A filled-in Form MSA-115 example: a first request for speech therapy
How to fill out Form MSA-115, box by box
Fax Submission Date, Requesting Provider and Provider's Address

Box 1: Enter the date the request is being faxed.
Boxes 2 to 3: Enter the Medicaid enrolled provider's organization name and NPI.
If not a facility/group practice, enter the Individual provider's name and NPI.
Requesting Provider (Organization/Group) Name: If not applicable, enter Individual.
Box 4: Enter the servicing location to which PA correspondence should be mailed, including determination letters and requests for additional clinical information.
Provider Office Contact Information

Box 5: Enter contact information for an individual in the provider's office that the Program Review Division can contact with questions regarding the PA request.
Beneficiary Name, mihealth Card Number, Date of Birth, Phone Number and Sex

Boxes 6 to 10: Enter the beneficiary's name, mihealth card number, phone number, date of birth, and sex.
The information should be taken directly from the mihealth card and verified in CHAMPS.
ICD Diagnosis Code and Description

Box 11: Enter the beneficiary's diagnosis code(s) and description(s) that relate to the service being requested.
For CSHCS covered services, providers are required to submit the beneficiary's CSHCS qualifying diagnosis related to the services being requested.
Expedited Review and Determination

Boxes 12 to 17: Indicate if an Expedited Review is being requested (due to medical necessity for provision of services within 10 calendar days).
If YES, questions 13-17 must be answered. If NO, skip to box #18.
Standard reviews will be determined within 7 calendar days.
If the request does not meet expedited criteria, it will be processed as a standard review and the requesting provider will be notified via the Provider Communication section for this request in CHAMPS.
If approved, will the service requested be rendered within ≤ 10 calendar days of the request submission date? YES NO
If the service requested is not rendered within ≤ 10 calendar days will the patient's life, health, or ability to regain maximum function be seriously jeopardized? YES NO
Is intervention within ≤ 10 calendar days necessary to correct a medical condition or avoid further damage/loss of function? YES NO
Will the patient be discharged from the hospital/nursing facility as of today's date (date this form is being completed)? YES NO
Explain need for Expedited Review and Determination. Supporting documentation submitted with this request must concur with this explanation for an expedited review to be granted.
Therapist Name, License Number, Office Phone Number and Email

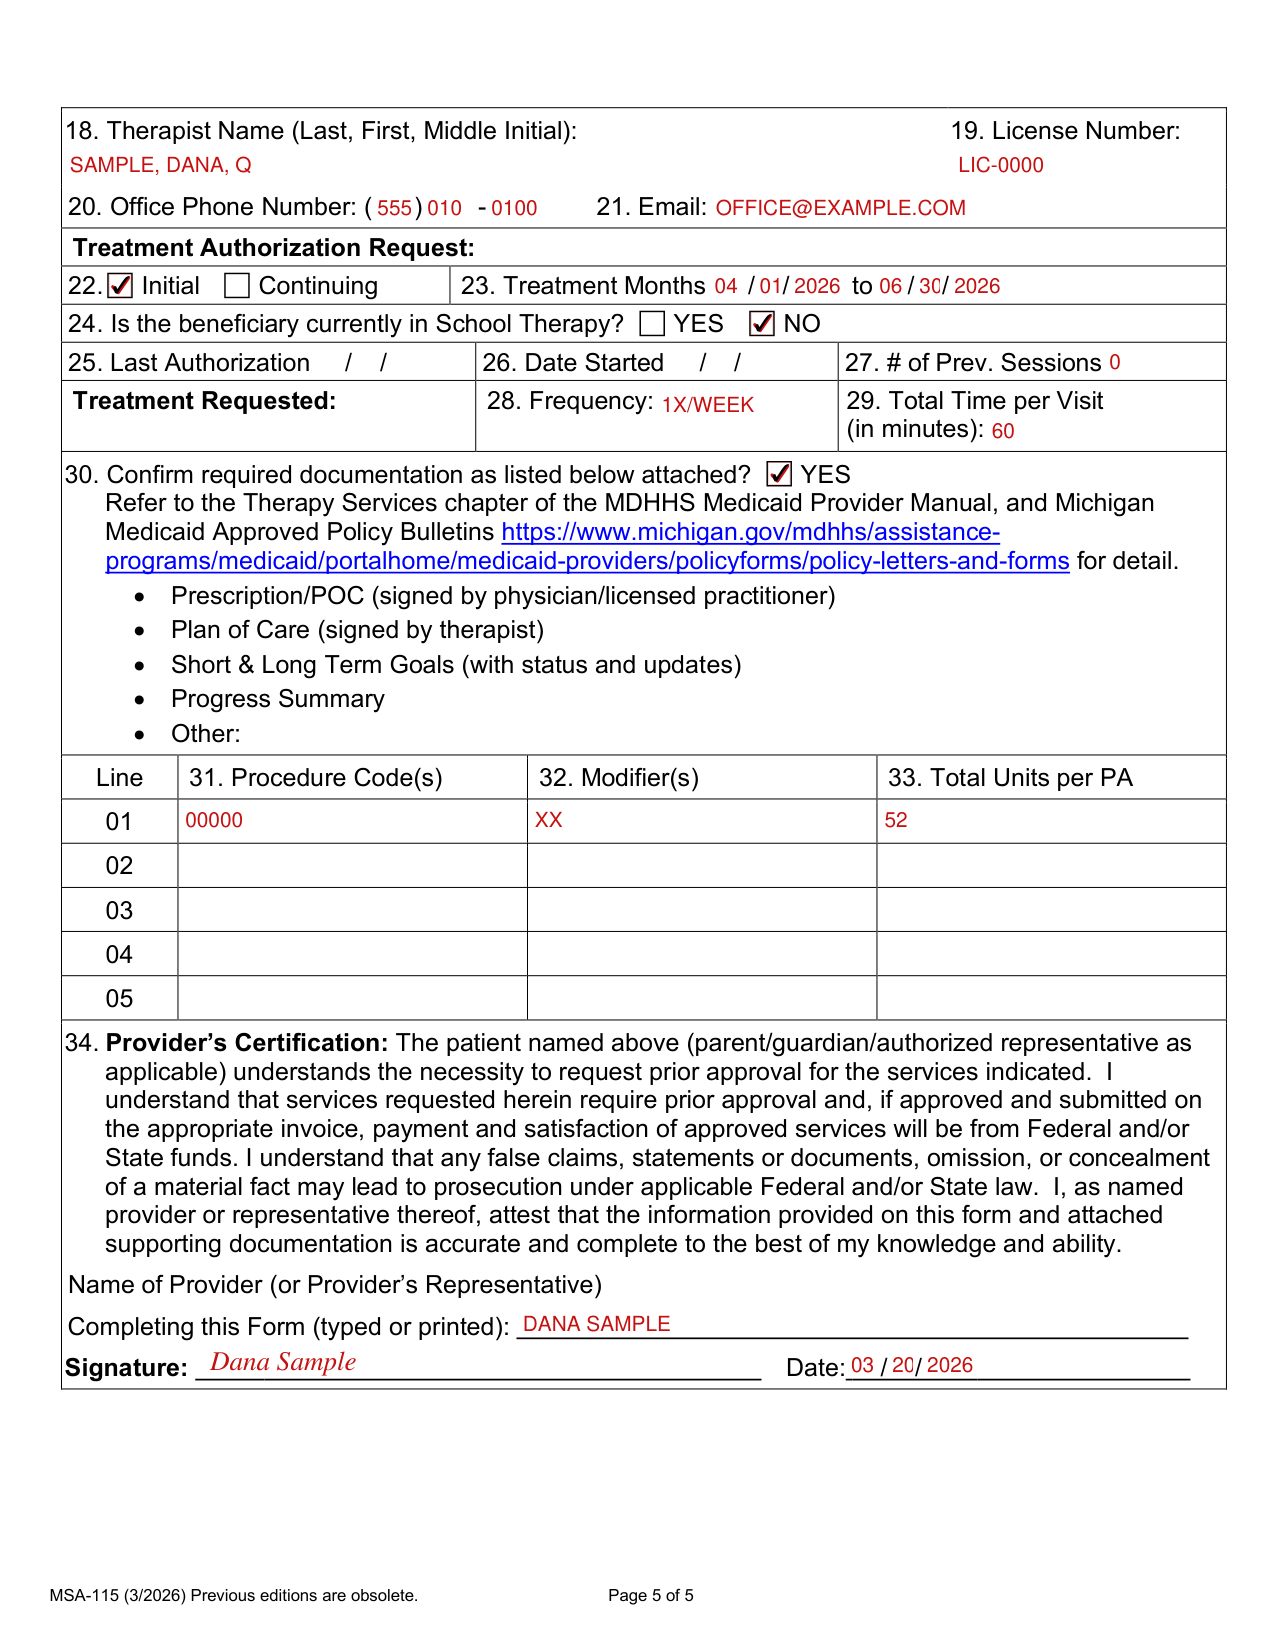
Boxes 18 to 21: The therapist's name, office telephone number (including area code), email address, and professional license number.
Treatment Authorization Request
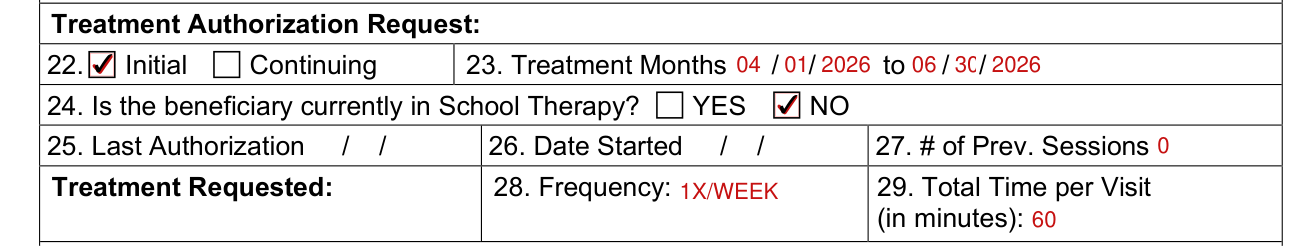
Box 22 Initial: The treatment authorization request is the initial prior authorization request for the beneficiary under this treatment plan.
Continuing: The treatment authorization request is to continue treatment for additional calendar month(s) of service under the treatment plan.
Box 23 Treatment Months: The requested date range for which treatment is to be rendered, in a eight-digit format (e.g mm/dd/yyyy to mm/dd/yyyy).
Box 24: Indicate if the beneficiary is receiving therapy services through the School Services Program.
Box 25 Last Authorization: The date MDHHS approved the last approved prior authorization request for the given diagnosis.
Box 26 Date Started: The date treatment was started for the given diagnosis (if treatment was initiated previously).
Box 27 Total # of Previous Sessions: The total number of sessions rendered since the development of the treatment plan.
Box 28 Frequency: Indicate the treatment plan frequency (e.g., 1x/week, 3x/week, 1x/month, etc.).
Box 29 Total Time per Visit (minutes): indicate the duration per visit in 15-minute increments, i.e., units (e.g. 2 units/visit, 4 units/visit, etc.).
Required documentation attached
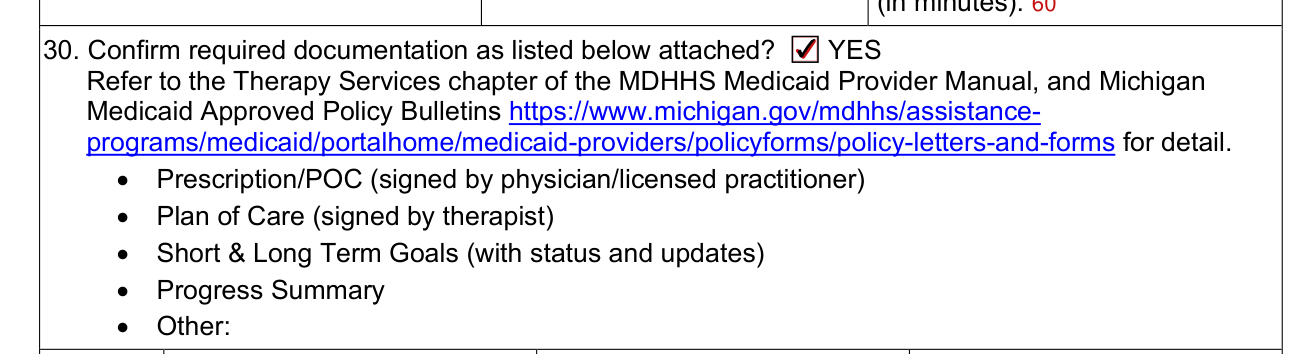
Box 30: Confirm required documentation has been attached to the PA request.
Prescription/POC (signed by physician/licensed practitioner), Plan of Care (signed by therapist), Short & Long Term Goals (with status and updates), Progress Summary, Other:
For detail, refer to the Therapy Services chapter of the MDHHS Medicaid Provider Manual, and Michigan Medicaid Approved Policy Bulletins.
Procedure Code(s), Modifier(s) and Total Units per PA
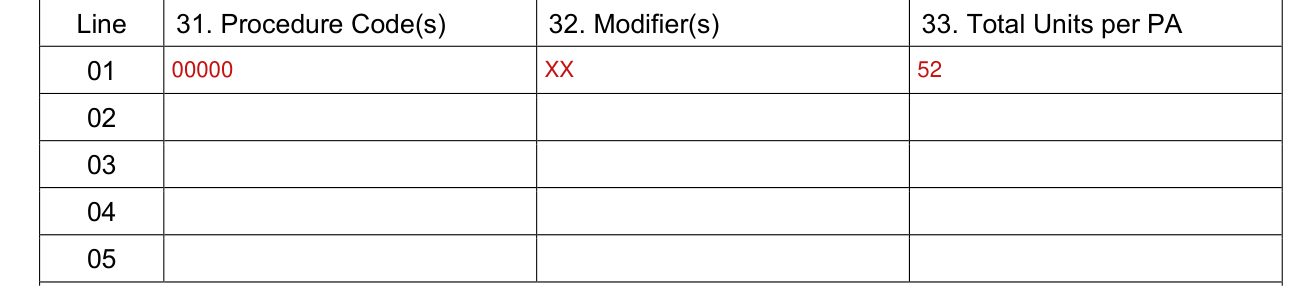
Box 31 Procedure Code(s): The Therapies Databases on the MDHHS website lists the HCPCS codes for covered services.
The database is located at the MDHHS website www.michigan.gov/medicaidproviders, Billing and Reimbursement, Provider Specific Information, Therapies, Choose applicable database.
Box 32 Modifier(s): For a list the required modifiers used to describe covered services for therapy providers, refer to the Billing & Reimbursement for Professionals chapter of the Medicaid Provider Manual, and Michigan Medicaid Approved Policy Bulletins.
Box 33 Total Units per PA: Total number of units (for each code) to be provided during the requested treatment period.
Provider's Certification and signature

Box 34 Provider (or Provider's Representative): Printed/typed name, along with signature and date are required, attesting to the Provider Certification.
Provider's Certification: The patient named (parent/guardian/authorized representative as applicable) understands the necessity to request prior approval for the services indicated.
I understand that services requested herein require prior approval and, if approved and submitted on the appropriate invoice, payment and satisfaction of approved services will be from Federal and/or State funds.
I, as named provider or representative thereof, attest that the information provided on this form and attached supporting documentation is accurate and complete to the best of my knowledge and ability.
More rules for Form MSA-115
The provider is responsible for eligibility verification.
Authorization does not guarantee beneficiary eligibility or payment.
Forms that are not legible will be returned for resubmission.
Questions regarding PA should be directed to the Program Review Division at (800) 622-0276.
Questions regarding navigating CHAMPS should be directed to the Provider Support Helpline at (800) 292-2550 or providersupport@michigan.gov.
Managed care plans, electronic requests, mail and extensions
The beneficiary is enrolled in a Medicaid Health Plan, other managed care plan or Healthy Kids Dental
For beneficiaries enrolled in Medicaid Health Plans, other managed care plans, or Healthy Kids Dental, providers must contact the assigned plan for authorization requirements.
You submit the PA request electronically
Providers are strongly encouraged to submit PA requests electronically through direct data entry into CHAMPS through the CHAMPS Provider Portal at https://milogintp.michigan.gov.
This form is not required if the PA Request is submitted electronically in CHAMPS via Direct Data Entry at https://milogintp.michigan.gov AND the Supplemental Information section is fully completed.
All other supporting clinical documentation required by policy must be uploaded to the request in CHAMPS, including a copy of the initial evaluation and treatment plan for the initial PA request. All documents must contain the beneficiary name and mihealth card number.
You mail the PA request
Providers are discouraged from mailing PA requests, but if necessary, requests may be mailed to MDHHS Prior Authorization P.O. Box 30170 Lansing, MI 48909.
Common questions about Form MSA-115
Is there a penalty?
I understand that any false claims, statements or documents, omission, or concealment of a material fact may lead to prosecution under applicable Federal and/or State law.
Sources
[1] Form MSA-115 (3/2026), Occupational Therapy - Physical Therapy - Speech Therapy Prior Authorization Request, Michigan Department of Health and Human Services (the Official source link on this page).