


Form OWCP-5a at a glance
What it is: Form OWCP-5a, Work Capacity Evaluation Psychiatric/Psychological Conditions, obtains the claimant's specific work tolerance limitation where the accepted condition is psychiatric or psychological in nature.
Who signs: Add the Physician's Signature for 8 and the Date for 9.
A filled-in Form OWCP-5a example: a physician evaluates a patient's work capacity

How to fill out Form OWCP-5a, box by box
Injured worker's name and OWCP No.
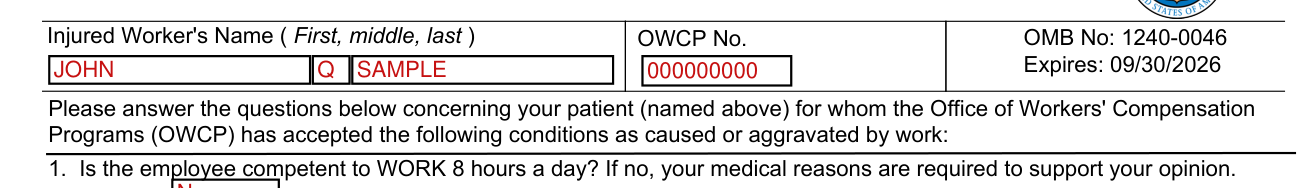
Enter the Injured Worker's Name (First, middle, last) and the OWCP No.
1. Competent to work 8 hours a day
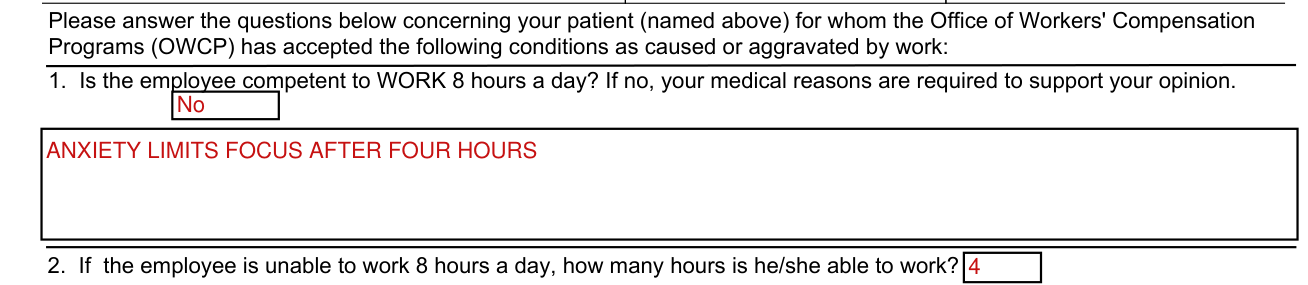
For 1, enter Yes or No: is the employee competent to WORK 8 hours a day? If no, your medical reasons are required to support your opinion.
2. Hours the employee is able to work
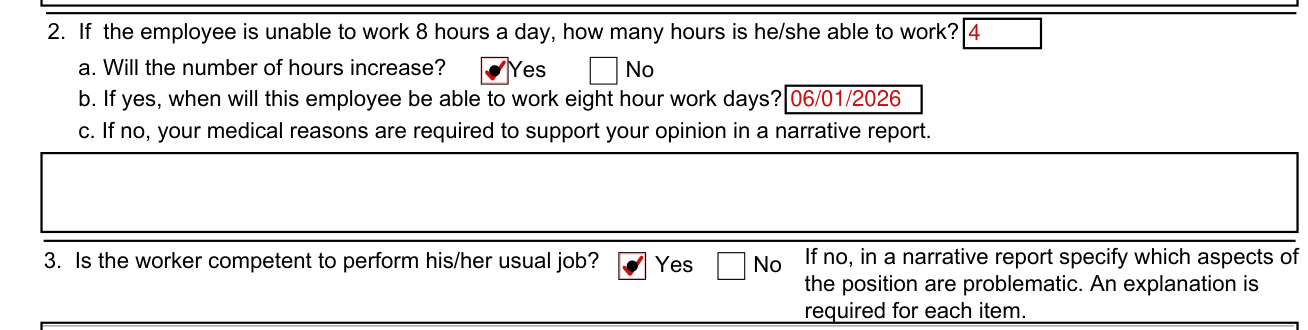
For 2, if the employee is unable to work 8 hours a day, enter how many hours he/she is able to work.
Enter Yes or No: a. will the number of hours increase? b. If yes, enter when this employee will be able to work eight hour work days. c. If no, your medical reasons are required to support your opinion in a narrative report.
3. Usual job
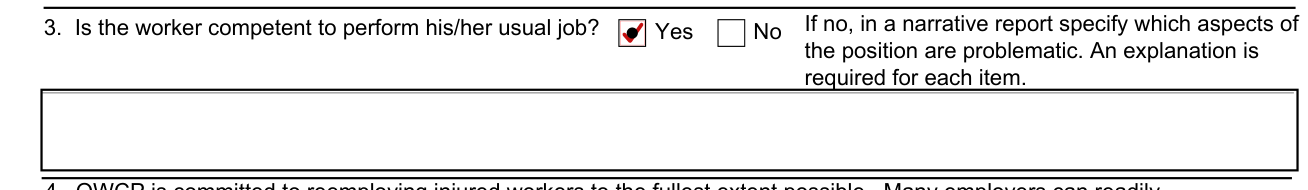
For 3, enter Yes or No: is the worker competent to perform his/her usual job? If no, in a narrative report specify which aspects of the position are problematic. An explanation is required for each item.
4. Suitable duties or work environments

For 4, describe the duties or work environment(s) which are suitable for your patient. Please be as detailed as possible. Please note that if reemployment at the employing agency is not possible, the Office may pursue vocational rehabilitation for the injured worker.
5. Other medical factors

For 5, list, if any, other medical factors which need to be considered in the identification of a position for this person. Please explain each item.
6 to 9. Physician's name, telephone, signature and date
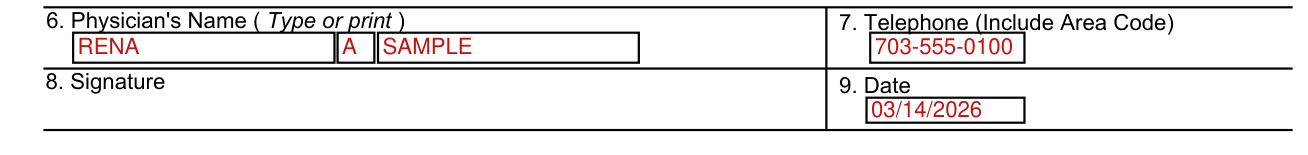
For 6, type or print the Physician's Name. For 7, enter the Telephone (Include Area Code).
Add the Physician's Signature for 8 and the Date for 9.
More rules for Form OWCP-5a
Completion of this form is voluntary (5 U.S.C. 8101, et seq), however, failure to provide the information may result in the delay of processing of the claim or payment or benefits, or may result in an unfavorable decision or reduced levels of benefits.
Public reporting burden for this collection of information is estimated to average 15 minutes per response, including time for reviewing instructions, searching existing data sources, gathering and maintaining the data needed, and completing and reviewing the collection of information.
Common questions about Form OWCP-5a
Where do I file it?
Send the form to the address shown on the letterhead.
Sources
[1] Form OWCP-5a (Rev. 08-14), Work Capacity Evaluation Psychiatric/Psychological Conditions, U.S. Department of Labor (the Official source link on this page).