


Patient Information Form at a glance
What it is: Clay-Platte Family Medicine Clinic, PC Patient Information Form, Partnering for Excellence in Health Care.
Who signs: Signed, Parent/Guardian and Date are the last lines of the form.
A filled-in Patient Information Form example: a patient fills out the form

How to fill out Patient Information Form, box by box
Date, Name, Address and Phone
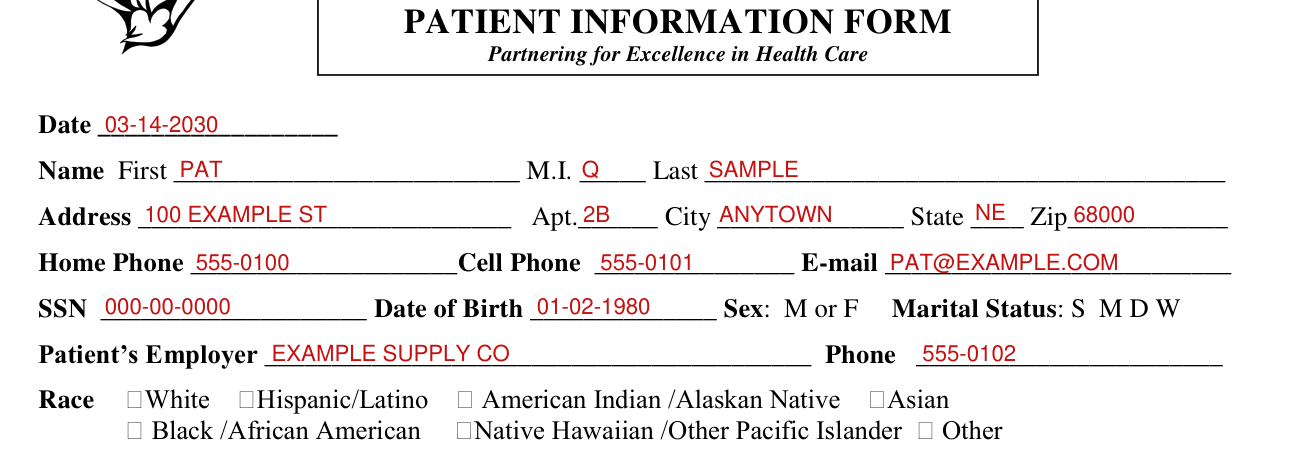
Enter the Date, then the Name: First, M.I. and Last.
Enter the Address, Apt., City, State and Zip.
Enter the Home Phone, Cell Phone and E-mail.
Enter the SSN and Date of Birth, then mark Sex: M or F and Marital Status: S, M, D or W.
Employer, Language and Preferred Contact Method

Enter the Patient's Employer and Phone.
Mark the Race that applies: White, Hispanic/Latino, American Indian /Alaskan Native, Asian, Black /African American, Native Hawaiian /Other Pacific Islander or Other.
Enter the Language Preference, then mark Hearing Impaired Yes or No and Vision Impaired Yes or No.
Mark the Preferred Contact Method: Phone, Email or Mail; mark Need Interpreter? Yes or No and enter the Type.
How did you hear about Clay Platte Family Medicine

Mark How did you hear about Clay Platte Family Medicine: Insurance, Family Member, Friend, Print Ad, Billboard, Website, Phonebook or Other, and enter the Other Specify line.
Person Responsible for Account
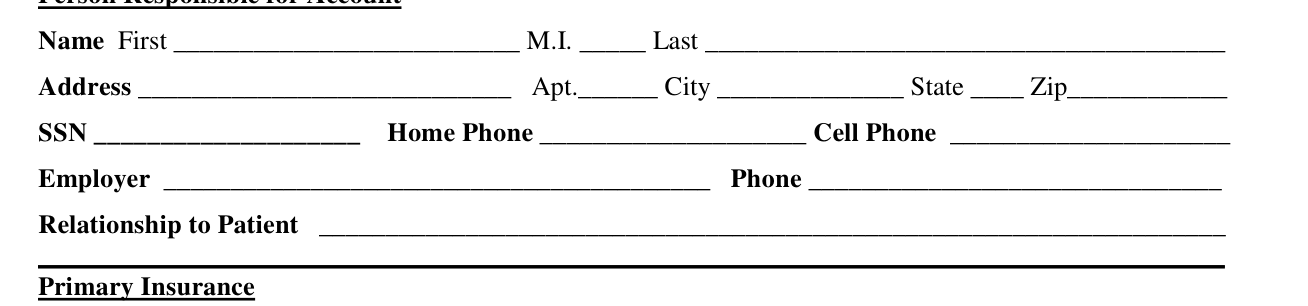
Under Person Responsible for Account, enter the Name, Address, SSN, Home Phone, Cell Phone, Employer, Phone and Relationship to Patient.
Primary Insurance
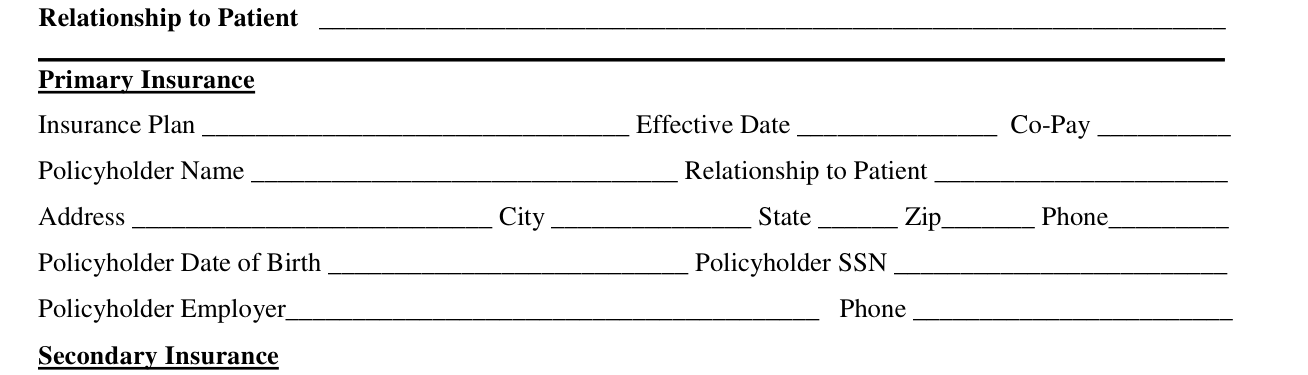
Under Primary Insurance, enter the Insurance Plan, Effective Date, Co-Pay, Policyholder Name, Relationship to Patient, Address, City, State, Zip, Phone, Policyholder Date of Birth, Policyholder SSN, Policyholder Employer and Phone.
Secondary Insurance
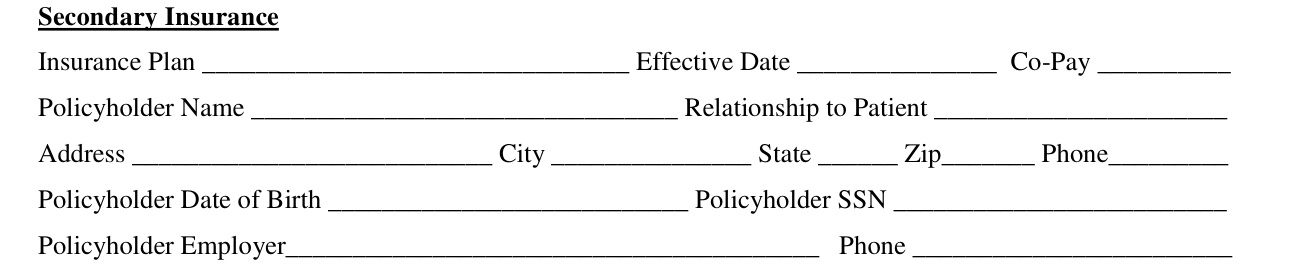
Under Secondary Insurance, enter the Insurance Plan, Effective Date, Co-Pay, Policyholder Name, Relationship to Patient, Address, City, State, Zip, Phone, Policyholder Date of Birth, Policyholder SSN, Policyholder Employer and Phone.
Spouse/Parent/Guardian Information
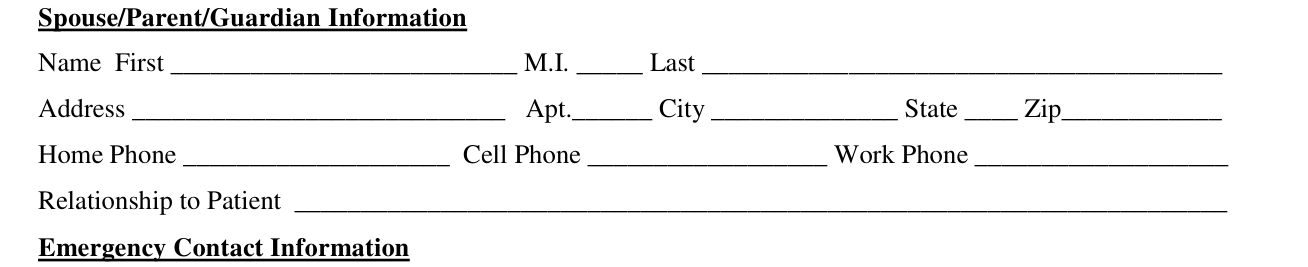
Under Spouse/Parent/Guardian Information, enter the Name, Address, Home Phone, Cell Phone, Work Phone and Relationship to Patient.
Emergency Contact Information
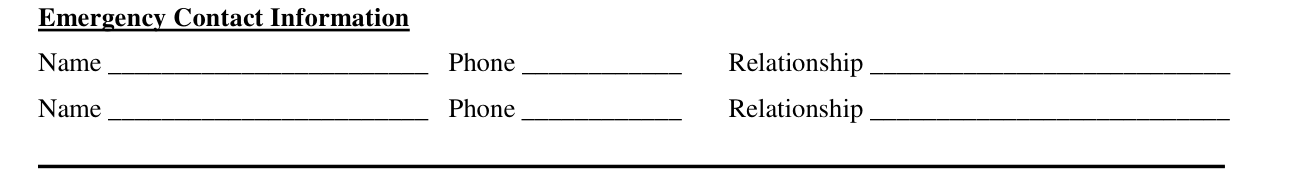
Under Emergency Contact Information, enter the Name, Phone and Relationship.
Privacy Information

Privacy Information: mark Yes or No for permission to leave messages regarding appointments or requests for your call back on an answering machine, and Yes or No for Cell phone.
To whom may protected health information be released? Choose One: To myself only; To myself and anyone else involved in my healthcare or payment for my healthcare; or To myself and Only to the designated persons.
Enter the Name and Relationship on each line.
Assignment of Insurance Benefits/Release of Medical Information, Signed, Parent/Guardian and Date

Assignment of Insurance Benefits/Release of Medical Information: I understand pre-certifications/authorizations/referrals are my responsibility. I hereby authorize treatment deemed necessary by the named physicians. I understand that I am responsible for any amount not covered by insurance. I also authorize the release of my medical records to any insurance company with whom I have health insurance coverage or to any company to which I have applied for coverage. I request payment of medical insurance benefits to include major medical to be made directly to CLAY PLATTE FAMILY MEDICINE on any unpaid bills for services rendered to myself or my dependents.
Sign on the Signed line and enter the Date; the Parent/Guardian line is for a parent or guardian.
Sources
[1] Patient Information Form, Clay-Platte Family Medicine Clinic, PC (Rev 8/27; the served file; no issuer file found) (the Official source link on this page).