

Lifeline Care Plan Agreement at a glance
What it is: Lifeline Care Plan Agreement: information for Lifeline Trained Care Specialists to have ready in case of an emergency.
Who signs: Sign on the Signature of Subscriber/Care Recipient line and enter the Date.
Complete this Care Plan Agreement with information that you would like Lifeline Trained Care Specialists to have ready in case of an emergency.
A filled-in Lifeline Care Plan Agreement example: a subscriber lists one caregiver
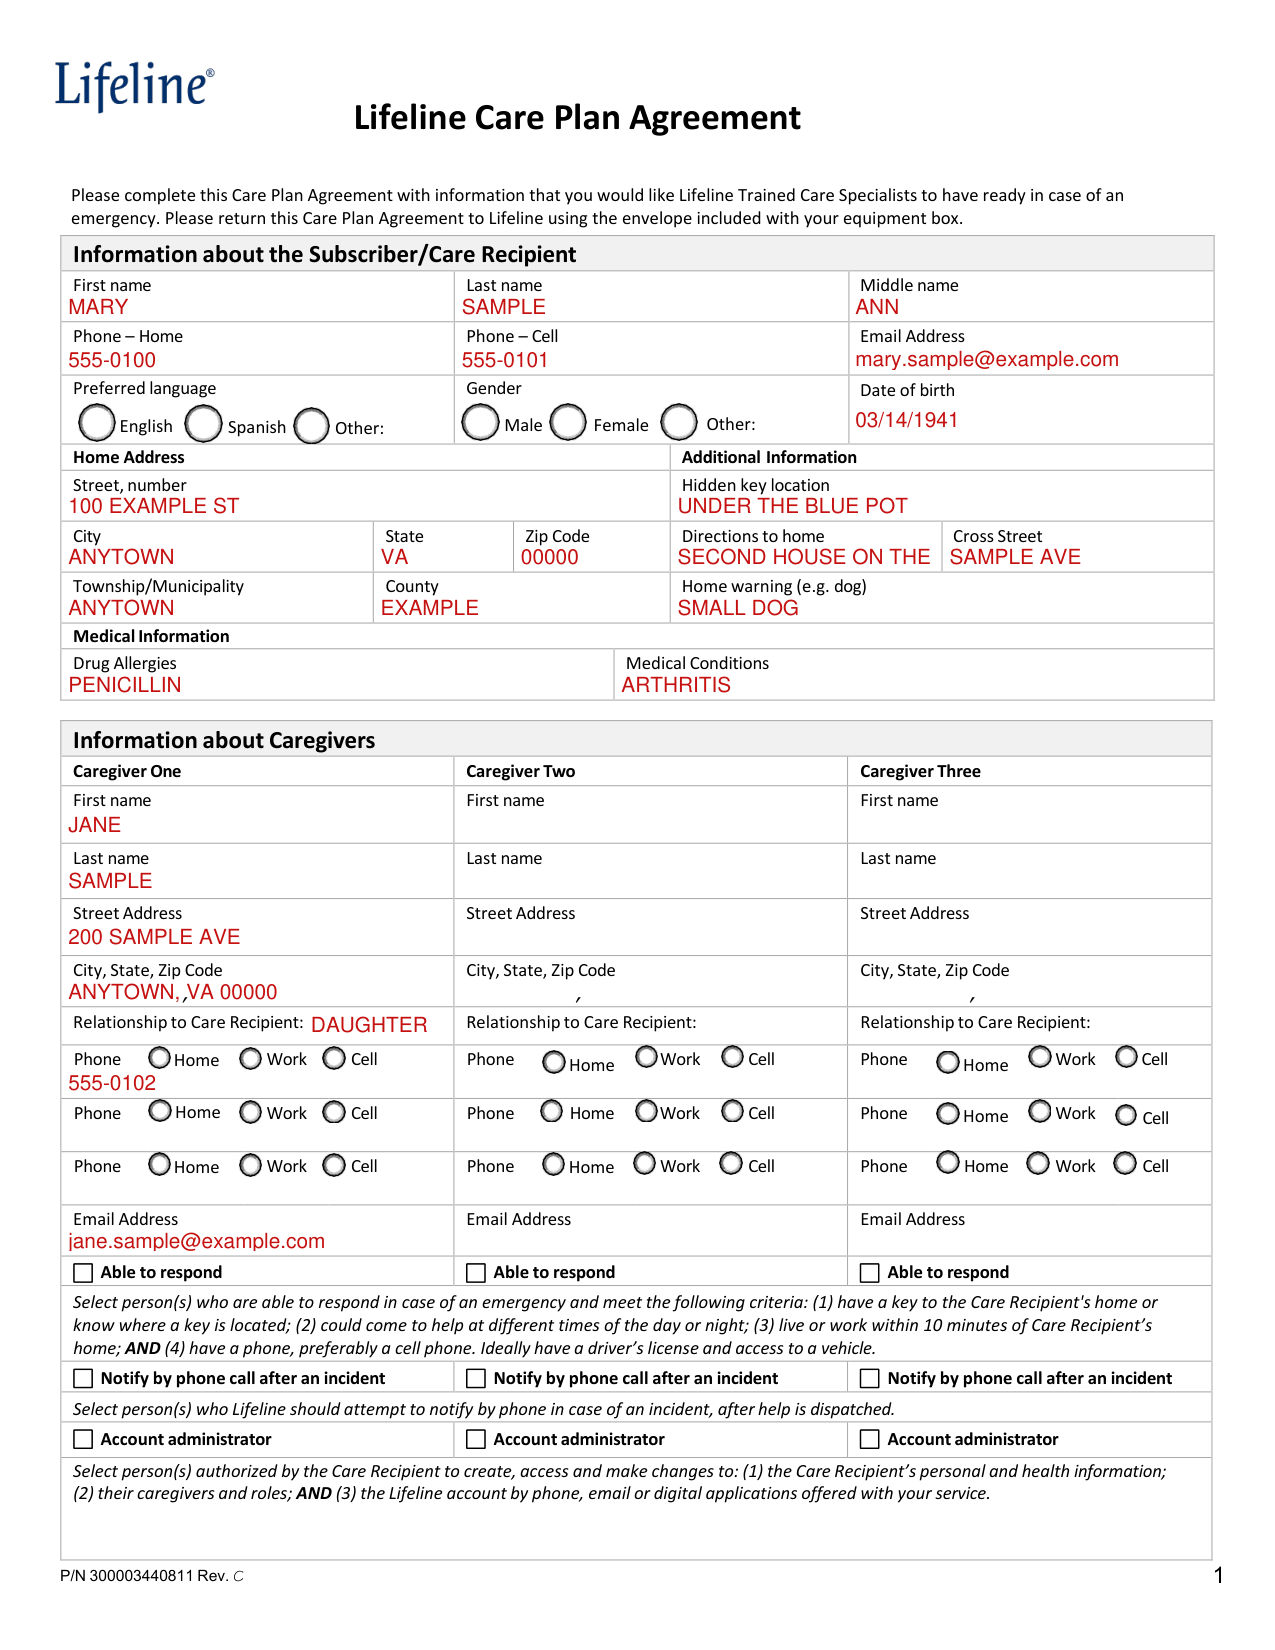
How to fill out Lifeline Care Plan Agreement, box by box
Information about the Subscriber/Care Recipient
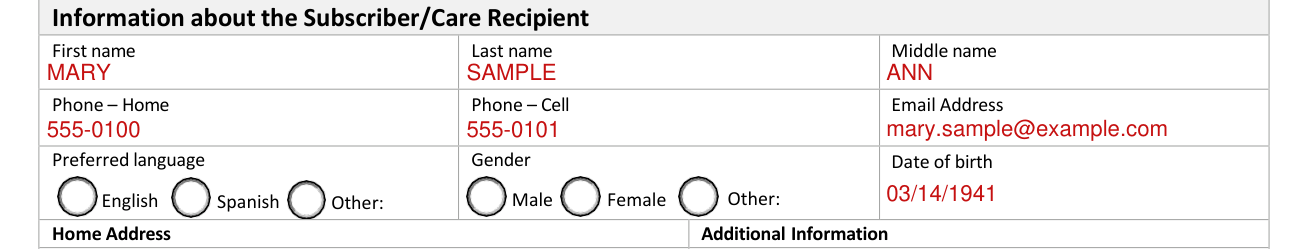
Under Information about the Subscriber/Care Recipient, enter First name, Last name, Middle name, Phone - Home, Phone - Cell and Email Address.
Preferred language: English, Spanish or Other; if you mark Other, write the language after Other. Gender: Male, Female or Other; if you mark Other, write it after Other.
Enter the Date of birth.
Home Address and Medical Information
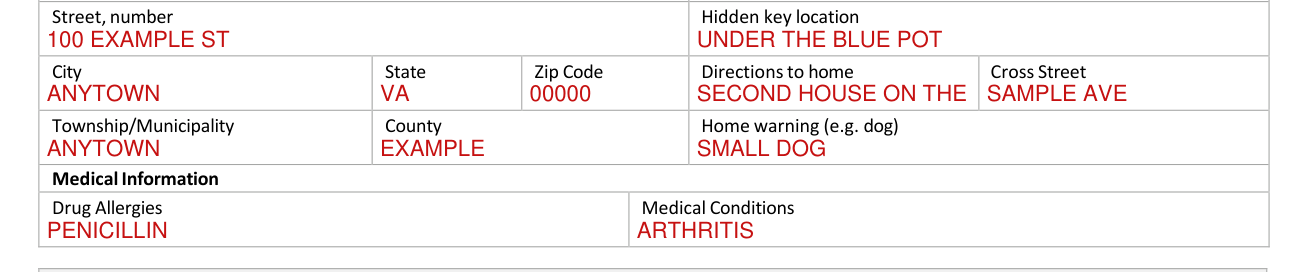
Under Home Address, enter Street, number, City, State, Zip Code, Township/Municipality and County.
Under Additional Information, enter Hidden key location, Directions to home, Cross Street and Home warning (e.g. dog).
Under Medical Information, enter Drug Allergies and Medical Conditions.
Information about Caregivers
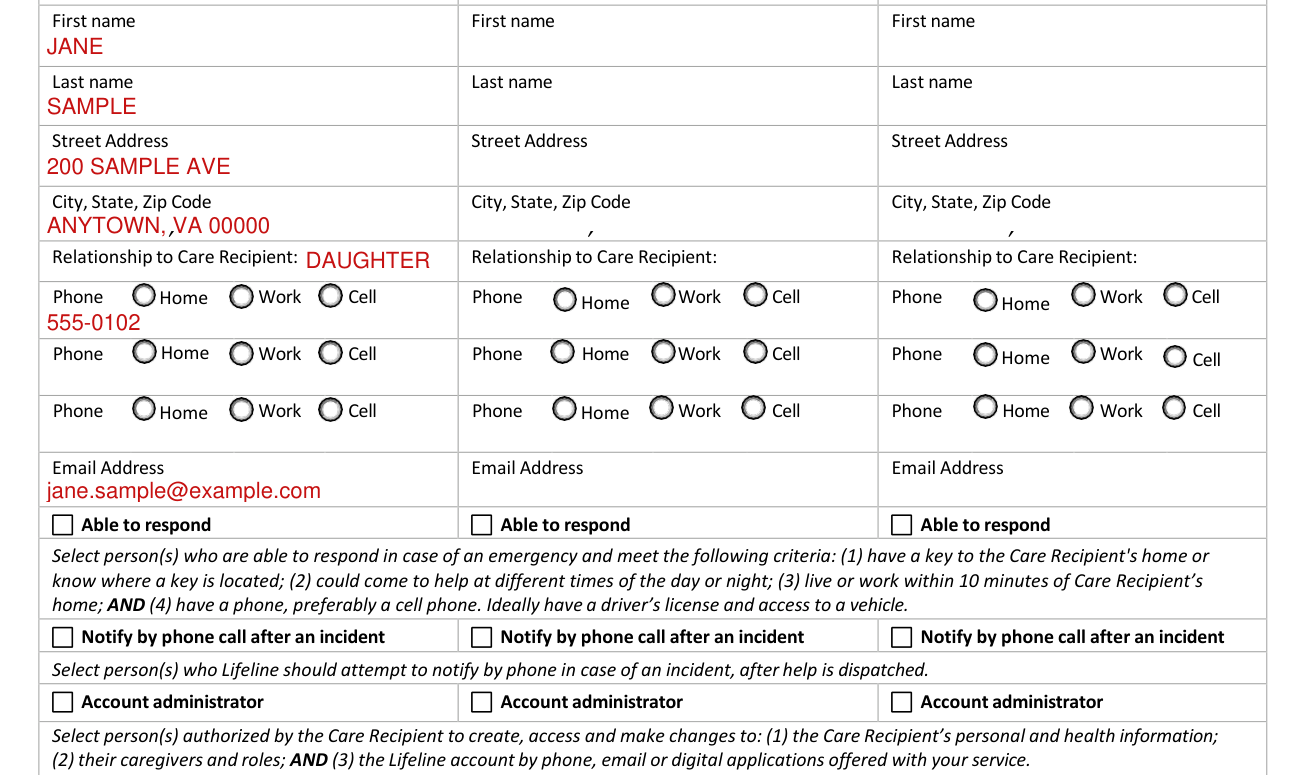
Under Information about Caregivers, enter for each of Caregiver One, Caregiver Two and Caregiver Three the First name, Last name, Street Address, City, State, Zip Code, Relationship to Care Recipient and Email Address.
Phone: mark Home, Work or Cell and enter the number.
Under Able to respond, select person(s) who are able to respond in case of an emergency and meet the following criteria: (1) have a key to the Care Recipient's home or know where a key is located; (2) could come to help at different times of the day or night; (3) live or work within 10 minutes of Care Recipient's home; AND (4) have a phone, preferably a cell phone. Ideally have a driver's license and access to a vehicle.
Under Notify by phone call after an incident, select person(s) who Lifeline should attempt to notify by phone in case of an incident, after help is dispatched.
Under Account administrator, select person(s) authorized by the Care Recipient to create, access and make changes to: (1) the Care Recipient's personal and health information; (2) their caregivers and roles; AND (3) the Lifeline account by phone, email or digital applications offered with your service.
More rules for Lifeline Care Plan Agreement
Under Primary physician, enter First name, Last name, Street address and Phone.
Under Third parties to be notified (if applicable), enter First name, Last name, Street address and Fax.
Under Information about Payer and payment, enter First name, Last name, If applicable, organization name, Phone, Billing address, City, State, ZIP code and Payer email address.
Enter Affiliation Name and ID and Medical Insurance Identification Number; State funded is a box you can mark.
Payment Frequency: Monthly, 6 Months or Yearly. Payment Method: Invoice, Credit Card or Debit Card.
Information about the service: For internal Lifeline use only.
Multiple Subscriber Household: Complete a separate Care Plan Agreement for each Subscriber/Care Recipient.
You may opt-out of receiving Automated Communications by contacting the number provided in such Automated Communications. Lifeline will honor opt-out requests within 30 days. Regardless of opt-out preference, Lifeline may still contact any provided number regarding healthcare communications or emergencies.
Common questions about Lifeline Care Plan Agreement
Who signs it?
Sign on the Signature of Subscriber/Care Recipient line and enter the Date. The Payer, if different from the Subscriber/Care Recipient, signs on the Signature of Payer (if different from subscriber) line and enters the Date. By signing you confirm that: 1. the information is accurate and complete; and 2. you agree to the terms of this agreement and accompanying document HOW LIFELINE WORKS.
Where do I file it?
Return this Care Plan Agreement to Lifeline using the envelope included with your equipment box.
Are there fees?
The form lists Monthly Fee(s) for Monitoring Service, and One Time Fee(s) for Enrollment Fee and Shipping & Handling.
What am I certifying when I sign?
The Subscriber/Care Recipient signs, and the Payer too if different. By signing as the Subscriber/Care Recipient you confirm that: 1. the information is accurate and complete; 2. you agree to the terms of this agreement and accompanying document HOW LIFELINE WORKS; and 3. you have been given the User Manual for the Lifeline equipment.
Sources
[1] Lifeline Care Plan Agreement (P/N 300003440811 Rev. C), Lifeline (the Official source link on this page).
