


SDMC Form 200 at a glance
What it is: SDMC Form 200 is the Declaration for Major Medical Treatment.
Who signs: This attestation must be signed by the declarant and dated AFTER all other supporting documents have been reviewed by the declarant.
What to bring and attach to SDMC Form 200
Include all Declaration supporting documents fully completed: SDMC Form 200 Declaration for Major Medical Treatment, SDMC Form 210 Certification on Capacity for Major Medical Treatment, SDMC Form 220-A Certification on Need for Major Medical Treatment, SDMC Form 220-B Related Medical Information for Major Medical Treatment.
Include supplemental medical information related to the procedure: Physician's consult, office notes, scripts, etc. supporting the medical procedure requested on Form 220-A; Reports for other diagnostic testing related to the procedure or treatment; Most recent Annual Physical Exam; Most current lab results; Most current EKG (if available); Most current chest x-ray (if available).
A filled-in SDMC Form 200 example: a nurse declares for a nursing home patient

How to fill out SDMC Form 200, box by box
INSTRUCTIONS
Complete the fillable form, print the form and sign the attestation on page 7 in black ink.
Submit by secure email (sdmc@justicecenter.ny.gov); fax (518) 549-0460 or mail.
401 State Street Schenectady, NY 12305.
If mailing, single-sided pages only; no staples.
Return all 4 SDMC declaration forms together to SDMC with the required supporting documentation.
Always call SDMC at (518) 549-0328 to confirm receipt in each case.
Part 1. Patient Information
Fill in Last Name, First Name, Date of Birth and Age; Religion is optional.
Mark MALE or FEMALE for Sex, then fill in Street Address, City, State and Zip.
Fill in Phone, Ext, Fax and Cell; include area code.
Fill in COUNTY of Patient's Residence.
Type of Residence
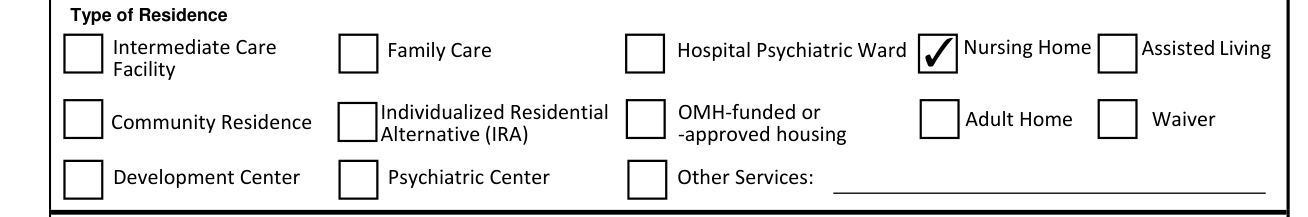
Type of Residence: Family Care, Hospital Psychiatric Ward, Nursing Home, Assisted Living, Intermediate Care Facility, Adult Home, Waiver, Community Residence, Individualized Residential Alternative (IRA), OMH-funded or -approved housing, Development Center, Psychiatric Center and Other Services.
Part 2. Proposed Major Medical Procedure or Treatment

What is the proposed procedure or treatment being sought on behalf of the patient? Refer to Part 4 on the SDMC Form 220-A Certification on Need for Major Medical Treatment.
Part 3. Biopsy

Will a biopsy be performed? YES, NO, Possible Biopsy or Unknown.
Part 4. Anesthesia

What is the physician's anticipated method of anesthesia, if known? IV Sedation or MAC, General Anesthesia, Unknown*, None or Local. *If unknown at this time, please consult with physician. This will be discussed at the hearing.
Part 5a. Declarant
The declarant should be familiar with the patient and be able to speak to the issues of capacity, surrogacy and best interest for this specific case.
The declarant identified in Part 5a must also sign the attestation on page 7.
Fill in Last Name, First Name, Title, Email Address, Agency Name (Please avoid abbreviations), Work Mailing Address, City, State, Zip, Phone, Ext, Fax and Cell.
Part 5b. Alternate Declarant
Alternate Declarant [Required]: THIS CANNOT BE THE SAME PERSON AS THE DECLARANT. The alternate declarant will be contacted if the declarant is not available and should be familiar with the patient and be able to speak to the issues of capacity, surrogacy and best interests for this specific case.
Part 5g. Hospital | Nursing Home Contact
Hospital | Nursing Home Contact (Case Manager, Social Worker, Discharge Planner): provide information if the patient has been transferred to a hospital, rehabilitation center or nursing home.
Part 6. Other Agencies Providing Services for the Patient
Please list any other agencies providing services for the patient if not previously listed on this declaration: (i.e. day program Not Medical Services or Clinics).
Part 7b. Possible surrogate
Please identify the possible surrogate and provide information to explain why the surrogate does not wish or is not able to make the decision (attach additional page if needed): Last Name, First Name, Relationship, Mailing Address, Email Address and Phone (Include area code).
Please indicate if the surrogate has a known opinion regarding the proposed treatment: Agrees, Disagrees, Unknown opinion or Does not wish to make the decision.
Part 8a. Correspondent, Community Advocate or Family Care Provider
A Correspondent is a person who has demonstrated a genuine interest in promoting the best interests of the patient by having a personal relationship with the patient, by participating in the patient's care and treatment or by regularly communicating with the patient [Mental Hygiene Law 80.03(k)].
Has the correspondent provided an opinion on the proposed treatment? Agree, Disagree or Unknown.
Part 9. Supporting Documentation Review [REQUIRED]
Yes: the Declarant has read the Certification on Capacity for Major Medical Treatment (SDMC Form 210) that has been completed by a NYS Licensed Psychiatrist or NYS Licensed Psychologist.
(Circle One) Yes: the Declarant has read the Certification on Need for Major Medical Treatment (SDMC Form 220-A) that has been completed by a Physician | Dentist | Podiatrist.
Part 10. Additional Information Required
List the TITLE (i.e. Dr., RN, Care Coordinator) of the person who explained the proposed major medical treatment(s) to the patient.
Describe the patient's reaction, if any, when the treatment(s) was/were explained, and any opinions expressed.
Based on your personal knowledge of this patient, explain in your own words why the patient cannot give informed consent for this procedure.
Based on your personal knowledge of this patient, explain in your own words why you believe the proposed treatment(s) is/are in the best interest of the patient.
Part 11. Communication Needs
Does the patient understand English? Yes or No. Does the patient speak English as their primary language? Yes or No.
If the patient is nonverbal, or has limited expressive language, how does the patient communicate his/her needs?
Does the patient use an interpreter for sign language or for a language other than English? Yes or No. If YES, please indicate the type of interpreter needed (language, ASL). If the patient uses a communication board or other assistive device, the communication device must be brought to the hearing.
Part 12. The SDMC Hearing
MHL Article 80 requires the patient to be present at the hearing, if able.
Is there a medical condition that would prevent the patient from attending the hearing? Yes or No. If yes, please add a description. Alternative arrangements for the panel to meet with the patient will be made.
Part 13. Attestation by the Declarant
This form must be dated the same or later than the other forms in this case. This includes the Certification on Capacity for Major Medical Treatment (SDMC Form 210); Certification on Need for Major Medical Treatment (SDMC Form 220-A); Related Medical Information for Major Medical Treatment (SDMC Form 220-B).
Only an actual personal signature or an official electronic signature may be used.
Do not insert a text signature in a font that mimics handwriting, as it will not be accepted.
More rules for SDMC Form 200
Retain a copy for your records.
Sources
[1] SDMC Form 200 (09/2024), Declaration for Major Medical Treatment, Justice Center for the Protection of People with Special Needs, New York State (the Official source link on this page).