


Form H1200-MBIC at a glance
What it is: Form H1200-MBIC, Application for Benefits, Medicaid Buy-In for Children, can help pay medical bills for children with disabilities.
Where and when to file: Fax: 1-877-447-2839. If your form is 2-sided, fax both sides. Mail: Health and Human Services Commission, P.O. Box 149024, Austin, TX 78714-9024.
The child must be age 18 or younger.
The child must meet the same rules for a disability that are used to get Supplemental Security Income (SSI).
If a parent's employer pays at least half of the annual cost of health insurance, the parent must sign up and keep that insurance.
The family must meet income limits set by the program.
What to bring and attach to Form H1200-MBIC
Health and Human Services Commission: Send copies of the following items (don't send originals); we only need items that apply to your case.
Proof of money from a job: Pay stubs or earning statements.
Proof of money not from a job (veterans benefits, Social Security income, etc.): Award letters.
Medical costs: Bills or statements from health care providers (doctors, hospitals, drug stores, etc.) from the past 6 months.
A filled-in Form H1200-MBIC example: a mother applies for her son

How to fill out Form H1200-MBIC, box by box
Child applying for benefits

Under Child applying for benefits, enter the Child's Full Name and the Social Security number, and mark Yes No for Is the child married?
Enter the Home Address - street and number, City, State, ZIP Code, County of Residence and Home Phone.
Where the child lives and citizenship

Enter the Date of Birth and mark Male Female for Is the child. Mark Yes No for Does the child live in Texas? Does the child plan to stay in Texas? Is the child a U.S. citizen?
If the child is not a U.S. citizen: Is the child a refugee or legally admitted immigrant? Yes No Is the child registered with the U.S. Citizenship and Immigration Services? Yes No If yes, give immigrant registration number:
Sign and date the form
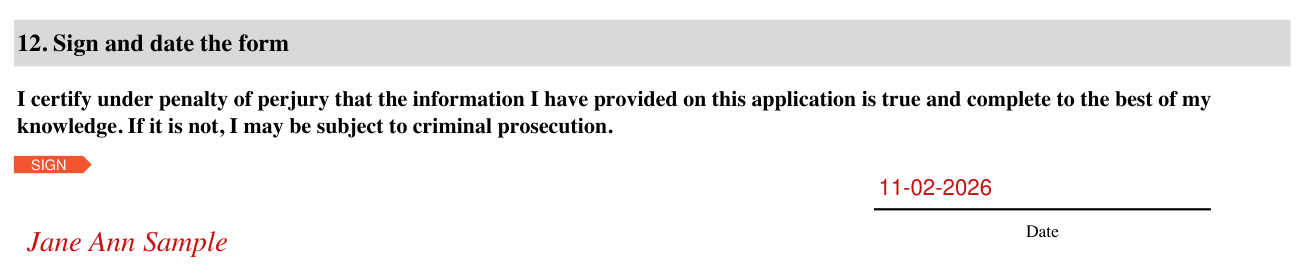
12. Sign and date the form
"I certify under penalty of perjury that the information I have provided on this application is true and complete to the best of my knowledge. If it is not, I may be subject to criminal prosecution."
More rules for Form H1200-MBIC
This program helps families who make too much money to get traditional Medicaid.
Fill out this form. You can ask a friend or family member to help you.
Answer each question on the form. If a question does not apply to you, write “none” for the answer.
Call or visit an HHSC benefits office. To find an office near you, call 2-1-1 (toll-free). 2-1-1 also can answer questions about this program. When you call: (1) pick a language (2) pick option 2.
The child is (mark one or more): American Indian or Alaska Native, Asian, Black or African-American, Native Hawaiian or Pacific Islander, White, Hispanic or Latino.
Under 1st parent, enter the Parent's Full Name, Social Security number (optional) and Date of Birth (optional), mark Yes No for Do you live with the child?, and mark Male Female for Are you:
Do you want this parent's employer to answer these questions? Yes No If yes, give the attached "Employment Verification" (Form H1028-MBIC) to your employer. Ask your employer to fill out the form and send it to the Health and Human Services Commission. (12-2016-E)
Enter the Employer's Name and Employer's Address, the Gross amount paid (before taxes are taken out), How often are you paid? (once a week, twice a month, etc.), and mark Yes No for Does your job have health insurance?
Does the child applying for benefits get health insurance coverage through your job? Yes No If no, answer the following question, then go to the next section: If your job has insurance and your child isn't on it, what is the next date you could enroll your child?
If yes, answer the next 6 questions: 1. What date did insurance coverage start? 2. How much do you pay for the insurance? 3. Does your employer pay at least half of the premium (this is usually a monthly payment)? Yes No 4. What is your policy number? 5. What is the insurance company's name? 6. What is the insurance company's address?
The following questions are about the 2nd parent's job and their job's health insurance.
Does a child applying for benefits have any brothers or sisters who are: (a) age 21 or younger, and (b) living in the same home? Yes No If no, skip this section.
For each Brother or Sister, enter the Full Name, Social Security number (optional) and Date of Birth (optional), and mark Yes No for Does this person have a job? If this person has a job, give employer's name and address:
Enter the Gross amount paid (before taxes are taken out) and How often are you paid? (once a week, twice a month, etc.) If age 18 to 21: Is this person in school or training for a job? Yes No
The following question is about health coverage other than Medicaid, Medicare, or your job's insurance: Does anyone pay now, or has anyone paid in the past year, for health coverage for the child applying for benefits? Yes No If yes, Health and Human Services Commission: tell us the following: Name of insurance company, Policy number, Address of insurance company, Coverage start date, Coverage end date.
Medicaid sometimes can pay for medical services you got 3 months before you applied. Does the child applying for benefits have medical bills for services they got in the past 3 months? Yes No If yes, send: (1) Copies of medical bills from the past 3 months. (2) Proof of money you got (income) from the past 3 months.
Health and Human Services Commission: Tell us about any other types of money you get; attach proof of the money you get (award letters or earning statements); we might not count some of the money you get.
For each Type of money, enter the Monthly amount (before taxes are taken out): Social Security, Veterans benefits, Railroad retirement, Civil service, Pension, Annuity, Interest, Farm income, Mineral / Royalty, Gifts, Other income not from a job.
Do you want to give someone the right to act for you - to be your authorized representative? Yes No If yes, Health and Human Services Commission: tell us about that person: Name of authorized representative, Organization, Mailing address, Phone.
The following is for anyone age 17 years and 10 months or older: If you are not registered to vote where you live now, would you like to apply to register to vote here today? Yes No. If you do not check either box, you will be considered to have decided not to register to vote at this time.
You only need to give the Social Security numbers (SSN) for people who want benefits. Giving or applying for an SSN is voluntary; however, anyone who doesn't apply for an SSN or doesn't give an SSN can't get benefits.
"I will let HHSC know within 10 days of any changes that could affect my eligibility. This includes changes in income, living arrangement or insurance (including health insurance premiums)."
Common questions about Form H1200-MBIC
Is there a deadline?
Health and Human Services Commission: After we get your form, we will check to see if you can get benefits; someone might contact you if we need more information; we will let you know the decision within 45 days.
Where do I file it?
Mail: Health and Human Services Commission, P.O. Box 149024, Austin, TX 78714-9024.
Are there fees?
The family might have to pay a monthly fee.
Is there a penalty?
"I understand that if I obtain or assist another person in obtaining, medical assistance by fraudulent means, I may be charged with a state or federal offense; and I may also be held liable for any repayment of benefits fraudulently obtained."
Sources
[1] Form H1200-MBIC (December 2016-E), Application for Benefits - Medicaid Buy-In for Children, Texas Health and Human Services Commission (the Official source link on this page).