

Form 10-10EZR at a glance
What it is: Form 10-10EZR, the Health Benefits Update Form, is used by VA to update your personal, insurance, or financial information after you are enrolled.
Who signs: You or an individual to whom you have delegated your Power of Attorney must sign and date the form.
All Veterans must complete Sections I, II, VII, and VIII.
Complete only the sections that apply to you; sign and date the form.
What to bring and attach to Form 10-10EZR
If you have access to a copier, attach a copy of your insurance cards, Medicare card and/or Medicaid card.
Attach any continuation sheets, a copy of supporting materials or your Power of Attorney documents to your application.
A filled-in Form 10-10EZR example: a Veteran updates insurance information

How to fill out Form 10-10EZR, box by box
Section I - General Information: name, sex and date of birth

Section I - General Information: Answer all questions.
Enter your name in 1A. VETERAN'S NAME (Last, First, Middle Name).
Enter your 1B. PREFERRED NAME.
Enter your 2. SOCIAL SECURITY NUMBER (999-99-9999).
Mark FEMALE or MALE for 3. SEX.
Enter your 4. DATE OF BIRTH (mm/dd/yyyy).
Telephone numbers, mailing address, home address and e-mail
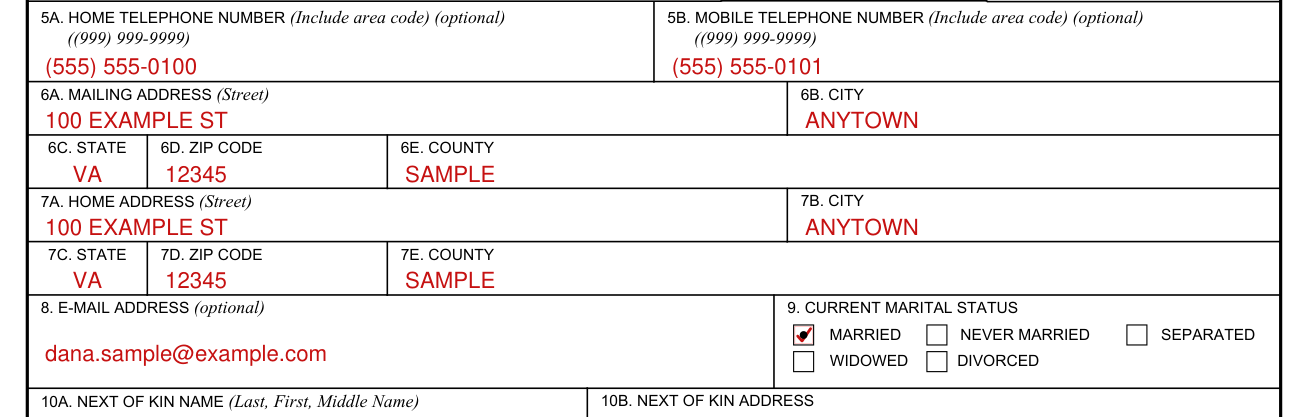
Enter your 5A. HOME TELEPHONE NUMBER and 5B. MOBILE TELEPHONE NUMBER (Include area code) (optional) as (999) 999-9999.
Enter your 6A. MAILING ADDRESS (Street), 6B. CITY, 6C. STATE, 6D. ZIP CODE and 6E. COUNTY.
Enter your 7A. HOME ADDRESS (Street), 7B. CITY, 7C. STATE, 7D. ZIP CODE and 7E. COUNTY.
Enter your 8. E-MAIL ADDRESS (optional).
Current marital status, next of kin and emergency contact
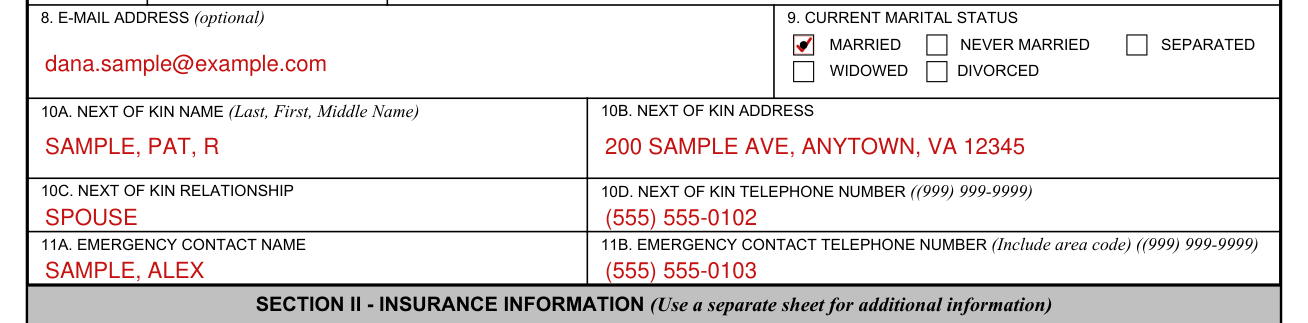
Mark one for 9. CURRENT MARITAL STATUS: MARRIED, NEVER MARRIED, SEPARATED, WIDOWED or DIVORCED.
Enter the 10A. NEXT OF KIN NAME (Last, First, Middle Name) and the 10B. NEXT OF KIN ADDRESS.
Enter the 10C. NEXT OF KIN RELATIONSHIP and the 10D. NEXT OF KIN TELEPHONE NUMBER ((999) 999-9999).
Enter the 11A. EMERGENCY CONTACT NAME and the 11B. EMERGENCY CONTACT TELEPHONE NUMBER (Include area code) ((999) 999-9999).
Section II - Insurance Information: company, policy holder, policy number and group code
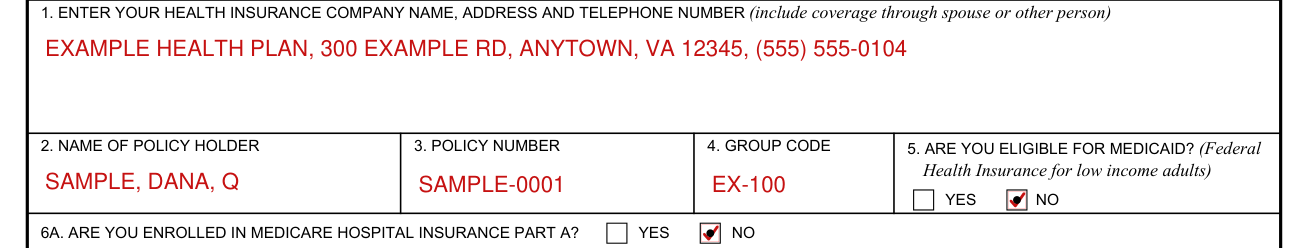
Section II - Insurance Information: Include information for all health insurance companies that cover you, this includes coverage provided through a spouse or significant other.
If you have more than one health insurer, provide this information on a separate sheet of paper and attach to the application.
Enter 1. Your health insurance company name, address and telephone number (include coverage through spouse or other person).
Enter the 2. NAME OF POLICY HOLDER, 3. POLICY NUMBER and 4. GROUP CODE.
Medicaid and Medicare Hospital Insurance Part A
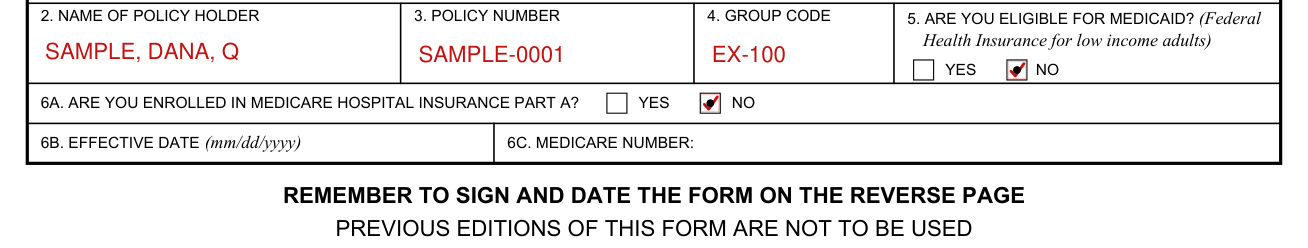
Mark YES or NO for 5. ARE YOU ELIGIBLE FOR MEDICAID? (Federal Health Insurance for low income adults).
Mark YES or NO for 6A. ARE YOU ENROLLED IN MEDICARE HOSPITAL INSURANCE PART A?
Enter the 6B. EFFECTIVE DATE (mm/dd/yyyy) and the 6C. MEDICARE NUMBER.
Section III - Military Service Information
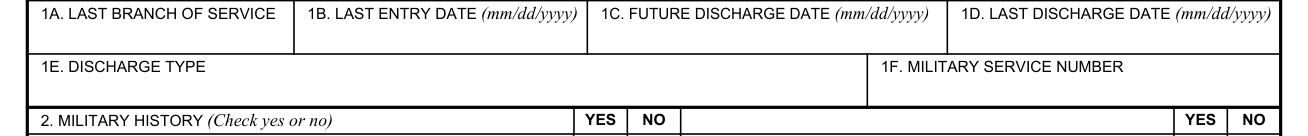
If you are not currently receiving benefits from VA, you may attach a copy of your discharge or separation papers from the military (such as DD-214), with your signed application to expedite processing of your application.
Enter 1A. LAST BRANCH OF SERVICE, 1B. LAST ENTRY DATE (mm/dd/yyyy), 1C. FUTURE DISCHARGE DATE (mm/dd/yyyy) and 1D. LAST DISCHARGE DATE (mm/dd/yyyy).
Enter 1E. DISCHARGE TYPE and 1F. MILITARY SERVICE NUMBER.
Section V - Previous Calendar Year Gross Annual Income
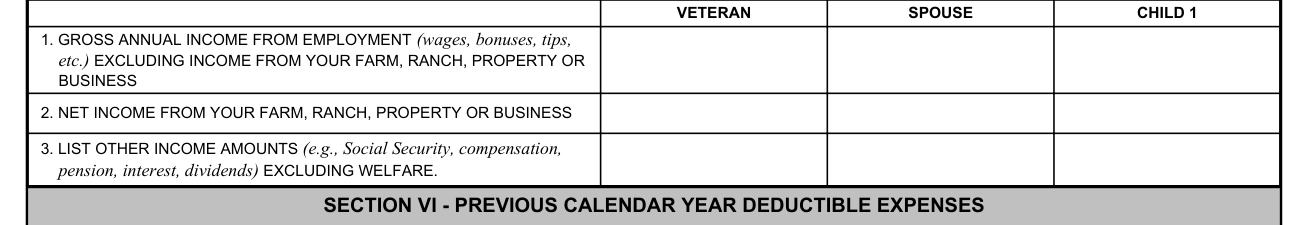
Veterans rated 50-100% disabled due to SC conditions and Veterans receiving VA pension are not required to provide a financial assessment.
Enter VETERAN, SPOUSE and CHILD 1 (Use a separate sheet for additional dependents).
For 1, report gross annual income from employment, except for income from your farm, ranch, property or business; include your wages, bonuses, tips, severance pay and other accrued benefits and your child's income information if it could have been used to pay your household expenses.
For 2, report net income from your farm, ranch, property, or business.
For 3, report other income amounts, including retirement and pension income, Social Security Retirement and Social Security Disability income, compensation benefits such as VA disability, cash gifts, interest and dividends.
Section VI - Previous Calendar Year Deductible Expenses

Report non-reimbursed medical expenses paid by you or your spouse.
For 1, enter total non-reimbursed medical expenses paid by you or your spouse.
For 2, enter the amount you paid last calendar year for funeral and burial expenses (including prepaid burial expenses) for your deceased spouse or dependent child (Also enter spouse or child's information in Section III.).
For 3, enter the amount you paid last calendar year for your college or vocational educational expenses (e.g., tuition, books, fees, materials). DO NOT LIST YOUR DEPENDENTS' EDUCATIONAL EXPENSES.
Section VIII - Submitting Your Update: signature and date

Sign in ink in SIGNATURE OF APPLICANT and enter the DATE (mm/dd/yyyy).
If you sign with an "X", 2 people you know must witness you as you sign. They must sign the form and print their names.
If the form is not signed and dated appropriately, VA will return it for you to complete.
Federal law provides criminal penalties, including a fine and/or imprisonment, for any materially false, fictitious, or fraudulent statement or representation.
"I declare under penalty of perjury that the foregoing is true and accurate to the best of my knowledge."
Section VII - Consent to Copays: By submitting this application, you are agreeing to pay the applicable VA copayments for care or services (including urgent care) as required by law.
Mail the completed VA Form 10-10EZR and any supporting materials to the Health Eligibility Center, PO Box 5207, Janesville, WI 53547-5207.
More rules for Form 10-10EZR
PREVIOUS EDITIONS OF THIS FORM ARE NOT TO BE USED.
If your situation is different
You check yes or no for Military history
Check yes or no for A. ARE YOU A PURPLE HEART AWARD RECIPIENT?
Check yes or no for B. ARE YOU A FORMER PRISONER OF WAR?
Check yes or no for C. DID YOU SERVE IN A COMBAT THEATER OF OPERATIONS AFTER 11/11/1998?
Check yes or no for D. Were you discharged or retired from military for a disability incurred in the line of duty?
Check yes or no for E. Did you serve in SW Asia during the Gulf War between August 2, 1990 and November 11, 1998?
Check yes or no for F. DO YOU HAVE A VA SERVICE-CONNECTED RATING?
You check yes or no for Military exposure information
Check yes or no for A. DID YOU SERVE IN AN IONIZING RADIATION LOCATION AND PARTICIPATE IN ANY NUCLEAR TESTING, TREATMENTS, OR CLEAN UP?
Check yes or no for B. DID YOU SERVE IN ANY OF THE FOLLOWING GULF WAR HAZARD LOCATIONS?
Check yes or no for C. WERE YOU DEPLOYED IN SUPPORT OF ANY OF THE FOLLOWING OPERATIONS?
Check yes or no for D. DID YOU SERVE IN ANY OF THE FOLLOWING HERBICIDE (e.g. Agent Orange) LOCATIONS?
Check all that apply for E. HAVE YOU BEEN EXPOSED TO ANY OF THE FOLLOWING? (Check all that apply)
For E, enter WHEN WERE YOU EXPOSED? as an approximate time-frame (mm/yyyy) FROM and TO.
Please provide an approximate time-frame (mm/yyyy) FROM and TO for WHEN DID YOU SERVE IN THESE LOCATIONS?
You have a spouse to list in Section IV - Dependent Information
Enter 1. SPOUSE'S NAME (Last, First, Middle Name) and 2. SPOUSE'S SOCIAL SECURITY NUMBER (999-99-9999). Use a separate sheet for additional dependents.
Enter 3. SPOUSE'S DATE OF BIRTH (mm/dd/yyyy) and mark MALE or FEMALE for 4. SPOUSE'S SEX.
Enter 5. DATE OF MARRIAGE (mm/dd/yyyy) and 6. SPOUSE'S ADDRESS AND TELEPHONE NUMBER (Street, City, State, ZIP - if different from Veteran's).
You have a child to list in Section IV - Dependent Information
You may count your biological children, adopted children, and stepchildren as dependents. These children must be unmarried and under the age of 18, or be at least 18 but under 23 and attending high school, college or vocational school on a full or part-time basis, or have become permanently unable to support themselves before reaching the age of 18.
Enter 7. CHILD'S NAME (Last, First, Middle Name), 8. CHILD'S DATE OF BIRTH (mm/dd/yyyy), 9. CHILD'S SOCIAL SECURITY NUMBER (999-99-9999) and 10. DATE CHILD BECAME YOUR DEPENDENT (mm/dd/yyyy).
Check STEPDAUGHTER, STEPSON, DAUGHTER or SON.
Check YES or NO for 12. Was child permanently and totally disabled before the age of 18?
Check YES or NO for 13. If child is between 18 and 23 years of age, did child attend school last calendar year?
Enter 14. Expenses paid by your dependent child with reportable income for college, vocational rehabilitation or training (e.g., tuition, books, materials).
Check YES or NO for 15. If your spouse or dependent child did not live with you last year, did you provide support?
Where to get help with Form 10-10EZR
Ask VA to help you fill out the form by calling 1-877-222-VETS (8387).
Sources
[1] VA Form 10-10EZR (FEB 2025), Health Benefits Update Form, U.S. Department of Veterans Affairs (the Official source link on this page).
