
Updated:
Get Form Now
CMS L564-R297, also known as “Request for Employment Information,” is designed for individuals who are applying for Medicare and are seeking to qualify for the premium-free Part A based on their employment history or that of a spouse. The CMS L564-R297 is filled out by the applicant’s employer or the employer of the spouse, and it verifies the employment and health insurance coverage details necessary to establish eligibility for premium-free Medicare Part A, which is generally available without a premium to those who have paid Medicare taxes for a sufficient number of quarters during their working years.
What it is: Medicare Request for Employment Information is a form to show proof of group health plan coverage based on current employment so you can enroll in Medicare.
Who signs: All Employers: Signature of company official, Date signed (mm/dd/yyyy).
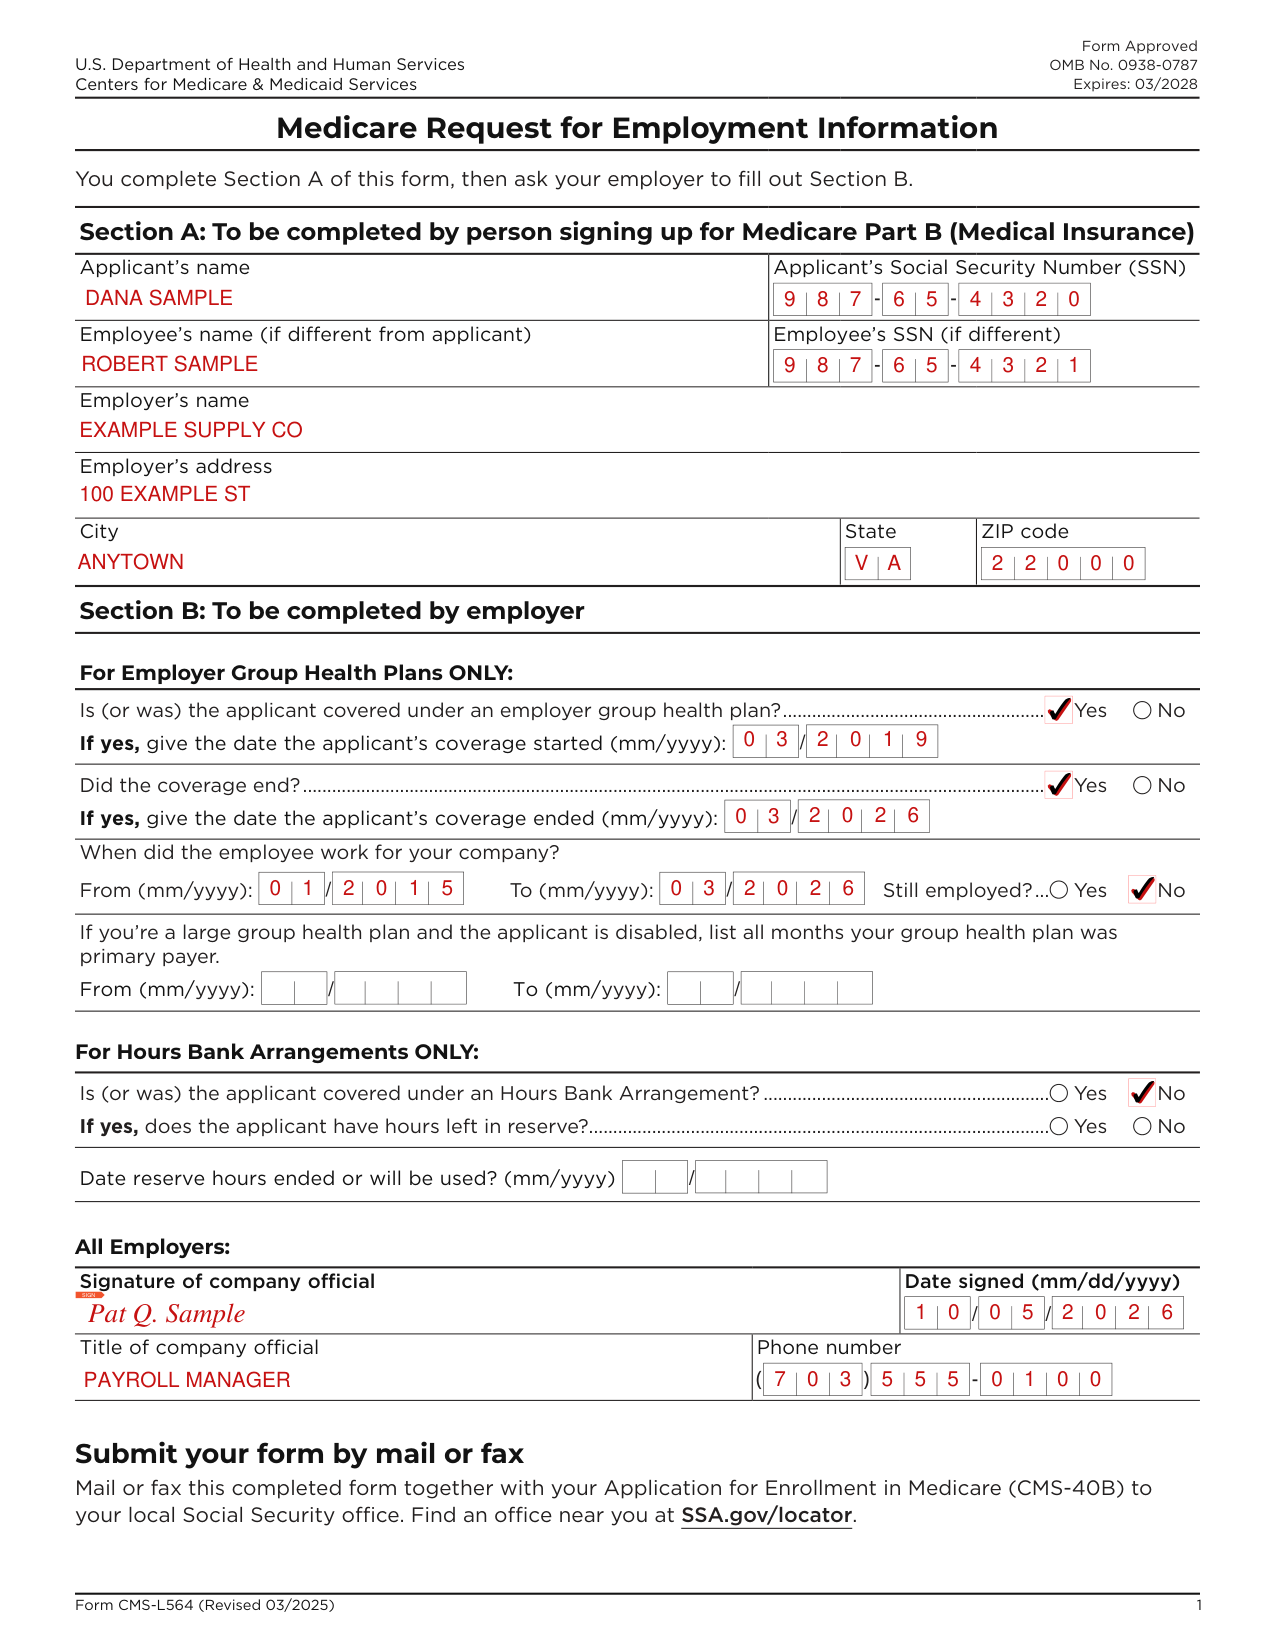
You complete Section A of this form, then ask your employer to fill out Section B.
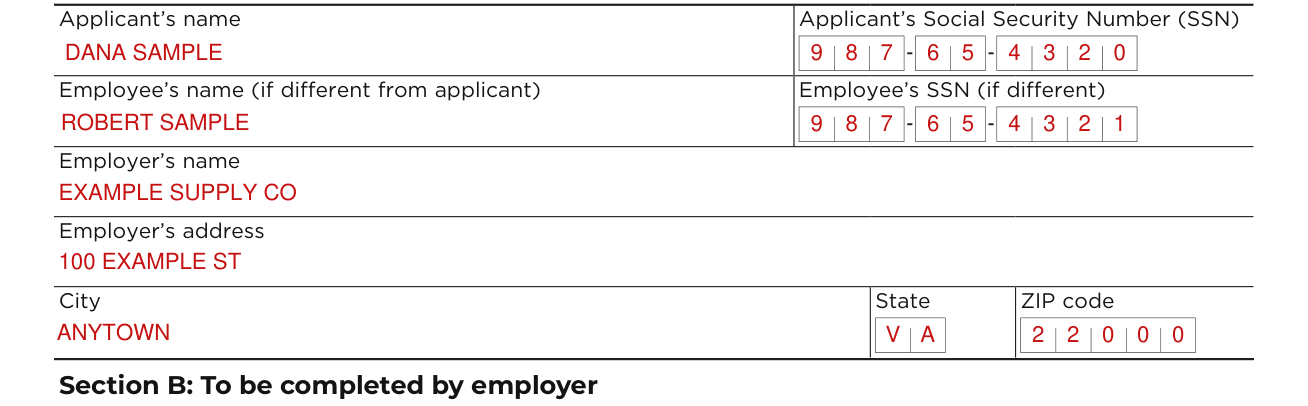
Section A is to be completed by person signing up for Medicare Part B (Medical Insurance): enter Applicant's name, Applicant's Social Security Number (SSN), Employee's name (if different from applicant) and Employee's SSN (if different).
Enter Employer's name, Employer's address, City, State and ZIP code.
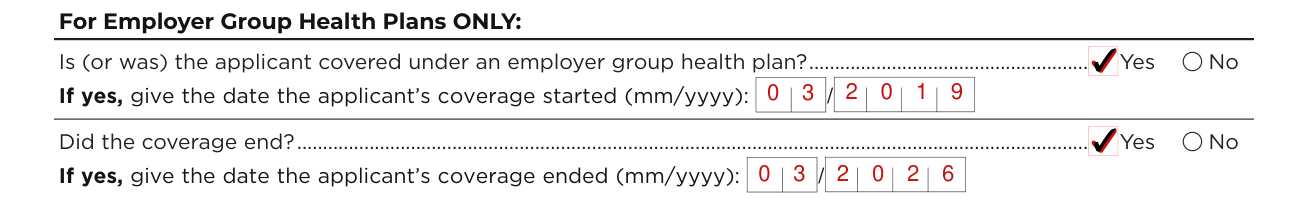
Section B is to be completed by employer. For Employer Group Health Plans ONLY: Is (or was) the applicant covered under an employer group health plan? Yes or No. If yes, give the date the applicant's coverage started (mm/yyyy).
Did the coverage end? Yes or No. If yes, give the date the applicant's coverage ended (mm/yyyy).

When did the employee work for your company? Enter From (mm/yyyy) and To (mm/yyyy), and Still employed? Yes or No.

If you're a large group health plan and the applicant is disabled, list all months your group health plan was primary payer, From (mm/yyyy) and To (mm/yyyy).
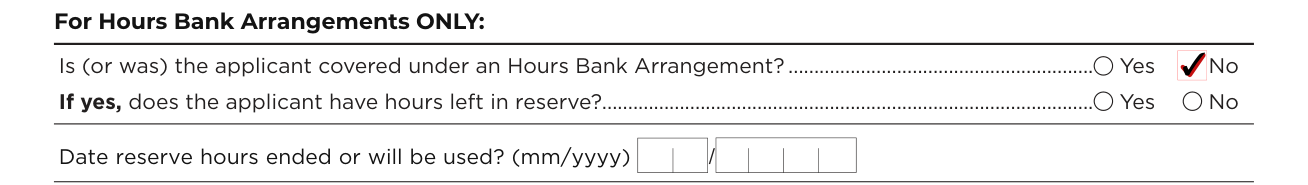
For Hours Bank Arrangements ONLY: Is (or was) the applicant covered under an Hours Bank Arrangement? Yes or No.
If yes, does the applicant have hours left in reserve? Yes or No. Enter the Date reserve hours ended or will be used? (mm/yyyy).

All Employers: Signature of company official, Date signed (mm/dd/yyyy).
Also enter Title of company official and Phone number.
If you qualify for Medicare because of a disability, you must have large group health plan coverage based on your, your spouse's or a family member's current employment.
To enroll in Medicare through a Special Enrollment Period, you must have had group health plan coverage through your or your spouse's current employment since the first month you were eligible for Medicare Part B. Your coverage must not have ended more than 8 months ago.
Submit your form by mail or fax. Mail or fax this completed form together with your Application for Enrollment in Medicare (CMS-40B) to your local Social Security office. Find an office near you at SSA.gov/locator.
[1] Form CMS-L564 (Revised 03/2025), Medicare Request for Employment Information, Centers for Medicare & Medicaid Services (the Official source link on this page).