

Reportable Event Record/Report at a glance
What it is: REPORTABLE EVENT RECORD/REPORT of the Arizona Department of Health Services Division of Licensing Services Long Term Care Licensing.
Who signs: State in your own words what you witnessed (be very descriptive) and sign. Signature of Witness and Date.
A filled-in Reportable Event Record/Report example: a nurse reports one event by fax

How to fill out Reportable Event Record/Report, box by box
Today's Date, Date of Event and Time of Event
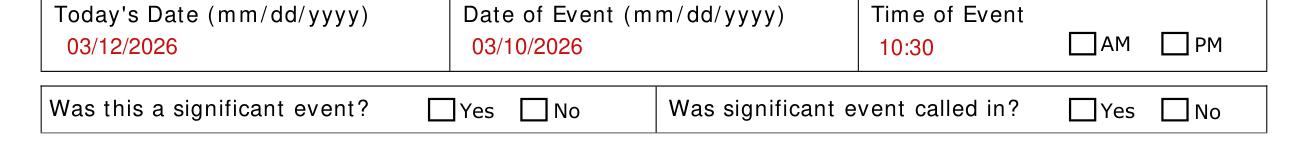
Enter Today's Date (mm/ dd/ yyyy), Date of Event (mm/ dd/ yyyy) and Time of Event.
Mark Yes or No for: Was this a significant event? Was significant event called in?
Full Name of Facility, Street Address and Facility License Number
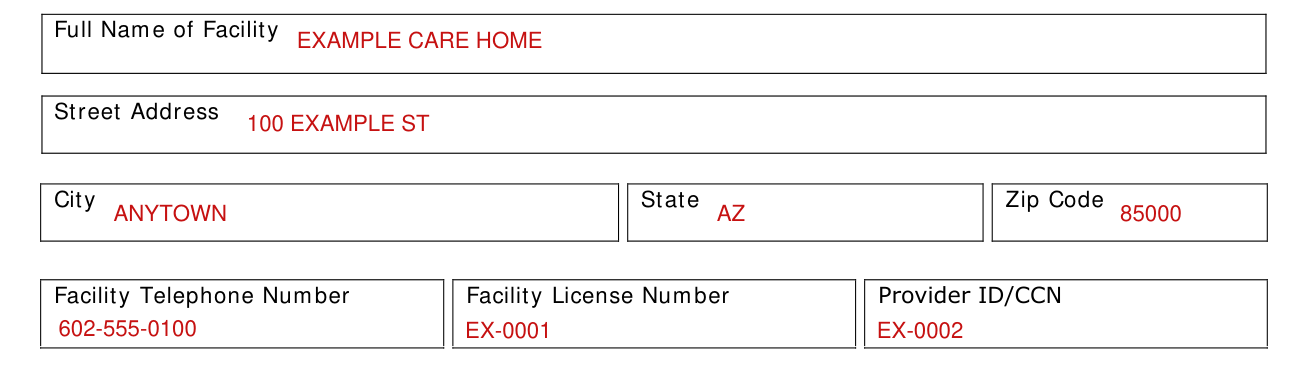
Enter the Full Name of Facility, Street Address, City, State and Zip Code.
Enter the Facility Telephone Number, Facility License Number and Provider ID/CCN.
Person Reporting and Title

Enter the Person Reporting and Title.
More rules for Reportable Event Record/Report
Answer ALL questions fully and address only one event per report. Complete Investigations Include: staff, resident, and witness interviews as well as ALL pertinent information.
Type of Incident (check all that apply): Elopement, Environmental Emergency, Financial Exploitation, Injury Incident, Involuntary Discharge, Other, Specify, Injury Unknown Origin, Neglect, Resident Care, Resident-to-Resident Abuse, Staff-to-Resident Abuse, Unexpected Death.
Who was notified of the occurrence (check all that apply)? Law Enforcement: Police Dept. Name, Case Number, Officer.
Nursing Board, Other Family/ Guardian, Medical Examiner, APS, Physician, Ombudsman, Pharmacy Board, ADHS (Name of surveyor you spoke to and time you called.)
Is the event an allegation of abuse, neglect or misappropriation of funds? Yes No. If yes, complete the Alleged Perpetrator Information Section.
Under ALLEGED PERPETRATOR INFORMATION enter Name: Last, First, MI, Alias, Address: Street/ Box, City, State, Zip, Telephone Number and Date of Hire (mm/dd/yyyy).
AP Suspended? Yes No Date (mm/dd/yyyy). AP Terminated? Yes No Date (mm/dd/yyyy).
Under CREDENTIALING/ LI CENSURE INFORMATION enter the Certificate or License No. and the Type of Certification (check all that apply): Nurse Aid (NA), Certified Nurse Aid (CNA), Registered Nurse (RN), Licensed Practical Nurse (LPN), Other (specify type: ).
Enter the Resident Name, Date of Admission (mm/dd/yyyy), Date of Birth (mm/dd/yyyy) and Exact Location of Incident.
Narrative: 1) Describe the event, including timeframes/ risk factors related to the incident/ event (relevant resident dx and cognitive status. If resident to resident altercation is this the first time the resident was involved in an altercation?)
2) Prior to the event, was a plan of care developed that addressed this issue, and were planned interventions in place when the event occurred? For example, a chair alarm or a lap buddy in place. Yes No Please describe:
3) What interventions were implemented after the incident/ event? For example, supervision, resident sent to hospital, CNA suspended. Please describe investigative findings/ conclusions:
Use Separate sheet for each witness/ person interviewed on the Witness Statement Form of the Facility Investigation Report for Resident Abuse, Neglect, Misappropriation of Property, And Exploitation of Residents in Long-Term Care Facilities.
On the form enter Date, Time, AM or PM, Witness Full Name, Job Title, Shift, Home Address, City/ Zip, Home Phone #, Work Phone # and Relation to Resident: (If any).
Common questions about Reportable Event Record/Report
Who signs it?
State in your own words what you witnessed (be very descriptive) and sign. Signature of Witness and Date.
Is there a deadline?
Submit via Fax within 5 days of event.
Where do I file it?
Arizona Department of Health Services Long Term Care Licensing: 150 N. 18th Ave., Ste. 440 Phoenix, AZ 85007, Fax: (602) 324-0993.
What am I certifying when I sign?
The information provided is true to the best of my knowledge.
Sources
[1] Reportable Event Record/Report (revised 11/07/2017), Arizona Department of Health Services (the Official source link on this page).