


Recommended Clinical Review (Predetermination) Request Form - Medical and Surgical at a glance
What it is: This is the Recommended Clinical Review (Predetermination) Request Form for Medical and Surgical.
Where and when to file: Fax each completed Recommended Clinical Review Request Form to 800-852-1360. If unable to fax, you may mail your request to BCBSIL, PO Box 660603, Dallas, TX, 75266-0603.
A filled-in Recommended Clinical Review (Predetermination) Request Form - Medical and Surgical example: a provider office submits a standard request
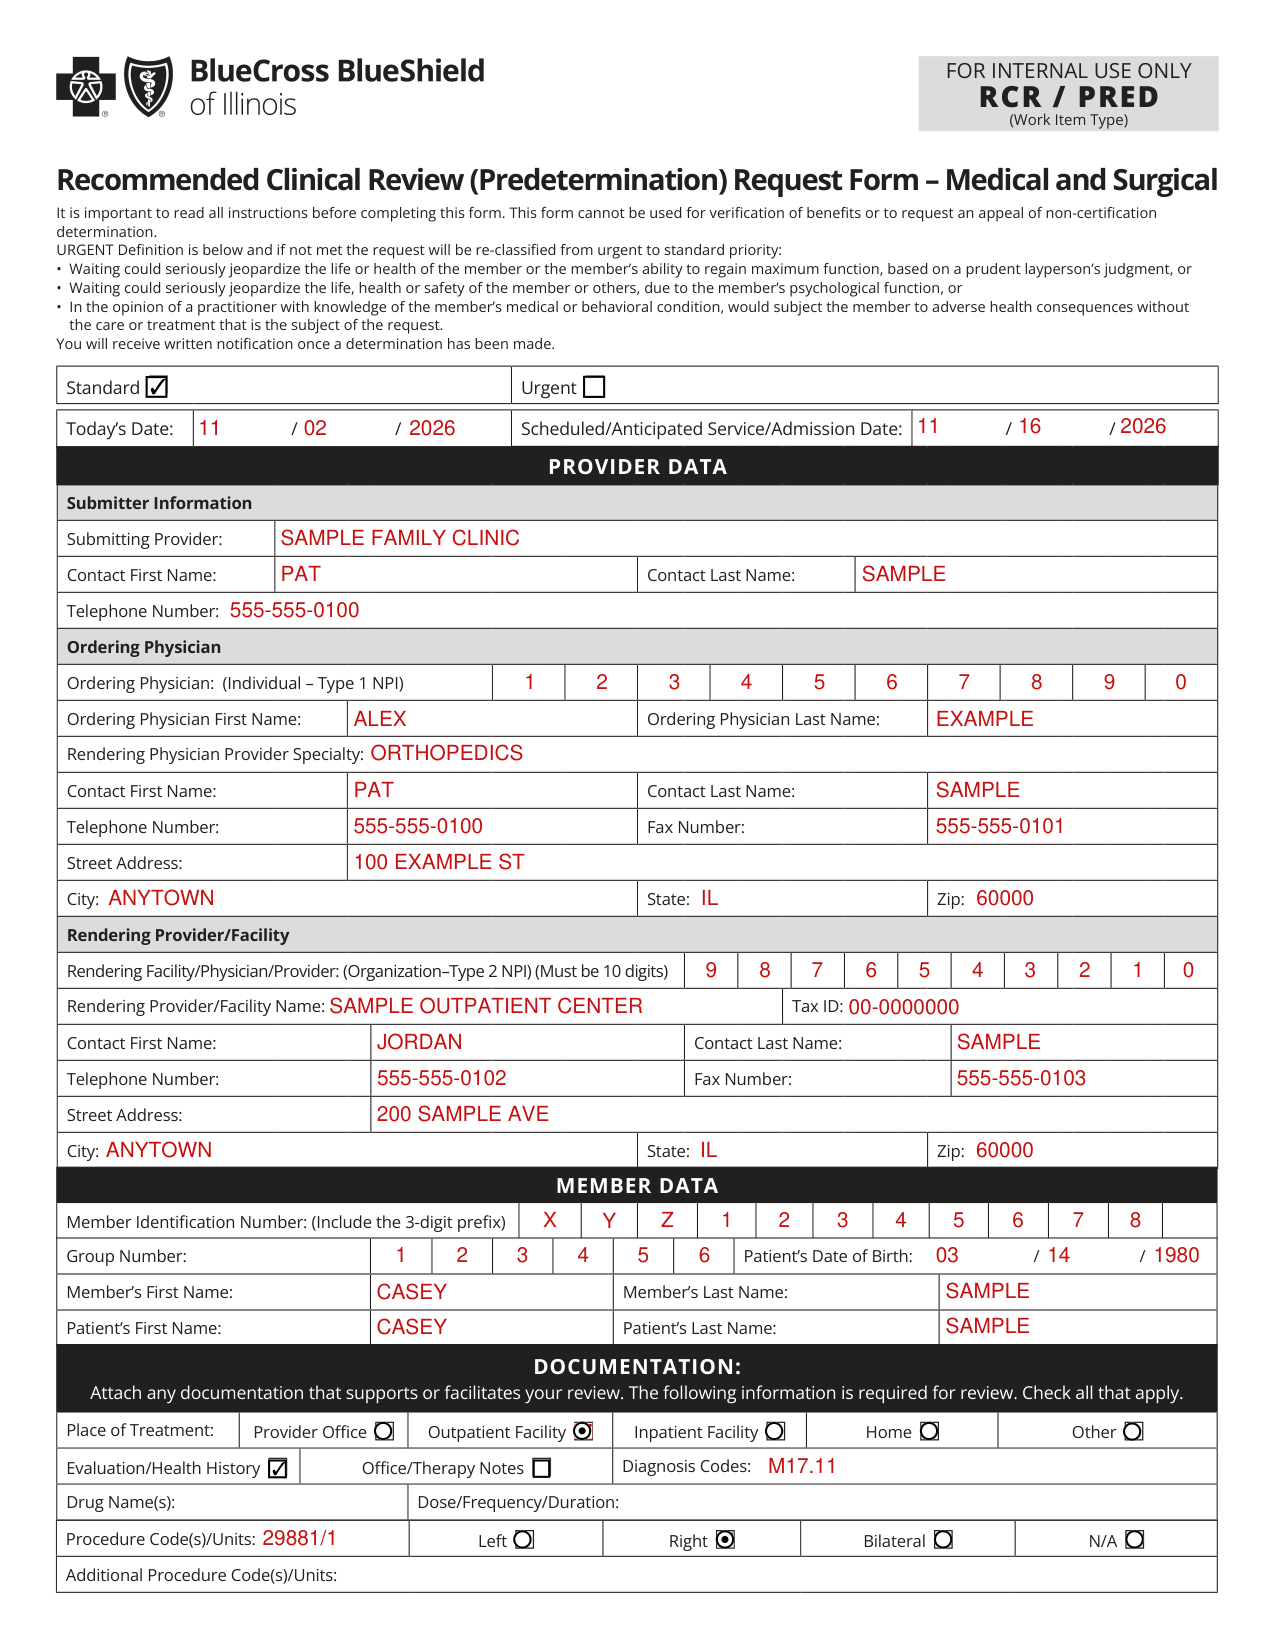
How to fill out Recommended Clinical Review (Predetermination) Request Form - Medical and Surgical, box by box
Standard Urgent

If the URGENT definition is not met, the request will be re-classified from urgent to standard priority.
Waiting could seriously jeopardize the life or health of the member or the member's ability to regain maximum function, based on a prudent layperson's judgment.
Waiting could seriously jeopardize the life, health or safety of the member or others, due to the member's psychological function.
In the opinion of a practitioner with knowledge of the member's medical or behavioral condition, would subject the member to adverse health consequences without the care or treatment that is the subject of the request.
Today's Date and Scheduled/Anticipated Service/Admission Date

Enter Today's Date and the Scheduled/Anticipated Service/Admission Date.
Submitter Information
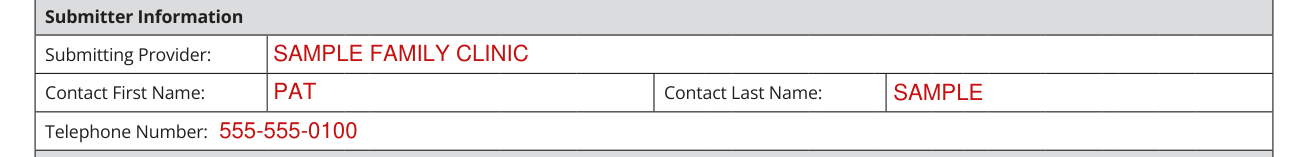
Under Submitter Information, enter the Submitting Provider, Contact First Name, Contact Last Name and Telephone Number.
Ordering Physician
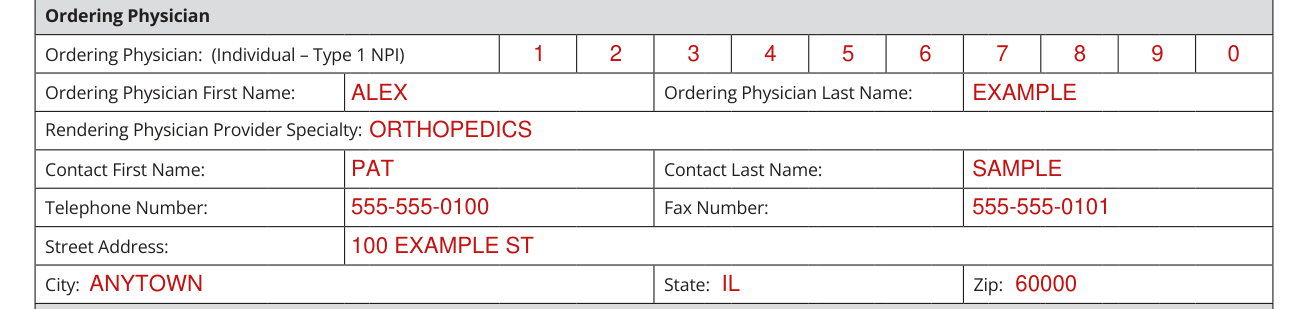
Under Ordering Physician, enter the Ordering Physician (Individual - Type 1 NPI), Ordering Physician First Name, Ordering Physician Last Name, Rendering Physician Provider Specialty, Contact First Name, Contact Last Name, Telephone Number, Fax Number, Street Address, City, State and Zip.
Rendering Provider/Facility
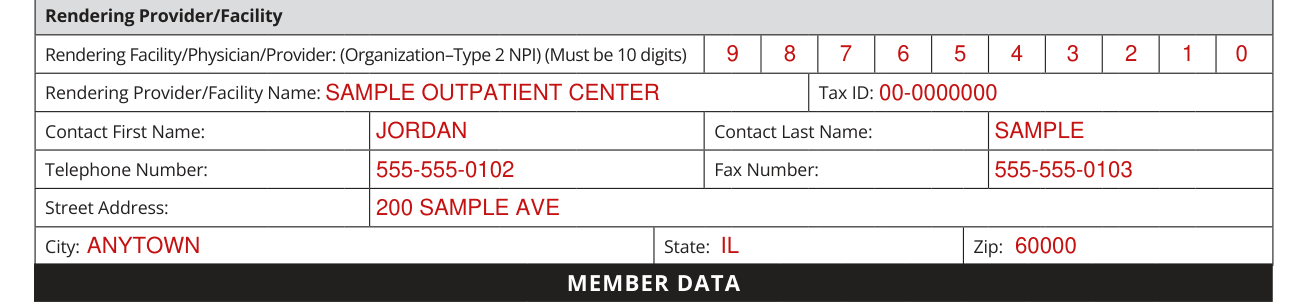
Under Rendering Provider/Facility, the Rendering Facility/Physician/Provider (Organization-Type 2 NPI) must be 10 digits.
Under Rendering Provider/Facility, enter the Rendering Provider/Facility Name, Tax ID, Contact First Name, Contact Last Name, Telephone Number, Fax Number, Street Address, City, State and Zip.
MEMBER DATA
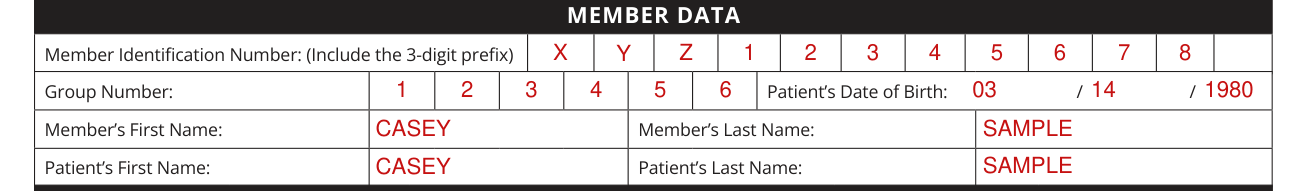
Under MEMBER DATA, include the 3-digit prefix in the Member Identification Number.
Enter the Group Number and the Patient's Date of Birth.
Enter the Member's First Name, Member's Last Name, Patient's First Name and Patient's Last Name.
DOCUMENTATION

Attach any documentation that supports or facilitates your review.
The following information is required for review. Check all that apply.
Place of Treatment: Provider Office, Outpatient Facility, Inpatient Facility, Home or Other.
Evaluation/Health History, Office/Therapy Notes and Diagnosis Codes.
Enter the Drug Name(s) and Dose/Frequency/Duration.
Enter the Procedure Code(s)/Units, mark Left, Right, Bilateral or N/A, and enter any Additional Procedure Code(s)/Units.
More rules for Recommended Clinical Review (Predetermination) Request Form - Medical and Surgical
It is important to read all instructions before completing this form.
This form cannot be used for verification of benefits or to request an appeal of non-certification determination.
You will receive written notification once a determination has been made.
Always confirm eligibility and benefits first.
You must also complete any other preservice requirements, such as prior authorization, if applicable and required. (For example, all inpatient admissions require prior authorization.)
3. All applicable fields are required. All information and documents provided must be legible. If all required or necessary information is not provided, this may cause a delay in the Recommended Clinical Review process. (Inquiries received without the member/patient's group number, ID number, and date of birth cannot be completed and may be returned to you to supply this information.) Procedure (CPT)/HCPCS codes for requested services along with ICD10 diagnosis codes must be listed on the form.
4. You MUST submit the Recommended Clinical Review to the Blue Cross and Blue Shield Plan that issues or administers the patient's health benefit plan which may not be the state where you are located.
5. Always place the completed Recommended Clinical Review Request Form on top of other supporting documents. Do not send in duplicate requests as this may delay the process.
6. Per Medical Policy, if photos are required for review, please email the photos to photohandling@bcbsil.com. The body of the email should include the patient's first and last name, Group number, Subscriber ID number and the patient's date of birth.
7. A Recommended Clinical Review decision is not a guarantee of payment.
Common questions about Recommended Clinical Review (Predetermination) Request Form - Medical and Surgical
What is a recommended clinical review?
This is the Recommended Clinical Review (Predetermination) Request Form for Medical and Surgical. A Recommended Clinical Review is a voluntary, written request by a member or a provider to determine if a proposed treatment or service is covered under a patient's health benefit plan. A Recommended Clinical Review is not required. The provider and member will be notified when the decision on a Recommended Clinical Review (Predetermination) has been reached.
Where do I file it?
For Federal Employee Program members, fax each completed Recommended Clinical Review Request Form to 888-368-3406. For Behavioral Health biofeedback requests fax to 877-361-7656.
When is this form not the right one?
8. ONLY use this form for requests for Recommended Clinical Review. Do Not Use This Form To: 1) submit a claim for payment or request payment on a claim; 2) request an appeal; 3) confirm eligibility; 4) verify coverage; 5) request a guarantee of payment; 6) ask whether a service requires prior authorization; 7) request a referral to an out of network physician, facility or other health care provider. This form does not apply to government programs (Illinois Medicaid and Medicare Advantage) or any commercial HMO members.
Sources
[1] Recommended Clinical Review (Predetermination) Request Form - Medical and Surgical, Blue Cross and Blue Shield of Illinois (the Official source link on this page).