

Prior Authorization Request Form at a glance
What it is: Prior Authorization Request Form, Blood Clotting Disorder Medications (2), Policy 9.165.
Where and when to file: Fax this form back to 877-503-7231.
A filled-in Prior Authorization Request Form example: a clinic requests NovoSeven
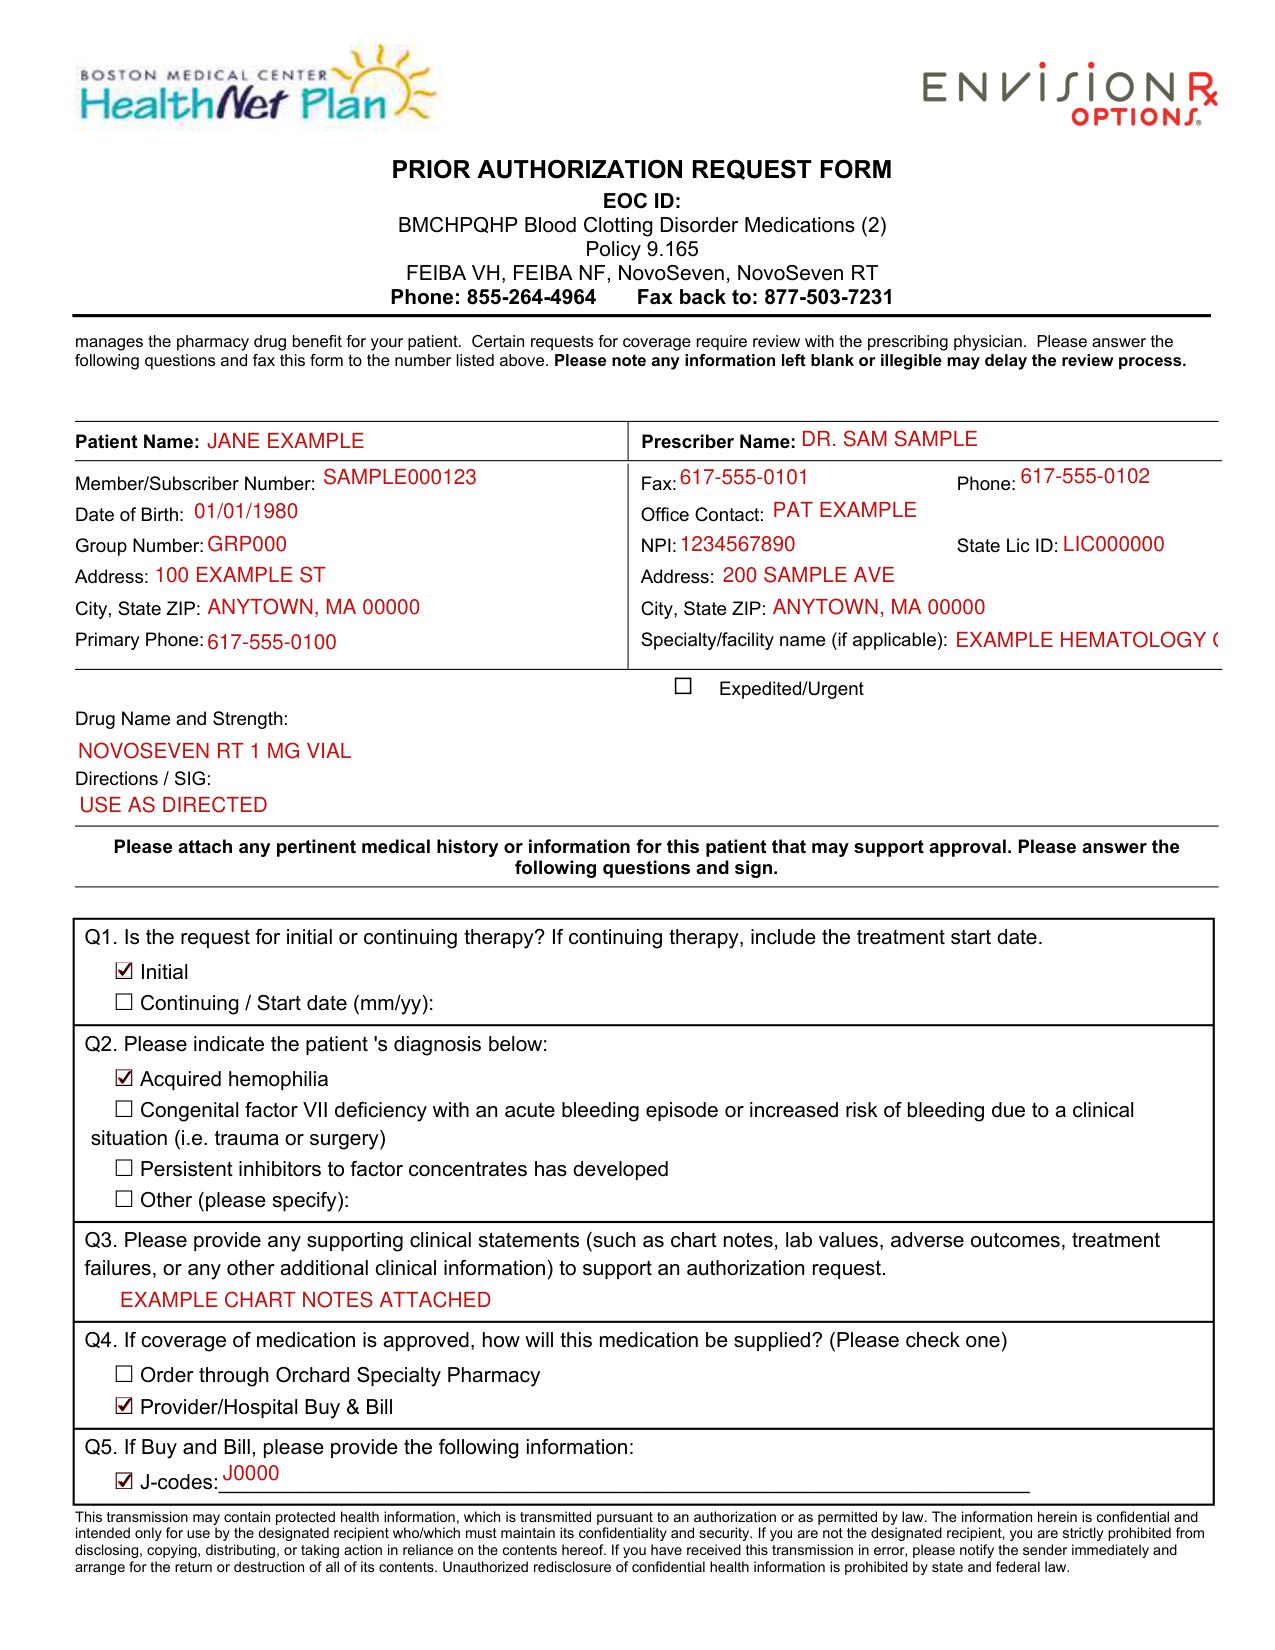
How to fill out Prior Authorization Request Form, box by box
Patient

For the patient, enter Patient Name, Member/Subscriber Number, Date of Birth, Group Number, Address, City, State ZIP and Primary Phone.
Prescriber

For the prescriber, enter Prescriber Name, Fax, Phone, Office Contact, NPI, State Lic ID, Address, City, State ZIP and Specialty/facility name (if applicable).
Drug Name and Strength, Directions / SIG

Enter the Drug Name and Strength and the Directions / SIG.
Initial or continuing therapy

Q1. Say initial or continuing therapy; if continuing therapy, include the treatment start date (mm/yy).
The patient's diagnosis

Q2. Indicate the patient's diagnosis: Acquired hemophilia, Congenital factor VII deficiency with an acute bleeding episode or increased risk of bleeding due to a clinical situation (i.e. trauma or surgery), Persistent inhibitors to factor concentrates has developed, or Other (please specify).
Supporting clinical statements

Q3. Provide any supporting clinical statements (such as chart notes, lab values, adverse outcomes, treatment failures, or any other additional clinical information) to support an authorization request.
How the medication will be supplied

Q4. If coverage of medication is approved, check one for how this medication will be supplied: Order through Orchard Specialty Pharmacy or Provider/Hospital Buy & Bill.
Q5. If Buy and Bill, provide the J-codes, the Procedure code(s) for administration of medication, the Number of Units and Visits, and the Date of planned administration.
Patient, prescriber and signature
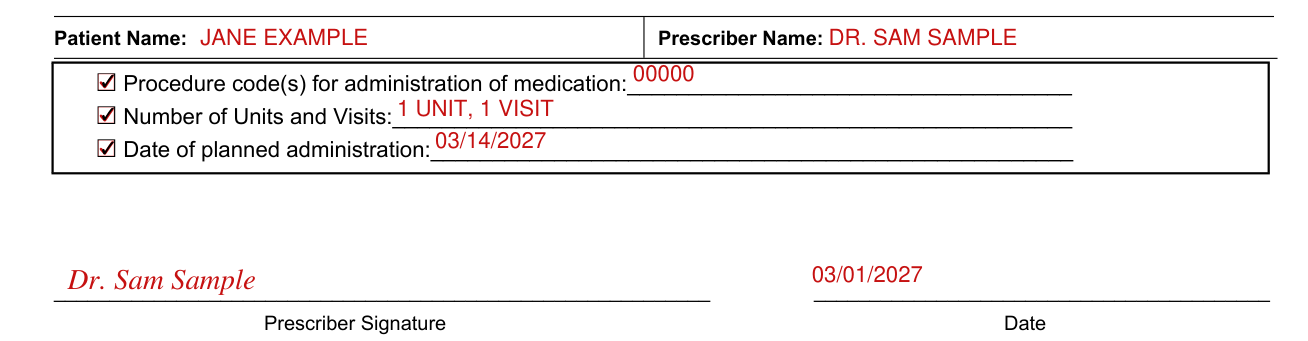
Enter the Patient Name and Prescriber Name, then sign the Prescriber Signature line and enter the Date.
More rules for Prior Authorization Request Form
Certain requests for coverage require review with the prescribing physician. Any information left blank or illegible may delay the review process.
Attach any pertinent medical history or information for this patient that may support approval.
Common questions about Prior Authorization Request Form
Where do I file it?
Fax this form back to 877-503-7231.
Sources
[1] Prior Authorization Request Form, Blood Clotting Disorder Medications (2), Policy 9.165 (the served file; no issuer file found) (the Official source link on this page).
