

Form CA-1 at a glance
What it is: Form CA-1 is the Federal Employee's Notice of Traumatic Injury and Claim for Continuation of Pay/Compensation, from the U.S. Department of Labor Office of Workers' Compensation Programs.
Who signs: Signature of employee or person acting on his/her behalf: sign and enter the Date. The witness signs in Signature of witness and enters the Date signed. The supervisor signs and enters the Date.
Employee: complete all boxes 1 - 15 and do not complete shaded areas. Witness: complete bottom section 16. Employing Agency (Supervisor or Compensation Specialist): complete shaded boxes a, b, and c.
A filled-in Form CA-1 example: an employee reports a fall
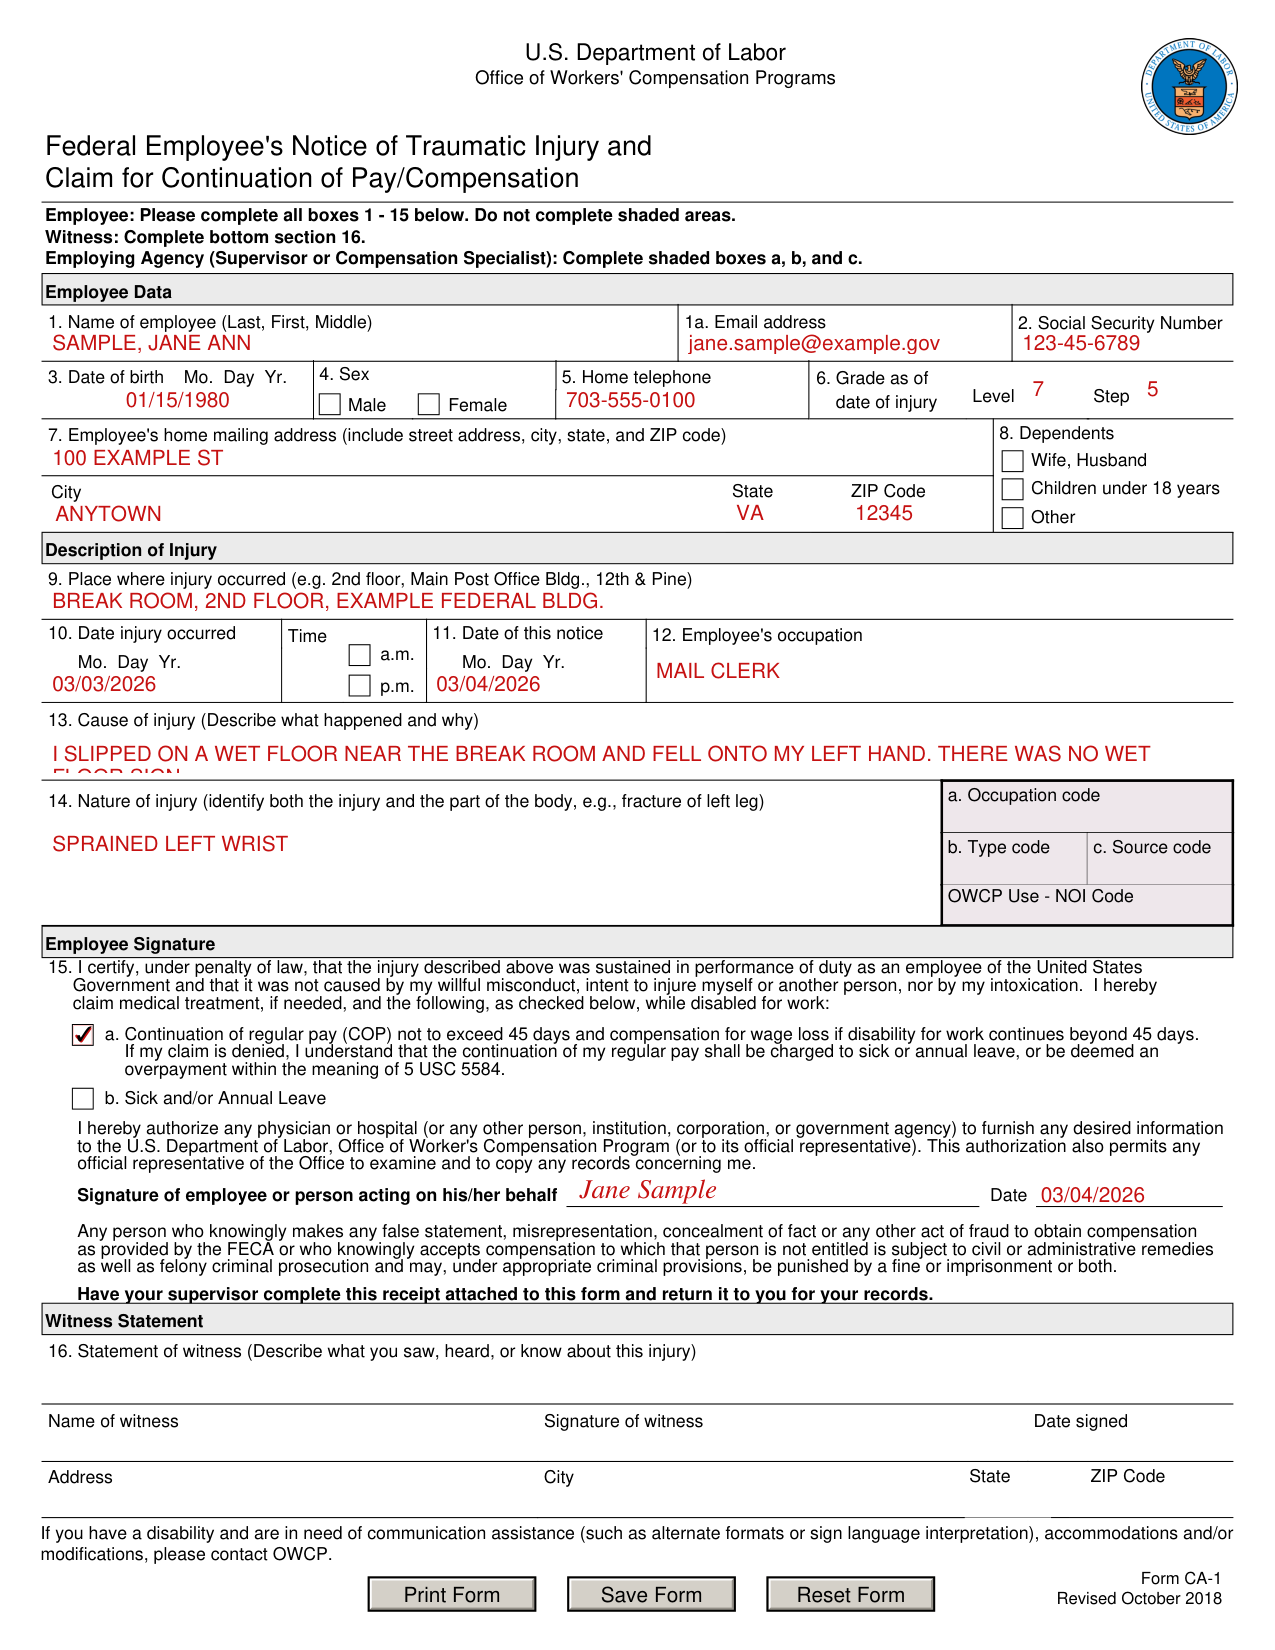
How to fill out Form CA-1, box by box
Employee Data
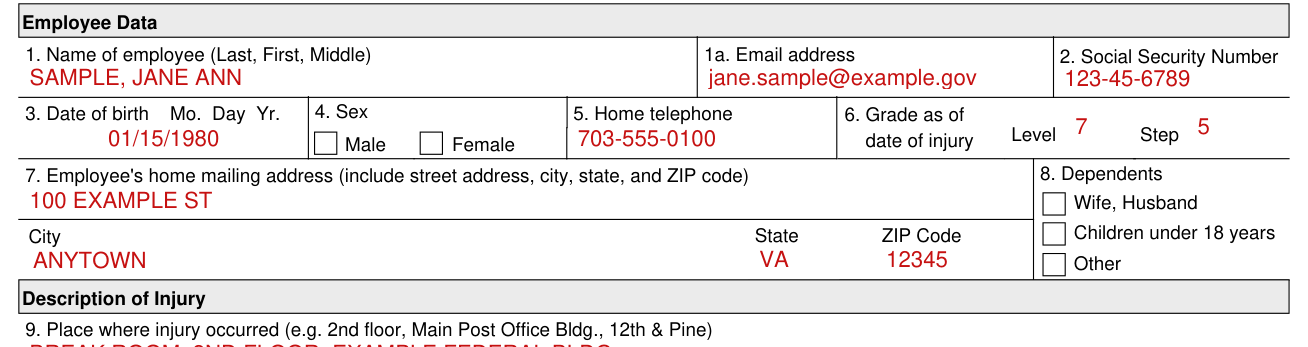
Enter the name of employee (Last, First, Middle) in Box 1 and the Social Security Number in Box 2.
Box 1a, Email address: injured workers should provide an email address when completing this form.
Enter the date of birth (Mo. Day Yr.) in Box 3 and the sex in Box 4.
Enter the home telephone in Box 5 and the grade as of date of injury, Level and Step, in Box 6.
Enter the employee's home mailing address (include street address, city, state, and ZIP code) in Box 7.
Description of Injury
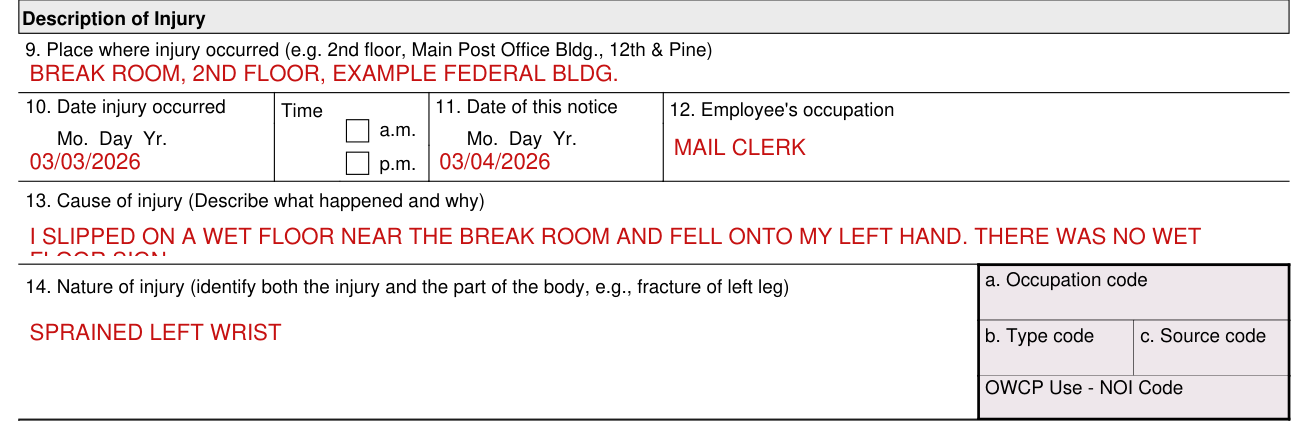
Enter the place where injury occurred in Box 9 (e.g. 2nd floor, Main Post Office Bldg., 12th & Pine).
Enter the date injury occurred (Mo. Day Yr.) and the Time in Box 10, and the date of this notice (Mo. Day Yr.) in Box 11.
Enter the employee's occupation in Box 12.
Box 13, Cause of injury: Describe what happened and why. Describe in detail how and why the injury occurred. Give appropriate details (e.g.: If you fell, how far did you fall and in what position did you land?)
Box 14, Nature of injury: identify both the injury and the part of the body, e.g., fracture of left leg. Give a complete description of the condition(s) resulting from your injury. Specify the right or left side if applicable (e.g., fractured left leg: cut on right index finger).
Employee Signature
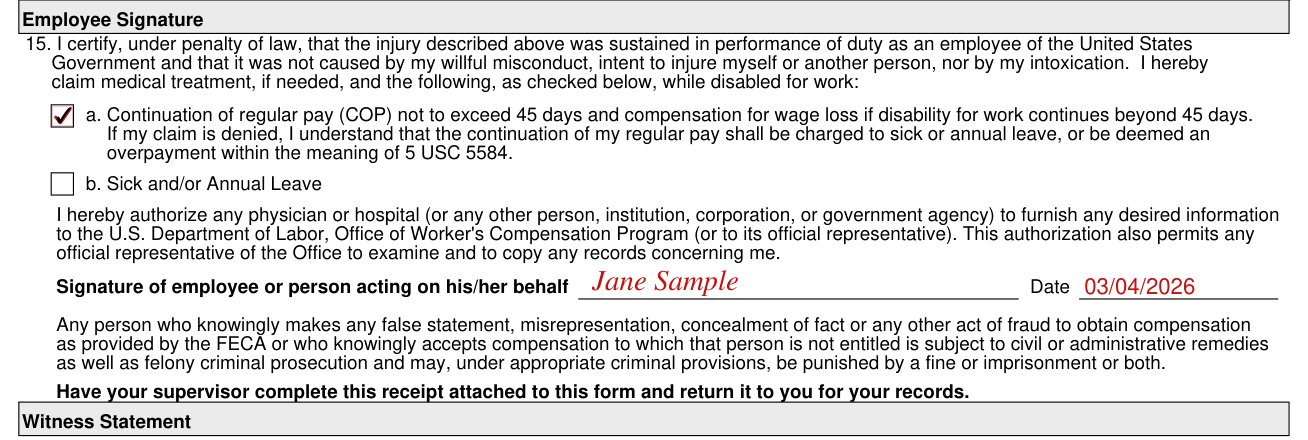
In Box 15, sign the following: "I certify, under penalty of law, that the injury described above was sustained in performance of duty as an employee of the United States Government and that it was not caused by my willful misconduct, intent to injure myself or another person, nor by my intoxication. I hereby claim medical treatment, if needed, and the following, as checked below (Box 15), while disabled for work:"
a. Continuation of regular pay (COP) not to exceed 45 days and compensation for wage loss if disability for work continues beyond 45 days. If my claim is denied, I understand that the continuation of my regular pay shall be charged to sick or annual leave, or be deemed an overpayment within the meaning of 5 USC 5584.
b. Sick and/or Annual Leave. If you elect sick or annual leave you may not claim compensation to repurchase leave used during the 45 days of COP entitlement.
Box 15, Election of COP/Leave: if you are disabled for work as a result of this injury and filed CA-1 within thirty days of the injury, you may be entitled to receive continuation of pay (COP) from your employing agency. COP is paid for up to 45 calendar days of disability, and is not charged against sick or annual leave.
Continuation of pay for disability resulting from traumatic, job-related injury, not to exceed 45 calendar days. To be eligible for continuation of pay, the employee, or someone acting on his/her behalf, must file Form CA-1 within 30 days following the injury and provide medical evidence in support of disability within 10 days of submission of the CA-1.
Signature of employee or person acting on his/her behalf: sign and enter the Date.
Any person who knowingly makes any false statement, misrepresentation, concealment of fact or any other act of fraud to obtain compensation as provided by the FECA or who knowingly accepts compensation to which that person is not entitled is subject to civil or administrative remedies as well as felony criminal prosecution and may, under appropriate criminal provisions, be punished by a fine or imprisonment or both.
Have your supervisor complete this receipt attached to this form and return it to you for your records.
Witness Statement

Box 16, Statement of witness: Describe what you saw, heard, or know about this injury. Then enter the Name of witness, Signature of witness, Date signed, Address, City, State and ZIP Code.
Reporting office and duty station
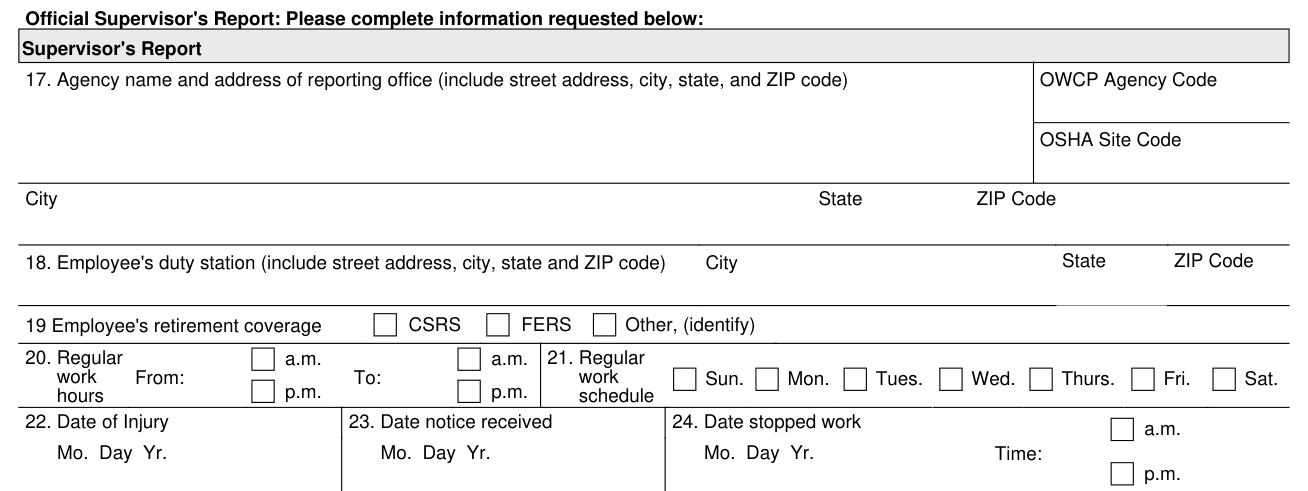
Box 17, Agency name and address of reporting office (include street address, city, state, and ZIP code): the name and address of the office to which correspondence from OWCP should be sent (if applicable, the address of the personnel or compensation office).
Box 18, Employee's duty station (include street address, city, state and ZIP code): the address and zip code of the establishment where the employee actually works.
Box 19, Employee's retirement coverage (CSRS, FERS, Other, identify): indicate which retirement system the employee is covered under.
Box a (Occupation Code), Box b (Type Code), Box c (Source Code) and OSHA Site Code: the Occupational Safety and Health Administration (OSHA) requires all employing agencies to complete these items when reporting an injury.
OWCP Agency Code: this is a four-digit (or four digit plus two letter) code used by OWCP to identify the employing agency.
Performance of duty

Box 28: Was employee injured in performance of duty? Yes or No (If "No," explain).
Box 29: Was injury caused by employee's willful misconduct, intoxication, or intent to injure self or another? Yes (If "Yes," explain) or No.
Third party and physician
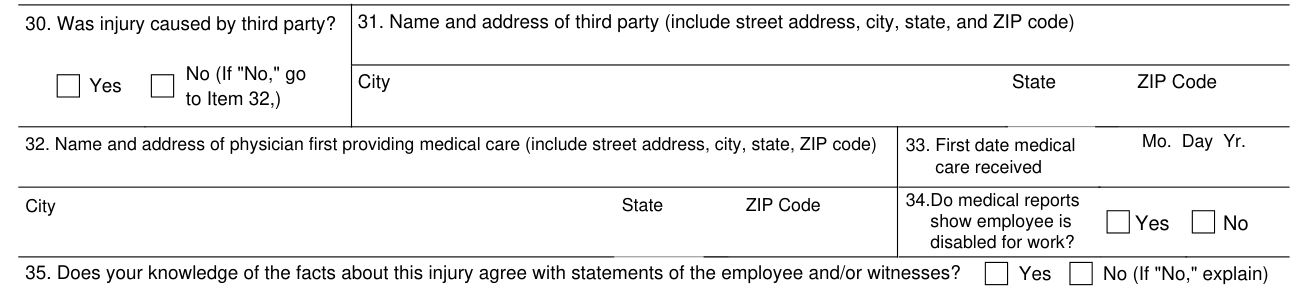
Box 30: Was injury caused by third party? Yes or No (If "No," go to Item 32,).
Box 31: Name and address of third party (include street address, city, state, and ZIP code).
Box 32, Name and address of physician first providing medical care (include street address, city, state, ZIP code): the name and address of the physician who first provided medical care for this injury.
Knowledge of the facts and pay rate
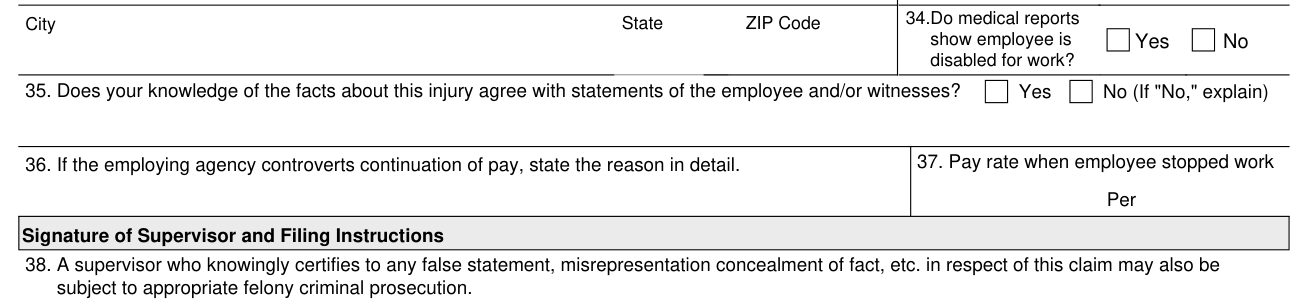
Box 35: Does your knowledge of the facts about this injury agree with statements of the employee and/or witnesses? Yes or No (If "No," explain).
Box 36: If the employing agency controverts continuation of pay, state the reason in detail. The supervisor should also submit any other information or evidence pertinent to the merits of this claim.
Box 37: Enter the Pay rate when employee stopped work and fill in Per.
Signature of Supervisor and Filing Instructions
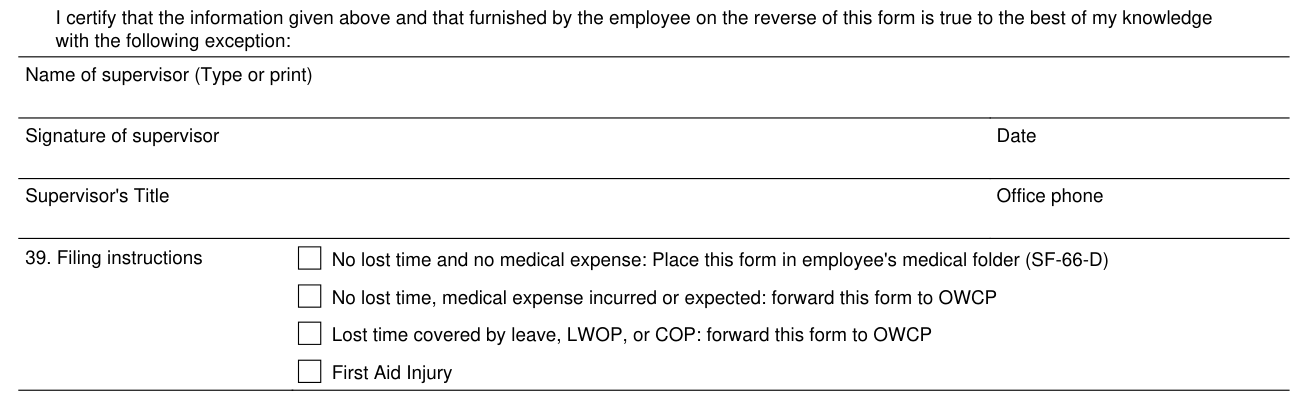
Box 38: a supervisor who knowingly certifies to any false statement, misrepresentation concealment of fact, etc. in respect of this claim may also be subject to appropriate felony criminal prosecution. By signing Box 38, you certify that the information given on this form and that furnished by the employee on the reverse of this form is true to the best of your knowledge with the following exception:
Enter the Name of supervisor (Type or print), the Signature of supervisor and Date, and the Supervisor's Title and Office phone.
In addition to completing Items 17 through 39, the supervisor is responsible for obtaining the witness statement in Item 16 and for filling in the proper codes in shaded boxes a, b, and con the front of the form.
Box 39, Filing instructions: No lost time and no medical expense: Place this form in employee's medical folder (SF-66-D). No lost time, medical expense incurred or expected: forward this form to OWCP. Lost time covered by leave, LWOP, or COP: forward this form to OWCP. First Aid Injury.
As the time the form is received, complete the receipt of notice of injury and give it to the employee.
If medical expense or lost time is incurred or expected, the completed form should be sent to OWCP within 10 working days after is received.
More rules for Form CA-1
Instructions for Completing Form CA-1 Complete all items on your section of the form. If additional space is required to explain or clarify any point, attach a supplemental statement to the form.
Common questions about Form CA-1
What is form CA-1?
Form CA-1 is the Federal Employee's Notice of Traumatic Injury and Claim for Continuation of Pay/Compensation, from the U.S. Department of Labor Office of Workers' Compensation Programs. The FECA, which is administered by the Office of Workers' Compensation Programs (OWCP), provides benefits for job-related traumatic injuries.
Sources
[1] Form CA-1 (Revised October 2018), Federal Employee's Notice of Traumatic Injury and Claim for Continuation of Pay/Compensation, U.S. Department of Labor Office of Workers' Compensation Programs (the Official source link on this page).
