
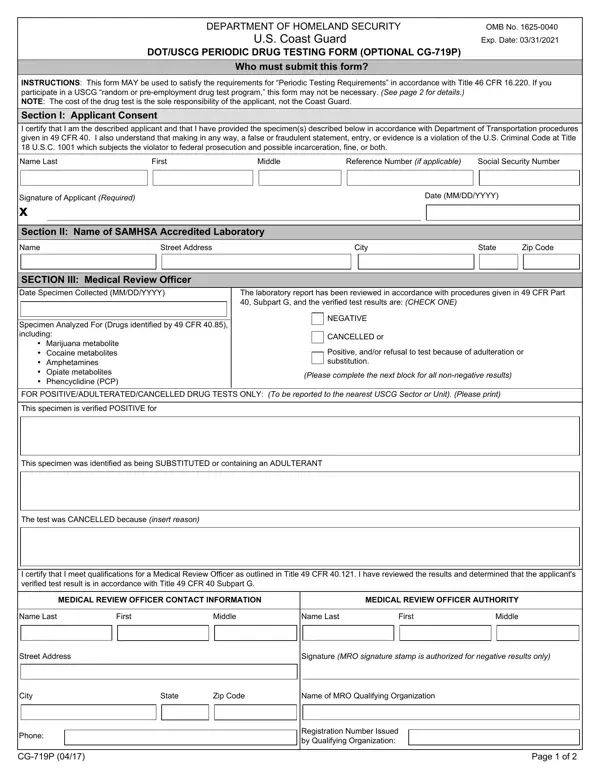

Form CG-719P at a glance
What it is: The DOT/USCG Periodic Drug Testing Form (Optional CG-719P) of the U.S. Coast Guard, Department of Homeland Security.
Who signs: Sign on Signature of Applicant (Required). The drug test result must be signed and dated by the MRO.
A drug test is required for all transactions EXCEPT endorsements, documents of continuity, duplicates, and STCW certificates.
Only a chemical test meeting the requirements of 49 CFR Part 40 will be accepted.
10.301 Purpose: The information is collected by the Coast Guard to determine whether an applicant meets the regulatory standards for issuance of a U.S. Merchant Mariner Credential (MMC).
A filled-in Form CG-719P example: a mariner reports a negative drug test
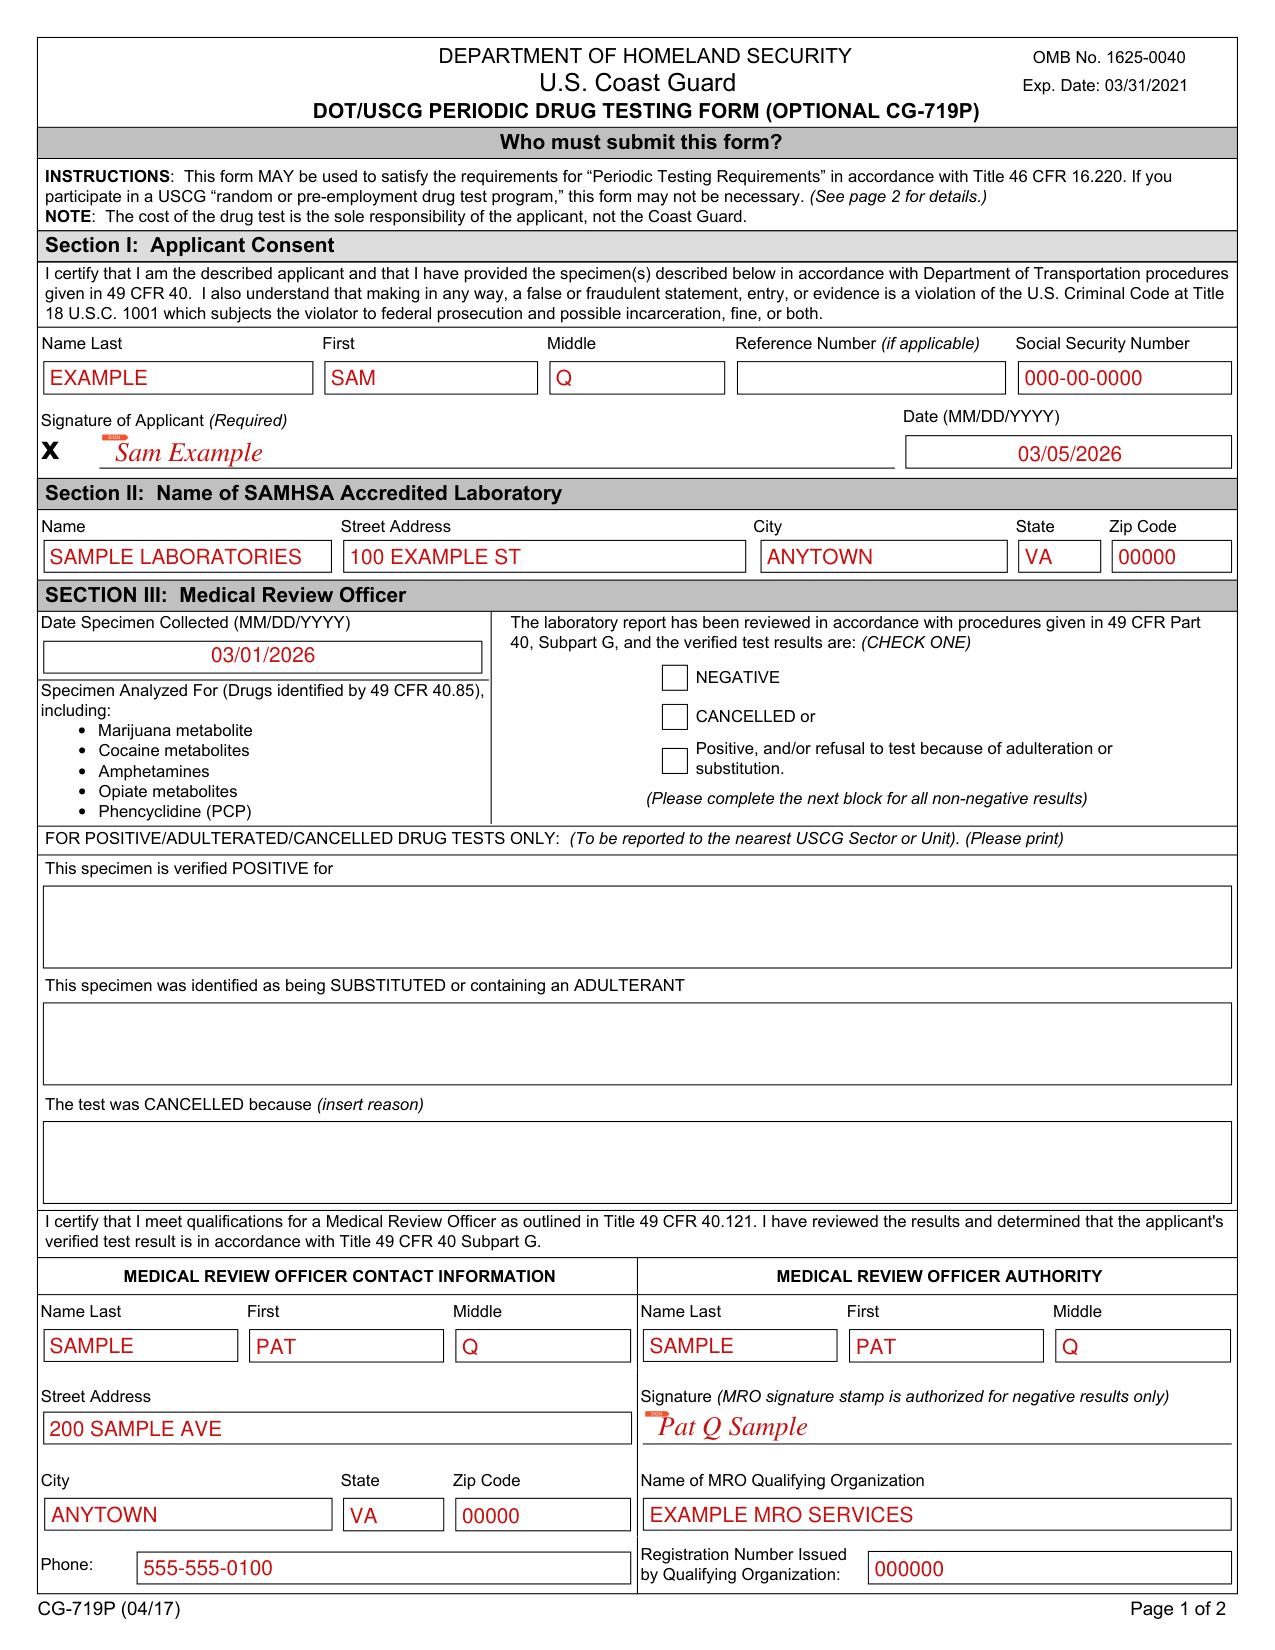
How to fill out Form CG-719P, box by box
Section I: Applicant Consent
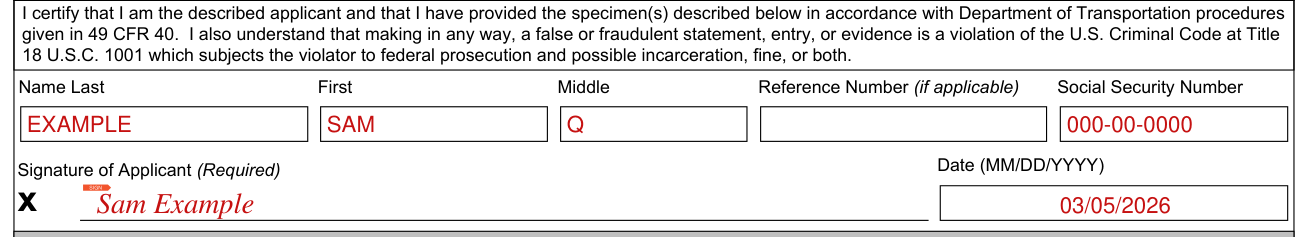
Enter your Name (Last, First, Middle), Reference Number (if applicable) and Social Security Number.
Section I: Applicant Consent: I certify that I am the described applicant and that I have provided the specimen(s) in accordance with Department of Transportation procedures given in 49 CFR 40. I also understand that making in any way, a false or fraudulent statement, entry, or evidence is a violation of the U.S. Criminal Code at Title 18 U.S.C. 1001 which subjects the violator to federal prosecution and possible incarceration, fine, or both.
Enter the Date (MM/DD/YYYY).
Furnishing this information (including your SSN) is voluntary; however, failure to furnish the requested information may result in the non-issuance of the MMC, any endorsement within the MMC, and medical certificate.
Section II: Name of SAMHSA Accredited Laboratory

It is CRITICAL that the sample is sent to an accredited SAMHSA laboratory for ANALYSIS or the drug test is invalid.
Under Section II, enter the Name, Street Address, City, State and Zip Code of the SAMHSA Accredited Laboratory.
Section III: Medical Review Officer, Date Specimen Collected and the verified test results

Enter the Date Specimen Collected (MM/DD/YYYY).
Medical Review Officer: check one: the laboratory report has been reviewed in accordance with procedures given in 49 CFR Part 40, Subpart G, and the verified test results are NEGATIVE, CANCELLED or Positive, and/or refusal to test because of adulteration or substitution.
Specimen Analyzed For (Drugs identified by 49 CFR 40.85), including: Marijuana metabolite, Cocaine metabolites, Amphetamines, Opiate metabolites, Phencyclidine (PCP).
FOR POSITIVE/ADULTERATED/CANCELLED DRUG TESTS ONLY
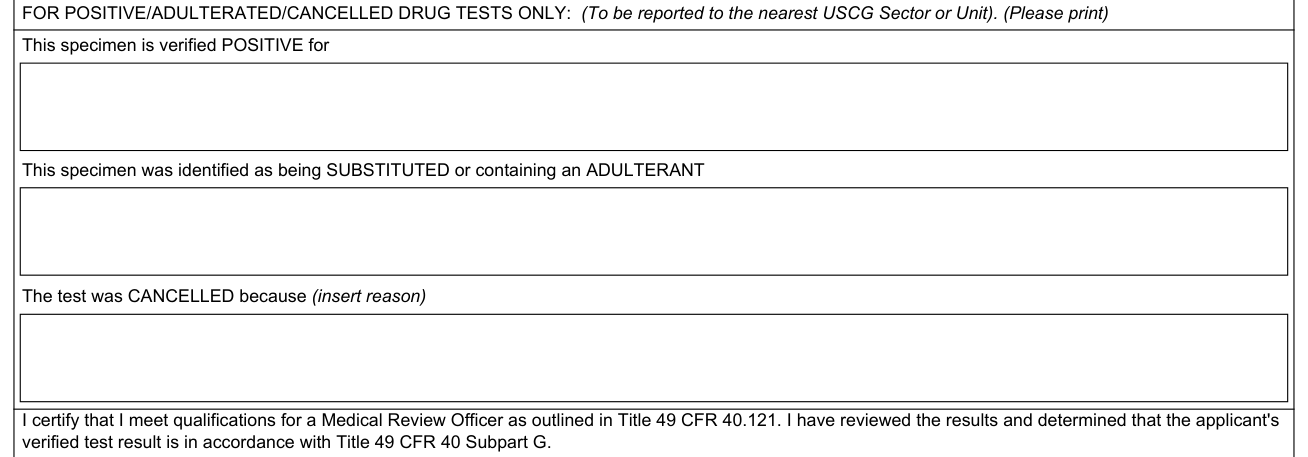
Complete this block for all non-negative results: FOR POSITIVE/ADULTERATED/CANCELLED DRUG TESTS ONLY (To be reported to the nearest USCG Sector or Unit). Please print.
Fill in This specimen is verified POSITIVE for.
Fill in This specimen was identified as being SUBSTITUTED or containing an ADULTERANT.
Fill in The test was CANCELLED because (insert reason).
Medical Review Officer Contact Information
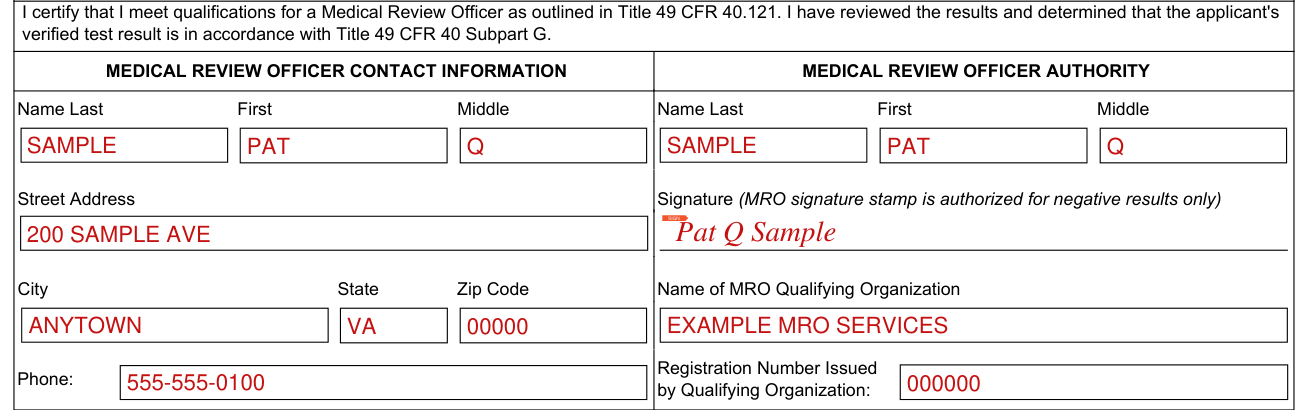
Under MEDICAL REVIEW OFFICER CONTACT INFORMATION, enter the Name (Last, First, Middle), Street Address, City, State, Zip Code and Phone.
Medical Review Officer Authority
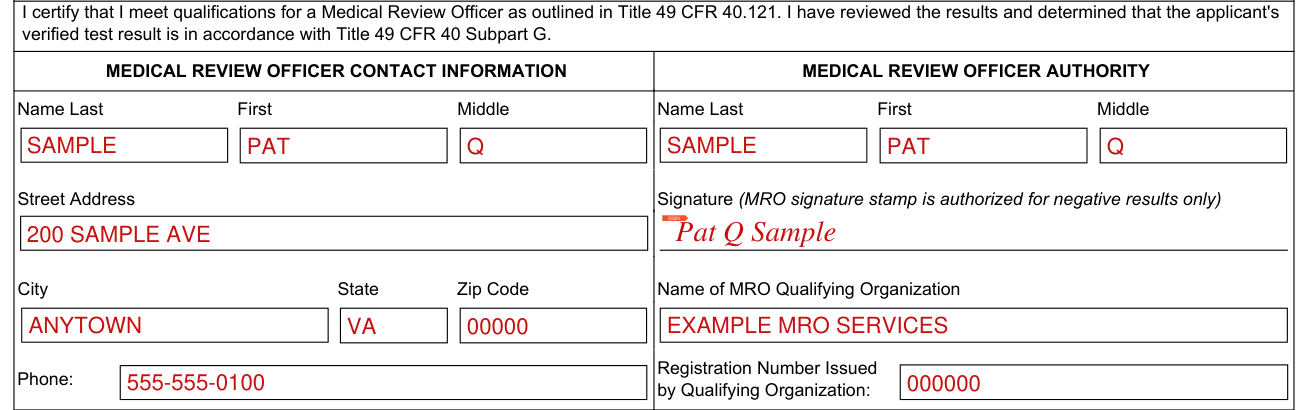
Sign to certify: I certify that I meet qualifications for a Medical Review Officer as outlined in Title 49 CFR 40.121. I have reviewed the results and determined that the applicant's verified test result is in accordance with Title 49 CFR 40 Subpart G.
Sign on Signature (MRO signature stamp is authorized for negative results only).
Under MEDICAL REVIEW OFFICER AUTHORITY, enter the Name (Last, First, Middle), the Name of MRO Qualifying Organization and the Registration Number Issued by Qualifying Organization.
Options for the drug test
OPTION I PERIODIC TESTING PROGRAM
A DOT Chemical test conducted within the past 185 days by a laboratory accredited by Substance Abuse and Mental Health Services Administration (SAMHSA), Department of Health and Human Services.
COLLECTION of a sample may be conducted by an independent medical facility, private physician or at an employer-designated site as long as the collection agent meets the qualification requirements to be a collection agent given in Title 49 CFR Part 40 Subpart C.
The ORIGINAL results are required. A FACSIMILE is acceptable, if it is originated from the Medical Review Officer (MRO) or the Service Agent assisting the mariner, and sent directly from the office.
OPTION II RANDOM TESTING
EXAMPLE (From Mariner Employers): APPLICANT'S NAME/SSN has been subject to a random testing program meeting the criteria of Title 46 CFR 16.230 for at least 60 days during the previous 185 days and has not failed nor refused to participate in a chemical test for dangerous drugs.
EXAMPLE (Active Duty Military/Military Sealift Command/N.O.A.A./Army Corps of Engineers): APPLICANT'S NAME/SSN has been subject to a random testing program with no subsequent positive drug test results during the remainder of the six month period.
OPTION III PRE-EMPLOYMENT TESTING
An ORIGINAL DATED letter on mariner employer stationary signed by a company official, stating that they hold evidence that mariner either passed a chemical test for dangerous drugs within the past 185 days or has been subject to a random testing program.
EXAMPLE: APPLICANT'S NAME/SSN passed a chemical test for dangerous drugs, required under Title 46 CFR 16.210 within the previous six months of the date of this letter with no subsequent positive drug test results during the remainder of the six month period.
Common questions about Form CG-719P
When is this form not the right one?
This form MAY be used to satisfy the requirements for Periodic Testing Requirements in accordance with Title 46 CFR 16.220. If you participate in a USCG random or pre-employment drug test program, this form may not be necessary. (See page 2 for details.) NOTE: The cost of the drug test is the sole responsibility of the applicant, not the Coast Guard.
Sources
[1] Form CG-719P (04/17), DOT/USCG Periodic Drug Testing Form, U.S. Coast Guard (the Official source link on this page).