

Change of Beneficiary Request Form at a glance
What it is: The Change of Beneficiary Request Form is a Beneficiary change request.
Where and when to file: For standard mail delivery: The Hartford Individual Life Division PO Box 64582 St. Paul, MN 55164-0582.
Beneficiary change requests can only be made during the lifetime of the insured. Upon the Insurer's receipt of this completed form, the Beneficiary change will be effective as of the date it was signed by the Policyowner and whether or not the Insured is living when the Insurer receives it. However, the change will be subject to any payment that the Insurer may have made or actions it may have taken prior to receipt of the completed form.
A filled-in Change of Beneficiary Request Form example: one Primary beneficiary at 100 percent
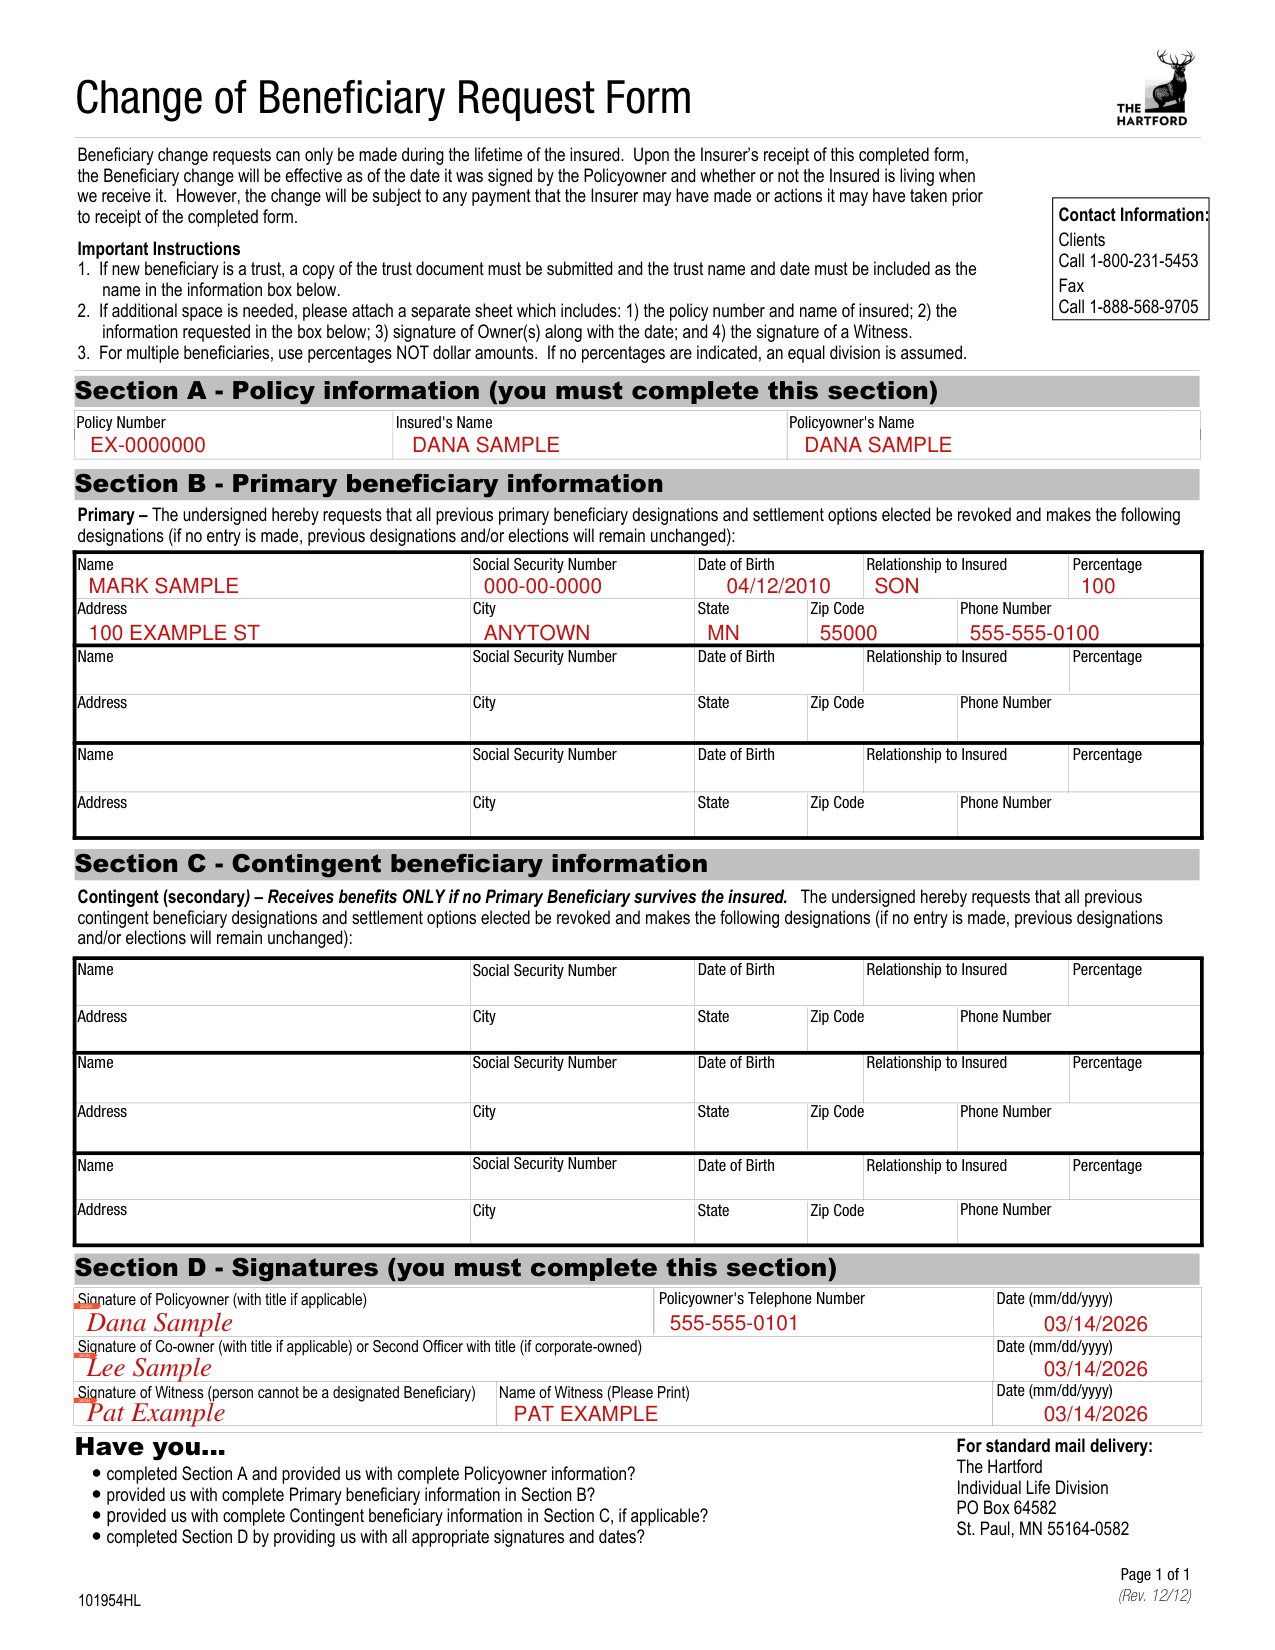
How to fill out Change of Beneficiary Request Form, box by box
Section A Policy information

In Section A, you must complete the Policy Number, the Insured's Name and the Policyowner's Name.
Section B Primary beneficiary information
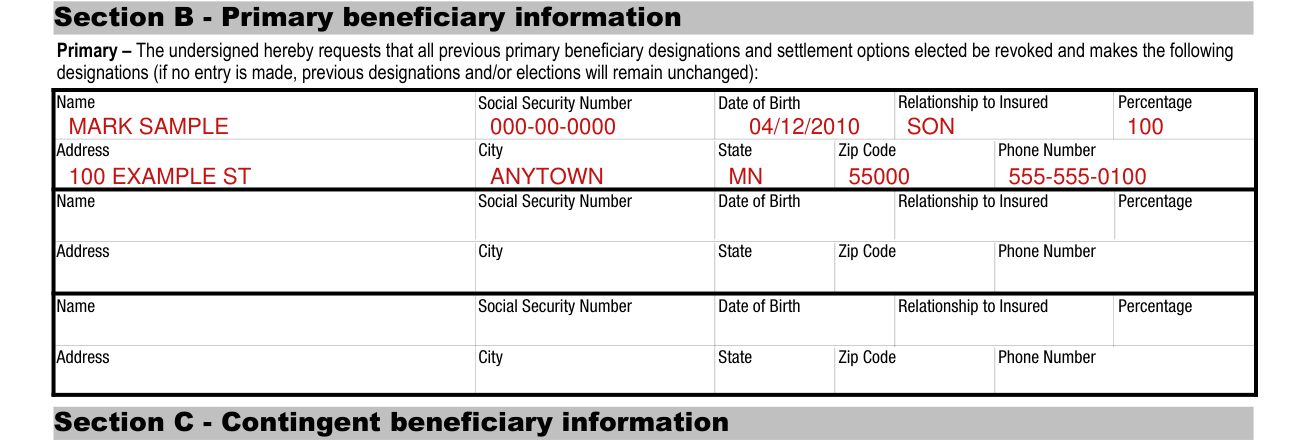
In Section B, the undersigned hereby requests that all previous primary beneficiary designations and settlement options elected be revoked and makes the following designations (if no entry is made, previous designations and/or elections will remain unchanged).
For each Primary beneficiary, enter the Name, Date of Birth, Relationship to Insured, Percentage, Social Security Number, Address, Phone Number, Zip Code, City and State.
Section C Contingent beneficiary information
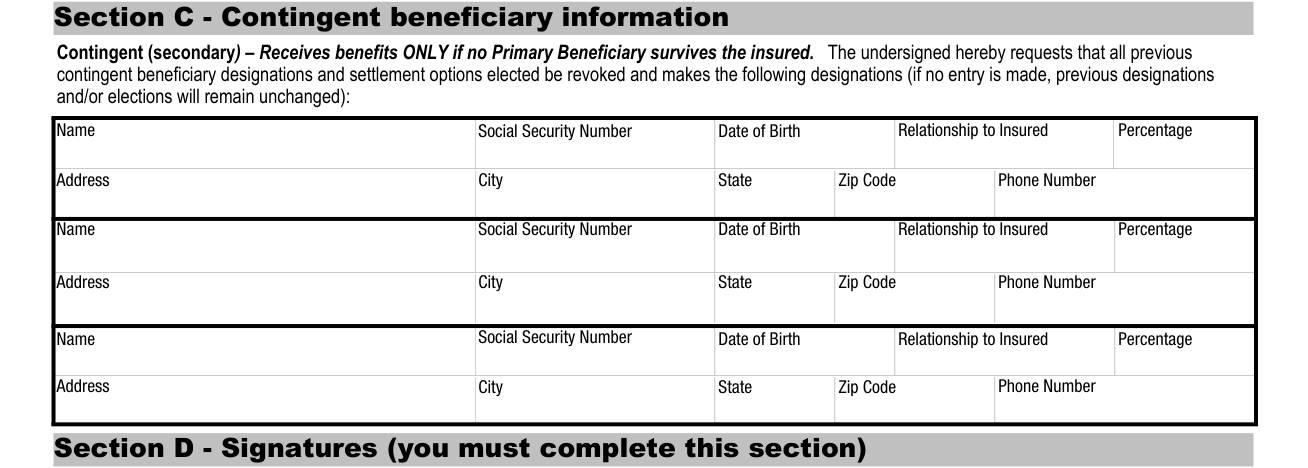
In Section C, Contingent (secondary) beneficiaries receive benefits ONLY if no Primary Beneficiary survives the insured.
In Section C, the undersigned hereby requests that all previous contingent beneficiary designations and settlement options elected be revoked and makes the following designations (if no entry is made, previous designations and/or elections will remain unchanged).
For each Contingent beneficiary, enter the Name, Date of Birth, Relationship to Insured, Percentage, Social Security Number, Address, Phone Number, Zip Code, City and State.
Section D Signatures

In Section D, you must complete the Signature of Policyowner (with title if applicable), the Date (mm/dd/yyyy) and the Policyowner's Telephone Number.
Add the Signature of Co-owner (with title if applicable) or Second Officer with title (if corporate-owned) and the Date (mm/dd/yyyy).
The Signature of Witness (person cannot be a designated Beneficiary), the Name of Witness (Please Print) and the Date (mm/dd/yyyy) go on the Witness lines.
More rules for Change of Beneficiary Request Form
Important Instructions 1. If new beneficiary is a trust, a copy of the trust document must be submitted and the trust name and date must be included as the name in the information box. 2. If additional space is needed, please attach a separate sheet which includes: 1) the policy number and name of insured; 2) the information requested in the box; 3) signature of Owner(s) along with the date; and 4) the signature of a Witness. 3. For multiple beneficiaries, use percentages NOT dollar amounts. If no percentages are indicated, an equal division is assumed.
Have you completed Section A and provided complete Policyowner information? Have you provided complete Primary beneficiary information in Section B? Have you provided complete Contingent beneficiary information in Section C, if applicable? Have you completed Section D by providing all appropriate signatures and dates?
Contact Information: Clients Call 1-800-231-5453 Fax Call 1-888-568-9705.
Common questions about Change of Beneficiary Request Form
Where do I file it?
For standard mail delivery: The Hartford Individual Life Division PO Box 64582 St. Paul, MN 55164-0582.
Sources
[1] Change of Beneficiary Request Form (Rev. 12/12), The Hartford Individual Life Division (the Official source link on this page).
