Cvs Prior Auth Form PDF Details

In navigating the complexities of obtaining medication through insurance, the CVS Caremark Prior Authorization form emerges as a critical document, a gatekeeper of sorts between patients and the prescription drugs they may require. It sets in motion a review process that involves filling out and faxing a request to Caremark, a step that, while seemingly straightforward, is layered with the potential for delays should any information be missing or presented imprecisely. Caremark’s response, involving a detailed Drug Specific Prior Authorization Request Form that demands exact patient information and clear responses to specified questions, underscores the importance of meticulous attention to detail in this process. Such diligence is not merely administrative. The outcome of this review not only affects the timely access to necessary medications but also determines whether individuals face barriers in their treatment paths based on the specifics of their insurance coverage. Notably, the form operates within a context of confidentiality and privacy, as emphasized by the initial notice, protecting sensitive patient data while traversing the procedural steps required for authorization. The denial of a request carries significant repercussions, including informing both patient and prescriber of the reasons for rejection, thereby inserting an additional layer of communication and potential appeal into the healthcare journey. This form, in essence, encapsulates a pivotal intersection of healthcare provision, insurance protocols, and patient rights, all governed by the imperative of safeguarding personal health information.

QuestionAnswer
Form NameCvs Prior Auth Form
Form Length1 pages
Fillable?No
Fillable fields0
Avg. time to fill out15 sec
Other namescvs caremark forms, cvs caremark pa form, caremark prior authorization form pdf, cvs prior authorization

How to Fill Out Caremark Prior Authorization Form Request

Caremark Prior Authorization Form Request at a glance

What it is: Caremark Prior Authorization Form Request to request a Drug Specific Prior Authorization Form.

Where and when to file: Please complete and fax this form to Caremark at 888-836-0730 to request a Drug Specific Prior Authorization Form.

A filled-in Caremark Prior Authorization Form Request example: a prescriber's office requests a prior authorization form

Caremark Prior Authorization Form Request example filled out, example: a prescriber's office requests a prior authorization form
Dr. Ann Sample's office fills out the Caremark form. It asks Caremark to send a Drug Specific Prior Authorization Form for one patient's drug. The picture shows page 1 filled in, and none of its entries is real.

How to fill out Caremark Prior Authorization Form Request, box by box

Section I: patient information
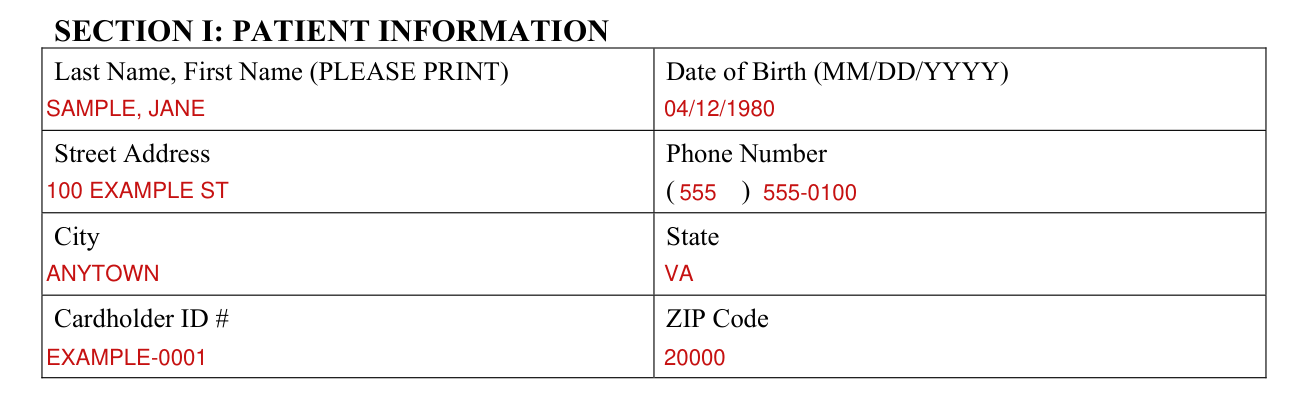
Caremark Prior Authorization Form Request example filled out, section I: patient information

Under SECTION I: PATIENT INFORMATION, enter the Last Name, First Name (PLEASE PRINT) and Date of Birth (MM/DD/YYYY).

Enter the Street Address and Phone Number.

Enter the City and State.

Enter the Cardholder ID # and ZIP Code.

Section II: drug information

Caremark Prior Authorization Form Request example filled out, section II: drug information

Under SECTION II: DRUG INFORMATION, enter the Drug Name (PLEASE PRINT) and the Drug Strength.

Section III: prescriber information

Caremark Prior Authorization Form Request example filled out, section III: prescriber information

Under SECTION III: PRESCRIBER INFORMATION, enter the Prescriber's Name (PLEASE PRINT).

Enter the Prescriber's Address (Street, City, State, ZIP code).

Enter the Prescriber's Phone Number and the Prescriber's Fax Number.

More rules for Caremark Prior Authorization Form Request

Once Caremark receives your request, it will fax you a Drug Specific Prior Authorization Request Form along with the patient's specific information and questions that must be answered.

When you fax the Drug Specific Prior Authorization Request Form to Caremark, it will review it and notify you and the patient of the result.

Incomplete or illegible forms and missing fields will delay the processing of your request. Please complete all fields to ensure appropriate processing.

Common questions about Caremark Prior Authorization Form Request

Where do I file it?

Please complete and fax this form to Caremark at 888-836-0730 to request a Drug Specific Prior Authorization Form.

Sources

[1] Caremark Prior Authorization Form Request (CVS Caremark) (the Official source link on this page).

Please rate Cvs Prior Auth Form

1 Votes
If you believe this page is infringing on your copyright, please familiarize yourself with and follow our DMCA notice and takedown process - click here to proceed .