
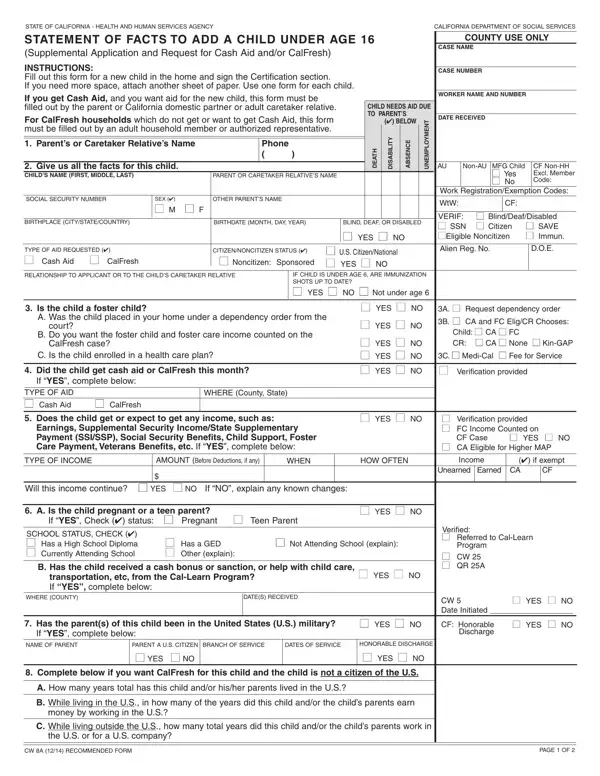

Form CW 8A at a glance
What it is: CW 8A is the California Department of Social Services Statement of Facts to Add a Child Under Age 16, a Supplemental Application and Request for Cash Aid and/or CalFresh.
Who signs: Who must sign this form: For Cash Aid, you and your aided spouse, Registered Domestic Partner, or the other parent (of cash aided children), if living in the home. For CalFresh, an adult household member or authorized representative.
If you get Cash Aid, and you want aid for the new child, this form must be filled out by the parent or California domestic partner or adult caretaker relative.
For CalFresh households which do not get or want to get Cash Aid, this form must be filled out by an adult household member or authorized representative.
A filled-in Form CW 8A example: a parent adds a son to a Cash Aid and CalFresh case
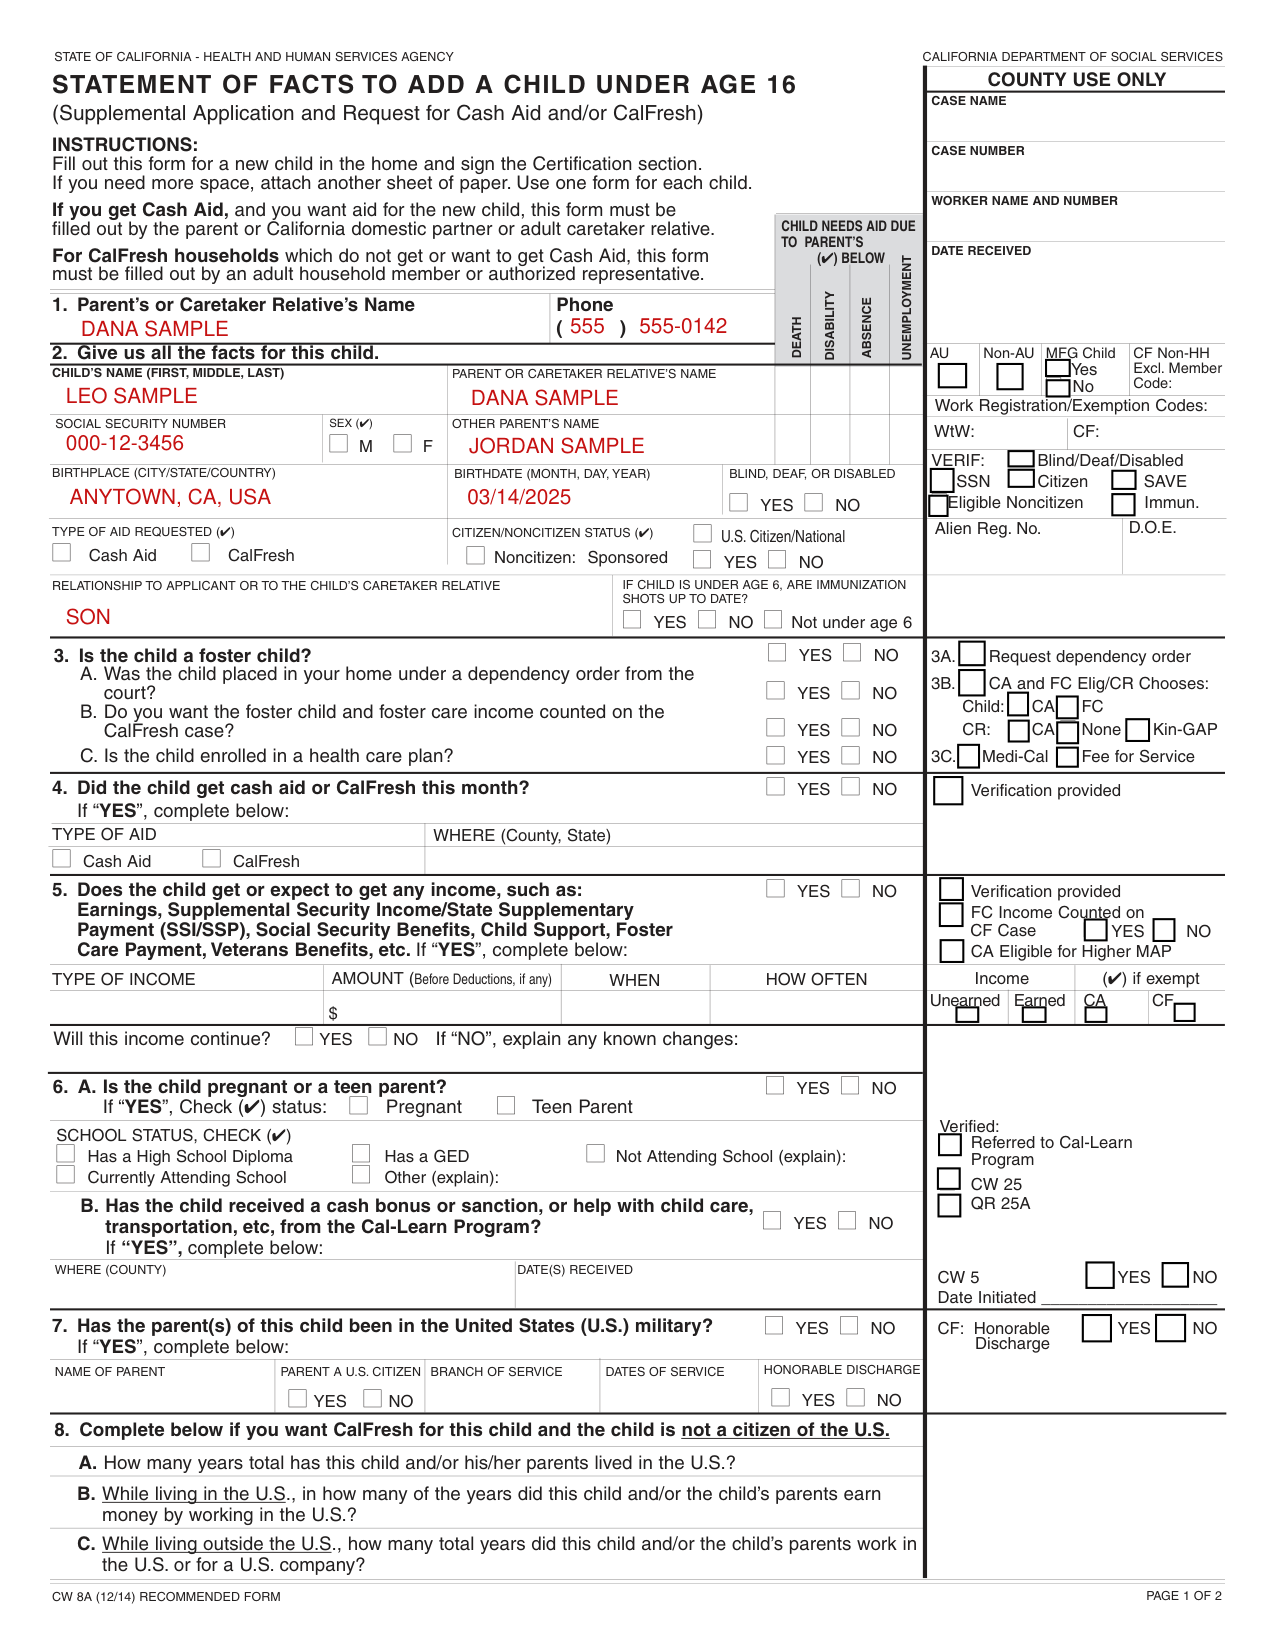
How to fill out Form CW 8A, box by box
1. Parent's or Caretaker Relative's Name

In box 1, write the Parent's or Caretaker Relative's Name and the Phone.
2. Give us all the facts for this child
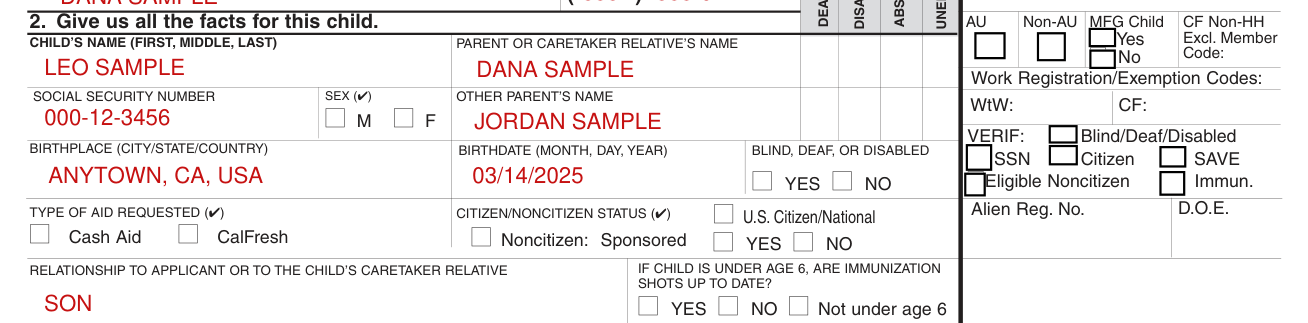
Give all the facts for this child: Child's Name (First, Middle, Last), Social Security Number, Birthplace (City/State/Country), Birthdate (Month, Day, Year), Parent or Caretaker Relative's Name, Other Parent's Name and Relationship to Applicant or to the Child's Caretaker Relative.
Mark Sex, M or F, and Blind, Deaf, or Disabled, YES or NO.
Under Type of Aid Requested, mark Cash Aid, CalFresh, or both.
Under Citizen/Noncitizen Status, mark U.S. Citizen/National or Noncitizen: Sponsored, with YES or NO.
If child is under age 6, are immunization shots up to date? Mark YES or NO, or Not under age 6.
3. Is the child a foster child?

Is the child a foster child? A. Was the child placed in your home under a dependency order from the court? B. Do you want the foster child and foster care income counted on the CalFresh case? C. Is the child enrolled in a health care plan?
4. Did the child get cash aid or CalFresh this month?

Did the child get cash aid or CalFresh this month? If “YES”, complete Type of Aid and Where (County, State).
5. Does the child get or expect to get any income
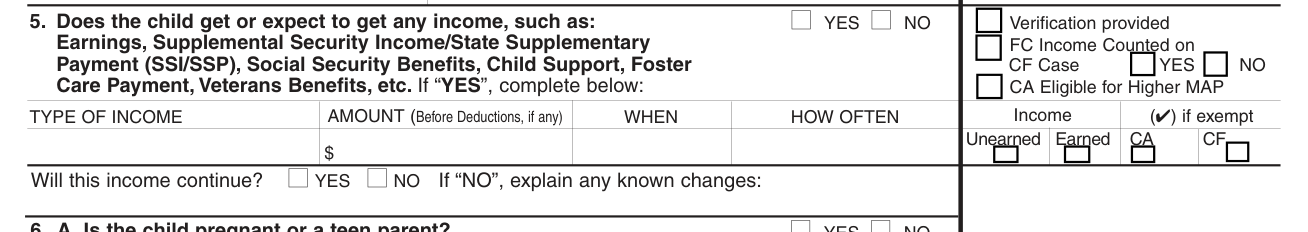
Does the child get or expect to get any income, such as: Earnings, Supplemental Security Income/State Supplementary Payment (SSI/SSP), Social Security Benefits, Child Support, Foster Care Payment, Veterans Benefits, etc. If “YES”, complete Type of Income, Amount (Before Deductions, if any) and When.
Will this income continue? If “NO”, explain any known changes.
6. A. Is the child pregnant or a teen parent?
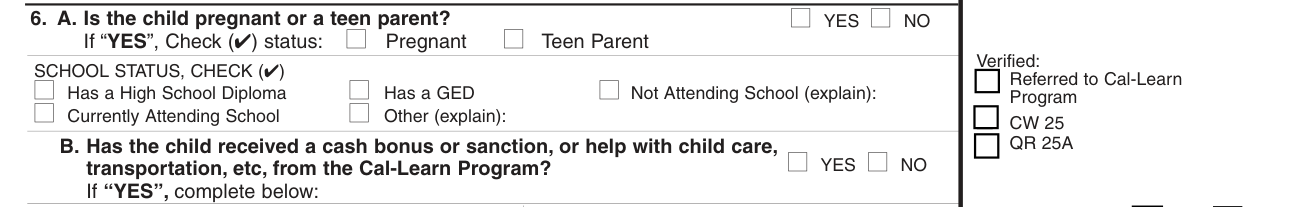
Is the child pregnant or a teen parent? If “YES”, check status: Pregnant or Teen Parent. School Status, check: Has a High School Diploma, Has a GED, Not Attending School (explain), Currently Attending School or Other (explain).
B. Has the child received a cash bonus or sanction

Has the child received a cash bonus or sanction, or help with child care, transportation, etc, from the Cal-Learn Program? If “YES”, complete Where (County) and Date(s) Received.
7. Has the parent(s) of this child been in the United States (U.S.) military?

Has the parent(s) of this child been in the United States (U.S.) military? If “YES”, complete Name of Parent, Parent a U.S. Citizen, Branch of Service, Dates of Service and Honorable Discharge.
8. Complete below if you want CalFresh for this child

Complete if you want CalFresh for this child and the child is not a citizen of the U.S.
9. Does the child own any property or have resources

Does the child own any property or have resources, such as: cash, land, bank accounts, trust funds, savings bonds, Native American per capita payments or trust funds, or other items? If “YES”, complete Type of Resource, Account/Policy Number, Name, Address of Bank, etc. and Current Value.
10. Does the child have Medicare or health insurance

Does the child have Medicare or health insurance, such as Blue Cross, Kaiser, CHAMPUS, etc., which is paid for by a parent or parent's employer? If “YES”, list insurance coverage.
11. If the child has been charged as an adult with a felony

If the child has been charged as an adult with a felony, is the child hiding or running from the law to avoid prosecution, being taken into custody, or going to jail for that felony crime or attempted felony crime?
12. Has the child been found by a court of law to be in violation of probation or parole?

Has the child been found by a court of law to be in violation of probation or parole?
13. CHDP services

Mark YES or NO: Do you want more facts about CHDP services? Do you want free CHDP medical or dental services? Do you need help making appointments or getting to the doctor or dentist?
Mark YES or NO: B. Do you want more facts about immunization services? C. Do you want facts about non-discrimination, alcohol/drug counseling, past medical expenses, and other special needs? D. Does anyone who is pregnant need to find a doctor, get medical transportation, and/or other help?
Mark YES or NO: E. Is anyone breastfeeding a child? If “YES”, was the birth within the last 12 months? F. Do you want to get facts or services from a Family Planning Clinic to help you plan your family size and prevent unplanned pregnancies?
Certification and signature

I understand that: if I give wrong facts or fail to report all facts or situations on purpose that affect my eligibility and aid payments, I may be fined, jailed/imprisoned, or both. I can be fined up to $10,000 for cash aid and $250,000 for CalFresh (checked November 1, 2026).
I can be sent to jail/prison for up to 3 years for cash aid and 20 years for CalFresh.
And benefits for cash aid and CalFresh can be stopped for 6 months, 12 months, 2 years, 4 years, 5 years, 10 years, 20 years or forever; and for Refugee Cash Assistance, 3 months and 6 months.
"I declare under penalty of perjury under the laws of the United States of America and the State of California that the information contained on this Statement of Facts is true, correct, and complete."
Signature of Witness to Mark, Interpreter, or Other Person Completing Form, and Date.
More rules for Form CW 8A
Fill out this form for a new child in the home and sign the Certification section.
Use one form for each child.
If you need more space, attach another sheet of paper.
Sources
[1] Form CW 8A (12/14), Statement of Facts to Add a Child Under Age 16, California Department of Social Services (the Official source link on this page).