

Form DCSS 0054 at a glance
What it is: Health Insurance Information, DCSS 0054 (04/27/05), of the State of California-Health and Human Services Agency, Department of Child Support Services.
Where and when to file: Within 40 business days, the employer must furnish the Local Child Support Agency a description of the coverage available, along with any forms required to activate coverage or claim benefits. This information should be submitted on the Health Insurance Information (DCSS 0054) form which will be included in the NMSN packet.[2]
Please complete SECTION I if health insurance is provided or available by the Noncustodial Parent or employer. SECTION II is about the other parent's insurance. Employers complete Sections I and III only. Please sign and date the completed form.
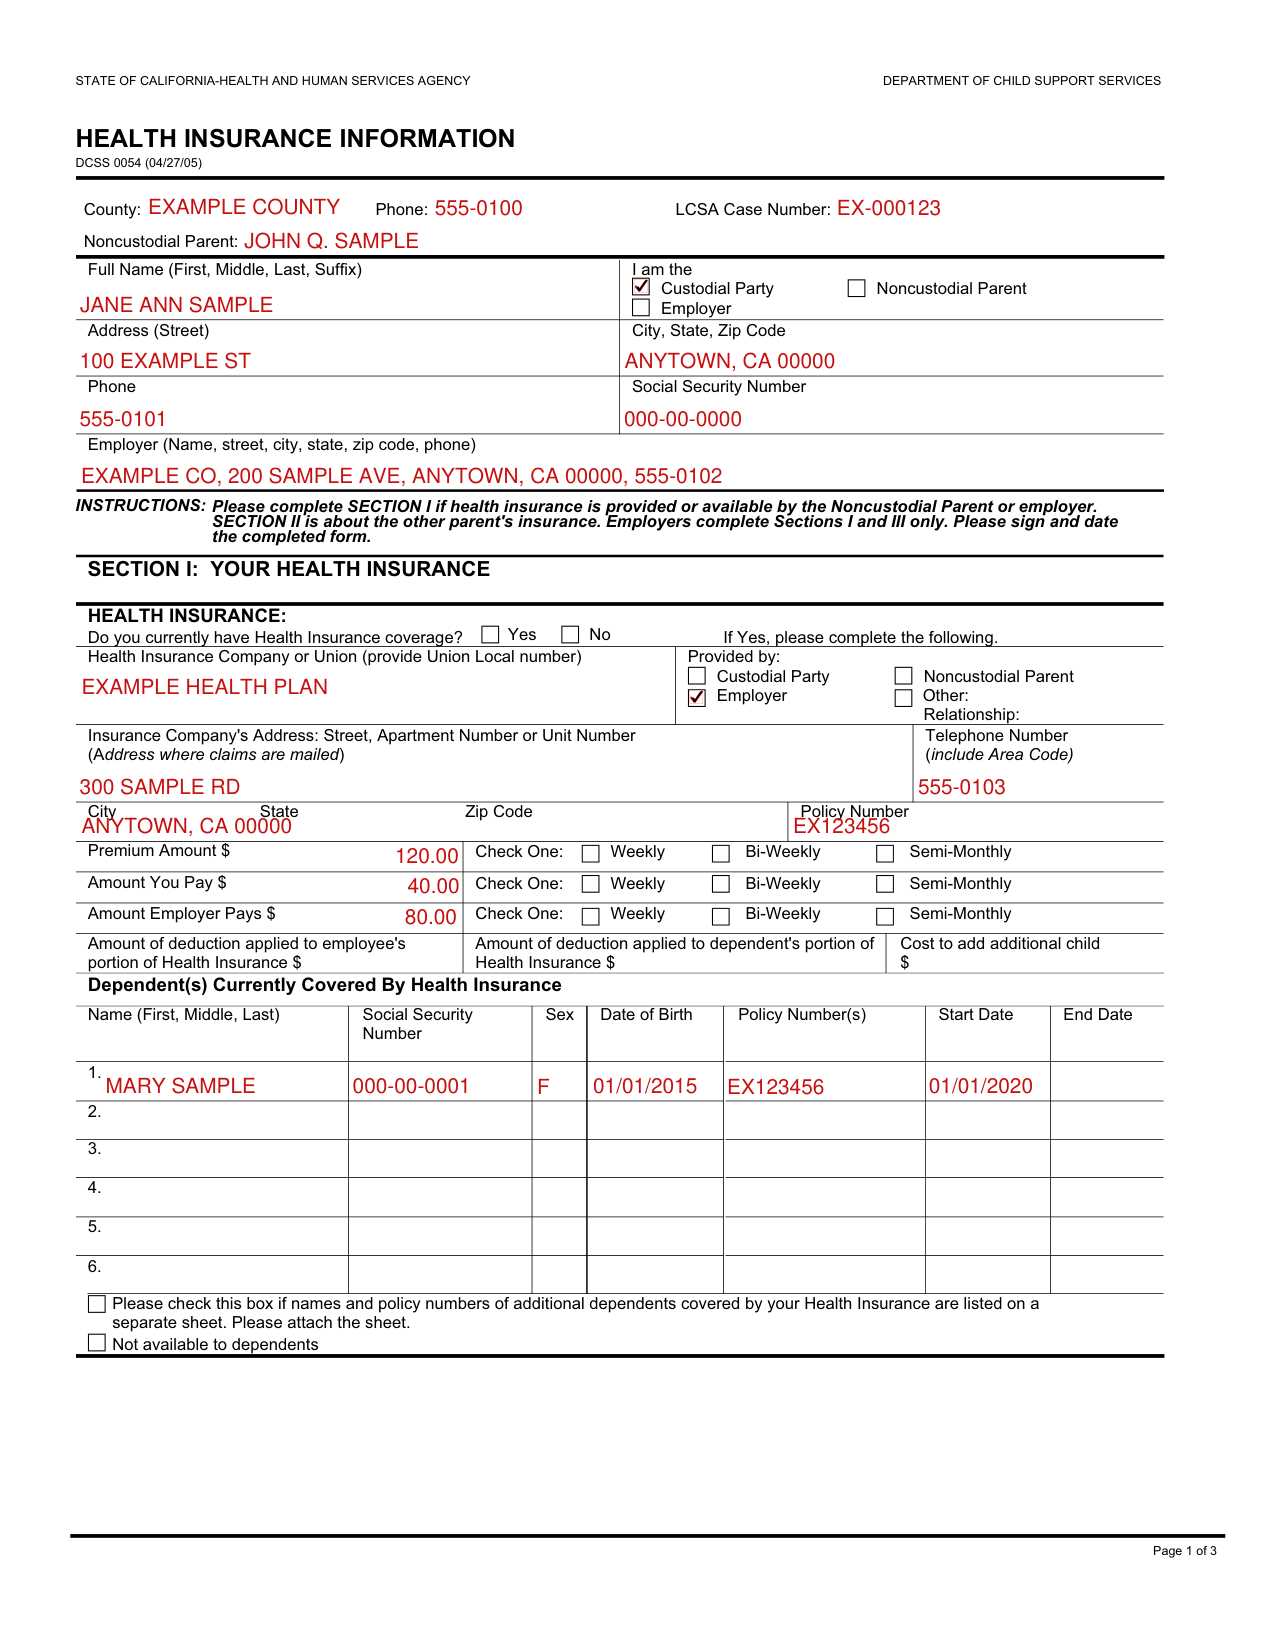
A filled-in Form DCSS 0054 example: a custodial party lists employer coverage
How to fill out Form DCSS 0054, box by box
County, Phone, LCSA Case Number and Noncustodial Parent
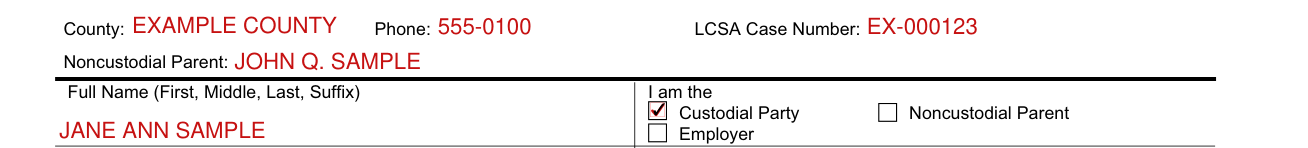
Enter the County, the Phone, the LCSA Case Number and the Noncustodial Parent.
I am the

After I am the, check Custodial Party, Employer or Noncustodial Parent.
Full Name, Address, Phone, Social Security Number and Employer

Enter the Full Name (First, Middle, Last, Suffix), the Address (Street), the City, State, Zip Code, the Phone, the Social Security Number and the Employer (Name, street, city, state, zip code, phone).
Social Security Number information is mandatory and will be kept on file at the local child support agency to locate and identify individuals and assets for the purpose of establishing, modifying, and enforcing child support obligations.
Enrolling a child in health insurance may require the release of the child's Social Security Number and mailing address to the other parent's employer or the release of the child's Social Security Number to the other parent.
Section I: Health Insurance Company or Union

Do you currently have Health Insurance coverage? Yes No. If Yes, please complete the following: Health Insurance Company or Union (provide Union Local number).
Enter the Insurance Company's Address: Street, Apartment Number or Unit Number (Address where claims are mailed), the Telephone Number (include Area Code), the City, State, Zip Code and the Policy Number.
Provided by

Check Provided by: Custodial Party, Employer, Noncustodial Parent or Other, and for Other enter the Relationship.
Premium Amount, Amount You Pay and Amount Employer Pays

Enter the Premium Amount $, the Amount You Pay $ and the Amount Employer Pays $, and for each Check One: Weekly, Bi-Weekly or Semi-Monthly.
Enter the Amount of deduction applied to employee's portion of Health Insurance $, the Amount of deduction applied to dependent's portion of Health Insurance $ and the Cost to add additional child $.
Dependent(s) Currently Covered By Health Insurance
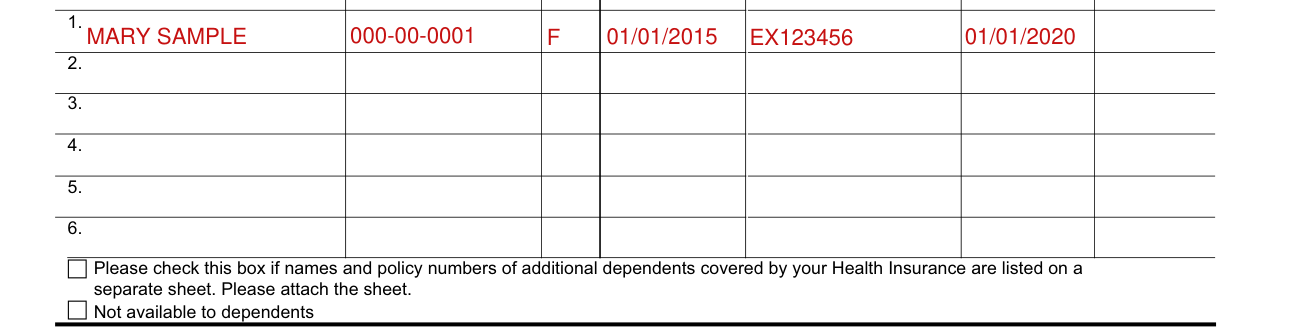
Under Dependent(s) Currently Covered By Health Insurance, enter for each dependent the Name (First, Middle, Last), Social Security Number, Sex, Date of Birth, Policy Number(s), Start Date and End Date.
Please check this box if names and policy numbers of additional dependents covered by your Health Insurance are listed on a separate sheet. Please attach the sheet. "Not available to dependents" is a check box of its own.
The Policy covers the following

Check all that apply for what the Policy covers: Doctor Visits, Medicare Supplemental, Specific Illness, Prescription Drugs, Long Term Care, Hospital Stays, Hospital Outpatient (i.e., lab work, physical therapy) or Other (Specify).
Dental Insurance and Vision Insurance
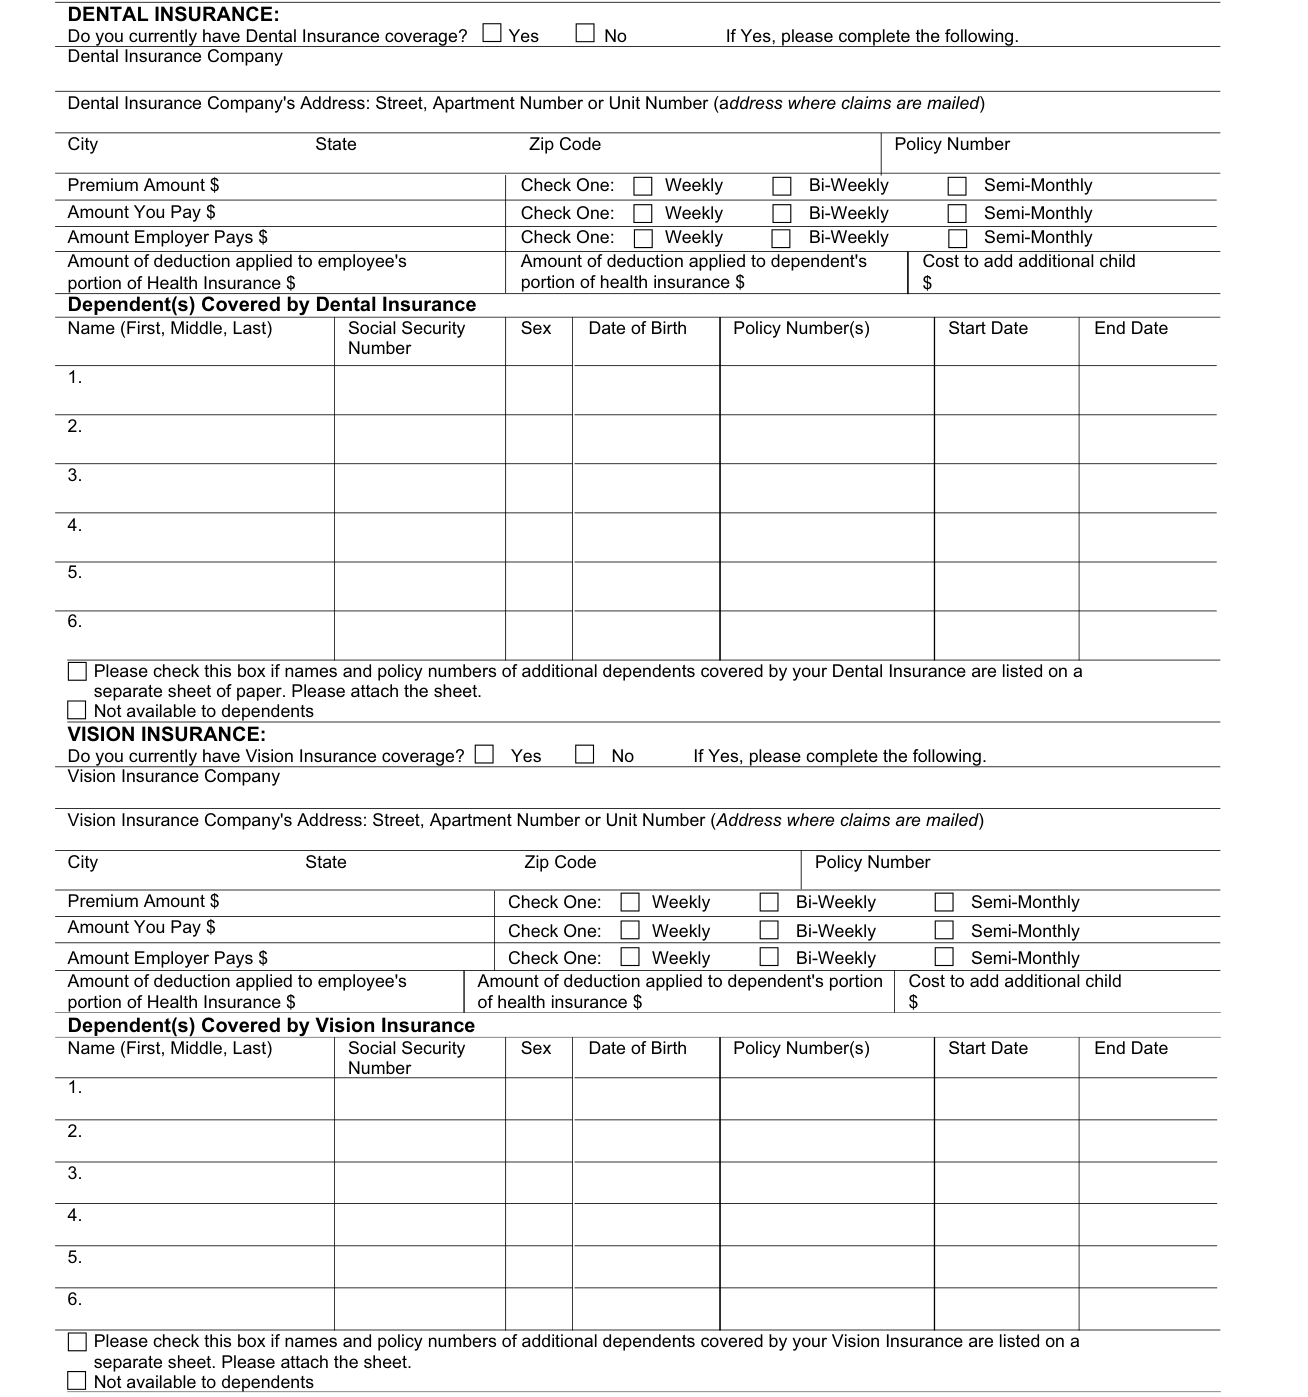
Do you currently have Dental Insurance coverage? Yes No. If Yes, please complete the following: Dental Insurance Company, its Address: Street, Apartment Number or Unit Number (address where claims are mailed), the City, State, Zip Code and the Policy Number.
"Not available to dependents" is its own check box. Do you currently have Vision Insurance coverage? Yes No. If Yes, please complete the following: Vision Insurance Company, its Address: Street, Apartment Number or Unit Number (Address where claims are mailed), the City, State, Zip Code and the Policy Number.
For Dental Insurance and Vision Insurance each, enter the Premium Amount $, the Amount You Pay $ and the Amount Employer Pays $, and for each Check One: Weekly, Bi-Weekly or Semi-Monthly; under Dependent(s) Covered by that insurance, enter each dependent's Name (First, Middle, Last), Social Security Number, Sex, Date of Birth, Policy Number(s), Start Date and End Date.
If names and policy numbers of additional dependents covered by your Dental Insurance or your Vision Insurance are listed on a separate sheet of paper, check the box and attach the sheet.
Section II: Other Parent's Insurance
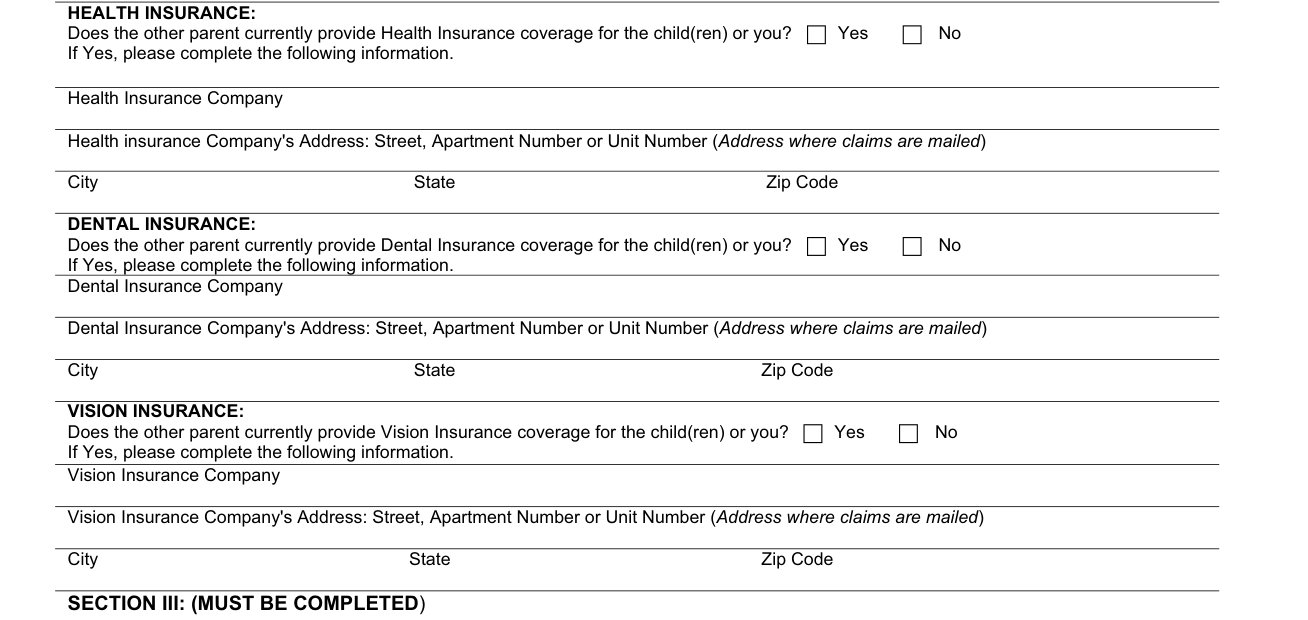
For Health Insurance, Dental Insurance and Vision Insurance: Does the other parent currently provide that coverage for the child(ren) or you? Yes No. If Yes, enter the Insurance Company, its Address: Street, Apartment Number or Unit Number (Address where claims are mailed), City, State, Zip Code.
Section III: Must Be Completed

Section III must be completed; check I have enclosed the insurance card(s)/information about the coverage for the child(ren), if you enclosed it.
If you do not have the insurance cards/information about the coverage for the child(ren), check At this time I do not have the insurance cards/information about the coverage for the child(ren). I will send the information to you when I get it from the insurance company.
If there is no health insurance coverage available, check At this time there is no health insurance coverage available. Coverage is unavailable because: Not offered, Seasonal, Part-Time, Refused enrollment, Unreasonable in cost or Probationary period/date eligible.
I understand that if it becomes available, I will have to add my child(ren) onto the plan and then notify the local child support agency of the coverage.
Signature, Date, Printed Name, Telephone and Title

Sign on SIGN and enter the SIGNATURE, DATE, PRINTED NAME, TELEPHONE (include Area Code) and TITLE.
Sources
[1] Health Insurance Information, DCSS 0054 (04/27/05), California Department of Child Support Services (the Official source link on this page).
[2] childsupport.ca.gov, submission_method. Accessed October 20, 2026.
