

Dermal Filler Consent Form at a glance
What it is: The Dermal Filler Consent Form is for treatment with Dermal Filler injection for the condition known as: Facial Static Wrinkles.
Who signs: Sign Patient Signature and fill in Date, then Witness Signature and Date.
A filled-in Dermal Filler Consent Form example: a patient completes the medical questionnaire

How to fill out Dermal Filler Consent Form, box by box
Name, Telephone, Email Address, Address, Medications and Allergies
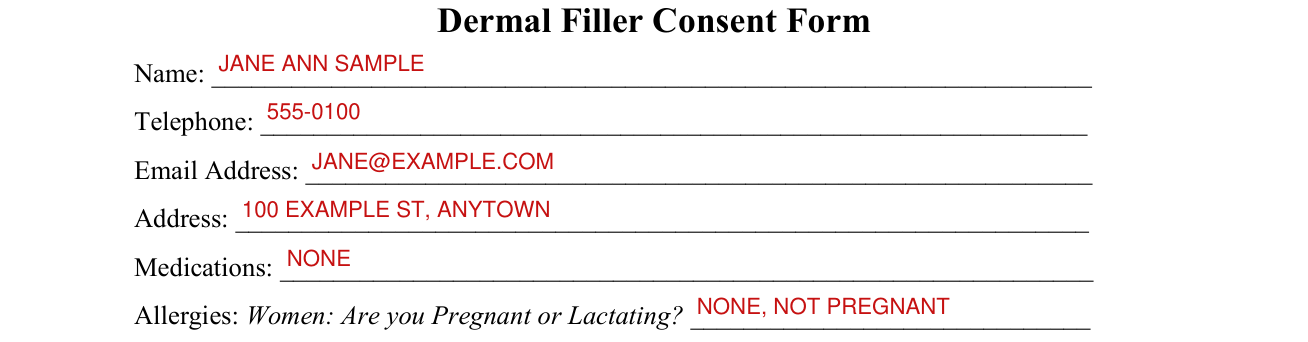
Fill in Name, Telephone, Email Address, Address and Medications.
Fill in Allergies and, for Women, Are you Pregnant or Lactating?
Medical history

Circle any of the following history you have or have had in the past: History of Anaphylaxis, Multiple Severe Allergies, Facial Acne, Active Inflammatory process, Infection (at proposed injection site), Hives, Immunosuppressive Therapy, Autoimmune Disease, Herpes, Facial Rashes.
Fill in Any Other Medical Disease, then EXPLAIN, and Previous Hospitalizations/Operations.
If any changes occur in my medical history/health I will report it to the office as soon as possible.
Signing the medical questionnaire

I have read and understand the medical questionnaire. Sign Patient Signature and fill in Date.
I acknowledge that all answers have been recorded truthfully and will not hold any staff member responsible for any errors or omissions that I have made in the completion of the form.
Patient Signature and Witness Signature

Sign Patient Signature and fill in Date, then Witness Signature and Date.
I am not aware that I am pregnant, have any significant Medical diseases, or have any severe allergies.
The procedure has been explained to me. I have read and understand it. My questions have been answered satisfactorily. I accept the risks and complications of the procedure.
Dental Infiltrate Consent
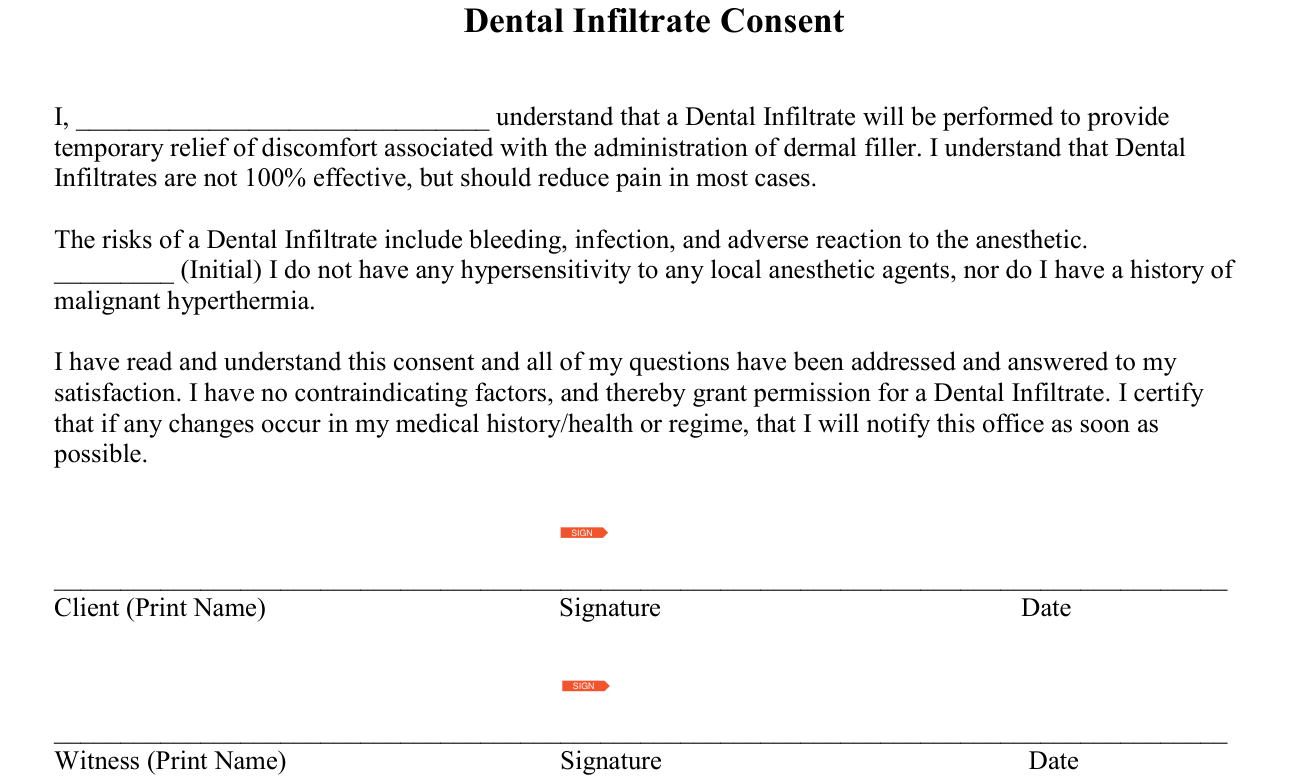
I understand that a Dental Infiltrate will be performed to provide temporary relief of discomfort associated with the administration of dermal filler.
The risks of a Dental Infiltrate include bleeding, infection, and adverse reaction to the anesthetic. Initial: I do not have any hypersensitivity to any local anesthetic agents, nor do I have a history of malignant hyperthermia.
I understand that Dental Infiltrates are not 100% effective, but should reduce pain in most cases.
I have read and understand this consent and all of my questions have been addressed and answered to my satisfaction. I have no contraindicating factors, and thereby grant permission for a Dental Infiltrate.
By signing you certify that if any changes occur in your medical history/health or regime, you will notify the office as soon as possible. Write Client (Print Name), Signature and Date, then Witness (Print Name), Signature and Date.
More rules for Dermal Filler Consent Form
The procedure takes about 20-30 minutes. Results last approximately six months.
Areas most frequently treated are: nasolabial folds, oral commissures, lips, and Glabellar. Client may experience a slight burning sensation during injections.
Such risks include but are not limited to: 1) Post treatment discomfort, swelling, redness, and bruising, 2) Post treatment bacterial, viral, and/or fungal infection requiring further treatment, 3) Allergic reaction.
Dermal Filler is a gel of hyaluronic acid generated by streptococcus species of bacteria, chemically cross linked with BDDE, stabilized and suspended in physiologic buffer at PH=7 and concentration of 20 mg/ml.
I authorize the taking of clinical photographs and their use for scientific purposes both in publications and presentation. I understand my identity will be protected.
I understand the information on this form is essential to determine my medical and cosmetic needs and the provision of treatment.
I understand that this procedure is cosmetic and that payment is my responsibility.
Sources
[1] Dermal Filler Consent Form, a generic template with no single issuer (the Official source link on this page).
