


DHCS 6002 Initial Treatment Provider Application at a glance
What it is: The Initial Treatment Provider Application is the initial residential licensure and certification application of the Licensing and Certification Section, MS 2600, PO Box 997413, Sacramento, CA 95899-7413.
Who signs: Only one signature is required unless applicant is a partnership.
What to bring and attach to DHCS 6002 Initial Treatment Provider Application
Tab 2 (all applicants): Corporations, LLP's, or LLC's must attach their approved articles of incorporation; partnerships must attach the partnership agreement; non-profit organizations must attach a copy of the 501(c)(3) filing from the California Secretary of State; sole proprietors must attach the Sole Proprietor Supplement.
The application and all supportive documentation must be printed single sided, with 12 point font on 8 1/2" by 11" white paper.
A filled-in DHCS 6002 Initial Treatment Provider Application example: a corporation applies for a residential license

How to fill out DHCS 6002 Initial Treatment Provider Application, box by box
Application Type and Purpose

Check the appropriate box(es) for the service(s) which you are applying for with this application. If you are applying for more than one type of service at the same location check all the boxes that apply.
Check all box(es) best describing the purpose of this application.
If you are changing ownership of an existing facility, list the license and/or certification number of the program that is being abolished. If you are merging this program with another program, list the license and/or certification number of that program. You must include the change of ownership documents and board resolution documents authorizing the merge and/or sale under Tab #2.
Legal Entity Name and Program/Facility Name

Enter the legal entity name.
Corporation only: For a corporation or Limited Liability Company (LLC) of any type this box must match exactly the name of the corporation (or LLC) as filed with the Secretary of State (SOS) and on the articles of incorporation.
Sole Proprietor only: For a sole proprietorship, this box must be the full legal name of the sole proprietor and include the Sole Proprietor Supplement. Sole proprietors only: Must submit a copy of the fictitious business name statement if different from their full legal name.
Enter the name of the Program/Facility. Do not include the legal entity name in this box unless the Program/Facility name is the same as the legal entity name.
Administrative/Corporate Address and Website
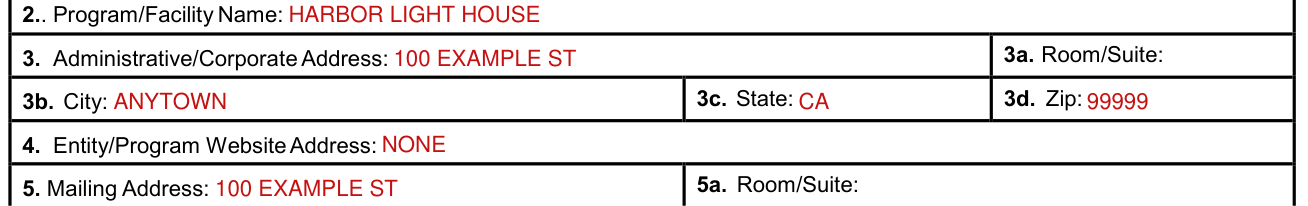
The Administrative/Corporate Address must be the physical address of the legal entity's main office. The Administrative/Corporate address may match the program's address if the entity does not have a separate Administrative/Corporate address.
P.O. Boxes or other mail receipt addresses will not be accepted as an administrative address; however, a P.O. Box may be used as a mailing address, as identified in instruction #5.
If the legal entity has a website, the website must be entered in the Entity/Program Website Address box. If the entity/program has no website, enter "None" in this box.
Mailing Address
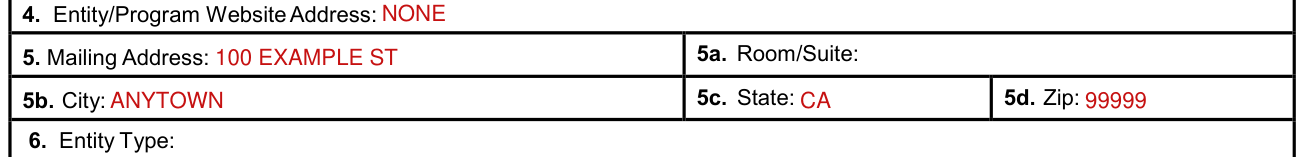
Enter the facility's mailing address. The department will use the mailing address to send all official mail.
Entity Type and Type of Organization
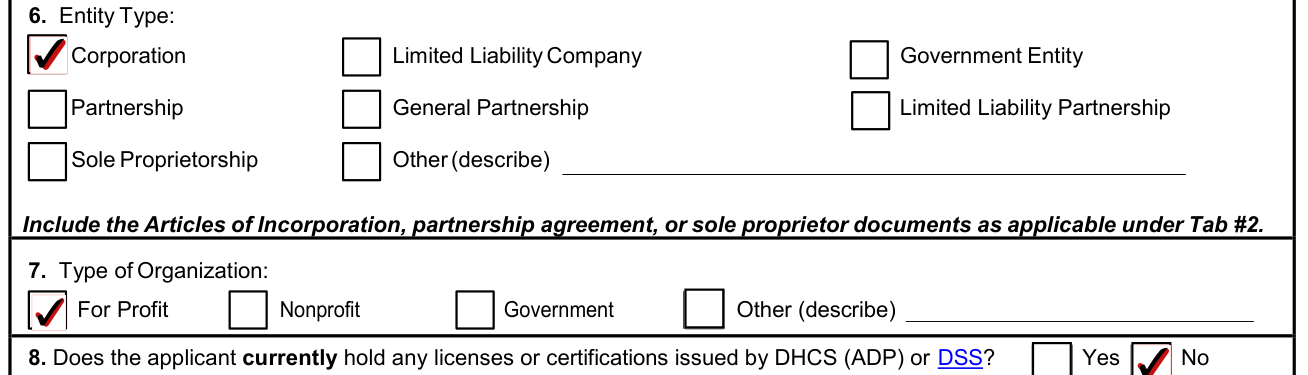
Entity Type: Check the box that describes the type of legal entity in which your organization operates.
For a corporation of any type, LLC, or LLP include the articles of incorporation under Tab #2.
Governmental Entities only: governmental entities do not need to provide documentation.
Type of Organization: Check the box that describes the tax status of your entity. If you check 'other', give a detailed description, including the government entity that granted the status.
Licenses and Certifications the Applicant Holds

Check 'Yes' if your legal entity has any other programs currently licensed and/or certified by the listed departments; check 'No' if not. If you check 'Yes' enter the license, certification and/or DMC billing number of all of your other facilities and select the type of facility from the drop down list.
More rules for DHCS 6002 Initial Treatment Provider Application
Current providers wishing to relocate, add or delete treatment services, increase/decrease treatment beds or change target population must complete the Supplemental Application DHCS 5255 (Rev. 6/16).
Complete all applicable sections of the application. If a line or question does not apply to you, fill the line or question with "N/A." If an entire section does not apply to your application, place a check mark in the "N/A" box located in the section heading.
Each item must be numbered and separated by correspondingly numbered tabbed dividers. Packets not submitted in this order will be rejected without review.
INSTRUCTIONS: Use this form to identify all staff of the facility.
Check 'Yes' if the legal entity has previously been issued a DHCS or ADP license or certification other than those listed in question 8; check 'No' if not. If you check 'Yes' enter the program name(s), license number(s) and address(es) in the boxes provided.
If anyone associated with the legal entity has previously had an ADP, DHCS, or DSS license or certification denied, terminated, suspended, or revoked, check 'Yes'. If you check 'Yes', provide the applicant/employee name, license and/or certification number, reason for denial, termination, suspension or revocation and the individual's relationship to the program. If necessary, include additional sheets under Tab #3.
Enter the contact information of the person you want the DHCS to contact regarding this application.
Facility/Building Address - Enter the address where the treatment services will be provided.
State - Must be California - this field cannot be changed. The Department does not license or certify programs not physically located in California.
Phone Number - Each licensed and/or certified facility must have a physical phone number, not including a cellular phone. Do not enter your corporate phone number unless your corporate facility address is the same as the facility address.
Fax Number - Enter the fax number assigned to the facility, if applicable.
If the facility currently holds a DMC Certification check 'Yes'; if not check 'No'. If yes, enter the 6 digit DMC Provider ID number: if you answered yes to #2, enter the six digit Provider ID number of your DMC certification.
Site specific National Provider Identification (NPI) number, if any: if you answered yes to #2, you must enter your NPI number. Enter the 10 digit NPI number for the facility.
If there is more than one building being used to provide the services for which you are applying, check 'yes'; if not, check 'no'. If you answer 'yes', enter the total number of buildings and put all addresses on the application (Section C, Box #1).
If the buildings that make up this facility are on the same piece of property or parcel of land check 'yes'. If you answer 'no' to whether or not the buildings are on the same piece of property or parcel of land, answer whether or not the services you are providing in each building are integral to each other. If the services are integral check 'yes'; if not, check 'no'.
Check the box that best describes the relationship between you and the owner of the building. If you lease the building, include a copy of the lease agreement under Tab #3.
Common questions about DHCS 6002 Initial Treatment Provider Application
Who signs it?
The application must be signed by an authorized individual. If the applicant applying is a partnership of any type, the application must be signed by all partners. If the applicant applying is a sole proprietor, the application must be signed by the sole proprietor.
Is there a deadline?
The application process is normally completed within 120 days. The 120 days begins when an application packet is determined to be complete.
Where do I file it?
Mail the completed application, documentation, and a check or money order, made out to the Department of Health Care Services, to cover the appropriate initial application fee, to Department of Health Care Services, Substance Use Disorder Compliance Division, Licensing and Certification Section, PO Box 997413, MS 2600, Sacramento, California 95899-7413.
Are there fees?
See the Department's website for the current fee structure.
Is there a penalty?
By signing you certify under penalty of perjury that you have read, understand, and will comply with the regulations and/or standards that govern the operation of the program for which you are applying.
What am I certifying when I sign?
The information contained in this application is accurate, true and complete in all material aspects.
Sources
[1] DHCS 6002 (Rev. 06/16), Initial Treatment Provider Application, Department of Health Care Services (the Official source link on this page).