

DHCS 6168 at a glance
What it is: The Potential Third Party Liability Notification is a Department of Health Care Services form.
Where and when to file: Fax it to the Department of Health Care Services, TPL/Personal Injury Unit, at (916) 440-5668, OR mail the original to Health Management Systems, WC Recovery Program, 660 J Street, Suite 270, Sacramento, CA 95814.
A filled-in DHCS 6168 example: a notice about an injury at a park

How to fill out DHCS 6168, box by box
To, date and Questions 1 and 2

After To:, mark Department of Health Care Services or Health Management Systems, and enter the Date.
Mark Yes or No for 1. Have you used, or will you use, Medi-Cal for your injury or illness? and for 2. Have you filed, or will you file, a lawsuit or insurance claim?
If you answered Yes to one or both of the above questions, complete box 3 and the boxes below it.
Injury/illness occurred at

Mark where the injury or illness occurred: Home, School, On someone else's property, Work, Motor vehicle or Other, and write it on the Other line.
Case name and date of injury or illness

Enter the Case name (first, middle, last) and the Date of injury or illness; the date must be provided.
Address and Social security number

Enter the Address (number, street), City, State, ZIP code and Social security number.
Mailing address and telephone number

Enter the Mailing address, City, State, ZIP code and Telephone number.
Injured Person(s)
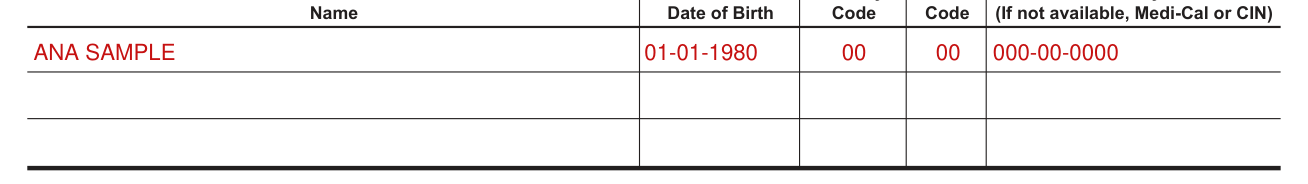
Under Injured Person(s), enter each Name, Date of Birth, County Code, Aid Code and Social Security Number; if the Social Security Number is not available, enter the Medi-Cal or CIN.
Have you filed, or will you file, a lawsuit?

Mark Yes or No for 4. Have you filed, or will you file, a lawsuit? If yes, provide the Attorney name, Telephone number and Mailing address, City, State, ZIP code.
Is there insurance covering you or anyone else
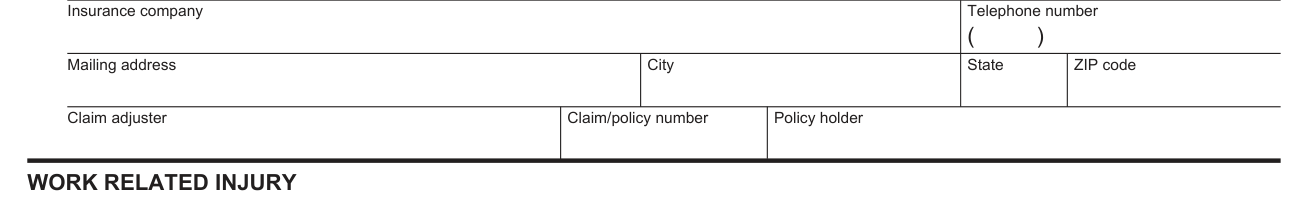
Mark Yes or No for 5. Is there insurance (other than Medi-Cal/Medicare) covering you or anyone else for this injury/illness? If yes, provide the Insurance company, Telephone number, Mailing address, City, State, ZIP code, Claim adjuster, Claim/policy number and Policy holder.
Work related injury
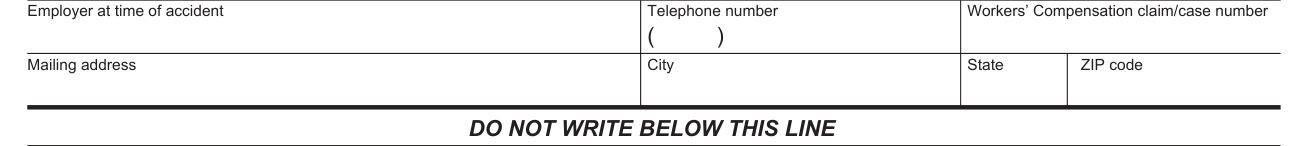
Under WORK RELATED INJURY, mark Yes or No for: Have you filed an application for Workers' Compensation benefits?
Enter the Employer at time of accident, the Telephone number, the Workers' Compensation claim/case number, and the Mailing address, City, State, ZIP code.
Sources
[1] DHCS 6168 (2/11), Potential Third Party Liability Notification, Department of Health Care Services (the Official source link on this page).