


Form DHS-1514 at a glance
What it is: Form DHS-1514 is the Application for State Emergency Relief of the Michigan Department of Health and Human Services.
Who signs: Sign and date the Signature of applicant or authorized representative; the Signature of spouse also has a Date.
You make application for the State Emergency Relief (SER) Program.
A filled-in Form DHS-1514 example: a single adult applies
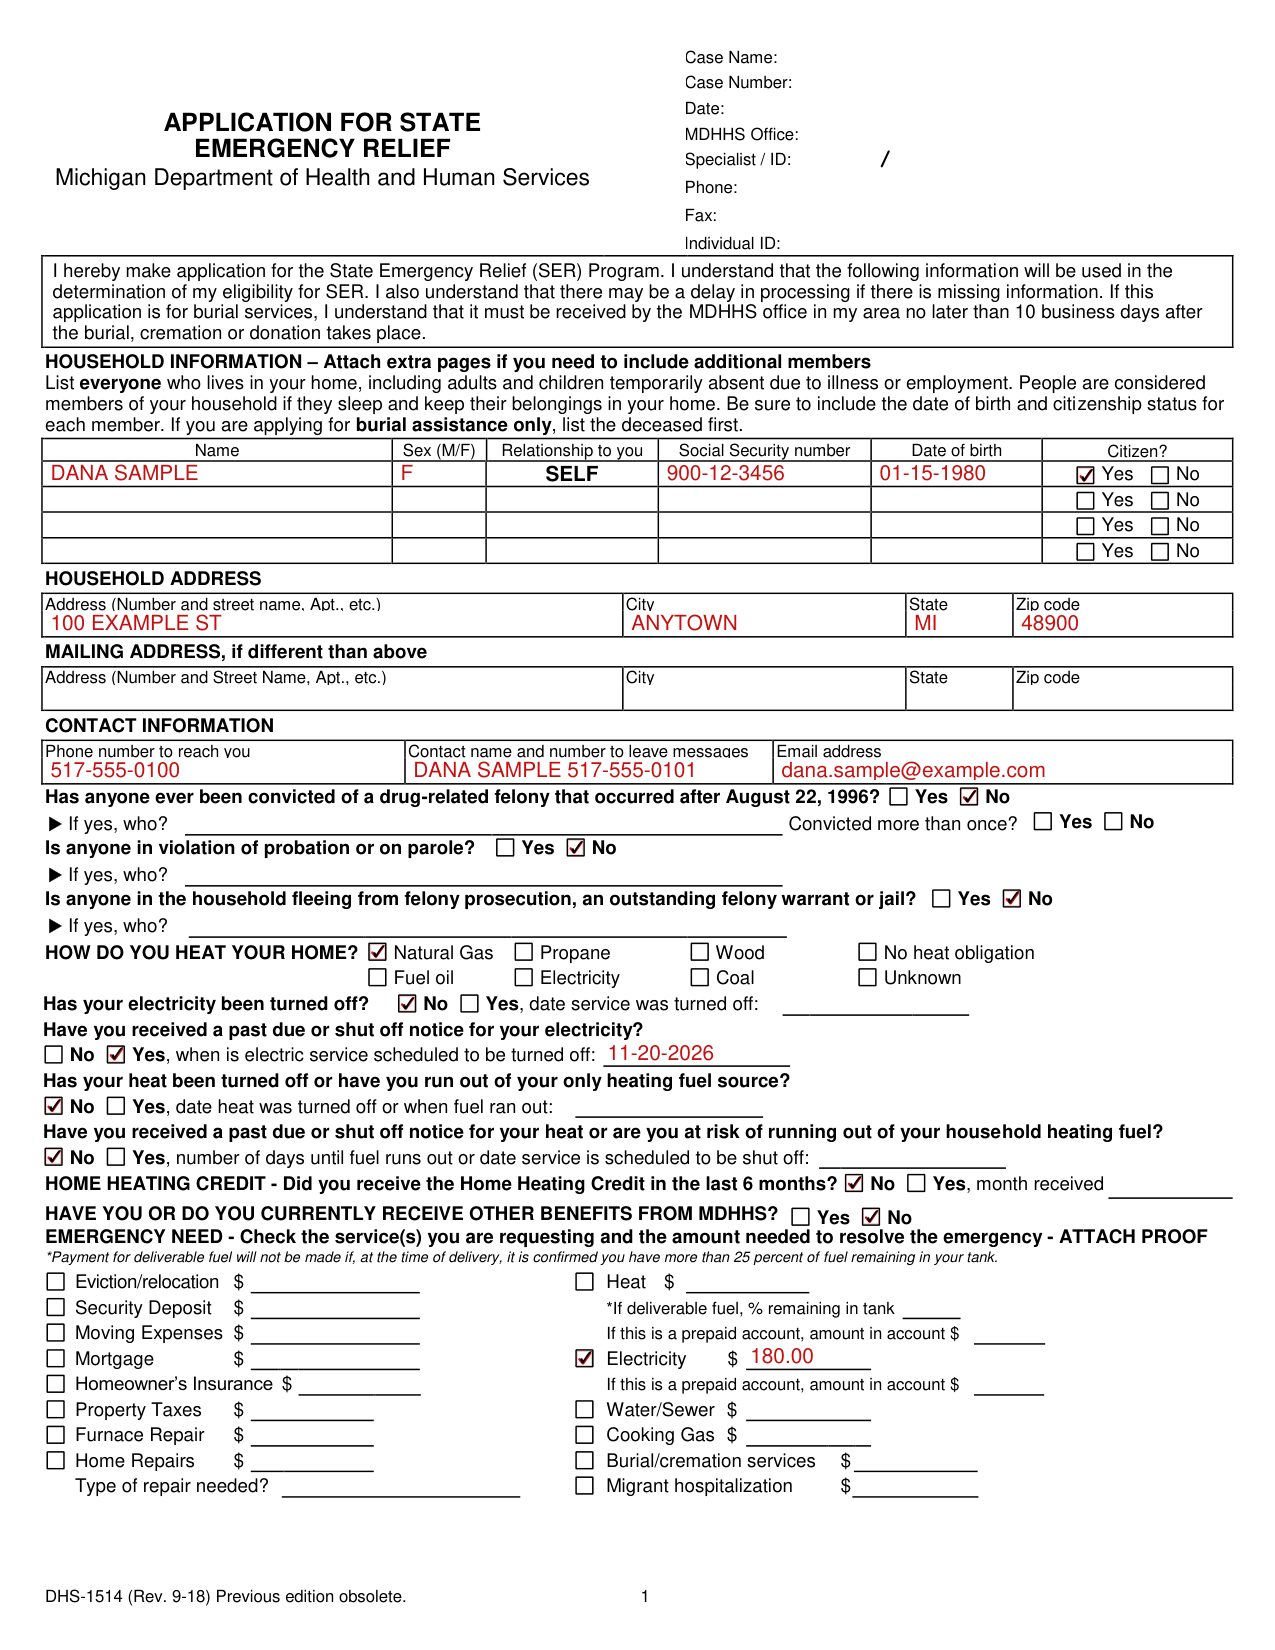
How to fill out Form DHS-1514, box by box
HOUSEHOLD INFORMATION

List everyone who lives in your home, including adults and children temporarily absent due to illness or employment. Attach extra pages if you need to include additional members.
People are considered members of your household if they sleep and keep their belongings in your home.
Be sure to include the date of birth and citizenship status for each member.
If you are applying for burial assistance only, list the deceased first.
Enter the Name, Sex (M/F), Relationship to you, Social Security number, Date of birth, and Citizen? Yes or No.
HOUSEHOLD ADDRESS and MAILING ADDRESS
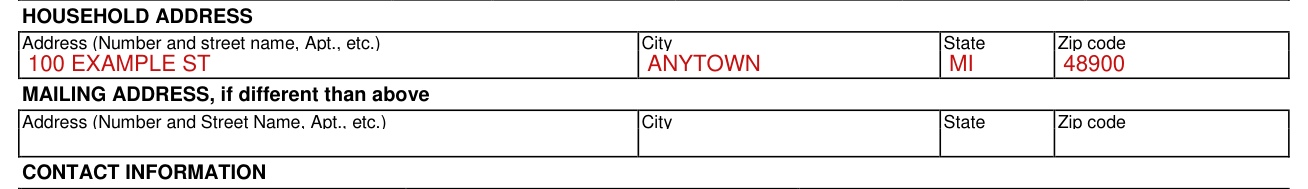
Enter the Address (Number and street name, Apt., etc.), City, State and Zip code under HOUSEHOLD ADDRESS; under MAILING ADDRESS, if different than the household address, enter the same boxes.
CONTACT INFORMATION

Enter the Phone number to reach you, the Contact name and number to leave messages, and the Email address.
Convicted of a drug-related felony
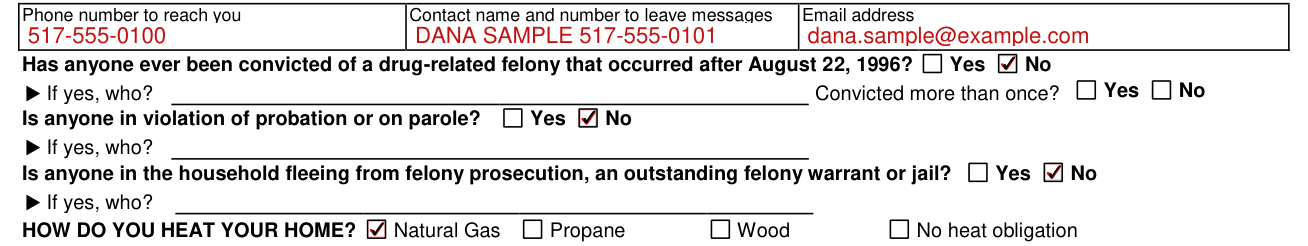
Has anyone ever been convicted of a drug-related felony that occurred after August 22, 1996? Mark Yes or No; if yes, write who.
Convicted more than once? Mark Yes or No.
Is anyone in violation of probation or on parole? Mark Yes or No; if yes, write who.
Is anyone in the household fleeing from felony prosecution, an outstanding felony warrant or jail? Mark Yes or No; if yes, write who.
HOW DO YOU HEAT YOUR HOME?

HOW DO YOU HEAT YOUR HOME? has the boxes Natural Gas, Propane, Wood, No heat obligation, Fuel oil, Electricity, Coal and Unknown.
Electricity or heat turned off

Has your electricity been turned off? Mark No, or Yes with the date service was turned off.
Have you received a past due or shut off notice for your electricity? Mark No, or Yes with when electric service is scheduled to be turned off.
Has your heat been turned off or have you run out of your only heating fuel source? Mark No, or Yes with the date heat was turned off or when fuel ran out.
Have you received a past due or shut off notice for your heat or are you at risk of running out of your household heating fuel? Mark No, or Yes with the number of days until fuel runs out or the date service is scheduled to be shut off.
HOME HEATING CREDIT

Did you receive the Home Heating Credit in the last 6 months? Mark No, or Yes with the month received.
OTHER BENEFITS FROM MDHHS

Have you or do you currently receive other benefits from MDHHS? Mark Yes or No.
EMERGENCY NEED
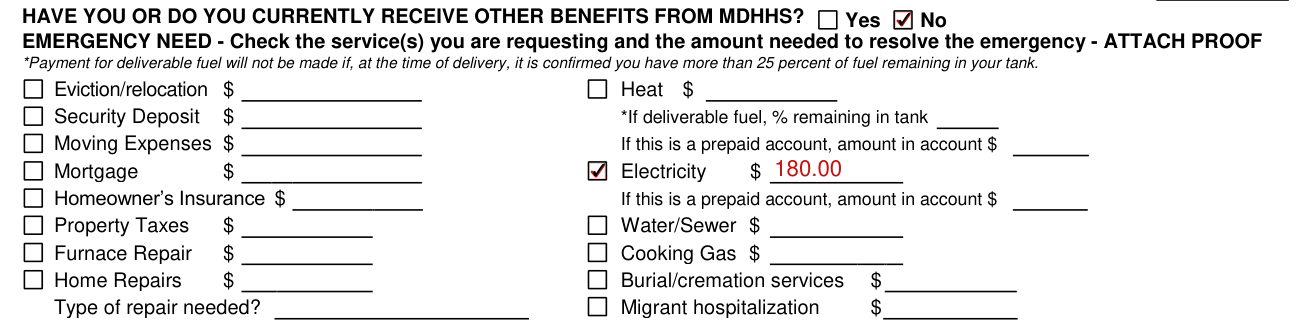
Check the service(s) you are requesting: Eviction/relocation, Security Deposit, Moving Expenses, Mortgage, Homeowner's Insurance, Property Taxes, Furnace Repair, Home Repairs (Type of repair needed?), Heat, Electricity, Water/Sewer, Cooking Gas, Burial/cremation services or Migrant hospitalization. Write the amount needed to resolve the emergency, and ATTACH PROOF.
Payment for deliverable fuel will not be made if, at the time of delivery, it is confirmed you have more than 25 percent of fuel remaining in your tank.
If deliverable fuel, write the % remaining in tank. If this is a prepaid account, write the amount in account.
HOUSEHOLD VEHICLE(S)
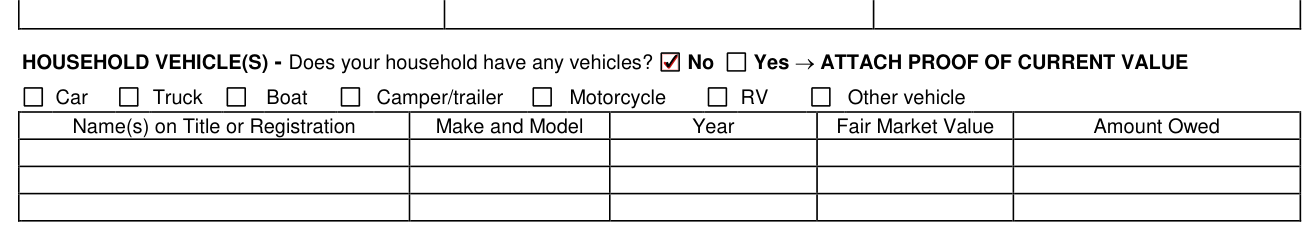
Does your household have any vehicles? Mark No, or Yes and ATTACH PROOF OF CURRENT VALUE.
For each vehicle, check Car, Truck, Boat, Camper/trailer, Motorcycle, RV or Other vehicle, and enter the Name(s) on Title or Registration, Make and Model, Year, Fair Market Value and Amount Owed.
HOUSEHOLD ASSETS
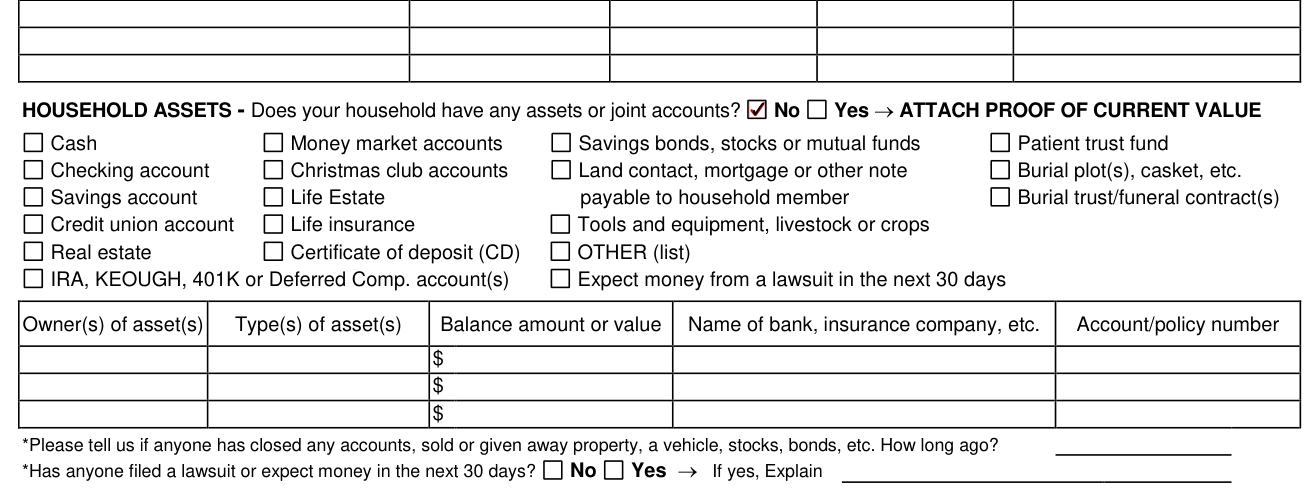
Does your household have any assets or joint accounts? Mark No or Yes; if Yes, ATTACH PROOF OF CURRENT VALUE.
Enter the Owner(s) of asset(s), Type(s) of asset(s), Balance amount or value, Name of bank, insurance company, etc. and Account/policy number.
Under HOUSEHOLD ASSETS, Does your household have any assets or joint accounts? Mark No or Yes. If anyone has closed any accounts, sold or given away property, a vehicle, stocks, bonds, etc., write How long ago?
Under HOUSEHOLD ASSETS, Does your household have any assets? Has anyone filed a lawsuit or expect money in the next 30 days? Mark No or Yes; if yes, Explain.
HOUSEHOLD INCOME
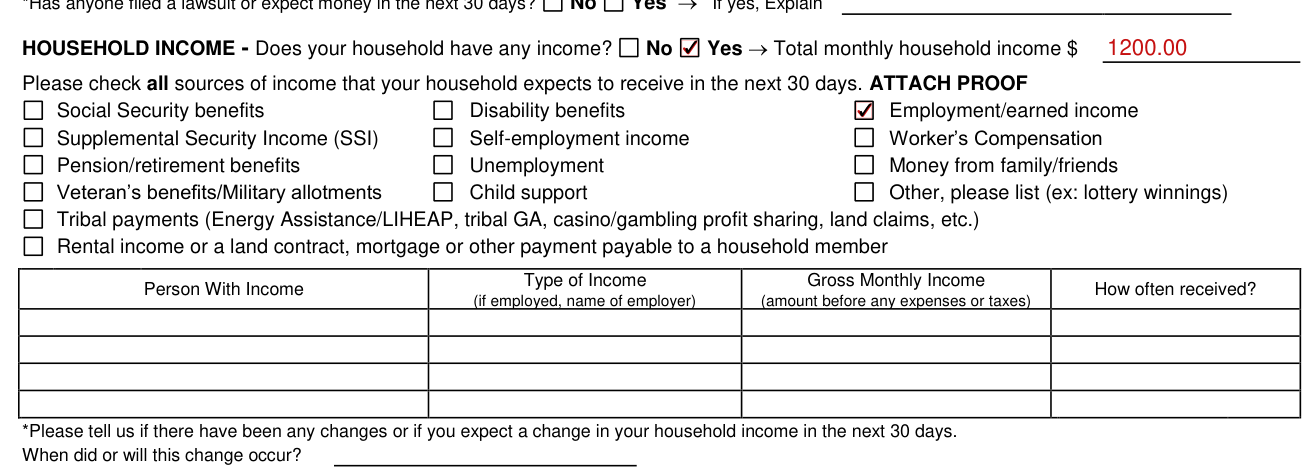
Does your household have any income? Mark No, or Yes with the Total monthly household income.
Check all sources of income that your household expects to receive in the next 30 days, and ATTACH PROOF.
For each income, enter the Person With Income, Type of Income (if employed, name of employer), Gross Monthly Income (amount before any expenses or taxes) and How often received?
If there have been any changes or if you expect a change in your household income in the next 30 days, write When did or will this change occur?
CURRENT HOUSING EXPENSES
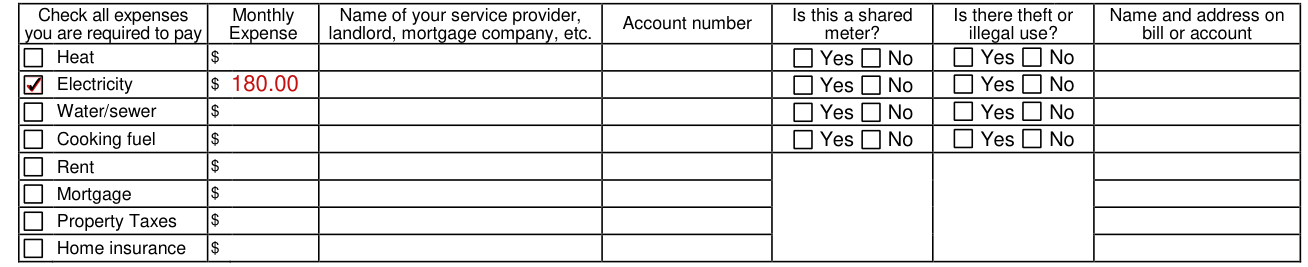
For housing expenses, check all expenses you are required to pay: Heat, Electricity, Water/sewer, Cooking fuel, Rent, Mortgage, Property Taxes or Home insurance. Enter the Monthly Expense.
Enter the Name of your service provider, landlord, mortgage company, etc., the Account number, and the Name and address on bill or account.
For Heat, Electricity, Water/sewer and Cooking fuel, mark Yes or No for Is this a shared meter? and for Is there theft or illegal use?
PAST SIX MONTHS

Complete the chart for the past six (6) months about your expenses, income and how many people live with you. If you did not have the expense, write “NONE” in the box.
For each of 1 MONTH AGO, 2 MONTHS AGO, 3 MONTHS AGO, 4 MONTHS AGO, 5 MONTHS AGO and 6 MONTHS AGO, enter the Month, # of people in home, Total monthly income, Rent/Mortgage amount, Heat, Electricity, and Water, Sewer & Cooking Gas.
INCOME EXPENSES

Under INCOME EXPENSES, does your household pay any of the following? Mark No, or Yes, check all that apply and ATTACH PROOF.
Check the expenses that apply: Health insurance premium (Paid how often?), Court ordered child support (amount paid per month), Actual child care costs paid by the employed person, not MDHHS, and Unusual employment related expenses (Explain expense).
SIGNATURE REQUIREMENT
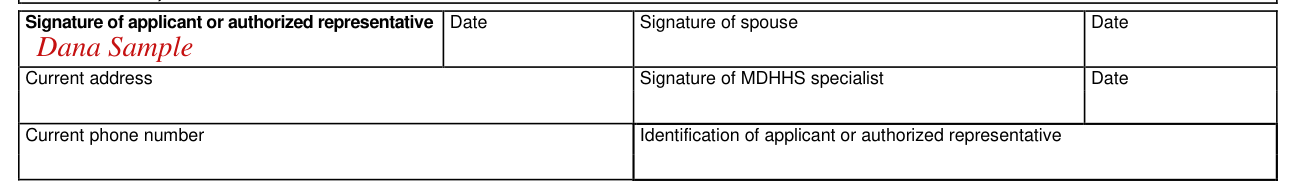
Sign the Signature of applicant or authorized representative and enter the Date, the Current address, the Current phone number and the Identification of applicant or authorized representative. The Signature of spouse also has a Date.
Failure to provide the information may result in denial of your application.
You have eight calendar days to provide all verifications requested.
Giving false information can result in referral to the prosecutor for fraud.
Under penalties of perjury, you swear or affirm that this application has been examined by or read to you.
If you are a third party applying on behalf of another person, you swear that this application has been examined by or read to the applicant, unless the application is for a deceased person.
To the best of your knowledge, the facts are true and complete.
register to vote
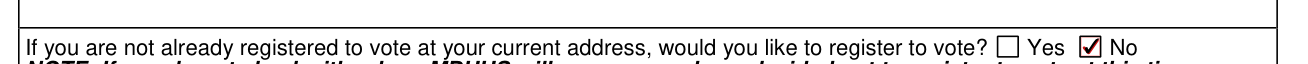
If you are not already registered to vote at your current address, would you like to register to vote? If you do not check either box, MDHHS will assume you have decided not to register to vote at this time.
If your situation is different
BURIAL
If this application is for burial services, you understand that it must be received by the MDHHS office in your area no later than 10 business days after the burial, cremation or donation takes place.
If you are applying for burial services, please complete this section.
HEARINGS
If you believe any action of the department is incorrect, or if the decision to approve or deny your application is not made within 10 (ten) days of the application date, you have the right to a hearing.
A request for a hearing must be in writing, signed by you or your authorized representative, and received by the Michigan Department of Health and Human Services within 90 days following the date of this form.
Hearing requests should be sent to your local MDHHS office in your area.
Before you go
You also understand that there may be a delay in processing if there is missing information.
Common questions about Form DHS-1514
Is there a penalty?
COMPLETION: Required. PENALTY: Denial of SER.
Sources
[1] Form DHS-1514 (Rev. 9-18), Application for State Emergency Relief, Michigan Department of Health and Human Services (the Official source link on this page).