


DHS Form 3090-1 at a glance
What it is: Department of Homeland Security Individual Complaint of Employment Discrimination: use this form for original complaints and amendments. FOR OFFICIAL USE ONLY: Department Case Number and Filing Date.
Who signs: In accordance with 29 CFR 1614.106(c), your written complaint must be signed by you or your attorney.
GENERAL: This form should be used only if you, as an applicant for employment with the Department of Homeland Security (DHS), or as a present or former Department of Homeland Security employee, believe you have been discriminated against because of your race, color, religion, sex (including pregnancy, gender identity, and sexual orientation), national origin, age (40 years or older at the time of the event giving rise to your claim), physical or mental disability, genetic information or in reprisal for opposition to activities protected by civil rights statutes, or participation in proceedings to enforce those statutes. Under 1., it should be used only if you have also presented the matter for informal resolution to an Equal Employment Opportunity (EEO) Counselor after the event giving rise to your claim, or after first becoming aware of the alleged discrimination.
A filled-in DHS Form 3090-1 example: an employee files an age discrimination complaint

How to fill out DHS Form 3090-1, box by box
Complainant identification: name, telephone and email, home address

In Box 1, enter your name as Last, First, Middle Initial.
In Box 2, telephone (Include Area Code) and email: enter the Home and Work telephone, the Email Address and the Alternate Email Address.
In Box 3, Home Address, enter your Street Address, City, State and Zip Code; you must notify the Department of any change of address while complaint is pending, or your complaint may be dismissed.
Your title, series and grade, and where you work
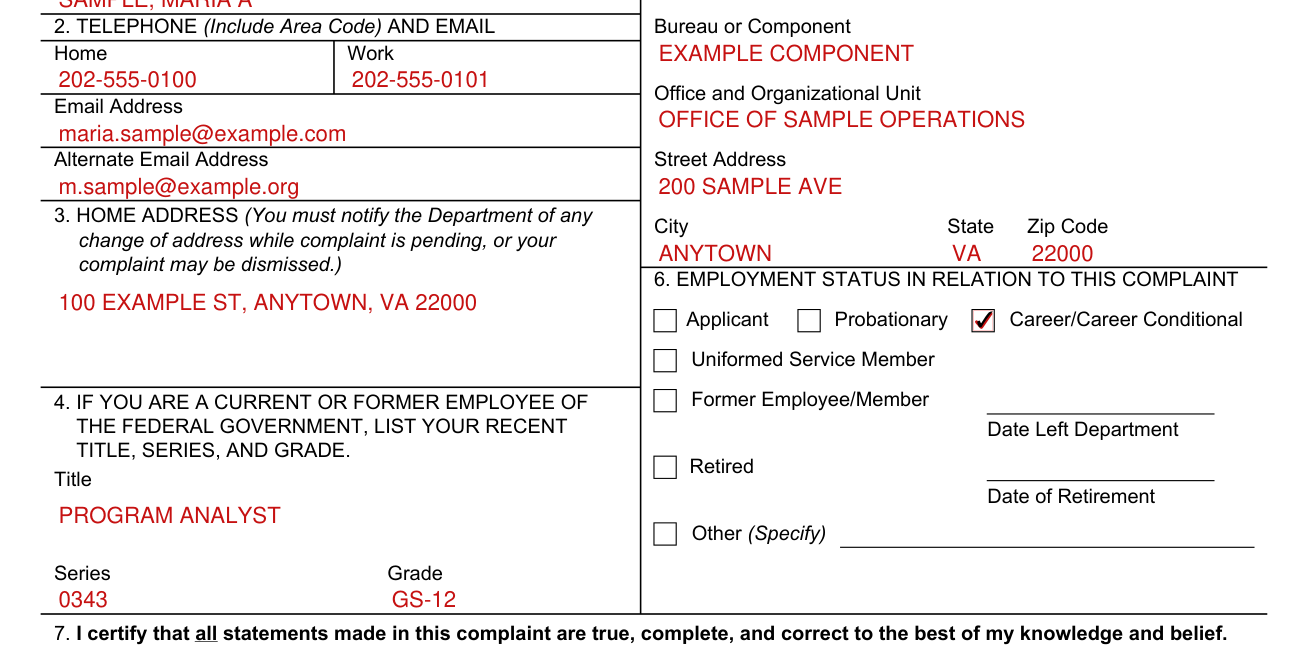
In Box 4, if you are a current or former employee of the Federal Government, list your recent Title, Series, and Grade.
In Box 5, Name and address of organization where you work (If a Department of Homeland Security Employee), enter the Bureau or Component, Office and Organizational Unit, Street Address, City, State and Zip Code.
Employment status in relation to this complaint

In Box 6, Employment status in relation to this complaint, mark Applicant, Probationary, Career/Career Conditional, Uniformed Service Member, Former Employee/Member, Retired or Other (Specify); enter the Date Left Department or the Date of Retirement where it applies.
Part II: designation of representative
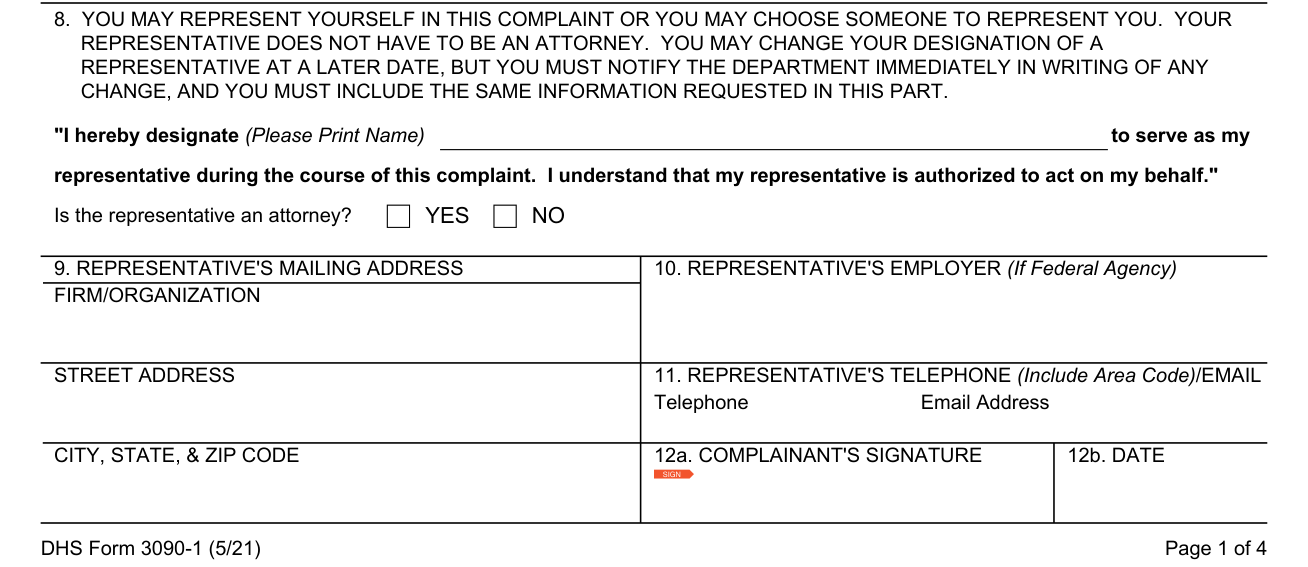
You may represent yourself in this complaint or you may choose someone to represent you. Your representative does not have to be an attorney. You may change your designation of a representative at a later date, but you must notify the Department immediately in writing of any change, and you must include the same information requested in this part.
In Part II, print the name of your representative after "I hereby designate (Please Print Name)", to serve as my representative during the course of this complaint. I understand that my representative is authorized to act on my behalf.
In Part II, mark YES or NO for Is the representative an attorney?
In Part II, Box 9 is the Representative's mailing address: Firm/Organization, Street Address, City, State, & Zip Code; Box 10 is the Representative's employer (If Federal Agency); Box 11 is the Representative's telephone (Include Area Code)/Email, with Telephone and Email Address; Box 12a is the Complainant's Signature and Box 12b is the Date.
Certification, signature and date

In Box 7, I certify that all statements made in this complaint are true, complete, and correct to the best of my knowledge and belief.
You must sign and date your complaint: sign on SIGNATURE OF COMPLAINANT OR ATTORNEY REPRESENTATIVE and enter the DATE.
Your representative need not be an attorney, but only an attorney representative may sign the complaint on your behalf.
Part III: who took the action, and mediation
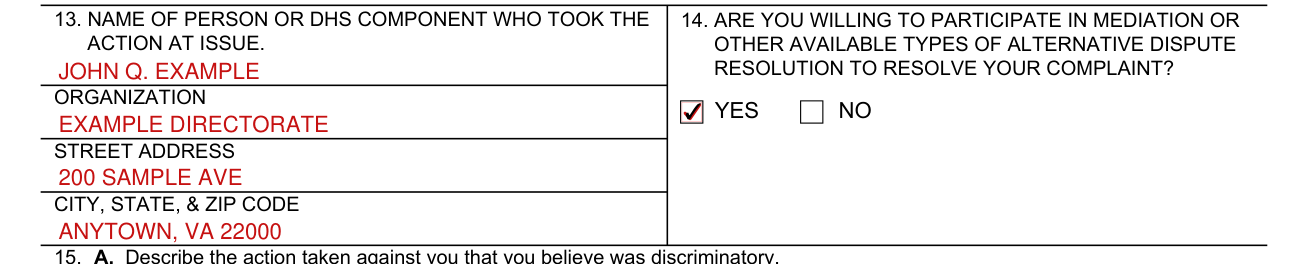
In Part III, Box 13 is the Name of person or DHS component who took the action at issue, with Organization, Street Address, and City, State, & Zip Code.
Box 14: are you willing to participate in mediation or other available types of alternative dispute resolution to resolve your complaint? Mark NO or YES.
Item 15: the action you believe was discriminatory

In Box 15A, describe the action taken against you that you believe was discriminatory.
In Box 15B, give the date when the action occurred, and the name of each person responsible for the action.
In Box 15C, describe how you were treated differently from other employees, applicants, or members for any of the reasons listed in Item 16.
In Box 15D, indicate what harm, if any, came to you in your work situation as a result of this action. (You may, but are not required to, attach extra sheets.)
In Box 15E, if the basis of your complaint is based on parental status, use this form, but your complaint is not statutorily based and will follow separate, parallel process.
In certain situations, the information provided in Part III of the attached complaint form may be used in lieu of an affidavit in the investigation of your complaint. Accordingly, the information you provide in Part III should be brief, clear, and complete.
Item 16: the bases

Item 16: Mark below ONLY the bases you believe were relied on to take the actions described in Item 15.
RACE (Specify), COLOR (Specify), RELIGION (Specify), NATIONAL ORIGIN (Specify), GENDER (Specify), Pregnancy, Gender Identity, Sexual Orientation, PARENTAL STATUS, GENETIC INFORMATION, AGE (Year of Birth), PHYSICAL OR MENTAL DISABILITY (Describe) and RETALIATION/REPRISAL (Dates of Prior EEO Activity).
Remedial or corrective action, and grievance or appeal

Box 17: What remedial or corrective action are you seeking to resolve this matter?
Box 18: on this same matter, have you filed a grievance or appeal under: Negotiated grievance procedure, Agency grievance procedure or Merit Systems Protection Board appeal procedure? Mark NO or YES for each.
If you filed a grievance or appeal, provide date filed, case number, and present status.
Part IV: contact with an EEO counselor
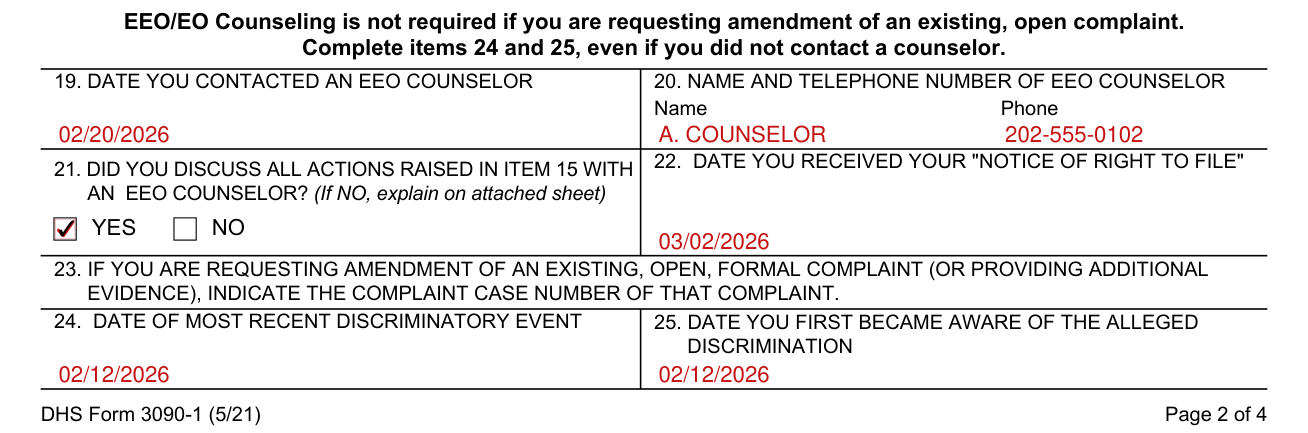
EEO/EO Counseling is not required if you are requesting amendment of an existing, open complaint.
Complete items 24 and 25, even if you did not contact a counselor.
Box 19 is the Date you contacted an EEO Counselor; Box 20 is the Name and Telephone number of the EEO Counselor.
Box 21: Did you discuss all actions raised in Item 15 with an EEO Counselor? Mark YES or NO; if NO, explain on attached sheet. Box 22 is the Date you received your "Notice of Right to File".
Box 23: if you are requesting amendment of an existing, open, formal complaint (or providing additional evidence), indicate the complaint case number of that complaint.
Box 24 is the Date of most recent discriminatory event; Box 25 is the Date you first became aware of the alleged discrimination.
More rules for DHS Form 3090-1
Please complete all items on the complaint form.
Keep a copy of the completed complaint form for your records.
Whether disclosure is mandatory or voluntary, and effect of not providing information: formal complaints of employment discrimination must be in writing, signed by the Complainant (or attorney representative), and must identify the parties and action or policy at issue. Failure to comply may result in the Department of Homeland Security dismissing the complaint. It is not mandatory that this form be used to provide the requested information.
Common questions about DHS Form 3090-1
Who signs it?
In accordance with 29 CFR 1614.106(c), your written complaint must be signed by you or your attorney.
Is there a deadline?
In accordance with 29 CFR 1614.106, your formal complaint must be filed within 15 calendar days of the date you received the "Notice of Right to File a Discrimination Complaint" from your EEO Counselor.
Where do I file it?
The complaint should be filed with the EEO Director of the Department of Homeland Security component where the alleged discrimination occurred; filing instructions are contained in the "Right to File" form, which was provided by your Counselor.
Sources
[1] DHS Form 3090-1 (5/21), Individual Complaint of Employment Discrimination, Department of Homeland Security (the Official source link on this page).