


Form SP-27 at a glance
What it is: SP-27 is the Disabled Persons License Plates and/or Placards Application.
Where and when to file: If applying for license plates you must go to your local DMV.
A filled-in Form SP-27 example: a first-time applicant for plates and one placard

How to fill out Form SP-27, box by box
Disabled License Plates, Placards, Motorcycle and Moped

Applicant Must Complete this Portion. You may select two (2) placards, or license plates and one (1) placard.
Disabled License Plates (permanent disability only), Disabled Placards(s) (no fee for placards) One or Two, Disabled Motorcycle Plate (permanent disability only), Disabled Motorcycle Sticker (permanent or moderate), Disabled Moped Plate (permanent disability only) or Disabled Moped Sticker (permanent or moderate).
Full Legal Name (Disabled Person)

Please Print or Type the Full Legal Name (Disabled Person): First, Middle, Last.
Enter the Nevada Driver's License or Identification Card Number and the Date of Birth.
Physical Address and Mailing Address

Under Physical Address, enter Address, City, State and Zip Code.
Under Mailing Address, enter Address, City, State and Zip Code.
Enter the County of Residence, Telephone No. and E-Mail Address.
Sign on the Signature of Applicant line and enter the Date.
Who completes this portion
Please Print or Type the Full Legal Name (Disabled Applicant): First, Middle, Last.
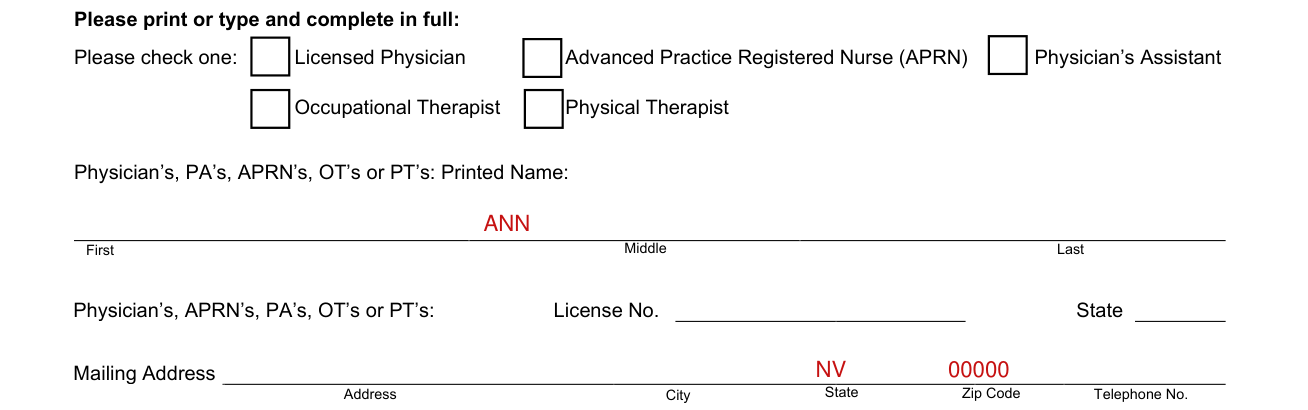
A licensed physician, physician's assistant (PA), advanced practice registered nurse (APRN), occupational therapist (OT) or physical therapist (PT) must complete this portion.
Please print or type and complete in full. Please check one: Licensed Physician, Advanced Practice Registered Nurse (APRN), Physician's Assistant, Occupational Therapist or Physical Therapist.
Enter the Printed Name: First, Middle, Last.
Enter the License No. and State.
Under Mailing Address, enter Address, City, State, Zip Code and Telephone No.
Physician, PA, APRN, OT or PT: certify that the applicant

"I hereby certify that the applicant: Cannot walk two hundred feet without stopping to rest."
Cannot walk without the use of a brace, cane, crutch, wheelchair, or prosthetic, or other assistive device, or another person.
Has a cardiac condition to the extent that functional limitations are classified as Class III or Class IV according to standards adopted by the American Heart Association.
Is restricted by a lung disease to such an extent that the person's forced expiratory volume for 1 second, when measured by a spirometer, is less than 1 liter, or the arterial oxygen tension is less than 60 millimeters of mercury on room air while the person is at rest.
Is severely limited in his/her ability to walk because of an arthritic, neurological, or orthopedic condition.
Has a visual disability. Uses portable oxygen.
Length of the disability

I further certify that my patient's condition is a: Temporary Disability (6 months or less): must indicate length of time not to exceed 6 months, beginning and ending. Moderate Disability (reversible but disabled longer than 6 months): must indicate length of time not to exceed 2 years, beginning and ending. Permanent Disability (irreversible, permanently disabled in his/her ability to walk): certification is valid indefinitely.
Sign on the Physician's, PA's, APRN's, OT's or PT's Signature line and enter the Date.
More rules for Form SP-27
You must have a permanent disability to qualify for disabled persons license plates.
First time applications for Disabled Persons license plates, motorcycle or moped license plates must be made in person.
In order to apply for disabled persons license plates or disabled motorcycle stickers, your name must appear on the vehicle certificate of registration and provide your current Nevada evidence of insurance.
If your vehicle is currently registered, you have the option of maintaining your current vehicle registration expiration date or renewing for a full twelve (12) month period.
Credit for any unused portion of your current registration is transferable to your disabled license plate registration.
In applicable counties, if you are renewing for a full 12-month period, and your previous emissions test was obtained more than 90 days ago, the vehicle must be re-tested prior to registration.
If the Physician's, APRN's, or Physician's Assistant portion is not completed in full, this application cannot be processed.
Erasures or whiteout will void this form.
Common questions about Form SP-27
Is there a penalty?
"I declare under penalty of perjury that the information on this application is true and correct."
Sources
[1] Form SP-27 (10/2026), Disabled Persons License Plates and/or Placards Application, Nevada DMV (the Official source link on this page).