

DWC Form-041 at a glance
What it is: DWC Form-041 is a claim filed within one year of the injury or within one year from the date the employee knew or should have known the injury or disease may be work-related.
Who signs: The injured employee or the person filling out this form on behalf of the injured employee signs.
Where and when to file: Send the completed form by fax to 512-804-4378.
A filled-in DWC Form-041 example: an injured employee files her claim
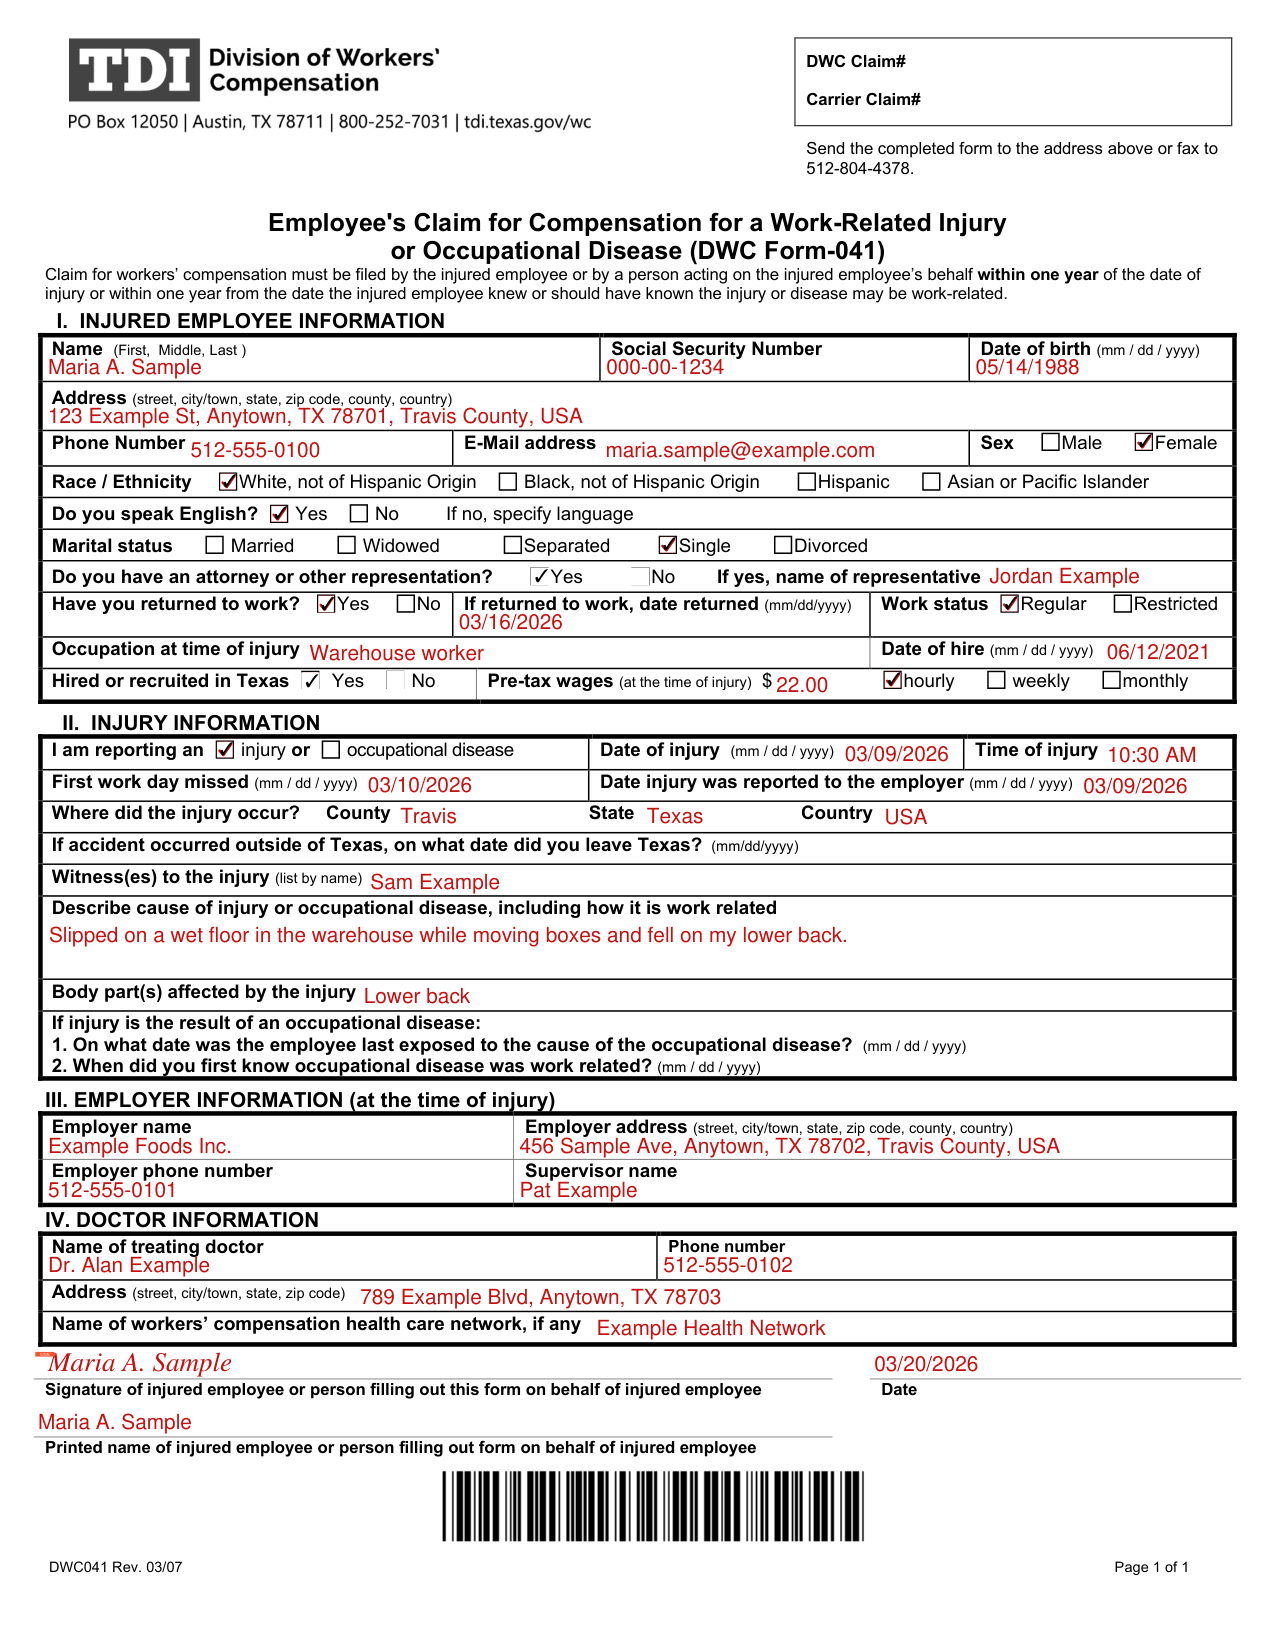
How to fill out DWC Form-041, box by box
Name, address, Phone Number and E-Mail address

Enter the Name (First, Middle, Last), Social Security Number and Date of birth (mm / dd / yyyy).
Enter the Address (street, city/town, state, zip code, county, country).
Enter the Phone Number and E-Mail address.
Sex, race, language and marital status
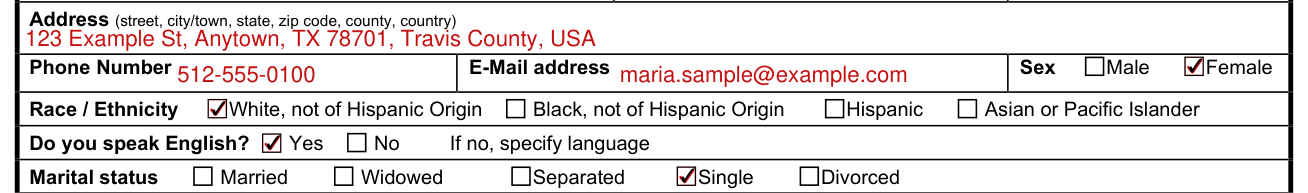
Under Sex, mark Male or Female.
Under Race / Ethnicity, mark White, not of Hispanic Origin, Black, not of Hispanic Origin, Hispanic or Asian or Pacific Islander.
Under Do you speak English?, mark Yes or No. If no, specify language.
Under Marital status, mark Married, Widowed, Separated, Single or Divorced.
Attorney and return to work

Under Do you have an attorney or other representation?, mark Yes or No. If yes, name of representative.
Under Have you returned to work?, mark Yes or No. If returned to work, date returned (mm/dd/yyyy).
If you have returned to your regular job and you are performing the same duties as you were before your injury, check the “Regular” box. If you have been released to work with restrictions by a doctor, check “Restricted.”
Occupation, hire date and wages

Enter the Occupation at time of injury and the Date of hire (mm / dd / yyyy).
Under Hired or recruited in Texas, mark Yes or No. Enter the Pre-tax wages (at the time of injury) and mark hourly, weekly or monthly.
Injury information
An injury is damage to your body that was caused by a single incident, accident, or event.
An occupational disease is an illness or injury related to or caused by the work you do, and may include injuries to your body that are the result of repetitive activities you performed on the job over a period of time.
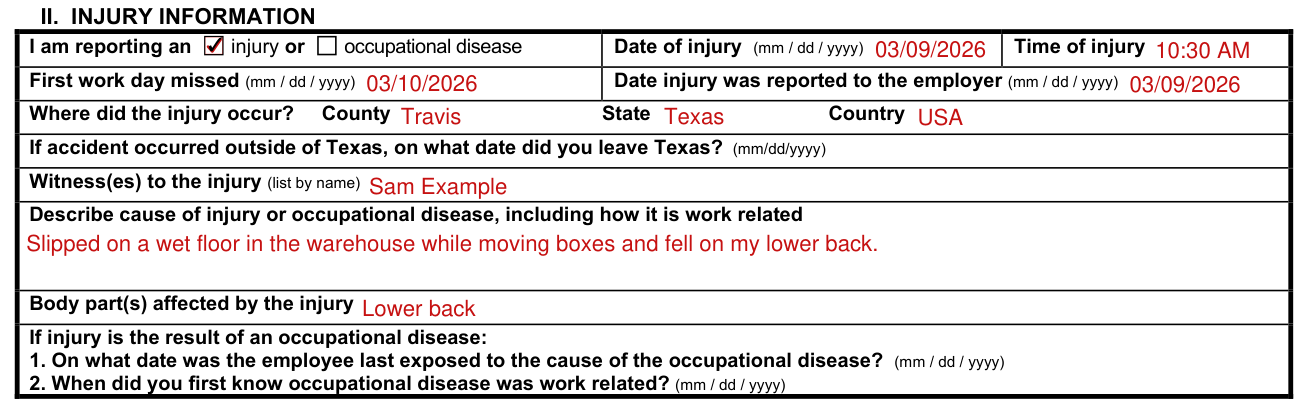
Under I am reporting an injury or occupational disease, mark injury or occupational disease. Enter the Date of injury (mm / dd / yyyy) and Time of injury.
Enter the First work day missed (mm / dd / yyyy) and the Date injury was reported to the employer (mm / dd / yyyy).
Under Where did the injury occur?, enter County, State and Country.
If accident occurred outside of Texas, on what date did you leave Texas? (mm/dd/yyyy).
List the Witness(es) to the injury by name.
Describe cause of injury or occupational disease, including how it is work related.
Enter the Body part(s) affected by the injury.
Occupational disease dates

If injury is the result of an occupational disease: 1. On what date was the employee last exposed to the cause of the occupational disease? (mm / dd / yyyy) 2. When did you first know occupational disease was work related? (mm / dd / yyyy)
Employer information

Provide information about your employer at the time you were injured.
Enter the Employer name and Employer address (street, city/town, state, zip code, county, country).
Enter the Employer phone number and Supervisor name.
Treating doctor and network

If you already have a workers' compensation treating doctor, provide the name and address of the doctor.
Enter the Name of treating doctor and Phone number.
Enter the Address (street, city/town, state, zip code).
If you are covered under a workers' compensation healthcare network, provide the name of the network.
Signature and date

Sign on the Signature of injured employee or person filling out this form on behalf of injured employee line, and enter the Date.
Enter the Printed name of injured employee or person filling out form on behalf of injured employee.
More rules for DWC Form-041
General Instructions: Complete all boxes in the DWC Form-041.
Upon receipt of your completed DWC Form-041, or other notice of your injury, the Division will create a claim and establish a DWC claim number for you, and the Division will mail information regarding workers' compensation in Texas to you.
The Division will also notify your employer and the employer's workers' compensation insurance carrier.
Common questions about DWC Form-041
What is the phone number for the Texas Division of workers compensation?
If you have questions about filling out this form or workers' compensation in Texas, please call your local Division Field Office at 1-800-252-7031.
Is there a deadline?
Instructions DWC041 Rev. 03/07: A claim for Workers' Compensation benefits must be filed with the Division of Workers' Compensation (Division) by the injured employee (you), or by a person acting on the injured employee's (your) behalf within one year of the injury or within one year from the date you knew or should have known the injury or disease may be work related; unless good cause exists for the failure to timely file a claim, or the employer or the employer's insurance carrier does not contest the claim.
Where do I file it?
Send the completed form by fax to 512-804-4378.
Sources
[1] Employee's Claim for Compensation for a Work-Related Injury or Occupational Disease (DWC Form-041, Rev. 03/07), Texas Department of Insurance, Division of Workers' Compensation (the Official source link on this page).
