

DWC/WCAB Form 6 at a glance
What it is: Notice and Request for Allowance of Lien, State of California Division of Workers' Compensation Workers' Compensation Appeals Board.
Who signs: Sign in (Signature of Attorney/Representative for Lien Claimant) or (Signature of Lien Claimant), and enter the Date (MM/DD/YYYY).
What to bring and attach to DWC/WCAB Form 6
Itemized statement justifying the lien must be attached.
A filled-in DWC/WCAB Form 6 example: an individual lien claimant fills in page 1

How to fill out DWC/WCAB Form 6, box by box
Date of the lien, case number and injury

Enter the Date Of Original Lien as MM/DD/YYYY and mark Original Lien or Amended Lien.
Enter the Case No.
Choose only one: a specific injury on (DATE OF INJURY: MM/DD/YYYY) or a cumulative injury which began on (START DATE: MM/DD/YYYY) and ended on (END DATE: MM/DD/YYYY).
Injured Worker
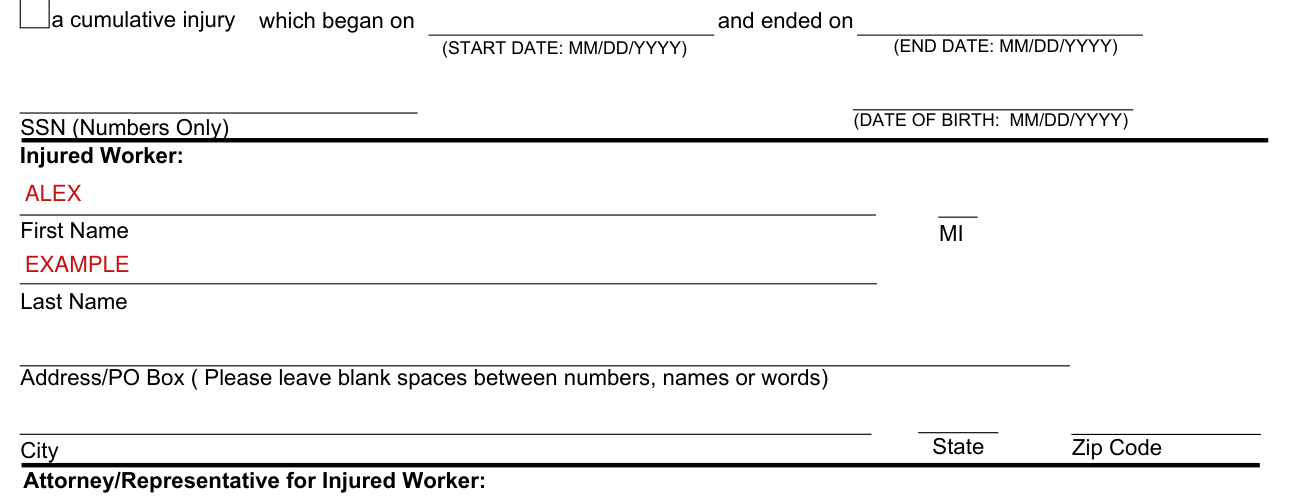
Enter the Injured Worker's (DATE OF BIRTH: MM/DD/YYYY), SSN (Numbers Only), First Name, MI and Last Name.
Enter the Address/PO Box.
Enter the City, State and Zip Code.
Attorney/Representative for Injured Worker

Under Attorney/Representative for Injured Worker, enter the Name, Address/PO Box, City, State and Zip Code.
Lien Claimant
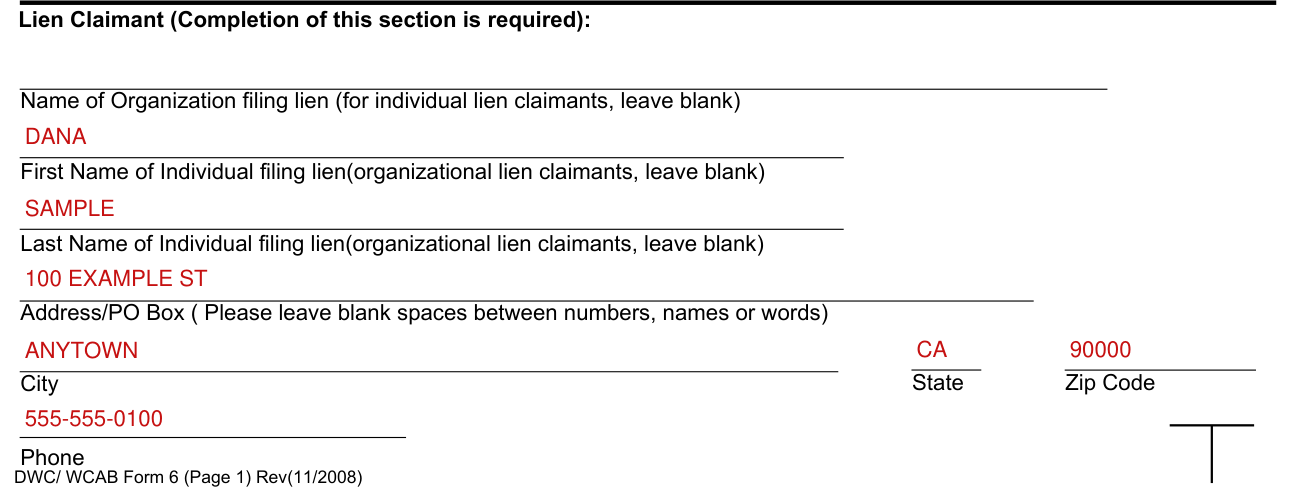
Completion of the Lien Claimant section is required.
Enter the Name of Organization filing lien; for individual lien claimants, leave blank. Enter the First Name and the Last Name of the Individual filing lien; organizational lien claimants, leave blank.
Enter the Address/PO Box, City, State, Zip Code and Phone. Please leave blank spaces between numbers, names or words.
Lien Claimant's Attorney/Representative, if any
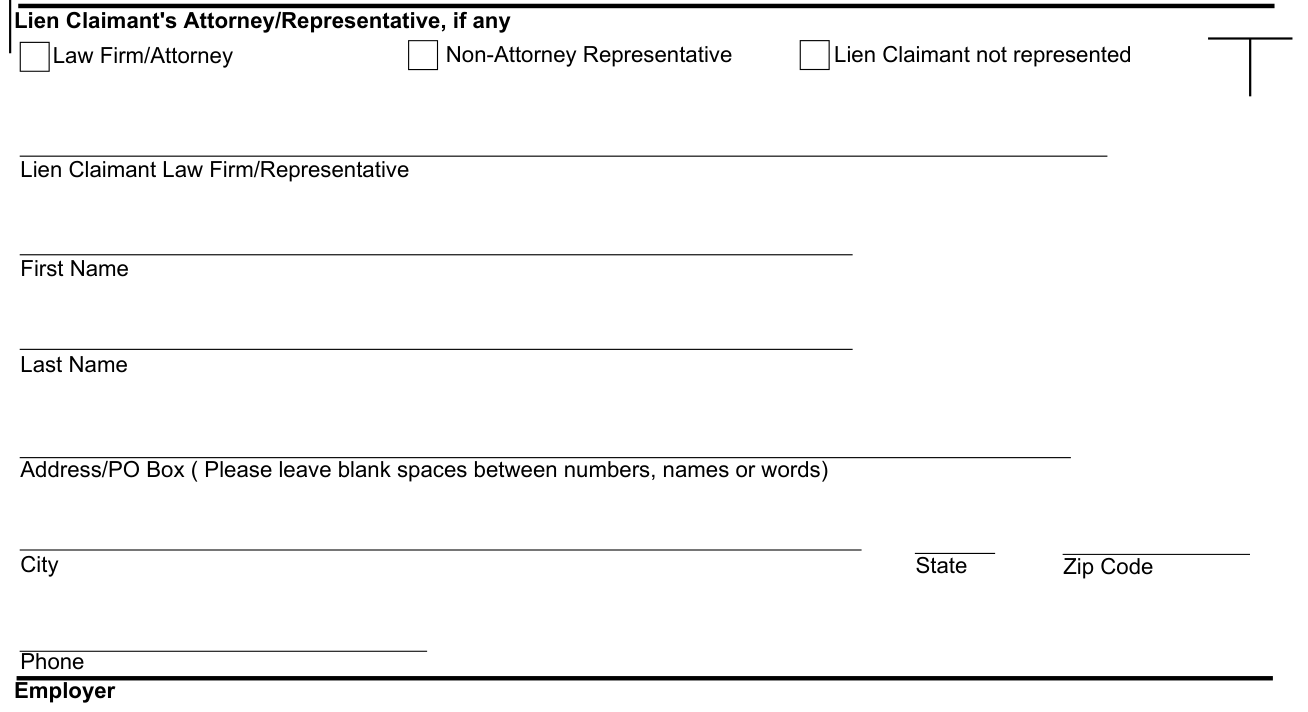
Under Lien Claimant's Attorney/Representative, if any, mark Non-Attorney Representative, Law Firm/Attorney or Lien Claimant not represented.
Enter the Lien Claimant Law Firm/Representative, First Name, Last Name, Address/PO Box, City, State, Zip Code and Phone.
Employer

Under Employer, enter the Name, Address/PO Box, City, State and Zip Code.
Insurance Carrier or Claims Administrator

Under Insurance Carrier or Claims Administrator, enter the Name, Address/PO Box, City, State and Zip Code.
Employer or Claims Administrator Attorney/Representative (if known)

Under Employer or Claims Administrator Attorney/Representative (if known), enter the Name, Address/PO Box, City, State and Zip Code.
Total Lien Amount and what the lien is for

The lien claimant requests the Workers' Compensation Appeals Board to determine and allow as a lien the sum of the Total Lien Amount against any amount now due or which may hereafter become payable as compensation to the named employee on account of the claimed injury.
This request and claim for lien is for (mark appropriate box):
A reasonable attorney's fee for legal services pertaining to any claim for compensation either before the appeals board or before any of the appellate courts, and the reasonable disbursements in connection therewith. (Labor Code § 4903 (a).)
Mark appropriate box: The reasonable expense incurred by or on behalf of the injured employee, as provided by Labor Code § 4600. (Labor Code § 4903 (b).)
Reasonable expense incurred by or on behalf of the injured employee for medical-legal expenses. (Labor Code § 4903 (b).)
The reasonable value of the living expenses of an injured employee or of his or her dependents, subsequent to the injury. (Labor Code § 4903 (c).)
The reasonable burial expenses of the deceased employee. (Labor Code § 4903 (d).)
The reasonable living expenses of the spouse or minor children of the injured employee, or both, subsequent to the date of the injury, where the employee has deserted or is neglecting his or her family. (Labor Code § 4903 (e).)
The reasonable fee for interpreter's services performed on 20 . (Labor Code § 4600 (f).)
The amount of indemnification granted by the California Victims of Crime Program. (Labor Code § 4903 (i).)
The amount of compensation, including expenses of medical treatment, and recoverable costs that have been paid by the Asbestos Workers' Account. (Labor Code § 4903 (j).)
Other Lien(s): Specify nature and statutory basis.
Signing and serving

A copy of the lien claim and supporting documents was served by mail or delivered to each of the named parties.
Sign in (Signature of Attorney/Representative for Lien Claimant) or (Signature of Lien Claimant), and enter the Date (MM/DD/YYYY).
Sources
[1] DWC/WCAB Form 6 (11/2008), Notice and Request for Allowance of Lien, State of California Division of Workers' Compensation (the Official source link on this page).
