
Form DWC073 at a glance
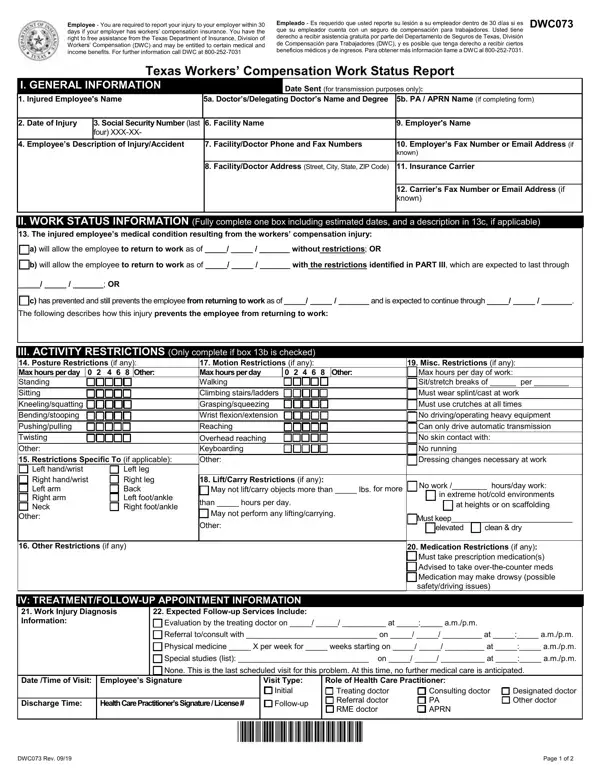
What it is: DWC073 is the Work Status Report (DWC Form-073).
Who signs: Sign on the Health Care Practitioner's Signature / License # line.
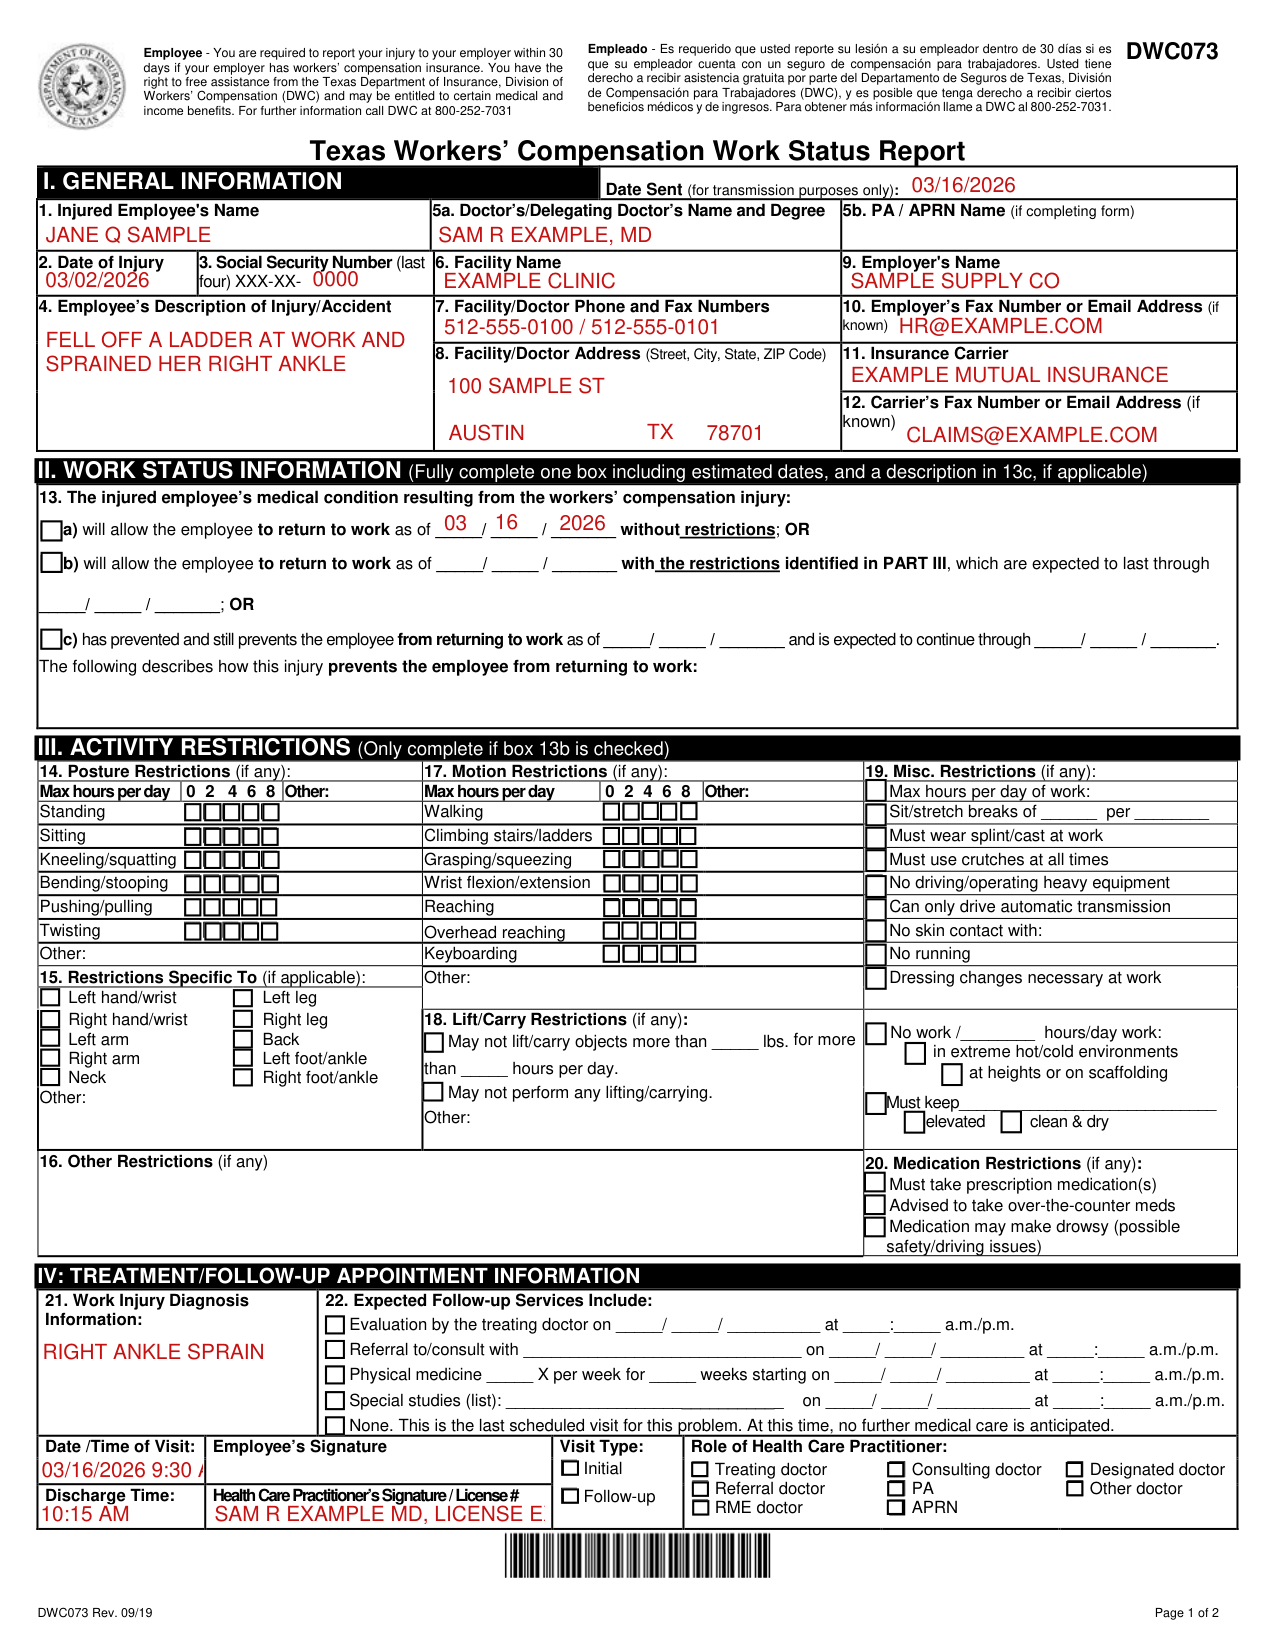
A filled-in Form DWC073 example: a treating doctor reports a return to work
How to fill out Form DWC073, box by box
I. GENERAL INFORMATION
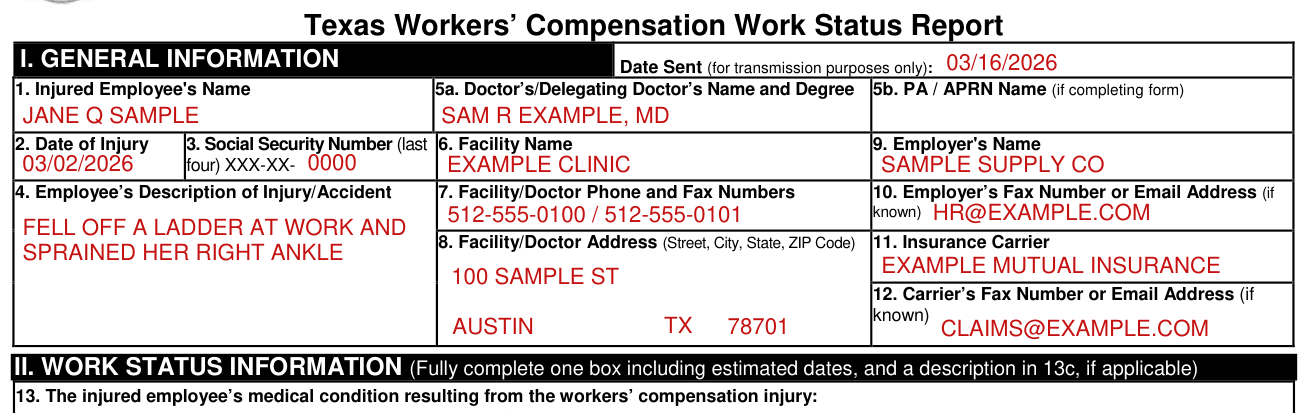
In the Texas Workers' Compensation Work Status Report I. GENERAL INFORMATION, enter the Date Sent (for transmission purposes only), the Injured Employee's Name, the Doctor's/Delegating Doctor's Name and Degree 5a, and the PA / APRN Name (if completing form) 5b.
Enter the Date of Injury and the Social Security Number (last four) after XXX-XX-.
Enter the Facility Name and the Employer's Name.
Enter the Employee's Description of Injury/Accident, the Facility/Doctor Phone and Fax Numbers, and the Employer's Fax Number or Email Address (if known).
Enter the Facility/Doctor Address (Street, City, State, ZIP Code) and the Insurance Carrier.
Enter the Carrier's Fax Number or Email Address (if known).
II. WORK STATUS INFORMATION

Fully complete one box including estimated dates, and a description in 13c, if applicable.
In box 13, check a) if the injured employee's medical condition resulting from the workers' compensation injury will allow the employee to return to work as of _____/ _____ / _______ without restrictions.
In box 13, check b) if the injured employee's medical condition resulting from the workers' compensation injury will allow the employee to return to work as of _____/ _____ / _______ with the restrictions identified in PART III, which are expected to last through _____/ _____ / _______.
In box 13, check c) if the injured employee's medical condition resulting from the workers' compensation injury has prevented and still prevents the employee from returning to work as of _____/ _____ / _______ and is expected to continue through _____/ _____ / _______.
III. ACTIVITY RESTRICTIONS
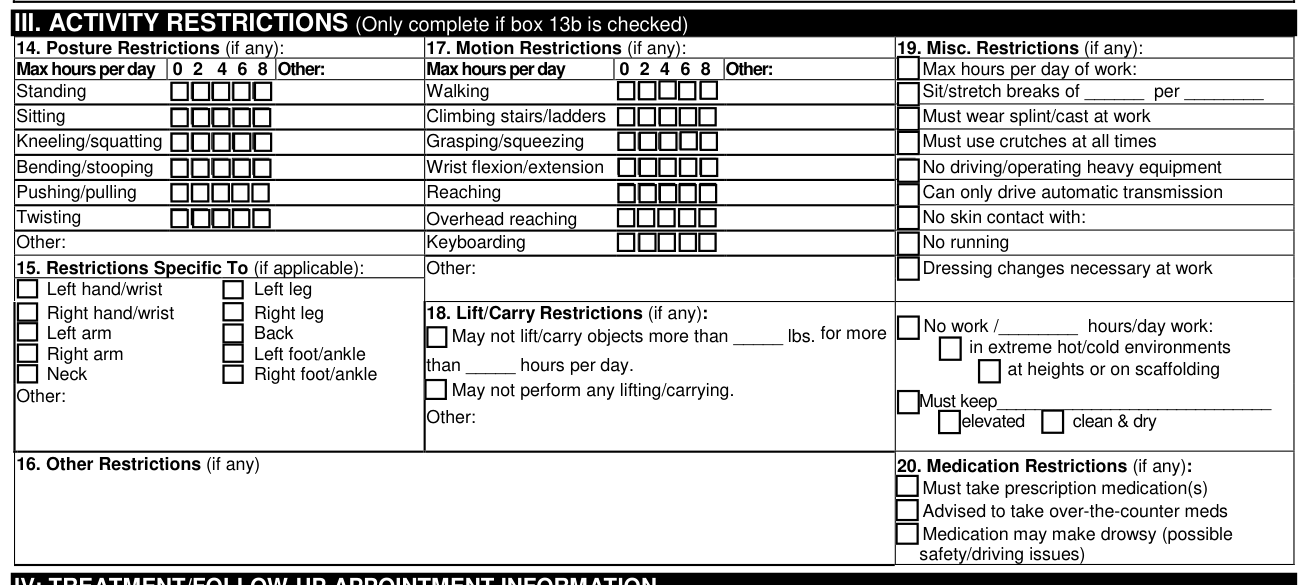
Only complete III. ACTIVITY RESTRICTIONS if box 13b is checked.
In 14. Posture Restrictions (if any), mark Max hours per day as 0, 2, 4, 6, 8 or Other: for Standing, Sitting, Kneeling/squatting, Bending/stooping, Pushing/pulling, Twisting and Other:
In 17. Motion Restrictions (if any), mark Max hours per day as 0, 2, 4, 6, 8 or Other: for Walking, Climbing stairs/ladders, Grasping/squeezing, Wrist flexion/extension, Reaching, Overhead reaching, Keyboarding and Other:
In 15. Restrictions Specific To (if applicable), mark Other:, Left hand/wrist, Left leg, Right hand/wrist, Left arm, Right arm, Neck, Right leg, Back, Left foot/ankle or Right foot/ankle.
In 18. Lift/Carry Restrictions (if any), enter May not lift/carry objects more than _____ lbs. for more than _____ hours per day, or May not perform any lifting/carrying.
In 19. Misc. Restrictions (if any), mark Max hours per day of work:, Sit/stretch breaks of ______ per ________, Must wear splint/cast at work, Must use crutches at all times, No driving/operating heavy equipment, Can only drive automatic transmission, No skin contact with:, No running, Dressing changes necessary at work, No work /________ hours/day work:, in extreme hot/cold environments, at heights or on scaffolding, or Must keep_____________________________ elevated clean & dry.
Enter Other Restrictions (if any) in box 16.
In 20. Medication Restrictions (if any), mark Must take prescription medication(s), Advised to take over-the-counter meds or Medication may make drowsy (possible safety/driving issues).
IV: TREATMENT/FOLLOW-UP APPOINTMENT INFORMATION

In IV: TREATMENT/FOLLOW-UP APPOINTMENT INFORMATION, enter the Work Injury Diagnosis Information in box 21.
In 22. Expected Follow-up Services Include:, enter Evaluation by the treating doctor on _____/ _____/ __________ at _____:_____ a.m./p.m.
Enter Referral to/consult with ______________________________ on _____/ _____/ _________ at _____:_____ a.m./p.m.
Enter Physical medicine _____ X per week for _____ weeks starting on _____/ _____/ _________ at _____:_____ a.m./p.m.
Enter Special studies (list): ______________________________ on _____/ _____/ __________ at _____:_____ a.m./p.m.
Visit Type, Role of Health Care Practitioner and Signature

In 22. Expected Follow-up Services Include:, check None if this is the last scheduled visit for this problem. At this time, no further medical care is anticipated. Enter the Date /Time of Visit and the Discharge Time, check Initial or Follow-up for Visit Type:, and sign on the Health Care Practitioner's Signature / License # line.
For Role of Health Care Practitioner, check Treating doctor, Referral doctor, RME doctor, Consulting doctor, PA, APRN, Designated doctor or Other doctor.
More rules for Form DWC073
Filing requirements for DWC Form-073 vary depending on the type of doctor filing the Work Status Report.
For complete requirements regarding the filing of this report, see 28 Texas Administrative Code §§126.6, 127.10, and 129.5. These rules are available on the TDI website at http://www.tdi.texas.gov/wc/rules/index.html.
If you have additional questions, call Comp Connection for Health Care Providers at 1-800-372-7713 (512-804-4000 in the Austin area) and select option 3.
When each type of doctor files DWC Form-073
Treating Doctor, Referral Doctor, Delegated Physician Assistant (PA) or Delegated Advanced Practice Registered Nurse (APRN)
Type of Doctor: Treating Doctor, Referral Doctor, Delegated Physician Assistant (PA) or Delegated Advanced Practice Registered Nurse (APRN). When to File DWC Form-073, Where to File, Delivery Method and Deadline.
After the initial examination of the injured employee, regardless of the employee's work status.
When there is a change in the injured employee's work status.
When there is a substantial change in the injured employee's activity restrictions.
On a schedule requested by the insurance carrier as long as it is based on the injured employee's scheduled appointments with the doctor (not to exceed one report every two weeks).
Injured employee: hand deliver; electronic transmission, with agreement (fax, email, or similar method) at the time of the examination.
Insurance carrier: electronic transmission within 2 working days of the examination.
Employer: electronic transmission unless recipient has not provided a fax number or email address; then by personal delivery or mail.
Designated doctor
After examination of an injured employee to address any question relating to return to work. The designated doctor must file a narrative report along with DWC Form-073.
Injured employee, injured employee's representative (if any) and insurance carrier: electronic transmission unless recipient has not provided a fax number or email address; then by other verifiable means within 7 working days of the examination.
Treating doctor: electronic transmission.
Division: fax to 512-490-1047.
Sources
[1] Form DWC073 (Rev. 09/19), Texas Workers' Compensation Work Status Report, Texas Department of Insurance, Division of Workers' Compensation (the Official source link on this page).