

Form FE-6 at a glance
What it is: Form FE-6 is the Claim for Death Benefits under the Federal Employees' Group Life Insurance (FEGLI) Program.
Who signs: Everyone must sign this form.
Only use this form for the death of a Federal employee, annuitant, or compensationer.
Each claimant/beneficiary is required to complete their own form.
What to bring and attach to Form FE-6
Death Certificate: a certified copy of the death certificate with the cause and manner of death.
If you are filing this claim on behalf of the estate, a copy of the appointment papers issued by the court.
If you are submitting the claim under a Power of Attorney (POA) instrument for the beneficiary, a copy of the POA papers for the beneficiary must be submitted.
A filled-in Form FE-6 example: a widow claims death benefits
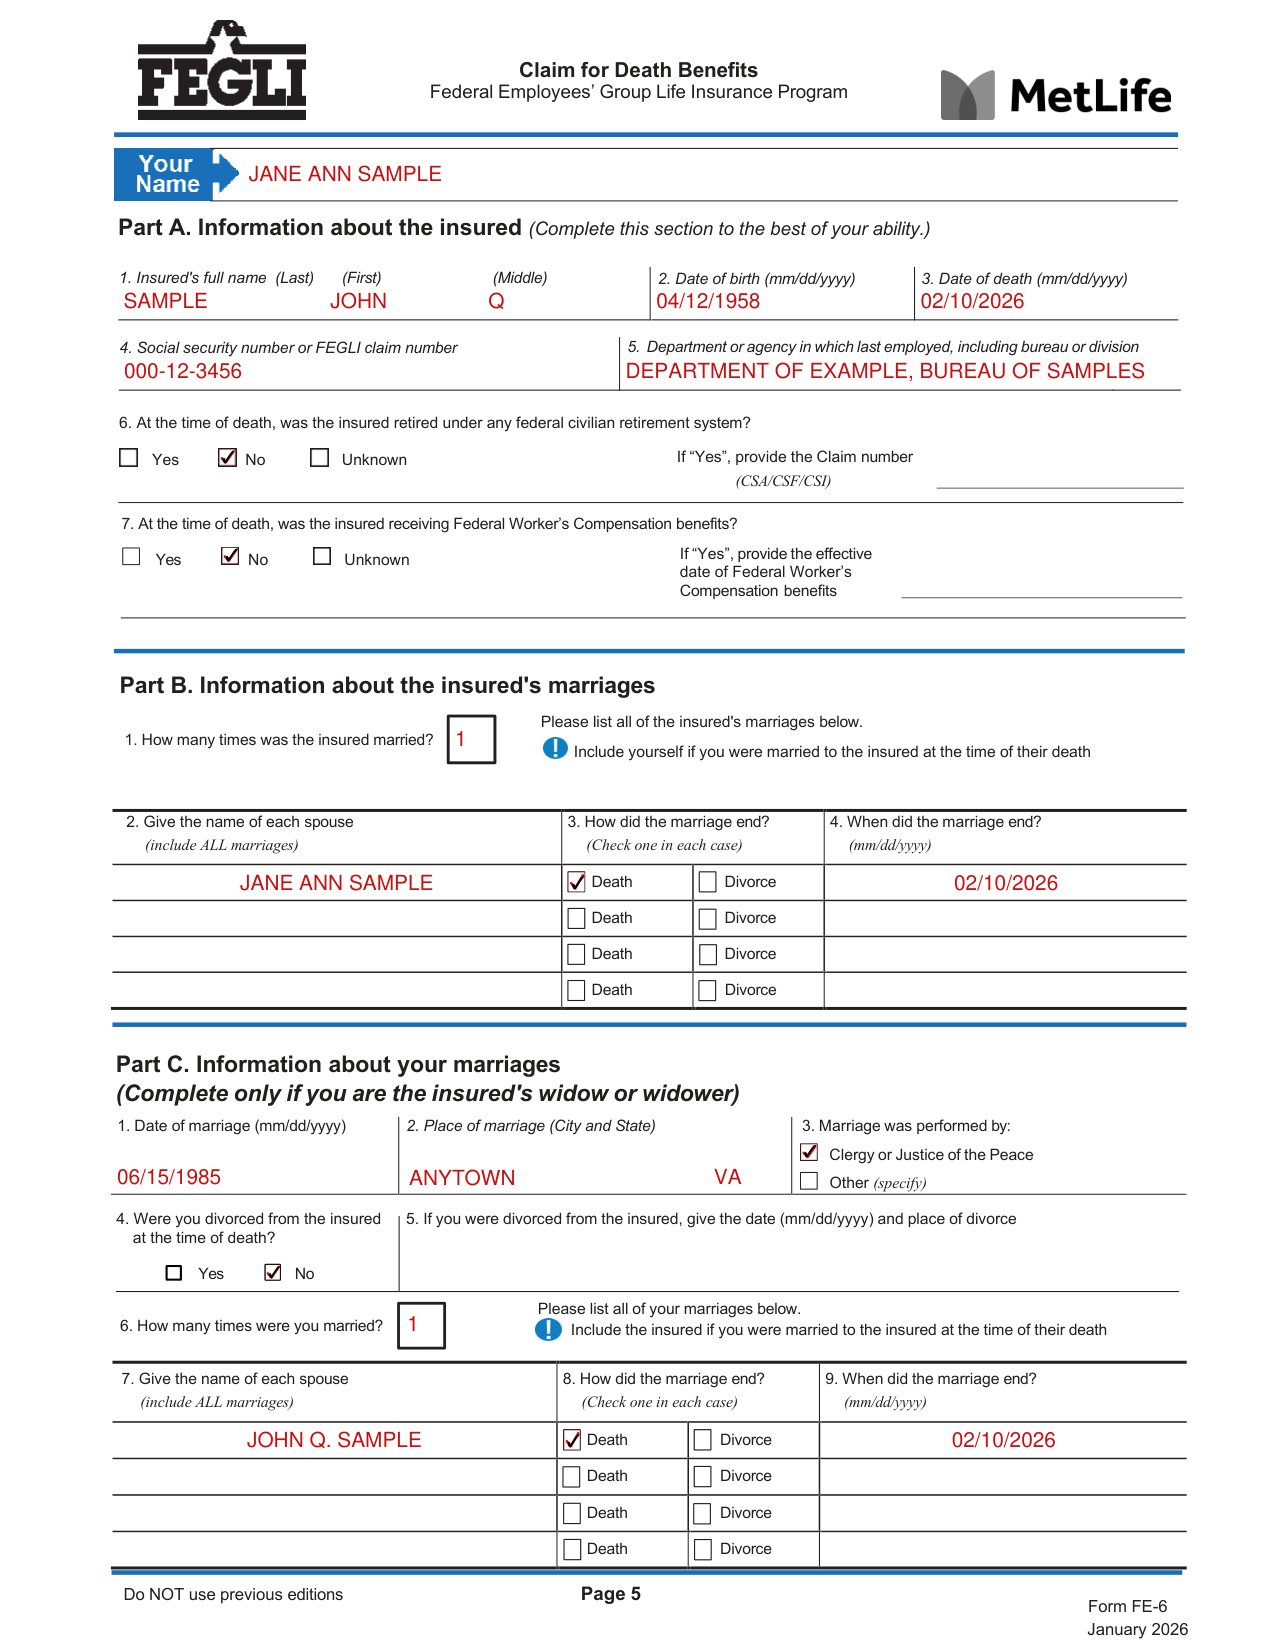
How to fill out Form FE-6, box by box
Who receives the FEGLI life insurance benefits?
If the deceased did not assign ownership and there is no valid court order on file with the employing agency or OPM (if retired), OFEGLI will pay: First, to the beneficiary(ies) the insured validly designated. Second, if none, to the insured's widow or widower. Third, if none of these, to the insured's child or children and descendants of any deceased children. Fourth, if none of these, to the insured's parents in equal shares, or the entire amount to the surviving parent. Fifth, if none of these, to the court-appointed executor or administrator of the insured's estate. Sixth, if none of these, to the insured's other next of kin, entitled under the laws of the state where the insured lived.
Part A. Information about the insured
In Part A, complete this section to the best of your ability: enter the insured's full name (Last) (First) (Middle), Date of birth (mm/dd/yyyy) and Date of death (mm/dd/yyyy).
Enter the Social security number or FEGLI claim number, and the Department or agency in which last employed, including bureau or division.
At the time of death, was the insured retired under any federal civilian retirement system? Mark Yes, No or Unknown; if Yes, provide the Claim number (CSA/CSF/CSI).
At the time of death, was the insured receiving Federal Worker's Compensation benefits? Mark Yes, No or Unknown; if Yes, provide the effective date of Federal Worker's Compensation benefits.
Part B. Information about the insured's marriages
In Part B, Information about the insured's marriages, list all of the insured's marriages: enter how many times the insured was married, and include yourself if you were married to the insured at the time of their death.
Give the name of each spouse (include ALL marriages).
How did the marriage end? Check one in each case: Death or Divorce.
When did the marriage end? Enter mm/dd/yyyy.
Part C. Information about your marriages
Part C, Information about your marriages: complete only if you are the insured's widow or widower.
Enter the Date of marriage (mm/dd/yyyy) and the Place of marriage (City and State). Marriage was performed by: mark Clergy or Justice of the Peace, or Other (specify).
Were you divorced from the insured at the time of death? Mark Yes or No.
If you were divorced from the insured, give the date (mm/dd/yyyy) and place of divorce.
List all of your marriages: enter how many times you were married, and include the insured if you were married to the insured at the time of their death.
Enter each spouse's name (include ALL marriages). How did the marriage end? Check one in each case: Death or Divorce. When did the marriage end? Enter mm/dd/yyyy.
Part D. Information about the insured's next of kin
Everyone must complete Part D unless you are the insured's widow or widower. Did the insured have any living children on the date of their death? Mark Yes or No; if Yes, enter how many.
List the insured's living children; step-children are not eligible. If the insured has no children, list the insured's parents; if one or both parents died before the insured, provide their name(s) and date(s) of death.
If the insured has no children, and both parents died before the insured, list the next of kin who may be capable of inheriting from the insured (brothers, sisters, descendants of deceased brothers, sisters, etc.).
Part E. Information about the insured's estate
Part E, Information about the insured's estate: complete if the insured's estate is entitled. Has a court issued, or is it expected to issue, a document appointing an executor or administrator of the decedent's estate? Mark Yes or No.
If yes, give their name and address and attach a copy of the court appointment papers.
Part F. Additional information
Part F, Additional information: have you signed a document with a funeral home that authorizes a payment directly to them? Mark Yes or No; if yes, please send a copy of the document with this claim form.
Are you claiming accidental death benefits (did the insured die solely through violent, external, and accidental means)? Mark Yes or No.
If Yes, submit coroner's and police reports, news clippings, and any other available reports concerning the accident.
OFEGLI cannot consider a claim for such benefits if the insured separated or retired before the accident.
Part G: How you will receive your payment
In Part G, the payment method for your claim will be through the establishment of a Total Control Account (TCA).
If you do not want to receive your payment in the form of a TCA, you may request a check as an alternative to TCA by writing "check" beneath "Your Signature" on the enclosed claim form.
Part H - Information about you
In Part H, everyone must complete and sign: enter your Name (please print), Relationship to the insured, Date of birth, Address (number, street, apartment number), City, State, Zip, Phone number and Social security number.
Mark either Social security number or Estate/Trust/Tax ID#.
Signing the form
Enter Today's Date and Your Signature.
Everyone must sign this form. If you are completing this claim form for someone else as a Power of Attorney or Guardian, sign your name "on behalf of" that person.
By signing this claim form, you certify that: all the information you have given is true and complete to the best of your knowledge.
If you knowingly and willfully make any materially false, fictitious, or fraudulent statement or representation on this form, or conceal a material fact related to the requests for information on this form, you may be subject to a monetary fine or imprisonment for not more than five years, or both under 18 U.S.C. § 1001.
Submission instructions
Return this claim form and the necessary documents to the Standard Mailing Address: OFEGLI PO Box 6080 Scranton, PA 18505-6080, or to the Overnight Address: OFEGLI 10 Ed Preate Drive Moosic, PA 18507. If a certified death certificate has already been submitted, you may fax your claim form to OFEGLI at: 570-558-8659.
Please return pages 5 through 8 to OFEGLI.
If your situation is different
You are filing a claim for a dependent
If you are filing a claim for a dependent, use form FE-6 DEP.
Common questions about Form FE-6
How do I notify the OPM of death?
If you have not previously notified the employing agency or OPM (if retired) of the death, please contact the appropriate office. The easiest way to report the death of a Federal retiree is online at www.opm.gov/reportdeath, or you can report the death by calling OPM at 1-888-767-6738.
Does it need a notary?
If a trust is designated, a notarized statement that the trust is still in effect and you are authorized to act under the trust, and a copy of the trust document. If you are not the original trustee, a copy of the page naming you as successor trustee.
Where to get help with Form FE-6
If you have questions, or need help completing this form, call OFEGLI at 1-800-633-4542, Monday - Friday, from 8:30 a.m. to 4:00 p.m. ET.
Sources
[1] Form FE-6 (01/26), Claim for Death Benefits, Federal Employees' Group Life Insurance (FEGLI) Program (the Official source link on this page).
