

Form EL2 at a glance
What it is: The EL2 is the Preparticipation Physical Evaluation: a Medical History Form, a Physical Examination Form and a Medical Eligibility Form.
Who signs: Student-Athlete Name (printed), Student-Athlete Signature and Date. Parent/Guardian Name (printed), Parent/Guardian Signature and Date. Signature of Student and Date, Signature of Parent/Guardian and Date. Name of Healthcare Professional (print or type), Date of Exam, Address, Phone, E-mail, Signature of Healthcare Professional, Credentials, License #. Name of Healthcare Professional, Date of Exam, Address, Phone, Signature of Healthcare Professional, Credentials, License #.
Florida Statute 1006.20 requires a student candidate for an interscholastic athletic team to successfully complete a preparticipation physical evaluation as the first step of injury prevention.
A filled-in Form EL2 example: a student athlete completes page 1
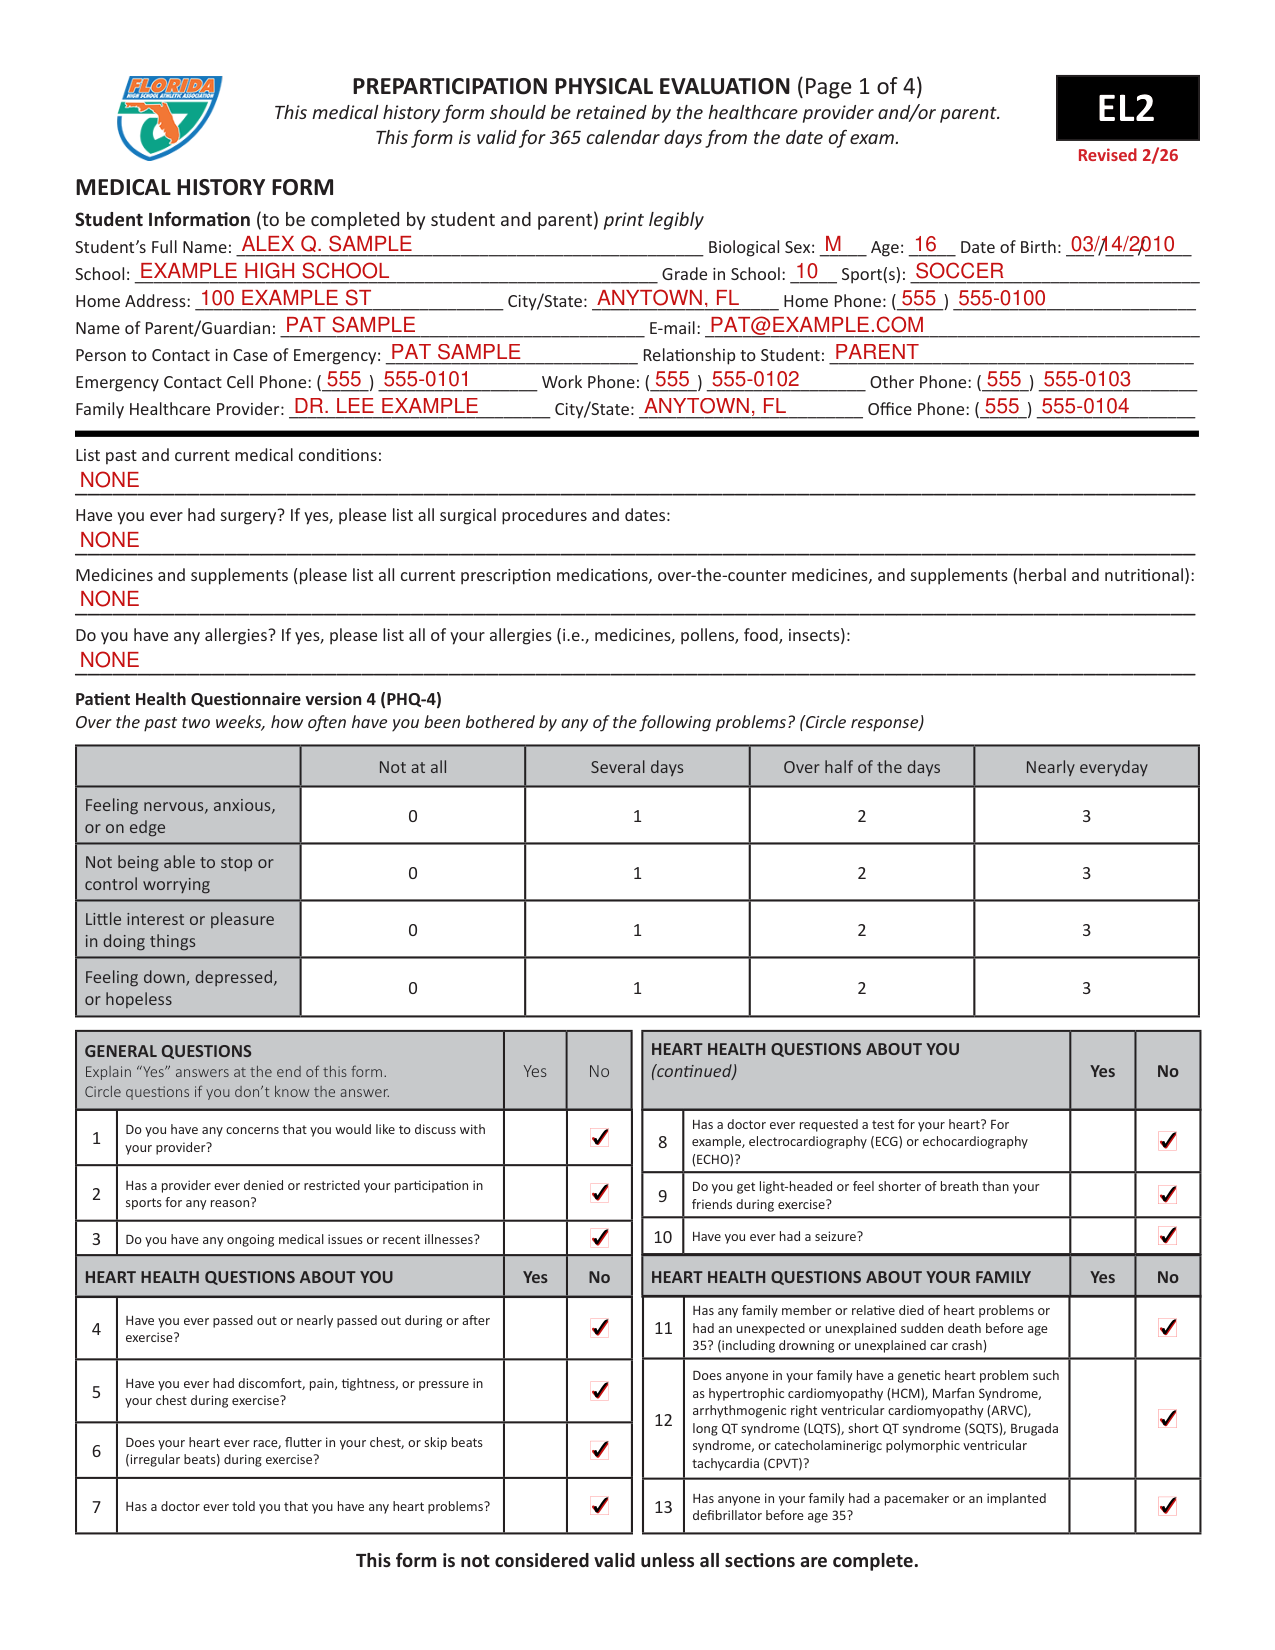
How to fill out Form EL2, box by box
Student Information
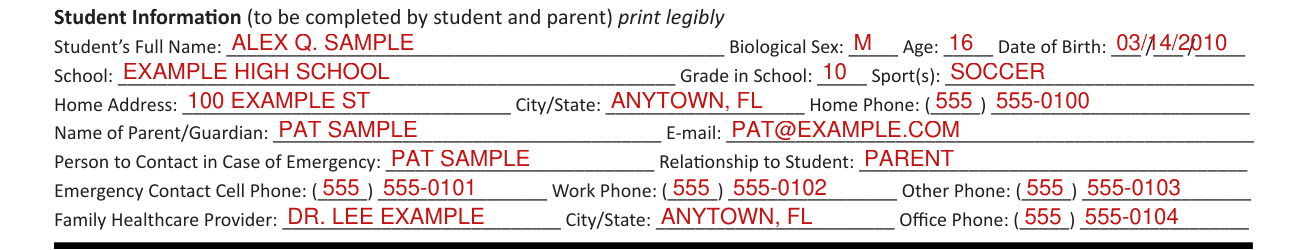
Student Information is to be completed by student and parent; print legibly: Student's Full Name, Biological Sex, Age, Date of Birth, School, Grade in School, Sport(s), Home Address, City/State, Home Phone, Name of Parent/Guardian, E-mail, Person to Contact in Case of Emergency, Relationship to Student, Emergency Contact Cell Phone, Work Phone, Other Phone, Family Healthcare Provider, City/State, Office Phone.
Medical conditions, surgery, medicines and allergies
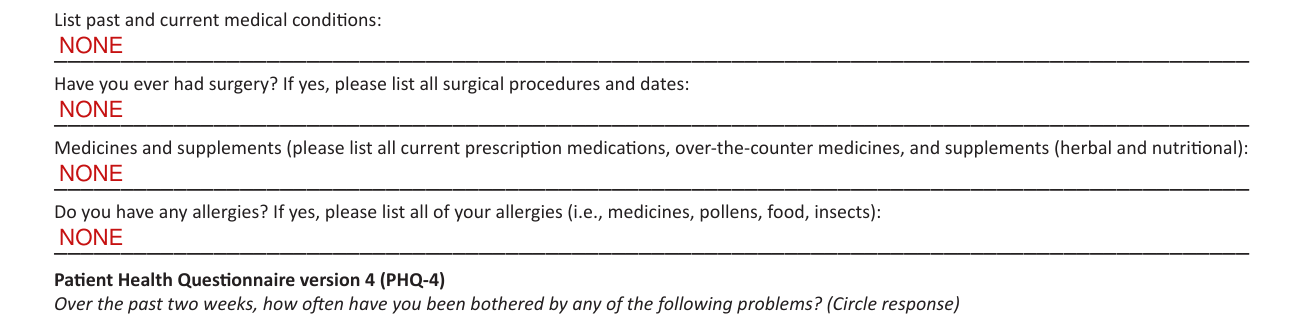
List past and current medical conditions.
Have you ever had surgery? If yes, please list all surgical procedures and dates.
Medicines and supplements: please list all current prescription medications, over-the-counter medicines, and supplements (herbal and nutritional).
Do you have any allergies? If yes, please list all of your allergies (i.e., medicines, pollens, food, insects).
General questions and heart health questions
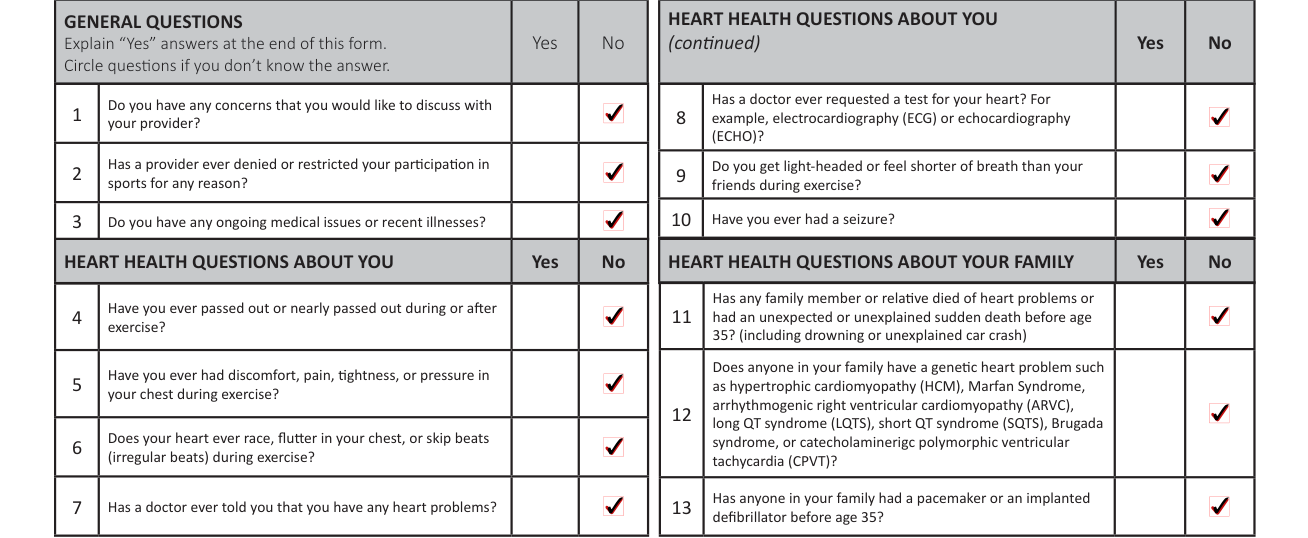
General questions, Yes No. Explain “Yes” answers at the end of this form. Circle questions if you don't know the answer. 1 Do you have any concerns that you would like to discuss with your provider? 2 Has a provider ever denied or restricted your participation in sports for any reason? 3 Do you have any ongoing medical issues or recent illnesses?
Heart health questions about you, Yes No: 4 Have you ever passed out or nearly passed out during or after exercise? 5 Have you ever had discomfort, pain, tightness, or pressure in your chest during exercise? 6 Does your heart ever race, flutter in your chest, or skip beats (irregular beats) during exercise? 7 Has a doctor ever told you that you have any heart problems? 8 Has a doctor ever requested a test for your heart? For example, electrocardiography (ECG) or echocardiography (ECHO)? 9 Do you get light-headed or feel shorter of breath than your friends during exercise? 10 Have you ever had a seizure?
Heart health questions about your family, Yes No: 11 Has any family member or relative died of heart problems or had an unexpected or unexplained sudden death before age 35? (including drowning or unexplained car crash) 12 Does anyone in your family have a genetic heart problem such as hypertrophic cardiomyopathy (HCM), Marfan Syndrome, arrhythmogenic right ventricular cardiomyopathy (ARVC), long QT syndrome (LQTS), short QT syndrome (SQTS), Brugada syndrome, or catecholaminerigc polymorphic ventricular tachycardia (CPVT)? 13 Has anyone in your family had a pacemaker or an implanted defibrillator before age 35?
Bone and joint questions
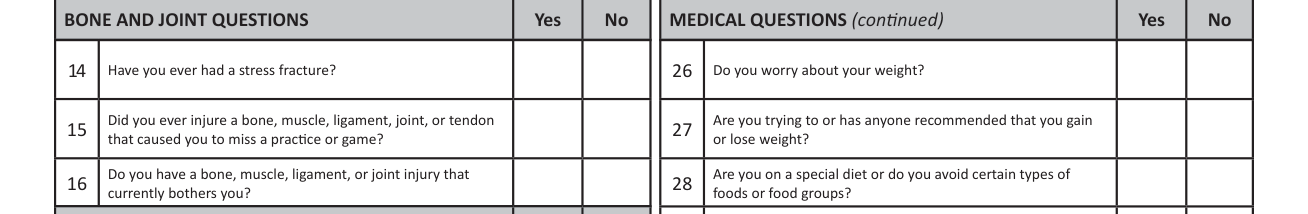
Bone and joint questions, Yes No: 14 Have you ever had a stress fracture? 15 Did you ever injure a bone, muscle, ligament, joint, or tendon that caused you to miss a practice or game? 16 Do you have a bone, muscle, ligament, or joint injury that currently bothers you?
Medical questions
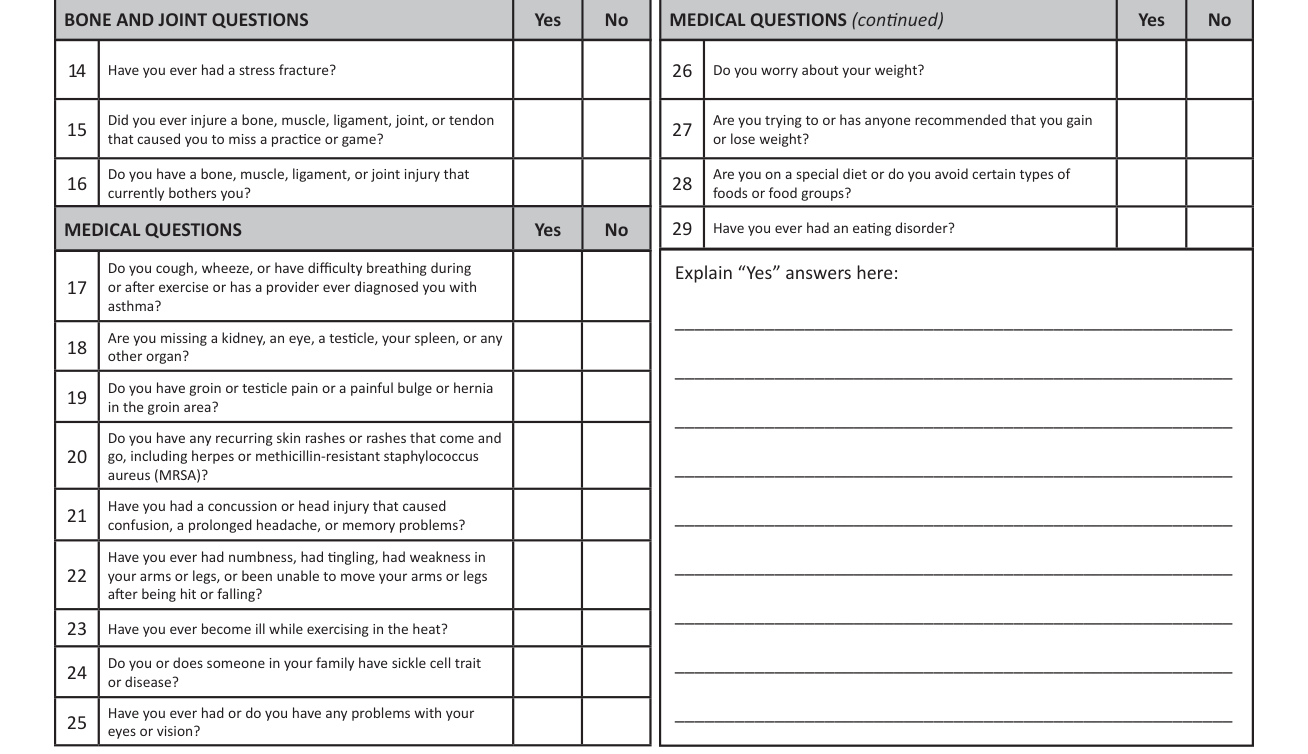
17 Do you cough, wheeze, or have difficulty breathing during or after exercise or has a provider ever diagnosed you with asthma? 18 Are you missing a kidney, an eye, a testicle, your spleen, or any other organ? 19 Do you have groin or testicle pain or a painful bulge or hernia in the groin area? 20 Do you have any recurring skin rashes or rashes that come and go, including herpes or methicillin-resistant staphylococcus aureus (MRSA)? 21 Have you had a concussion or head injury that caused confusion, a prolonged headache, or memory problems? 22 Have you ever had numbness, had tingling, had weakness in your arms or legs, or been unable to move your arms or legs after being hit or falling? 23 Have you ever become ill while exercising in the heat? 24 Do you or does someone in your family have sickle cell trait or disease? 25 Have you ever had or do you have any problems with your eyes or vision?
26 Do you worry about your weight? 27 Are you trying to or has anyone recommended that you gain or lose weight? 28 Are you on a special diet or do you avoid certain types of foods or food groups? 29 Have you ever had an eating disorder? Yes No
Explain “Yes” answers here
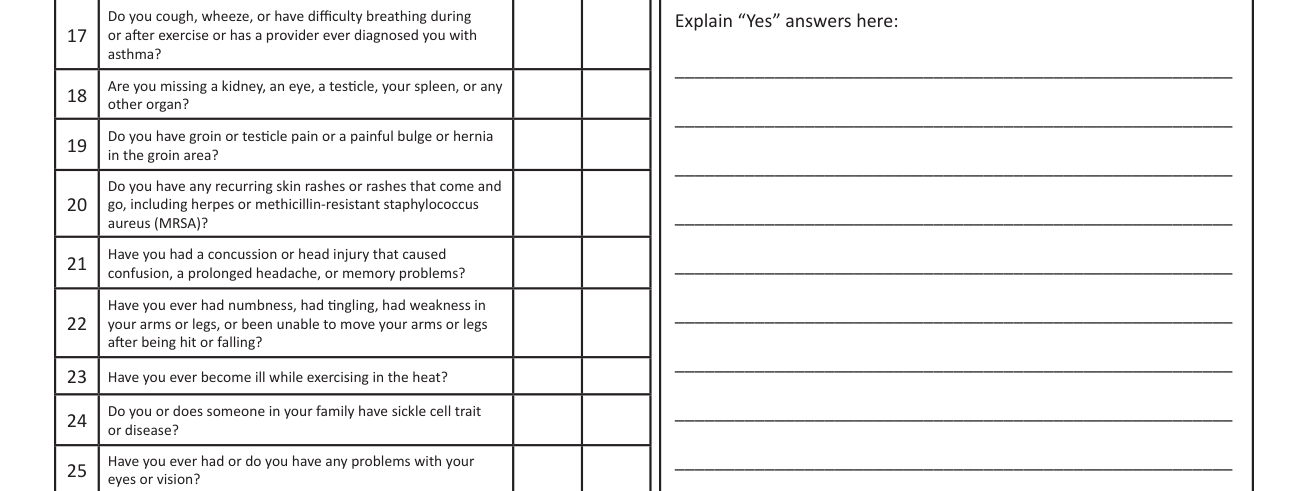
Explain your “Yes” answers here.
Student-Athlete Signature and Parent/Guardian Signature

Student-Athlete Name (printed), Student-Athlete Signature and Date. Parent/Guardian Name (printed), Parent/Guardian Signature and Date.
Name of Healthcare Professional

Name of Healthcare Professional (print or type), Date of Exam, Address, Phone, E-mail, Signature of Healthcare Professional, Credentials, License #.
Shared emergency information
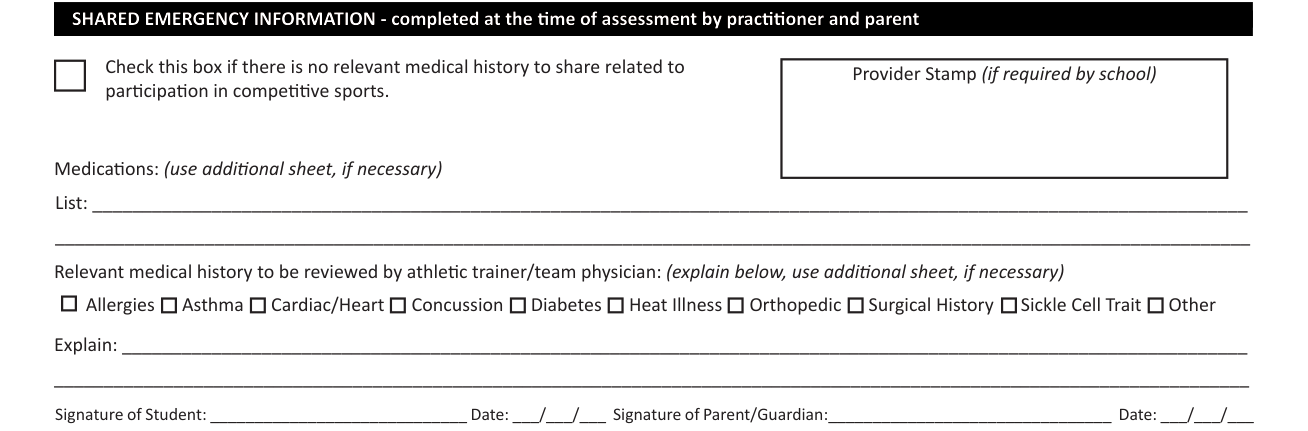
SHARED EMERGENCY INFORMATION - completed at the time of assessment by practitioner and parent Check this box if there is no relevant medical history to share related to participation in competitive sports. Provider Stamp (if required by school).
Medications: (use additional sheet, if necessary) List:
Relevant medical history to be reviewed by athletic trainer/team physician: (explain, use additional sheet, if necessary) Allergies, Asthma, Cardiac/Heart, Concussion, Diabetes, Heat Illness, Orthopedic, Surgical History, Sickle Cell Trait, Other. Explain:
Signature of Student and Signature of Parent/Guardian

Signature of Student and Date, Signature of Parent/Guardian and Date.
Medical eligibility

Medically eligible for all sports without restriction. Medically eligible for all sports without restriction after clearance by medical specialist for: (If this option is checked, additional medical follow-up and clearance prior to sports participation is required. Use Form EL1/2S for documentation.) Medically eligible for only certain sports. Not medically eligible for any sports. Recommendations: (use additional sheet, if necessary)
Name of Healthcare Professional on page 4

Name of Healthcare Professional, Date of Exam, Address, Phone, Signature of Healthcare Professional, Credentials, License #.
More rules for Form EL2
This form is not considered valid unless all sections are complete.
This medical history form should be retained by the healthcare provider and/or parent.
Patient Health Questionnaire version 4 (PHQ-4): Over the past two weeks, how often have you been bothered by any of the following problems? (Circle response) Not at all, Several days, Over half of the days, Nearly everyday.
Feeling nervous, anxious, or on edge 0 1 2 3. Not being able to stop or control worrying 0 1 2 3. Little interest or pleasure in doing things 0 1 2 3. Feeling down, depressed, or hopeless 0 1 2 3.
Common questions about Form EL2
Is there a deadline?
This preparticipation physical evaluation shall be completed each year before participating in interscholastic athletic competition or engaging in any practice, tryout, workout, conditioning, or other physical activity, including activities that occur outside of the school year.
Where do I file it?
Submit this Medical Eligibility Form to the school. This form is valid for 365 calendar days from the date of exam.
Sources
[1] Form EL2 (Revised 2/26), FHSAA (the Official source link on this page).
