

Form DH-MQA 1094 at a glance
What it is: DH-MQA 1094 is the Nursing Licensure by Examination Application of the Board of Nursing.
Where and when to file: Board of Nursing, P.O. Box 6330, Tallahassee, FL 32314-6330. Website: floridasnursing.gov. Email: mqa.nursingappstatus@flhealth.gov. Phone: 850-245-4125. Fax: 850-617-6460.
All applicants applying for the NCLEX examination through Florida for the first time are considered initial applicants, regardless of whether you have previously taken the exam in a different state. If you are a first-time examination taker in Florida, this is the correct application for you to complete.
Graduates from: Florida approved nursing education programs as defined in section 464.003, Florida Statutes. ACEN or CCNE accredited nursing programs that have been issued an NCLEX code by the NCSBN. Nursing education programs that have been approved or recognized by the jurisdiction in which it is based and that has been issued an NCLEX code by NCSBN. Military nursing programs that have been issued an NCLEX code by NCSBN. Generic Master of Science in Nursing (MSN) or higher programs that have been issued an NCLEX code by NCSBN. A non-NCSBN jurisdiction or international education program that the Board of Nursing determines is equivalent to an approved program. Practical Nurse examination based on practical nurse equivalency (PNEQ): applicants who have successfully completed courses equivalent to practical nursing education in a registered nursing program (see Nursing Education History, Section 7 in the application for more information).
A filled-in Form DH-MQA 1094 example: an RN examination applicant

How to fill out Form DH-MQA 1094, box by box
Application type and NCLEX
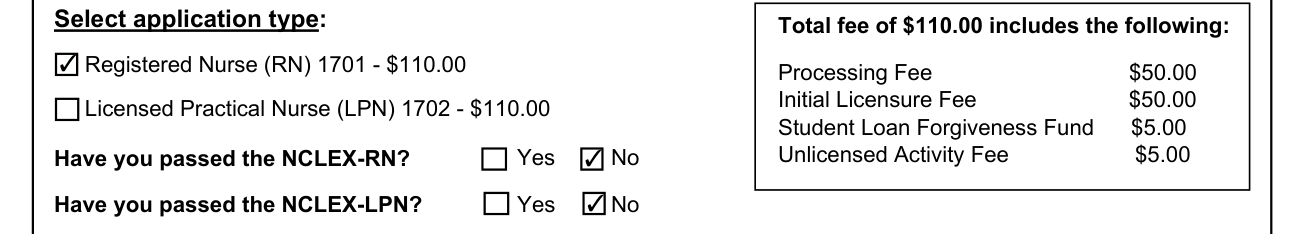
Select application type: Registered Nurse (RN) 1701, $110.00, or Licensed Practical Nurse (LPN) 1702, $110.00 (checked October 19, 2026).
Check Yes or No for Have you passed the NCLEX-RN? and for Have you passed the NCLEX-LPN?
Name, date of birth and mailing address
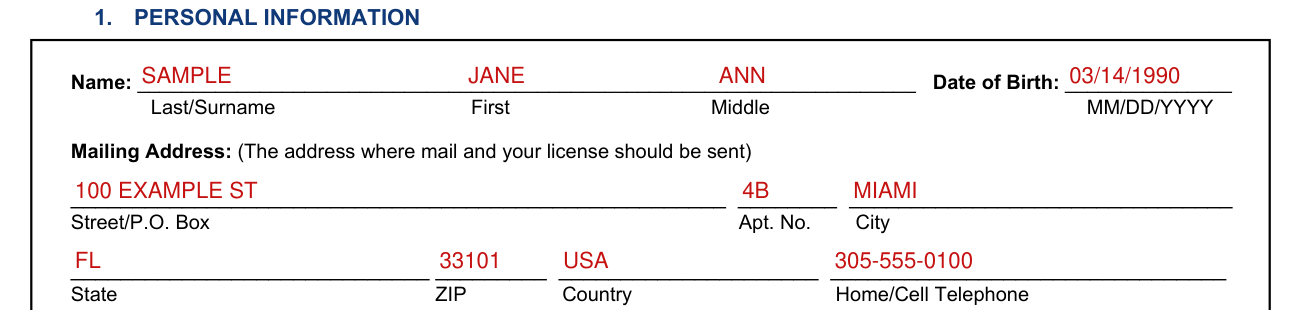
Enter your Name (Last/Surname, First, Middle) and Date of Birth (MM/DD/YYYY).
Enter your Mailing Address, the address where mail and your license should be sent: Street/P.O. Box, Apt. No., City, State, ZIP, Country and Home/Cell Telephone.
Physical location

Physical Location is required if your mailing address is a P.O. Box. The Physical Location address will be posted on the Department of Health's website. Enter Street, Apt. No., City, State, ZIP, Country and Work/Cell Telephone.
Equal opportunity data and email notification
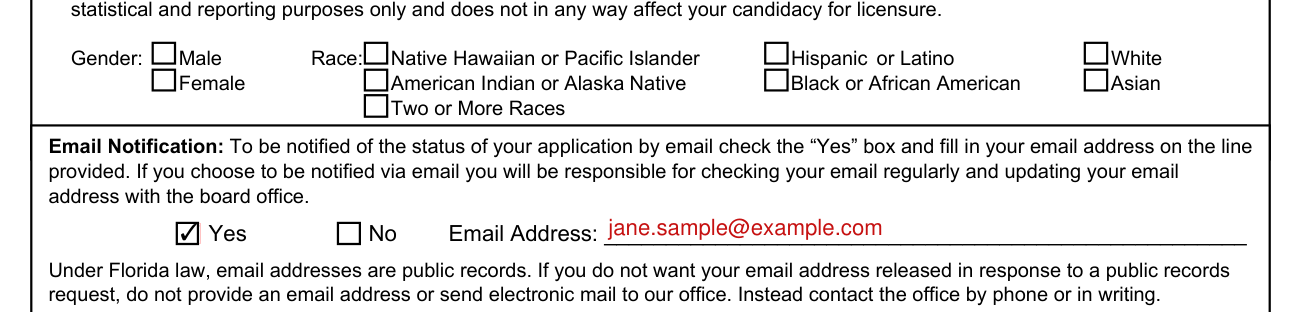
Equal Opportunity Data is gathered for statistical and reporting purposes only and does not in any way affect your candidacy for licensure.
To be notified of the status of your application by email, check the Yes box and fill in your email address.
Under Florida law, email addresses are public records. If you do not want your email address released in response to a public records request, do not provide an email address.
Pearson VUE registration
In addition to applying for licensure with the board, all applicants must register with Pearson VUE and pay the fee. All fees paid to Pearson VUE are nonrefundable.
The first and last name listed on your application and provided to Pearson VUE must match the identification that you intend to provide on the day of your examination.
Nurse Licensure Compact
If your declared primary state of residence is another Compact state and you are not changing your primary residence to Florida, you are not eligible for a multistate license in Florida and should not submit this application, as your NLC license allows you to practice in Florida.
Education history
List the nursing school(s) you attended. For Graduation Date, enter the graduation date or anticipated graduation date.
Official transcripts must be mailed directly from the education program to the Board of Nursing, 4052 Bald Cypress Way, Bin C-02, Tallahassee, FL 32399-3252. Only applicants who are graduating from a United States school outside of Florida should use the Transcript Request form.
Health history
Failure to disclose information in this section may result in denial of your application. Check Yes or No for each of A to F about the last two years (a diagnosed physical or mental disorder), the last five years (a diagnosed substance-related (alcohol or drug) disorder or a treatment or recovery program, and if you were previously in such a program, a relapse) and a current participant in an alternative to discipline program.
For each question, check Yes or No. If a Yes response was provided to any of the questions in this section, provide directly to the board office: (a) a letter from a Licensed Health Care Practitioner that explains the impact the condition may have on the ability to practice the profession with reasonable skill and safety; (b) a written self-explanation, identifying the medical condition(s) or occurrence(s); and current status.
Discipline history
If you responded Yes to any questions in this section, you must provide: (a) a written self-explanation, describing in detail the circumstances surrounding the disciplinary action; (b) a copy of the Administrative Complaint and Final Order; (c) three current (written in the last year) professional Letters of Recommendation.
Criminal history
For the question in Section 11 (Criminal History), you must include all misdemeanors and felonies, even if adjudication was withheld. Reckless driving, driving while license suspended or revoked (DWLSR), driving under the influence (DUI) or driving while impaired (DWI) are not minor traffic offenses.
Pursuant to section 943.0585(6)(b), Florida Statutes, and section 943.059(6)(b), Florida Statutes, an applicant seeking to be licensed by the Department of Health must disclose expunged and sealed criminal history records.
If you responded Yes in this section, you must provide: (a) Self-Explanation, describing in detail the circumstances surrounding each offense; including date, city and state, charges, and final results; (b) Final Dispositions and Arrest Records for all offenses.
Medicaid and Medicare fraud questions
Check Yes or No for each of 1 to 5. If you responded No to the question above it in Section 12, skip to question 2 after 1, question 3 after 2, question 4 after 3 and question 5 after 4. Question 1: a felony under Chapter 409, 817 or 893, Florida Statutes, or a similar felony offense(s) in another state or jurisdiction. Question 2: a felony under 21 U.S.C. ss. 801-970 or 42 U.S.C. ss. 1395-1396. Question 3: termination for cause from the Florida Medicaid Program pursuant to section 409.913, Florida Statutes. Question 4: termination for cause from any other state Medicaid program. Question 5: listing on the LEIE.
For each question, check Yes or No. If you responded Yes to any of the questions in this section, you must provide (a) a written explanation for each question including the county and state of each termination or conviction, date of each termination or conviction, and copies of supporting documentation. You must also provide (b) supporting documentation including court dispositions or agency orders where applicable.
Livescan and electronic fingerprinting
Livescan Privacy Statement: check the box to confirm that you have been provided and read the statement from the Florida Department of Law Enforcement and the Privacy Statement document from the Federal Bureau of Investigation. The board will not receive your Livescan results if you do not confirm the statement by checking the box.
Electronic Fingerprinting is required for ALL applicants, including out-of-state applicants. The board cannot accept hard fingerprint cards or results; all results must be submitted electronically by the Livescan service provider. The Department of Health accepts electronic fingerprinting offered by Livescan service providers that are approved by the Florida Department of Law Enforcement; for a list of approved vendors, visit FLHealthSource.gov/Background-Screening.
The ORI number for the Board of Nursing is EDOH4420Z. If you do not provide the correct Originating Agency Identification (ORI) number to the Livescan service provider, the board office will not receive your background screening results.
Applicant signature
Sign on the Applicant Signature line and enter the Date (MM/DD/YYYY). You may print this application and sign it or sign digitally.
Florida law requires the applicant to immediately inform the board of any material change in any circumstances or condition stated in the application which takes place between the initial filing and the final granting or denial of the license.
If your situation is different
Taken the examination for Florida previously
If you have taken the examination for Florida previously you will need to apply for re-examination. To locate the re-examination application visit FloridasNursing.gov/Applications/LPN-RN-Re-Exam-App.pdf.
Common questions about Form DH-MQA 1094
Is there a deadline?
An incomplete application shall expire one year after the initial filing with the department (section 456.013(1)(a), Florida Statutes).
Where do I file it?
Board of Nursing, P.O. Box 6330, Tallahassee, FL 32314-6330. Website: floridasnursing.gov. Email: mqa.nursingappstatus@flhealth.gov. Phone: 850-245-4125. Fax: 850-617-6460.
Are there fees?
Fees must be paid in the form of a cashier's check or money order, made payable to the Department of Health.
Is there a penalty?
Providing false information may result in disciplinary action pursuant to section 456.072, Florida Statutes, or criminal penalties pursuant to section 456.067, Florida Statutes.
Sources
[1] Form DH-MQA 1094 (Revised 6/2026), Nursing Licensure by Examination Application, Florida Board of Nursing (the Official source link on this page).
