


Form DHS 1147 at a glance
What it is: Form DHS 1147 is the State of Hawaii Level of Care (LOC) and At Risk Evaluation of the Department of Human Services Med-QUEST Division.
Who signs: Sign under "I have reviewed and agree with this assessment". The form prints "Hard copy signature on file" next to the SIGNATURE line.
What to bring and attach to Form DHS 1147
Under XIX MEDICATIONS/TREATMENTS, list all significant medications, dosage, frequency and mode. Attach an additional sheet if necessary.
Check Yes or No for Restorative Therapy. Check the therapy (PT, OT or Speech) and submit or attach the evaluation and treatment plan.
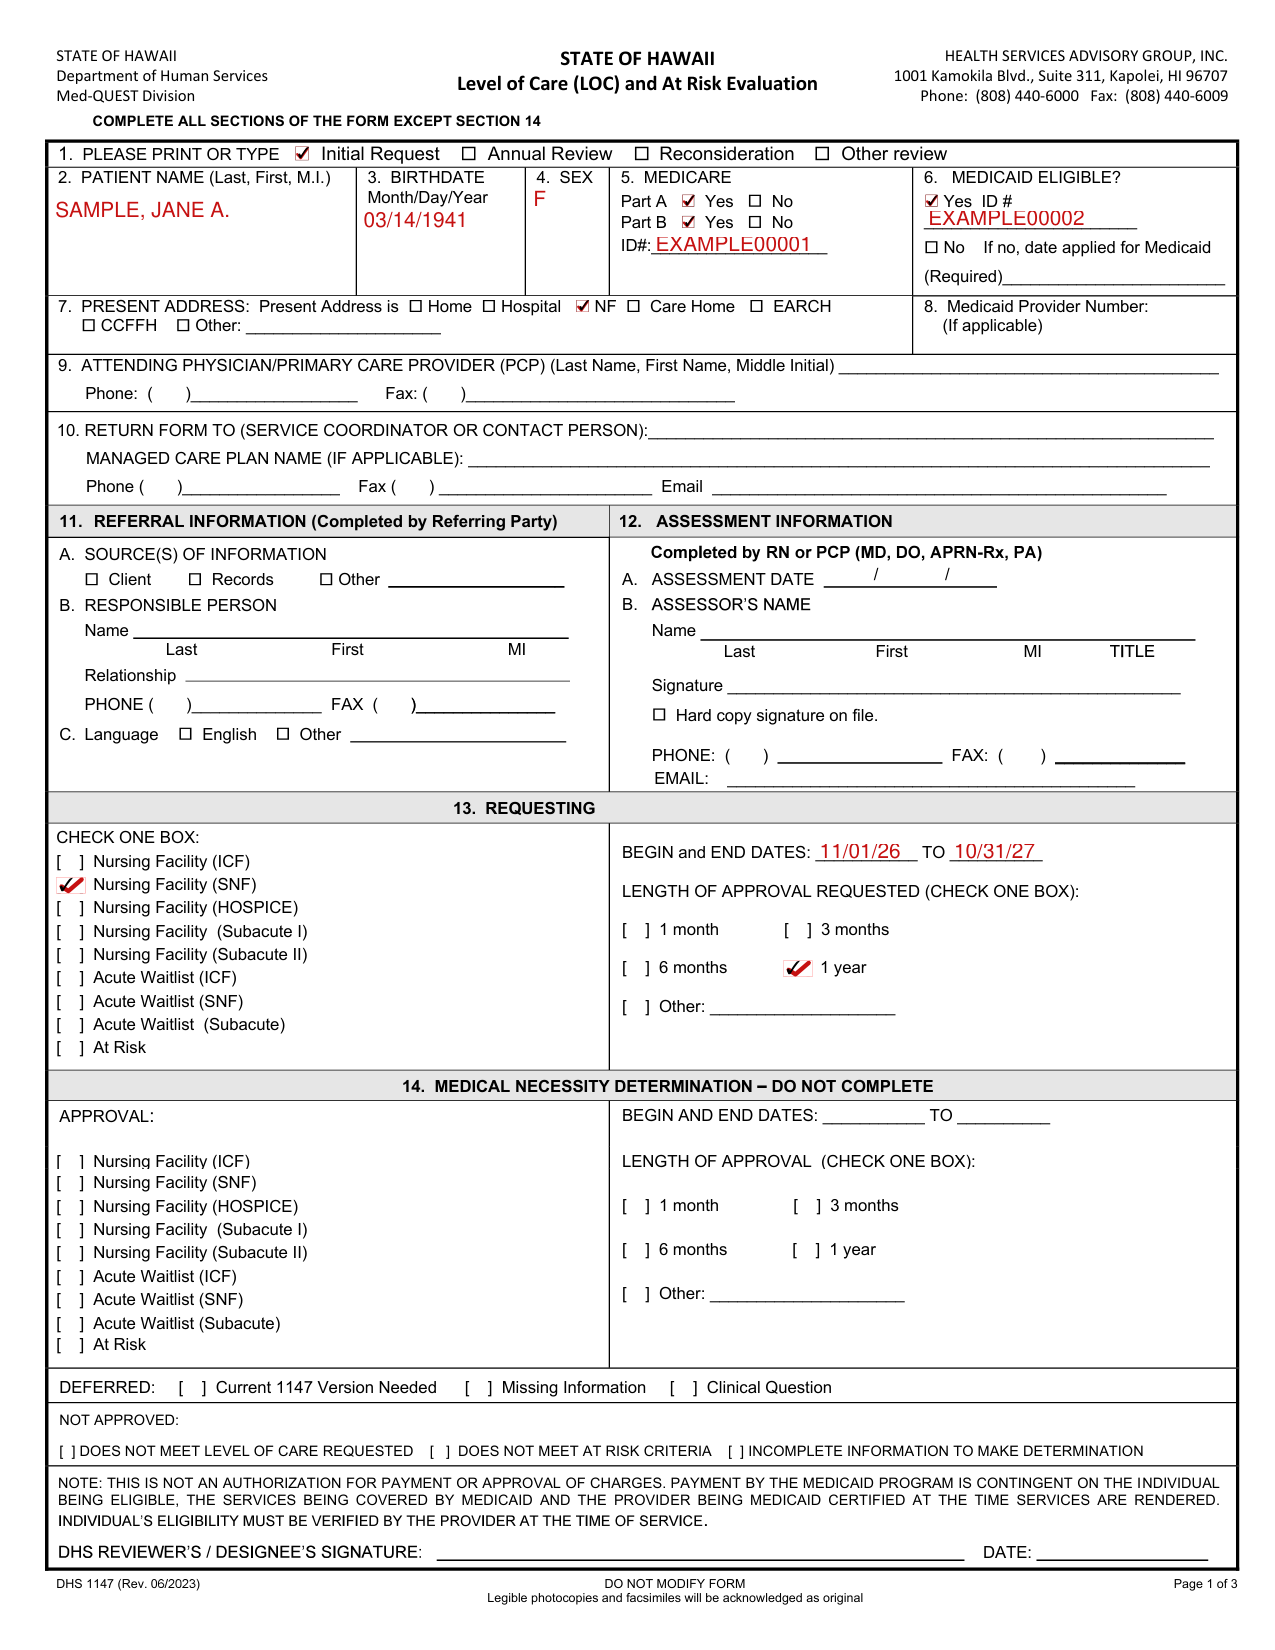
A filled-in Form DHS 1147 example: an initial request for one year of nursing facility care
How to fill out Form DHS 1147, box by box
Sections to complete
Complete all sections of the form except section 14, Medical Necessity Determination. Do not complete section 14.
Request type, patient, Medicare and Medicaid
Please print or type, and check Initial Request, Annual Review, Reconsideration or Other review.
Write the patient name (Last, First, M.I.) and the birthdate (Month/Day/Year).
Write the sex. For Medicare, check Yes or No for Part A and for Part B, and write the ID#.
For Medicaid eligible, check Yes and write the ID #, or check No. If no, the date applied for Medicaid is required.
Present address, provider and physician
For present address, check where the present address is: Home, Hospital, NF, Care Home, EARCH, CCFFH or Other. After Other, write on the line.
Write the Medicaid Provider Number, if applicable.
Write the attending physician or primary care provider (PCP) as Last Name, First Name, Middle Initial, and the Phone and Fax.
Return the form
Write the service coordinator or contact person to return the form to. Write the managed care plan name, if applicable, and the Phone, Fax and Email.
11. Referral information
The referring party completes 11. REFERRAL INFORMATION.
Under A. SOURCE(S) OF INFORMATION, check Client, Records or Other.
Under B. RESPONSIBLE PERSON, write the Name (Last First MI), the Relationship, and the PHONE and FAX.
Under C., check the Language: English or Other.
12. Assessment information
For 12. ASSESSMENT INFORMATION, write the A. ASSESSMENT DATE, the Name (Last First MI), the Signature, and the PHONE, FAX and EMAIL. The form also prints Hard copy signature on file.
13. Requesting
For 13. REQUESTING, check one box. The boxes are Nursing Facility (ICF), Nursing Facility (SNF), Nursing Facility (HOSPICE), Nursing Facility (Subacute I), Nursing Facility (Subacute II), Acute Waitlist (ICF), Acute Waitlist (SNF), Acute Waitlist (Subacute) or At Risk.
Write the begin and end dates.
For length of approval requested, check one box: 1 month, 3 months, 6 months, 1 year, or Other with the line filled in.
Pages 2 and 3: name, birthdate, diagnoses, comatose and total points
On the next two pages, under APPLICANT/CLIENT BACKGROUND INFORMATION (Please Type or Print), write the NAME (Last, First, Middle Initial) and the BIRTHDATE.
Under 3. FUNCTIONAL STATUS RELATED TO HEALTH CONDITIONS, list significant current diagnosis(es) after I., with PRIMARY and SECONDARY.
Check No or Yes for II. COMATOSE; the form points to XVIII, where Comatose = 30 points and the Total Points Indicated is written.
Mental status and mobility
For VI. MENTAL STATUS / BEHAVIOR, mark only one selection for orientation items a through c. Aggressive and/or abusive and wandering may also be checked with appropriate orientation.
Mark Wanders at Day, Night or Both, and/or in danger of self-inflicted harm or self-neglect. Examples are required in section XX: include examples, frequency of occurrences, and interventions for aggressive and/or abusive behaviors, wandering, and/or self-inflicted harm or self-neglect behaviors.
For IX. MOBILITY / AMBULATION, check a maximum of 2 for items b through e (item a is marked [0]). If an individual is either independently mobile or unable to walk, no other selections can be made.
Skilled procedures and therapy
Under XXI. SKILLED PROCEDURES, mark D (Daily) and indicate the number of times per day, L (Less than once per day) or N (Not applicable / Never) for each procedure.
For Total Parenteral Nutrition (TPN), specify the number of hours per day. For IV Therapy, specify the agent and frequency.
For wound care, specify the nature of the wound and care prescribed, and check debridement, irrigation, packing or wound vac.
Check Yes or No for Therapeutic Diet and describe it.
Check Yes or No: the patient is able to participate in therapy a minimum of 45 minutes per session 5 days a week.
Name
Write the Name (PRINT).
More rules for Form DHS 1147
This is not an authorization for payment or approval of charges. Payment by the Medicaid program is contingent on the individual being eligible, the services being covered by Medicaid and the provider being Medicaid certified at the time services are rendered.
Do not modify the form. Legible photocopies and facsimiles will be acknowledged as original.
If your situation is different
The request is At Risk
Complete questions XIV to XVII for At Risk requests only.
Sources
[1] Form DHS 1147, Level of Care (LOC) and At Risk Evaluation, State of Hawaii Department of Human Services Med-QUEST Division (the Official source link on this page).