


Form CMS-1696 at a glance
What it is: Form CMS-1696, Appointment of Representative, is the form that appoints a representative to act on behalf of a person for their claim, appeal, grievance or request.
Who signs: An appointment of a representative is considered valid for one year from the date this form is signed by both the person appointing a representative and the appointed representative.
A filled-in Form CMS-1696 example: a daughter is appointed to act in a Medicare appeal

How to fill out Form CMS-1696, box by box
Section 1: Information about the person appointing the representative
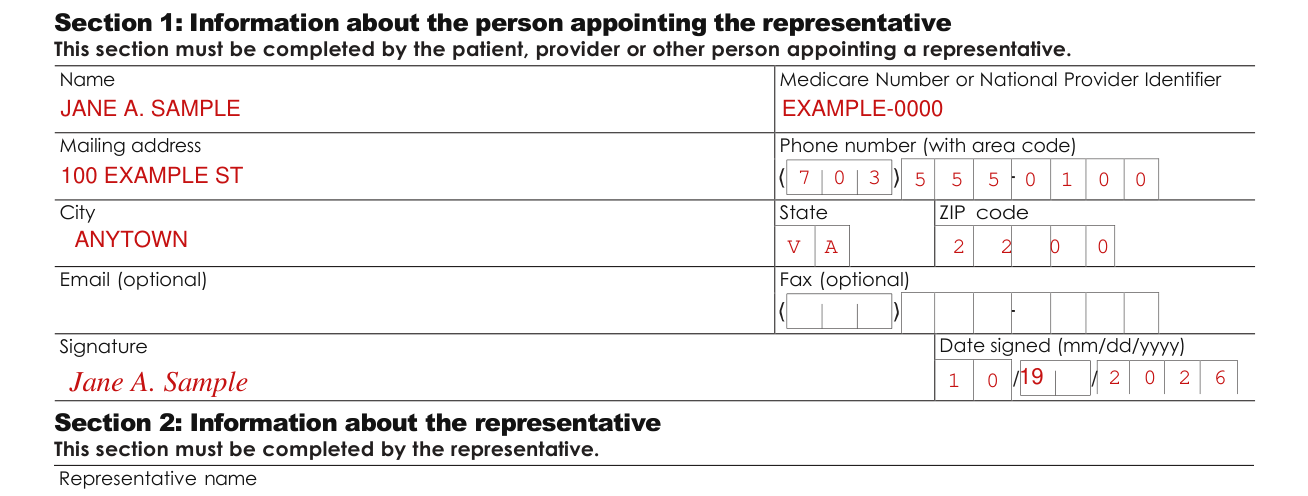
Section 1 must be completed by the patient, provider or other person appointing a representative.
Fill in the Name, Medicare Number or National Provider Identifier, Mailing address, Phone number (with area code), City, State, ZIP code, Email (optional), Fax (optional), Signature and Date signed (mm/dd/yyyy).
If the person or entity appointing a representative doesn't have a Medicare number or National Provider Identifier, fill in "not applicable."
Section 2: Information about the representative
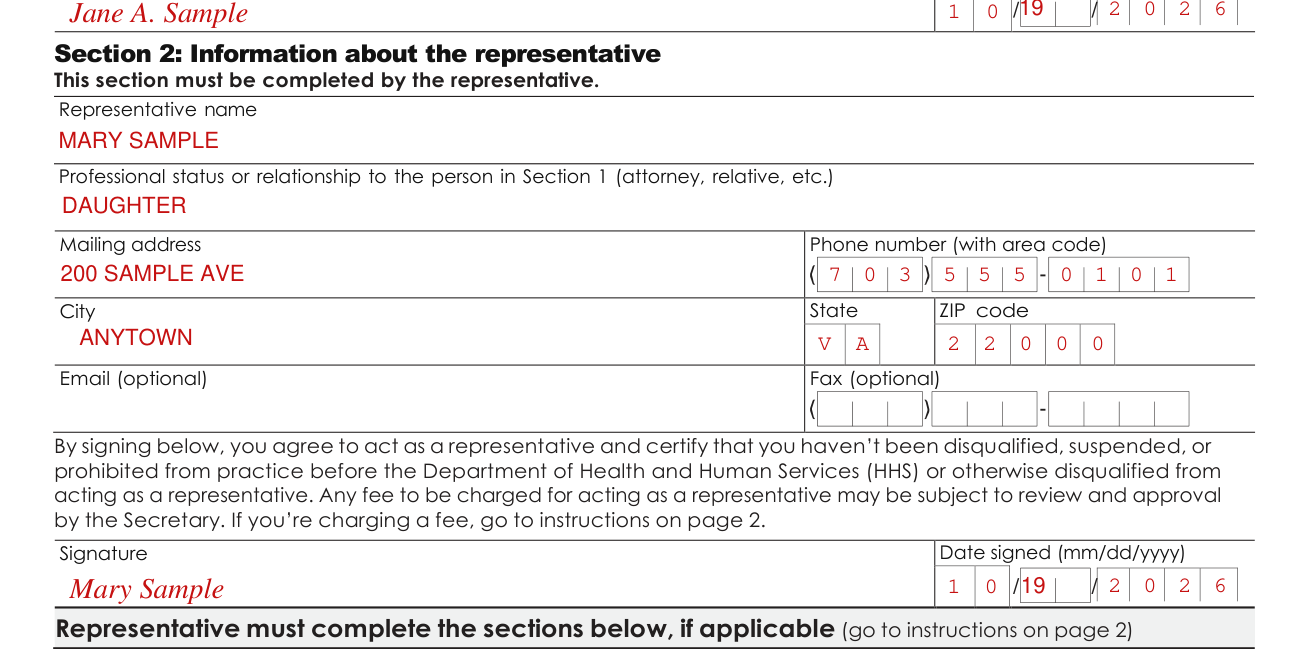
Section 2 must be completed by the representative.
Fill in the Representative name, Professional status or relationship to the person in Section 1 (attorney, relative, etc.), Mailing address, Phone number (with area code), City, State, ZIP code, Email (optional), Fax (optional), Signature and Date signed (mm/dd/yyyy).
By signing in Section 2, you agree to act as a representative and certify that you haven't been disqualified, suspended, or prohibited from practice before the Department of Health and Human Services (HHS) or otherwise disqualified from acting as a representative.
Section 3: Waiver of fee for representation

Section 3 is required when a representative is required, or has agreed, to waive or not charge a fee for their representation (go to the regulation at 42 CFR 405.910).
Representatives are permitted to waive their fee if they choose.
Representatives who choose to waive their fee for representation must also sign Section 3.
Section 3 prints: "I waive my right to charge and collect a fee for representing the person in Section 1 before the Secretary of HHS." Sign it and enter the Date signed (mm/dd/yyyy).
Section 4: Waiver of payment for items or services at issue

Section 4 is required if a provider or supplier who furnished items or services to the patient represents the patient and liability (knowledge of non-coverage) under §1879(a)(2) of the Act is at issue in the appeal.
Section 4 applies if you're a provider or supplier and you furnished items or services to the patient you're representing, if the appeal involves a question of whether you or the patient didn't know, or couldn't reasonably be expected to know, that Medicare wouldn't cover the items or services.
Section 4 prints: "I waive my right to collect payment from the patient for the items or services at issue in this appeal if a determination of liability under §1879(a)(2) of the Act is made." Sign it and enter the Date signed (mm/dd/yyyy).
More rules for Form CMS-1696
A completed form can be used for other appeals or actions during the one-year period it's valid.
Unless revoked, the representation is valid for the duration of the claim, appeal, grievance, or request for which it was filed.
Which situation applies to you
You want to charge a fee for representing a patient
An attorney, or other representative for a patient, who wants to charge a fee for services rendered in connection with an appeal before the Secretary of HHS (i.e., an Administrative Law Judge (ALJ) hearing or attorney adjudicator review by the Office of Medicare Hearings and Appeals (OMHA), Medicare Appeals Council review, or a proceeding before OMHA or the Medicare Appeals Council as a result of a remand from federal district court), is required to have the fee approved in accordance with 42 CFR 405.910(f).
The representative should complete the form OMHA-118, "Petition to Obtain Approval of a Fee for Representing a Beneficiary" and file it with the request for ALJ hearing, OMHA review, or request for Medicare Appeals Council review. Get form OMHA-118 at HHS.gov/sites/default/files/OMHA-118.pdf.
Fee approval is not required if: (1) the appellant being represented is a provider or supplier; (2) the fee is for services rendered in an official capacity such as that of legal guardian, committee, or similar court-appointed representative, and the court approved the fee; (3) the fee is for representing a patient in a proceeding in federal district court; or (4) the fee is for representing a patient in a redetermination or reconsideration.
In approving a requested fee, OMHA or Medicare Appeals Council will consider the nature and type of services rendered, the complexity of the case, the level of skill and competence required, the amount of time spent on the case, the results achieved, the level of administrative review needed, and the amount of the fee requested.
You are a provider or supplier who furnished the items or services
A provider or supplier who furnished the items or services to a Medicare patient that are the subject of the appeal may represent that patient in an appeal, but the provider or supplier may not charge the beneficiary any fee associated with the representation (42 CFR 405.910(f)(3)).
Providers and suppliers who furnished the items or services at issue can't charge a fee for representation and must sign Section 3 to waive their fee.
Conflict of interest
Individuals with a conflict of interest are excluded from serving as representatives of patients before HHS.
Sections 203, 205 and 207 of Title XVIII of the United States Code make it a criminal offense for certain current and former officers and employees of the United States to render certain services in matters affecting the government or to aid or assist in prosecuting claims against the United States.
Before you go
By signing the form and appointing a representative, you agree that the representative will be the main contact and have authority to make requests, present evidence, get information, and receive all communication about your action. The representative may see your personal medical information.
On Form CMS-1696, all fields in Sections 1 and 2 are required unless marked "optional."
Common questions about Form CMS-1696
What is form CMS 1696 used for?
Form CMS-1696, Appointment of Representative, is the form that appoints a representative to act on behalf of a person for their claim, appeal, grievance or request.
Where do I file it?
Send this form to the same location you send your claim, appeal, grievance, or request.
Where to get help with Form CMS-1696
For questions about this form, contact your Medicare plan or call 1-800-MEDICARE (1-800-633-4227).
TTY users call 1-877-486-2048.
Sources
[1] Form CMS-1696, Appointment of Representative, Centers for Medicare and Medicaid Services (the Official source link on this page).