


Form CMS-20027 at a glance
What it is: Form CMS-20027 is the Medicare Redetermination Request Form, the 1st level of appeal.
Who signs: Mark the person appealing as Beneficiary, Provider/Supplier or Representative, and enter an email of the person appealing (optional).
A filled-in Form CMS-20027 example: a supplier appeals a denied claim

How to fill out Form CMS-20027, box by box
Beneficiary, item and dates

Enter the Beneficiary's name (First, Middle, Last), the Medicare number and the item or service you wish to appeal.
Enter the date the service or item was received and the date of the initial determination notice, both as mm/dd/yyyy, and include a copy of the notice with this request.
If you received your initial determination notice more than 120 days ago, include your reason for the late filing.
Overpayment for providers and suppliers only

Does this appeal involve an overpayment? (for providers and suppliers only): mark Yes or No. The name of the Medicare contractor that made the determination is not required.
Why you do not agree and the evidence

Write why you do not agree with the determination decision on your claim, and add any additional information Medicare should consider.
If you have evidence to submit, attach the evidence to this form or attach a statement explaining what you intend to submit and when you intend to submit it; all evidence must be received prior to the issuance of the redetermination. If you have no evidence, mark that you do not have evidence to submit.
Person appealing
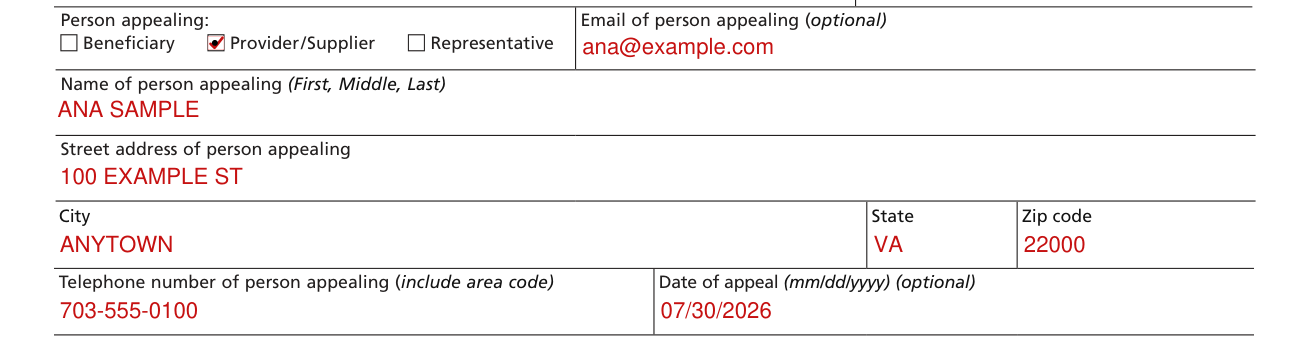
Mark the person appealing as Beneficiary, Provider/Supplier or Representative, and enter an email of the person appealing (optional).
Enter the name of the person appealing (First, Middle, Last), the street address, the city, state and zip code, and the Telephone number of person appealing (include area code); the date of appeal (mm/dd/yyyy) is optional.
Sources
[1] Form CMS-20027 (2/14/2018), Medicare Redetermination Request Form, 1st Level of Appeal, Centers for Medicare & Medicaid Services (the Official source link on this page).