


Form CMS-3427 at a glance
What it is: This form is the End Stage Renal Disease Application and Survey and Certification Report, and Part 1, the application, is to be completed by the facility.
Where and when to file: Upon completion, forward a copy of form CMS-3427 (Part I) to the State agency.
Who signs: Signature of Administrator/Medical Director.
A filled-in Form CMS-3427 example: a new facility applies for Medicare approval

How to fill out Form CMS-3427, box by box
Type of application

Check all that apply for Type of Application/Notification: Initial, Recertification, Relocation, Expansion/change of services, Change of ownership or Other, specify; if Other, specify in the Remarks section [Item 33].
Type of Application (Item 1): check appropriate category. A change of service refers to an addition or deletion of services. Expansion refers to addition of stations.
If you relocate one of your services to a different physical location, you may be required to obtain a separate CCN for that service at the new location.
Facility name and address
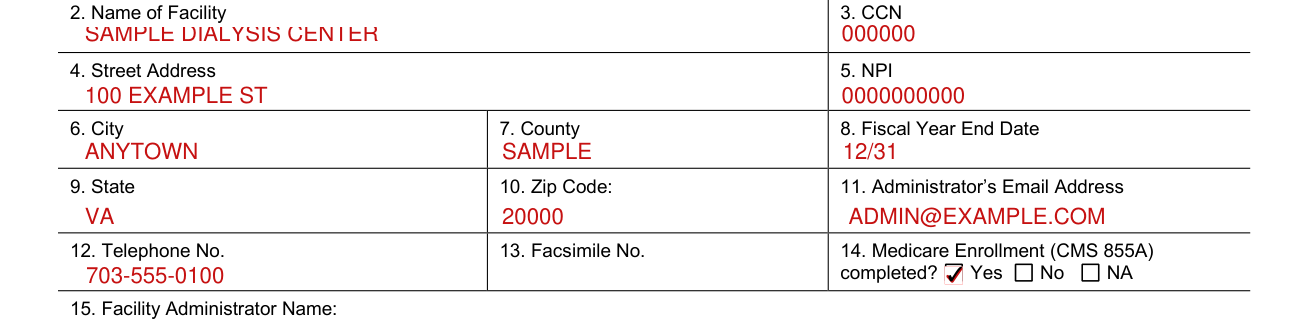
Enter the Name of Facility and CCN, the Street Address and NPI, the City, County and Fiscal Year End Date, then the State, Zip Code and Administrator's Email Address.
Enter the Telephone No. and Facsimile No., and mark Yes, No or NA: Medicare Enrollment (CMS 855A) completed?
Identifying information (Items 2-24): enter the name and address (actual physical location) of the ESRD facility where the services are performed. If the mailing address is different, show the mailing address in Remarks (Item 33).
Facility administrator

For the Facility Administrator, enter the Name, then the Address, City, State, Zip Code and Telephone No.
Ownership, hospital and SNF/NF

For Ownership, mark 1. For Profit, 2. Not for Profit or 3. Public. Then mark 1. Yes or 2. No: Is this facility owned and managed by a hospital and on the hospital campus (i.e., hospital-based)?
Mark 1. Yes or 2. No: Is this facility owned and managed by a hospital and located off the hospital campus (i.e., satellite)? Mark 1. Yes or 2. No: Is this facility not owned or managed by a hospital (i.e., independent)?
Check one, 1. Yes or 2. No: Is this facility located in a SNF/NF? If Yes, enter the SNF/NF name and CCN.
For a multi-facility organization, mark 1. No, 2. Yes, Owned or 3. Yes, Managed. If Yes, enter the name of the multi-facility organization and the Multi-facility organization's address.
Services, patients and stations
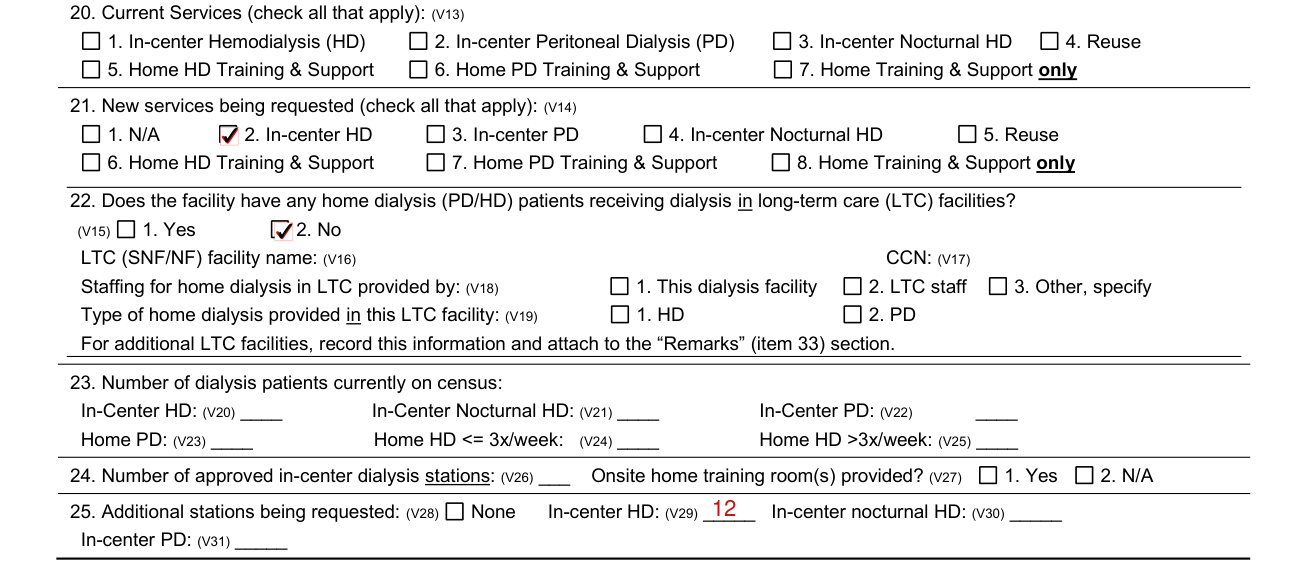
For Current Services, check all that apply: 1. In-center Hemodialysis (HD), 2. In-center Peritoneal Dialysis (PD), 3. In-center Nocturnal HD, 4. Reuse, 5. Home HD Training & Support, 6. Home PD Training & Support or 7. Home Training & Support only.
For New services being requested, check all that apply: 1. N/A, 2. In-center HD, 3. In-center PD, 4. In-center Nocturnal HD, 5. Reuse, 6. Home HD Training & Support, 7. Home PD Training & Support or 8. Home Training & Support only.
Check N/A or each New service for which you are requesting approval (Item 21). Note that facilities providing home therapies must provide both training and support.
If you are requesting to offer home training and support only (Item 21), you must have a functional plan/arrangement to provide backup dialysis as needed. A new home training and support only service applies to initial applications.
If you request any home training and support program (Item 21), you must also indicate Yes for a training room (Item 24).
Mark 1. Yes or 2. No: Does the facility have any home dialysis (PD/HD) patients receiving dialysis in long-term care (LTC) facilities? If Yes, enter the LTC (SNF/NF) facility name and CCN.
For Number of dialysis patients currently on census, enter the number for In-Center HD, In-Center Nocturnal HD, In-Center PD, Home PD, Home HD <= 3x/week and Home HD >3x/week.
Enter the Number of approved in-center dialysis stations, and mark 1. Yes or 2. N/A: Onsite home training room(s) provided?
For Additional stations being requested, check None or enter the number for In-center HD, In-center nocturnal HD and In-center PD.
Enter the number of stations for which you are asking approval (Item 25).
Isolation, shifts and reprocessing
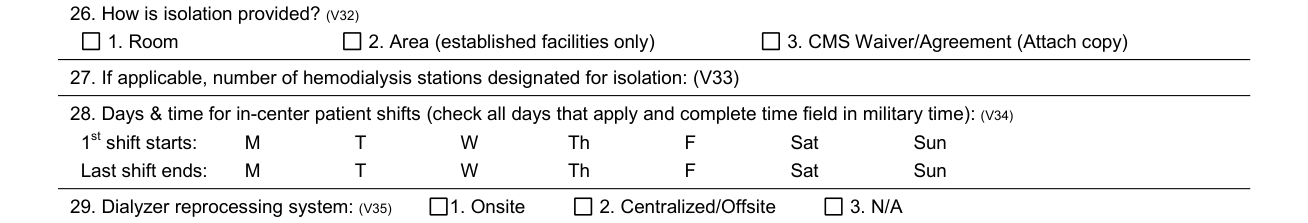
Mark how isolation is provided: 1. Room, 2. Area (established facilities only) or 3. CMS Waiver/Agreement (Attach copy). If applicable, enter the number of hemodialysis stations designated for isolation.
Provide information on isolation (Items 26-27). Facilities not existing prior to October 14, 2008 which do not have an isolation room must attach evidence of CMS waiver and written agreement with geographically proximal facility with isolation room.
Check all days that apply and complete the time field in military time for the 1st shift starts and the Last shift ends, for M, T, W, Th, F, Sat and Sun.
Provide all days and start time for the first shift of patients and end time for the last shift of patients (in military time) for each day of operation (Item 28).
For the Dialyzer reprocessing system, mark 1. Onsite, 2. Centralized/Offsite or 3. N/A.
Staff, license and remarks

Staff (List full-time equivalents): enter Registered Nurse, Certified Patient Care Technician, LPN/LVN, Technical Staff (water, machine), Registered Dietitian, Masters Social Worker and Others.
Other includes non-certified patient care technicians, administrative personnel, etc. To calculate the number of full-time equivalents of any discipline (Item 30), add the total number of hours that all members of that discipline work at this facility and enter that number in the numerator. Enter into the denominator the number of hours that facility policy defines as full-time work for that discipline. Report FTEs in 0.25 increments only.
Enter the State license number (if applicable), and mark 1. Yes, 2. No or 3. NA: Certificate of Need required?
If your state requires licensing for ESRD facilities, include your current license number in Item 31. If your state requires a Certificate of Need (CON) for an initial ESRD or for the change you are requesting, mark the applicable box in Item 32 and include a copy of the documentation of the CON approval.
Remarks (Item 33): copy if more and attach additional pages if needed. You may use this block for explanatory statements related to Items 1-32.
Signature

The information contained in this Application Survey and Certification Report (Part I) is true and correct to the best of my knowledge. Incorrect or erroneous statements may cause the request for approval to be denied, or facility approval to be rescinded, under 42 C.F.R. 494.1 and 488.604 respectively.
Sign I have reviewed this form and it is accurate on the line, then enter the Title and the Date.
More rules for Form CMS-3427
Part II is the Survey and Certification Report to be completed by State agency.
Common questions about Form CMS-3427
What does ESRD stand for?
Part 1 documentation needed to process a facility application (Form CMS-3427, Revision 05/13): a completed request for approval as a supplier of End Stage Renal Disease (ESRD) services in the Medicare program (Part I - Form CMS-3427) must include a narrative statement describing the need for the service(s) to be provided, and a copy of the Certificate of Need approval, if such approval is required by the state.
Sources
[1] Form CMS-3427 (Revision 05/13), End Stage Renal Disease Application and Survey and Certification Report, Centers for Medicare & Medicaid Services (the Official source link on this page).