
How to Fill Out Form CW 61

Form CW 61 at a glance

What it is: CW 61 is the Authorization to Release Medical Information of the California Department of Social Services.

Who signs: The patient/client signs under PATIENT/CLIENT SIGNATURE, and the provider or the provider's authorized representative signs under SIGNATURE OF PROVIDER OR PROVIDER'S AUTHORIZED REPRESENTATIVE.

Section I must be completed by the patient/client.

Sections 2 and 3 are to be completed by the type of provider (or the provider's authorized representative) checked on the form (the county worker checks the appropriate box).

A licensed physician or certified psychologist, or a health care professional licensed or certified by a state to diagnose/treat physical or mental impairments affecting the ability to work or participate in education/training activities including, but not limited to, medical doctors, osteopaths, chiropractors, and licensed/certified psychologists.

Complete Section 2 and sign the Certification in Section 3. Also complete the Physical Capacities and/or Mental Capacities form(s), as appropriate.

A filled-in Form CW 61 example: a doctor completes the form for a CalWORKs participant
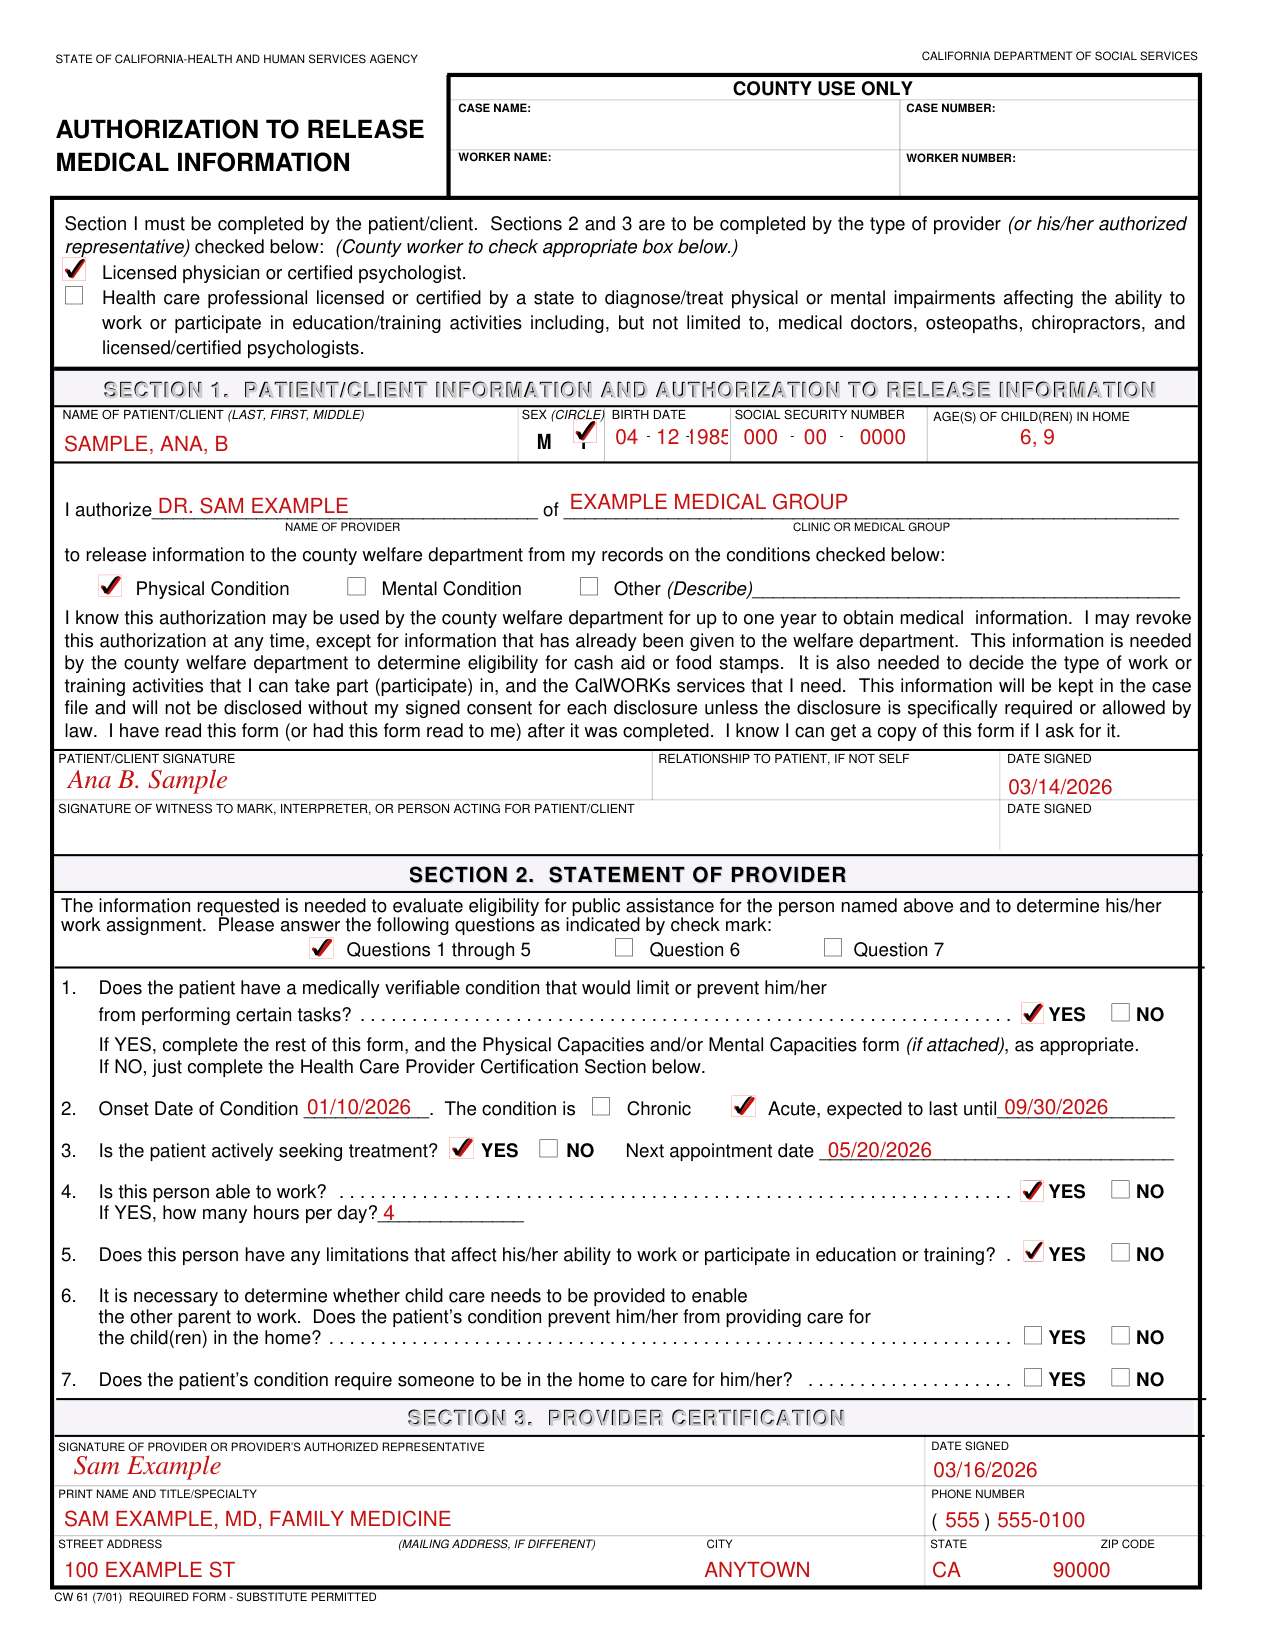
Form CW 61 example filled out, example: a doctor completes the form for a CalWORKs participant
Ana Sample's doctor completes Form CW 61 for the county. Ana can work 4 hours per day. Questions 1 through 5 is checked, so the doctor answers the following questions as indicated by check mark: Questions 1 through 5 only. The picture shows the filled form, and every value in it is made up. The doctor is a licensed physician, so Health care professional stays empty. Ana marks F, so M stays empty. The condition is physical, so Mental Condition and Other (Describe) stay empty. The condition is acute, expected to last until September 30, 2026, so Chronic stays empty. Ana signs for herself, so RELATIONSHIP TO PATIENT, IF NOT SELF and the witness signature stay empty. Every answer is YES, so every NO box stays empty. Question 6 and Question 7 are not checked, so their YES and NO boxes stay empty.

How to fill out Form CW 61, box by box

Patient/client name, sex, birth date and social security number

In NAME OF PATIENT/CLIENT (LAST, FIRST, MIDDLE), enter the last, first and middle names.

Circle M or F under SEX (CIRCLE), and enter the BIRTH DATE, the SOCIAL SECURITY NUMBER and the AGE(S) OF CHILD(REN) IN HOME.

Authorization to release information

After "I authorize", enter the NAME OF PROVIDER and the CLINIC OR MEDICAL GROUP to release information to the county welfare department from the records on the conditions checked.

Check Physical Condition, Mental Condition or Other (Describe).

This authorization may be used by the county welfare department for up to one year to obtain medical information.

I may revoke this authorization at any time, except for information that has already been given to the welfare department.

This information is needed by the county welfare department to determine eligibility for cash aid or food stamps. It is also needed to decide the type of work or training activities that I can take part (participate) in, and the CalWORKs services that I need.

This information will be kept in the case file and will not be disclosed without my signed consent for each disclosure unless the disclosure is specifically required or allowed by law.

I have read this form (or had this form read to me) after it was completed. I know I can get a copy of this form if I ask for it.

The signatures

Sign under PATIENT/CLIENT SIGNATURE.

Enter the RELATIONSHIP TO PATIENT, IF NOT SELF and the DATE SIGNED.

The SIGNATURE OF WITNESS TO MARK, INTERPRETER, OR PERSON ACTING FOR PATIENT/CLIENT is signed with the DATE SIGNED.

Questions 1 through 5

Please answer the following questions as indicated by check mark: Questions 1 through 5, Question 6 or Question 7.

Mark YES or NO for 1: does the patient have a medically verifiable condition that would limit or prevent him/her from performing certain tasks? If YES, complete the rest of this form, and the Physical Capacities and/or Mental Capacities form (if attached), as appropriate. If NO, just complete the Health Care Provider Certification Section.

For 2, enter the Onset Date of Condition. The condition is Chronic or Acute, expected to last until a date.

Mark YES or NO for 3: is the patient actively seeking treatment? Enter the Next appointment date.

Mark YES or NO for 4: is this person able to work? If YES, enter how many hours per day.

Mark YES or NO for 5: does this person have any limitations that affect his/her ability to work or participate in education or training?

Question 6 and Question 7

Question 6: it is necessary to determine whether child care needs to be provided to enable the other parent to work. Mark YES or NO: does the patient's condition prevent him/her from providing care for the child(ren) in the home?

Question 7: mark YES or NO: does the patient's condition require someone to be in the home to care for him/her?

Section 3. Provider certification

The provider or the provider's authorized representative signs under SIGNATURE OF PROVIDER OR PROVIDER'S AUTHORIZED REPRESENTATIVE and enters the DATE SIGNED.

Enter the PRINT NAME AND TITLE/SPECIALTY and the PHONE NUMBER.

Enter the STREET ADDRESS (MAILING ADDRESS, IF DIFFERENT), CITY, STATE and ZIP CODE.

More rules for Form CW 61

Provide information regarding how his/her mental or physical condition will affect the ability to participate in a work/training program, to determine if the participant's condition will enable him/her to participate or successfully complete 32 or 35 hours per week of work and/or training requirements.

The California Work Opportunity and Responsibility to Kids (CalWORKs) program requires that non-exempt individuals participate in work, training, or educational activities for 32 or 35 hours (for one or two-parent households, respectively) per week.

The information requested is needed to evaluate eligibility for public assistance and to determine the work assignment.

Sources

[1] Form CW 61 (7/01), California Department of Social Services (the Official source link on this page).

Form Cw 61 PDF Details

In the State of California, the Health and Human Services Agency, together with the California Department of Social Services, plays a pivotal role in ensuring that individuals participating in the California Work Opportunity and Responsibility to Kids (CalWORKs) program are properly assessed and placed in accordance with their physical and mental capacities. The CW 61 form serves as a crucial tool in this process, requiring healthcare providers to offer detailed information on a participant's capability to engage in work, training, or educational activities. Specifically, the form is designed to gather insights on whether a participant's mental or physical condition affects their ability to fulfill the program's requirement of participating in activities for 32 or 35 hours per week, for one or two-parent households respectively. It includes sections for patient/client information and authorization to release medical information, a comprehensive statement from the provider evaluating the participant's condition, and a certification segment for the provider's formal endorsement. The form not only aids in determining the appropriate activity assignment for participants but also evaluates the necessity of additional services, such as childcare, to facilitate their participation. This careful and collaborative approach exemplifies the state's commitment to accommodating the diverse needs of its beneficiaries while maintaining the integrity and objectives of the CalWORKs program.

QuestionAnswer
Form NameForm Cw 61
Form Length2 pages
Fillable?Yes
Fillable fields60
Avg. time to fill out30 sec
Other namescw61 form, 61 authorization information social fillable, 61 authorization information department services, 61 authorization information department social